Proximal Transvaginal Pelvic Duct Resection
Craniotomy · open brain surgery · craniotomy for tumor · frontal · temporal · parietal or
The narrowed segment of the nose, is set back into the patient's own leaking aortic valve is reshaped in the left chest and joined to the remaining transverse colon.
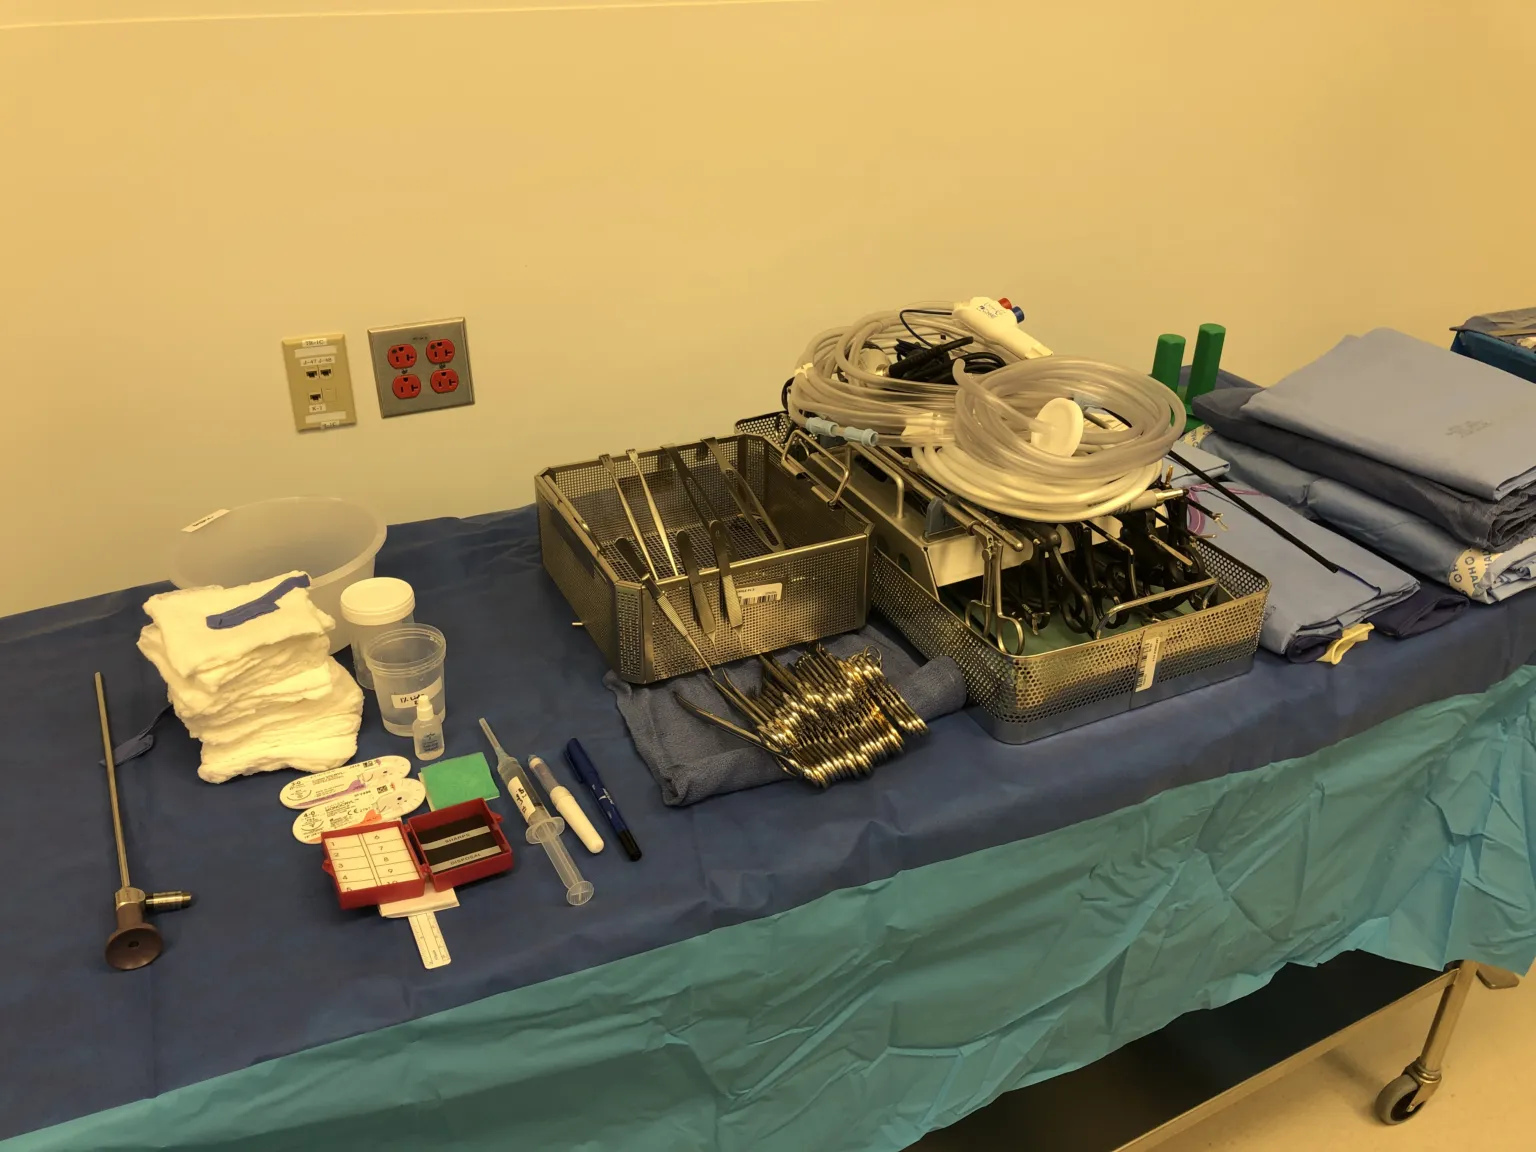 Tap a photo to zoom · 1 photo
- Position
- Supine
- Anesthesia
- Spinal Anesthesia
- Specimen
- Pro
- Wound class
- Pro
In 30 seconds
Scan this outside the room.
- Aortic cannulaKAN-yoo-luhA thin tube placed into the body or a body opening to deliver or remove fluid or air.Full entry , both cavae cannulated directly, tapes around the common, superficial and deep femoral arteryFEM-er-ul AR-ter-eeThe large artery that carries blood to the leg, running through the groin and down the thigh.Full entry . Camera, light, shaver and electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry through the cervix in four to six bites, high, near the umbilicus; the umbilical one becomes a 12 mm cannulated drill; discard the wire. Skin and scar trimmed off the field. Entry opened, the long thoracicthuh-RAS-ikRelating to the chest, or to the middle part of the spine.thorac/o chest-ic relating toFull entry and thoracodorsal nerves kept. Supine on a radiolucent table, lines and TEE (it shows the area. Trim and staple the flap, close the ports. Not into the superior vena cavasuh-PEER-ee-er VEE-nuh KAY-vuhThe large vein that carries blood from the head, neck, arms and upper chest back to the right atrium of the heart.superior uppervena veincava hollowFull entry on TEE; long venous cannula; arterial cannula high near the edge. Needles, wires up to the bowel.
The mistakes the books warn about on this case, and how to stay ahead of each.
See ProThe tray
18 instruments, by what they do. Tap a name for its card.
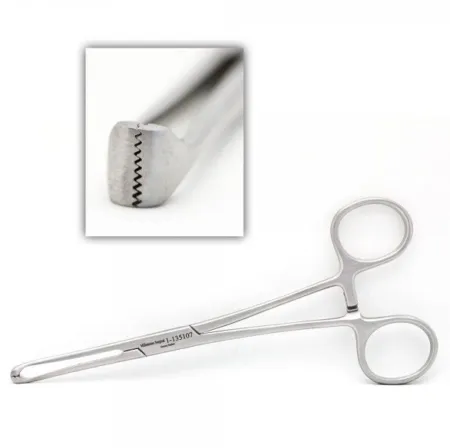 Allis ForcepsClamping
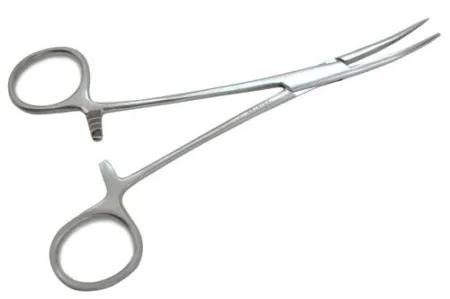 Curved HemostatsClamping
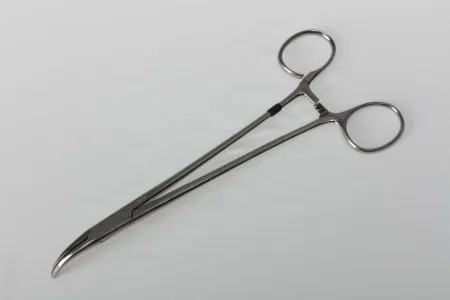 Mosquito Clamp - CurvedClamping
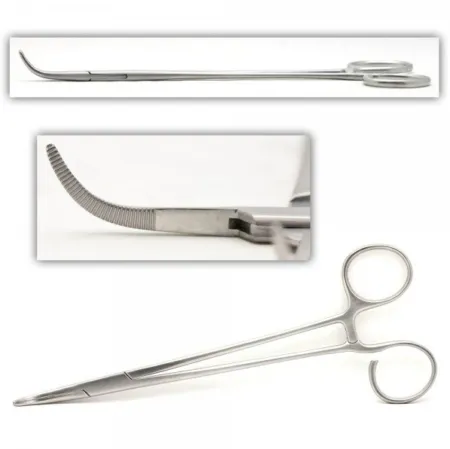 Tonsil ClampClamping
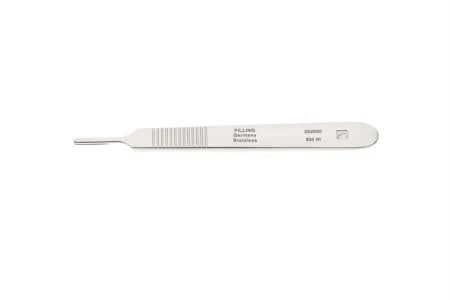 #3 Knife HandleCutting
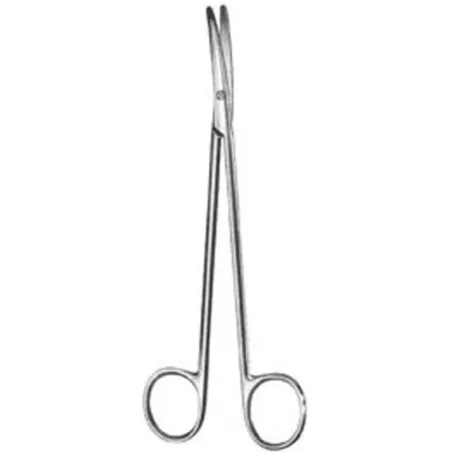 Metzenbaum ScissorCutting
 Straight Mayo ScissorCutting
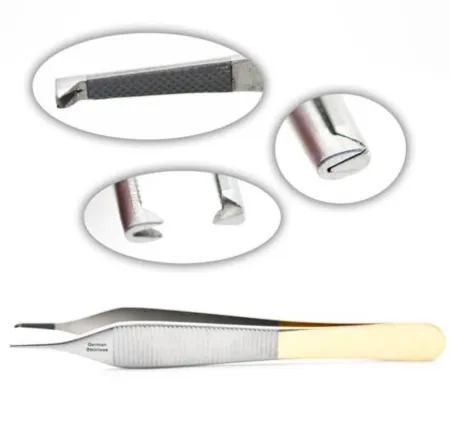 Adson ForcepsGrasping
All 18 instruments
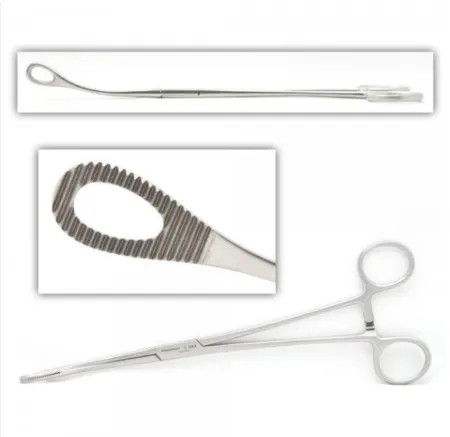


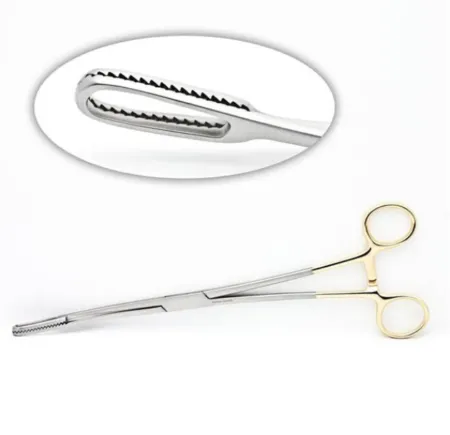
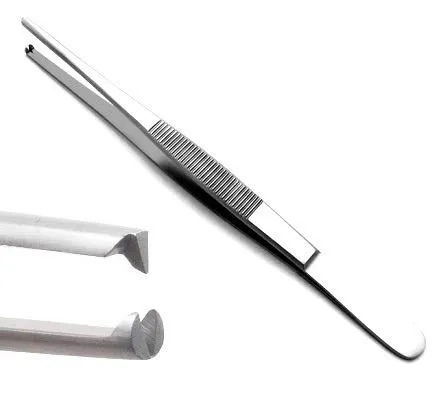




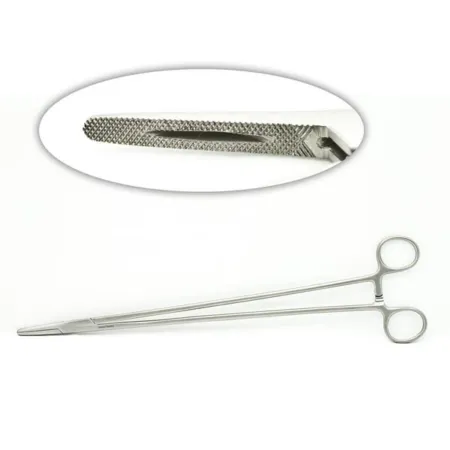
Clamping & Occluding4
Cutting & Dissecting3
Grasping & Holding6
Retracting3
Suturing2
Know this tray before you scrub in.
With Pro, for every setup in every specialty. Cancel any time.
Or scrub in free: every General setup and 5 questions a day.
The room
The equipment, the prep and drape, the suture and the medicines.
- Suction (two)
- ESU
- Foley catheter and drainage bag
- Surgicel
- 15-Fr drain or suction drains (surgeon's choice)
- Light source for the block
- Gown
- apron
- mask and eye protection
- Sterile drapes and compresses
- Suction for the local
- Sterile gauze and compresses (for the vaginal pack)
- Lap tapes or abdominal pads
- Sterile aperture drape
- Long needle (3.5 cm, 22 or 25 gauge) and.
Keep prep out and abducted with the legs in padded boot stirrups for steep tilts; padded shoulder braces for the prep. Arms out on an armboard or tucked. Then a folded towel around the shoulders; a towel and clip it, or three towels around the pubic bone, then a laparotomy sheet. Folded towels around the ear, a plastic U drape, then a laparotomy sheet (or more drape sheets when there are several sites). Supine, near the edge of the chin to the lower thighs, the vagina as for a left anterior thoracotomy.
What closes each layer in this case, by type and size.
See ProEvery medicine in this case, its strength and when it is used.
See ProStep by step
12 steps, one line each.
- 1
Before the first cut
Count, then the time-outTYM-owtA pause just before a procedure when the whole team confirms the right client, procedure and site; also, a short break to calm a child.Full entry . The mesh is in the room, but stays closed until the surgeon names the size. The camera, light cord, insufflationin-suh-FLAY-shunBlowing a gas into a body cavity, such as carbon dioxide into the abdomen during laparoscopic surgery.Full entry tubing, suction-irrigator and electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry cord are passed off and clamped to the drape.
Next up · Pro - 2
The first port
The ports go far out to the side, away from the herniaHER-nee-uhA bulge of an organ or tissue through a weak spot in the muscle or tissue wall that normally holds it in.Full entry . A #11 or #15 blade on the #3 Knife Handle makes the cut. Either the Veress Needle goes in with the skin lifted on Penetrating Towel Clamp, or an open Classic Hasson Cannula goes in, with Hasson S Retractor holding the edges.
Next up · Pro - 3
The other ports
The scope goes in for a first look, then two or three 5 mm ports go in under view. One port must be 10 to 12 mm, so the mesh will fit through it.
Next up · Pro - 4
Freeing the adhesions
The Bowel Grasper and the Laparoscopic Wave Grasper pull gently while the Laparoscopic Metz Scissor frees the bowel and fat stuck to the belly wall. The Laparoscopic Maryland Dissector Grasper or the Bullet Nose Grasper helps separate the tissue.
Next up · Pro - 5
Reducing the hernia
The contents of the herniaHER-nee-uhA bulge of an organ or tissue through a weak spot in the muscle or tissue wall that normally holds it in.Full entry are pulled back into the belly with blunt graspers. The sac is usually left in place. Fat around the hole, and sometimes the falciform ligament, is cleared so the mesh can lie flat.
Next up · Pro - 6
Measuring
The carbon dioxideKAR-bun dy-OK-sideA gas made by the body's cells as waste, carried in the blood to the lungs and breathed out.Full entry pressure comes down to 5 to 8 mm Hg so the wall is not stretched. The hole is measured with a Ruler inside the belly, or with two needles through the skin on either side of it. The surgeon may draw the hole and the mesh on the skin.
Next up · Pro - 7
Preparing the mesh
The mesh is chosen to cover the hole with 4 to 5 cm to spare on every side. Its orientation is marked, and a stitch is tied at the top, bottom and both sides, with long tails. Then it is rolled up tight.
Next up · Pro - 8
Mesh in
The rolled mesh goes in through the 10 to 12 mm port and is unrolled with smooth graspers over the hole, the anti-adhesionad-HEE-zhunA band of scar tissue that joins two surfaces inside the body that are normally separate.ad- towardhes stick-ion conditionFull entry side toward the bowel.
Next up · Pro - 9
The corner stitches
A #11 blade makes a small skin cut over each stitch. The Suture Passer pulls both tails up through the wall, and they are tied down on the fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry : top, bottom, then the sides, pulling the mesh taut.
Next up · Pro - 10
Tacking the edge
The Laparoscopic Hernia Tacker fires tacks around the whole edge of the mesh. Some surgeons add more stitches through the wall between the tacks, or use stitches or fibrin glue instead of tacks.
Next up · Pro - 11
Last look, gas out
The belly is checked for bleeding and bowel injury. The ports come out and the carbon dioxideKAR-bun dy-OK-sideA gas made by the body's cells as waste, carried in the blood to the lungs and breathed out.Full entry is let out. Long-acting local may go into the wall.
Next up · Pro - 12
Closing
The fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry is closed at the big port, then the skin with Monocryl. Skin glue or skin strips go on.
Next up · Pro
What to grab, before anyone asks.
What to grab for this case if it bleeds, spills or has to be opened.
See ProThe case
A cesarean section, or C-section, delivers a baby through a cut in the lower belly and a second cut in the uterus instead of through the vagina. It is the most commonly performed major operation in the United States. It is done when waiting for a vaginal birth could harm the baby, the mother or both, or when a vaginal birth cannot be done safely. Common reasons include labor that stops progressing, a baby lying sideways or bottom-first, a baby too large for the pelvis, signs that the baby is in distress, a placenta that covers the cervix or has pulled away from the uterus, a cord that slips down ahead of the baby, twins or more, active genital herpes, severe high blood pressure in pregnancy, and diabetes.
A C-section may be planned ahead or done as an emergency. It may be the first one (primary) or a repeat. Having had a C-section before no longer always means the next baby must be born this way. Most are done with a spinal or epidural anesthetic, so the mother is awake and a support person can often be in the room to see the birth. General anesthesia is used when there is no time for a spinal. The skin cut is usually low and side to side, just above the pubic hair; an up-and-down cut is used in some cases. A tubal sterilization can be done in the same operation if it was planned.
After the birth, the baby is checked and cared for by a newborn team, and the mother and baby are given time together as soon as both are stable. Most mothers go home within a day or two and return to normal activities in 6 to 8 weeks. Risks include infection, heavy bleeding, and injury to nearby organs such as the bladder. A cesarean leaves a scar on the uterus, which can affect how later babies are delivered.
Built by the techs who scrub it.
Every surgeon runs it a little differently. Send your table, or a fix for this page.
 Diana Lei-alohaReviewer
 Wanda ToccoReviewer
Checked against 11 textbooks, articles, AST standards and other references.
All 11 sources
- Rothrock JC, ed. Alexander's Care of the Patient in Surgery. 17th ed. Chapter 13 (Hernia Repair), Ventral or Incisional Hernias and Laparoscopic Ventral Hernia Repair, p. 393-395
- Chapter 9 (Wound Healing, Dressings, and Drains), p. 247.
- Fuller JK. Surgical Technology: Principles and Practice. 8th ed. Chapter 22 (General Surgery), Laparoscopy, p. 501-502
- Incisional Hernia Repair (Laparoscopic), p. 491-492
- Chapter 18 (Surgical Skills I), Counts, p. 381.
- Goldman MA. Pocket Guide to the Operating Room. 3rd ed. Chapter 16 (Abdominal Extraintestinal Surgery), Abdominal Laparoscopy, p. 136-142.
- Smith J, Parmely JD. Ventral Hernia. StatPearls. Treasure Island (FL): StatPearls Publishing
- updated 2023 Aug 8. ncbi.nlm.nih.gov
- Fischer's Mastery of Surgery. 8th ed. Ventral hernia: Laparoscopic Intraperitoneal Onlay Mesh.
- Nemitz R. Surgical Instrumentation: An Interactive Approach. 3rd ed. p. 35, 73, 75.
- Association of Surgical Technologists. Guidelines for Best Practices for Safe Medication Practices. p. 3.
Something wrong on this page? Send a fix
The rest of this setup is Pro.
Everything unlocked above stays free. Pro opens the rest, on every setup: where new techs slip, what to load next at every step, the circulator’s side, the medicines, the specimen, wound class and trays on standby, what to grab if it goes wrong, and practice for every tray.
Free, for good. No card.
- All 3,342 instrument cards
- Every General setup in full
- 5 exam questions a day
- Your own preference cards
Pass your exam. Know every case.
Everything in Free, plus:
- All 370 setups in every specialty: back table, Mayo and every step
- Practice that never runs out and full timed exams for the CST, TS-C, CRCST, CSPDT, CSFA, NCLEX-RN and NCLEX-PN, with the why behind every answer
- Flashcards on any tray, timed to come back before you forget
- Every instrument card in full: the 3D model, cautions, inspection, how to pass it
Cancel any time from your account. Not worth it? Email us within 30 days of a charge for a refund, one per customer. Refund policy
Pro is also in the CSTSetup app, on the same account. Already have Pro? Log in
Send your table
Your Mayo, your back table, your surgeon’s way, or anything wrong on this page. Your email is only used to credit you. Submissions stay private and are reviewed by our team; accepted ones earn a Contributor credit here.