Eye surgery
Cataracts, the cornea, glaucoma, the retina, eye muscles, eyelids and tear ducts: tiny instruments under the microscope, drugs that look alike, and an awake patient who hears every word.
1What eye surgery covers
Eye surgery aims to bring back sight lost to disease, injury or a defect present from birth. It works on the outside of the eye, such as the lids, the tear ducts and the eye muscles, and on the inside, such as the lens, the corneaKOR-nee-uhThe clear, dome-shaped layer at the front of the eye, over the iris and pupil.Full entry and the retinaRET-ih-nuhThe thin layer of light-sensing tissue at the back of the inside of the eye.Full entry . It is done in hospitals and in outpatient centers, and cataractKAT-uh-raktClouding of the lens of the eye.Full entry surgery is the operation done most often in ambulateAM-byuh-laytTo walk, or to help a client walk.Full entry surgery in the United States.
The surgeon is an ophthalmologist. Some focus on one area: children's eye problems, the cornea, the retina, or oculoplastics, the blend of plastic surgery and eye surgery that treats the lids, tear ducts and orbit. Many eye surgeons hire their own surgical technologistSUR-jih-kul tek-NOL-uh-jistA member of the operating room team who prepares the sterile field and instruments and hands them to the surgeon.Full entry , and ophthalmicoff-THAL-mikHaving to do with the eye, or describing a medicine made to be put in the eye.ophthalm/o eye-ic relating toFull entry surgical technologists may work in the eye clinic as well as the OR.
Eye operations are small, but they are not minor. Even a slight jar of an instrument touching the eye can injure it, the patient is often awake, and the number of cases is high. You learn to work in tiny detail, keep a steady hand and speak clearly to the surgeon.
The Core Curriculum groups eye operations by the part of the eye they treat: the conjunctivakon-junk-TY-vuhThe thin, clear layer that lines the inside of the eyelids and covers the white of the eye.Full entry , cornea and iris; the eyelid; the globe; the lens; the muscles; the retina; and the tear duct. Cases that share instruments, supplies, positions and steps are co-related procedures, so learn the pattern once and each case becomes a new middle. Each case below links to its setup card, which holds the full instrument list and every step; here you get the reasons, and the moments when the scrub matters most.
The Core Curriculum lists every eye operation under the open approach, and for cataract surgery it adds a laser-assisted form. A dacryocystorhinostomy can also be done endoscopically, through the nose, usually by an ear, nose and throat surgeon.
2The eye in brief
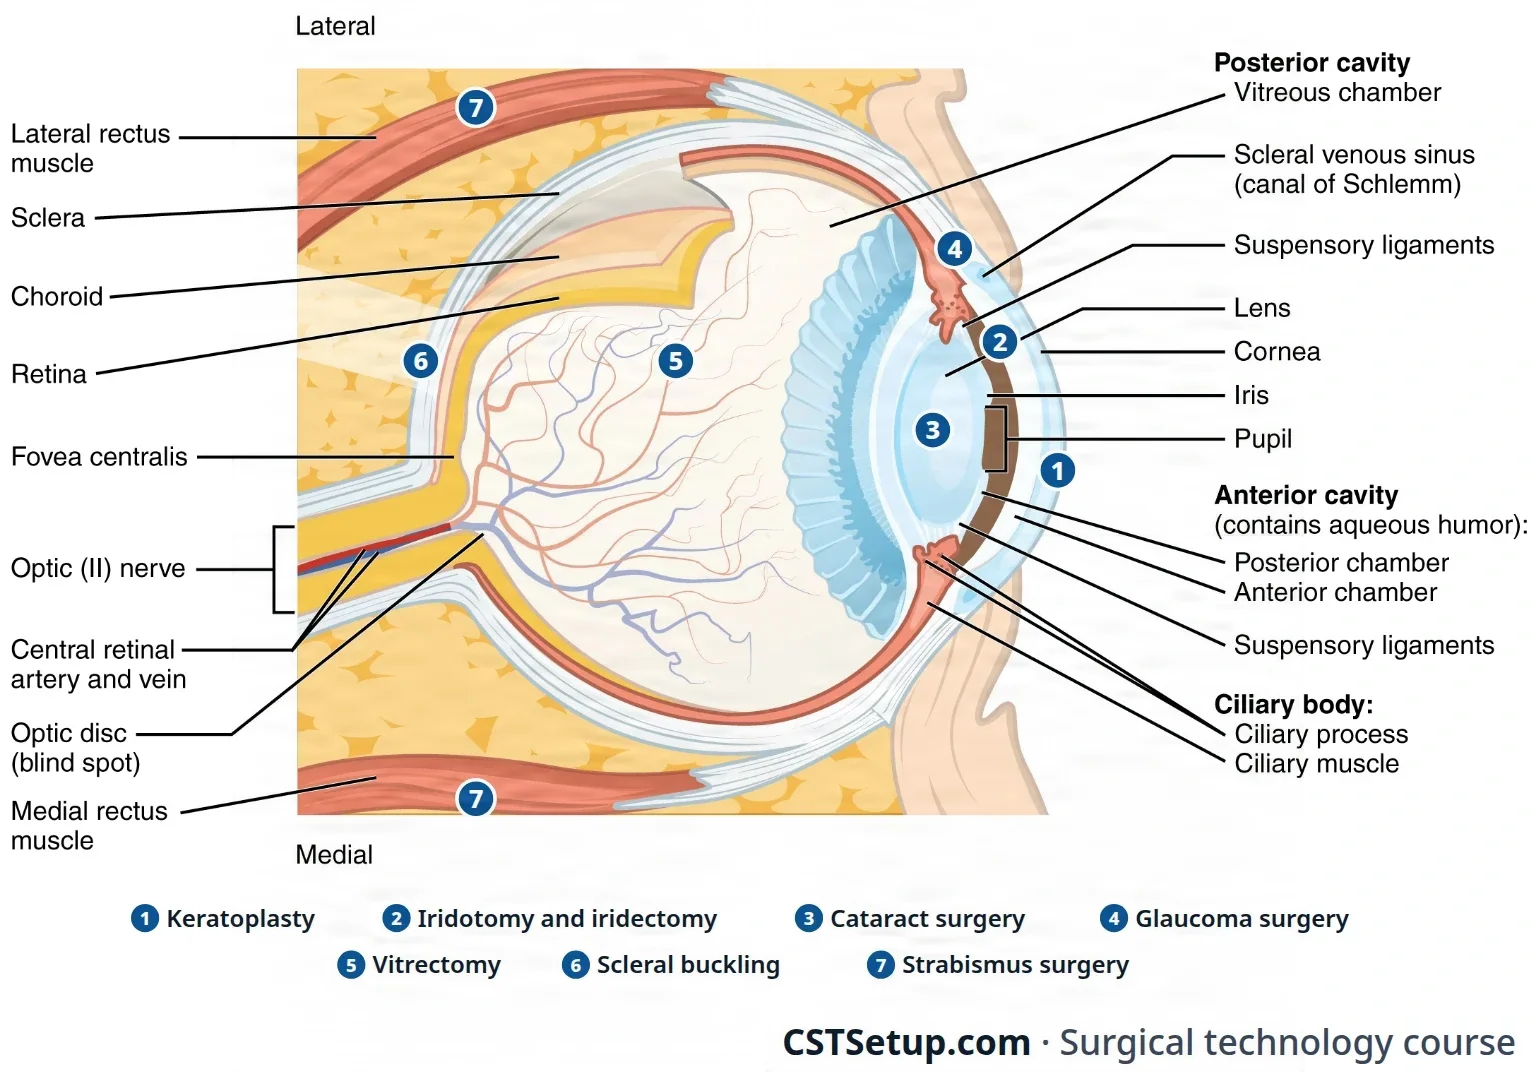
Chapter 4 teaches the eye's anatomy in full. This section reviews only the parts each operation touches.
The orbit, lids and conjunctiva
- Orbit: the eyeball, or globe, sits in a bony socket built from seven bones (frontalFRUN-tulRelating to the front of the body, or to the forehead and the bone or brain area behind it.Full entry , lacrimal, sphenoid, ethmoid, maxillary, zygomatic and palatine), lined with connective tissuekuh-NEK-tiv TISH-ooBody tissue that supports, binds together and protects other tissues and organs.Full entry that cushions it. The rim is thick and protective, and the optic nerveOP-tik nervThe nerve that carries visual signals from the back of the eye to the brain; the second cranial nerve.Full entry enters at the back through the optic foramen.
- Eyelids: thin skin over a scaffold of dense fibrousFY-brusMade of or containing tough threads (fibers), especially of connective tissue.fibr/o fiber-ous full of, relating toFull entry tissue, the tarsal plate. The plates hold the meibomian glands, tiny oil glands along the lid margin, about 30 in the upper lid and 20 in the lower, whose oil slows the evaporation of tears. The gap between the open lids is the palpebral fissureFISH-erA narrow crack or split in the skin, a lining or an organ.Full entry , and each corner where the lids meet is a canthus, inner (medial) and outer (lateral).
- Eyelid muscles: the orbicularis oculi closes the lids, and the levator palpebrae superioris raises the upper lid.
- conjunctivakon-junk-TY-vuhThe thin, clear layer that lines the inside of the eyelids and covers the white of the eye.Full entry : a thin, clear mucous membrane. Its palpebral part lines the inside of the lids and folds back at the fornix as the bulbar part over the white of the eye, up to the limbus, where the corneaKOR-nee-uhThe clear, dome-shaped layer at the front of the eye, over the iris and pupil.Full entry meets the scleraSKLAIR-uhThe tough white outer layer of the eyeball.Full entry . Under it lies Tenon capsule, the fibrous layer surgeons dissectdy-SEKT, or dih-SEKTTo cut apart or separate tissues carefully during surgery.Full entry to reach the muscles and sclera.
The wall of the globe
- Cornea: the clear window at the front, with no blood vessels. It does most of the bending of light, about 65 percent of the eye's focusing power. It has five layers: the epitheliumep-ih-THEE-lee-umThe tissue that covers the body's surfaces and lines its organs, vessels and cavities.Full entry , the Bowman membrane, the stroma, the Descemet membrane and the endothelium, a single layer of cells that pumps fluid out to keep the cornea clear. Endothelial cells do not grow back, so damage to them leaves a swollen, cloudy cornea. Some references count only the three main layers: epithelium, stroma and endothelium.
- Sclera: the tough white coat over most of the globe. It gives the eye its shape and takes the tendons of the eye muscles.
- Choroid and ciliary body: the choroid is a dark layer full of blood vessels under the sclera. At the front it becomes the ciliary body, a ring of muscle that holds the lens on fine fibers and makes aqueous humor. Its rear band, the pars plana, lies just in front of where the retinaRET-ih-nuhThe thin layer of light-sensing tissue at the back of the inside of the eye.Full entry begins, which is why surgeons enter the back of the eye there.
- Iris and pupil: the iris is the colored ring of muscle between the cornea and the lens; the pupil is the opening in its center. The iris narrows the pupil in bright light and widens it in dim light.
The lens and the fluids
- Lens: a clear disc, curved on both sides, inside a thin, clear capsule. It sits behind the iris, held to the ciliary body by fine fibers called zonules (the suspensory ligament). Its center is the nucleus and its outer part the cortexKOR-teksThe outer layer of an organ, especially the folded gray outer layer of the brain.cortic/o cortex, outer layerFull entry , like the pit and flesh of a peach, with the capsule as the skin. cataractKAT-uh-raktClouding of the lens of the eye.Full entry surgery takes out the nucleus and cortex and leaves the capsule to hold the new lens.
- Chambers and aqueous humor: the space in front of the lens holds two chambers: the anterior chamber between the cornea and the iris, and the posterior chamber between the iris and the lens. Both hold aqueous humor, a clear watery fluid made by the ciliary body. It flows from the posterior chamber through the pupil into the anterior chamber, then drains through the trabecular meshwork, in the angle where the iris meets the cornea, into the canal of Schlemm and the veins. The balance between what is made and what drains sets the intraocular pressure (IOP).
- Vitreous humor: a clear jelly, about 99 percent water, that fills the back 80 percent of the eye and holds it in shape. It sticks to the retina at its base. Unlike aqueous humor, the body does not replace it.
The retina and optic nerve
- Retina: the inner, light-sensing layer. Its center, the macula, gives sharp central vision, and the fovea at the center of the macula is where vision is sharpest. The optic nerve (cranial nerveKRAY-nee-ul NERVOne of the 12 pairs of nerves that come straight from the brain and brainstem rather than the spinal cord.Full entry II) leaves at the optic disc, which has no light-sensing cells and so makes a blind spot. The central retinalRET-ih-nulRelating to the retina, the thin layer at the back of the eye that senses light and sends images to the brain.retin/o retina-al relating toFull entry artery and vein run inside the optic nerve.
The muscles and the tear system
- Eye muscles: six muscles move each eye: four recti (superior, inferior, medial and lateral) and two obliques (superior and inferior). The oculomotor nerveok-yoo-loh-MOH-ter nervThe third cranial nerve, which moves most of the muscles of the eye, raises the eyelid and narrows the pupil.ocul/o eyemotor movingFull entry (III) supplies the superior, inferior and medial recti, the trochlear nerve (IV) the superior oblique, and the abducens nerve (VI) the lateral rectusREK-tusLatin for straight; the name of several straight muscles, such as the rectus abdominis of the abdomen and the rectus femoris of the thigh.Full entry . The muscles let both eyes aim at one point, so the brain fuses two images into one (binocular vision).
- Lacrimal apparatus: the lacrimal gland, in the upper outer orbit, makes tears. Tears run across the eye to the puncta, the small openings at the inner ends of the lids, then through the canaliculi into the lacrimal sac and down the nasolacrimal duct into the nose. Tears keep the cornea moist, bring it nutrients and antibodyAN-tih-bod-eeA Y-shaped protein made by the immune system that sticks to one specific germ or foreign substance and marks it for destruction.anti- againstbody Full entry , and hold enzymeEN-zimeA protein that speeds up a chemical reaction in the body without being used up.Full entry that break down bacteria.
How the eye focuses
Light bends (refraction) as it passes through the cornea, the aqueous humor, the lens and the vitreous. The rays meet at the focal point, which should fall on the retina. To keep near and far objects sharp, the lens changes shape, a process called accommodationuh-kom-uh-DAY-shunThe eye's ability to change its focus from distant objects to near ones.Full entry .
When the focus misses the retina, the eye has a refractive error:
- myopiamy-OH-pee-uhNearsightedness: close things are seen clearly but distant things look blurred.my to shut (from squinting)-opia visionFull entry (nearsightedness): the rays focus in front of the retina, so faraway things look blurry.
- Hyperopia (farsightedness): the rays focus behind the retina.
- Astigmatism: an unevenly curved cornea scatters the focus.
- presbyopiaprez-bee-OH-pee-uhThe gradual loss, with age, of the eye's ability to focus on things up close.presby/o old age-opia visionFull entry : after about age 40 the lens and zonules stiffen, so the lens can no longer change shape enough for near vision.
Glasses and contact lenses correct most refractive errors; corneal laser surgery and lens implants are the surgical options.
3Eye disease
The Core Curriculum lists eight conditions of the eye that lead to surgery. Each is taught again with the operation that treats it.
Cataract
A cataractKAT-uh-raktClouding of the lens of the eye.Full entry is a clouding of the lens or its capsule, so light no longer focuses sharply on the retinaRET-ih-nuhThe thin layer of light-sensing tissue at the back of the inside of the eye.Full entry . With age, the proteins of the lens clump together and the lens turns from clear to yellow or brown. Vision blurs and slowly worsens, colors fade, headlights glare, night vision drops, and some patients see double.
Age-related cataracts are the most common. Others are present at birth (congenitalkun-JEN-ih-tulPresent at birth.con- withgen birth, origin-al relating toFull entry ), follow an injury (traumatic), or come with diabetes, long use of corticosteroidkor-tih-koh-STER-oydA drug that acts like the hormones of the adrenal glands, used mainly to calm inflammation and the immune system.cortic/o cortex (the outer layer of the adrenal gland)-oid likeFull entry , smoking, ultraviolet light or earlier eye surgery (secondary). Surgery is the only treatment, and it is advised when the cataract gets in the way of daily life, such as driving and reading, or blocks the surgeon's view of the retina.
Conjunctivitis
conjunctivitiskun-junk-tih-VY-tisInflammation of the thin, clear layer that covers the white of the eye and lines the inside of the eyelids.conjunctiv/o conjunctiva-itis inflammationFull entry is inflammation of the conjunctivakon-junk-TY-vuhThe thin, clear layer that lines the inside of the eyelids and covers the white of the eye.Full entry , often called pinkeye. It may be bacterial, with thick, sticky discharge, or viral, with a more watery discharge, and it spreads easily to the other eye and to other people, so hand washing matters. Bacterial conjunctivitis is treated with antibiotic drops. It usually does not harm vision for good.
Corneal damage requiring transplant
The corneaKOR-nee-uhThe clear, dome-shaped layer at the front of the eye, over the iris and pupil.Full entry must stay clear to let light through. It can be clouded or scarred by chemical and heat burns, infection, injury, inherited diseases (corneal dystrophyDIS-truh-feeA condition in which a muscle or other tissue weakens and wastes away over time.dys- bad-trophy nourishment or growthFull entry ), swelling after eye surgery, or keratoconus, a cornea that thins and bulges into a cone. When the cornea cannot be cleared any other way, a corneal transplant (keratoplasty) replaces it, as long as the retina and optic nerveOP-tik nervThe nerve that carries visual signals from the back of the eye to the brain; the second cranial nerve.Full entry still work.
Eye muscle disorders
In strabismus, the extraocular muscles do not work together, so the eyes do not line up and binocular vision is lost. An eye may turn in (esotropia), out (exotropia), up (hypertropia) or down (hypotropia). By one estimate, about 2 to 4 percent of people have it, more often with conditions that affectAF-ekt (stress on the first syllable)In mental health, the outward expression of a person's emotions, as seen in the face, voice and body language.Full entry the brain, such as cerebral palsySER-uh-brul PAWL-zeeA group of lifelong disorders of movement and posture caused by damage to the developing brain before, during or soon after birth.cerebr/o brain-al relating topalsy paralysisFull entry , hydrocephalushy-droh-SEF-uh-lusA buildup of too much cerebrospinal fluid inside the spaces (ventricles) of the brain.hydr/o watercephal/o head-us noun endingFull entry and Down syndromeDOWN SIN-drohmA genetic condition in which a person has a third copy of chromosome 21.Full entry . In a child, the brain begins to ignore the image from the turned eye to avoid double vision (diplopiadih-PLOH-pee-uhSeeing two images of a single object; double vision.dipl/o double-opia visionFull entry ). Left untreated, this becomes amblyopia, a lasting loss of vision in that eye, which is why strabismus is treated early.
Glaucoma
glaucomaglaw-KOH-muhAn eye disease in which the optic nerve is damaged, usually with raised pressure inside the eye, leading to loss of vision.Full entry is a group of diseases that damage the optic nerve and narrow the field of vision, usually because the intraocular pressure is too high. In nearly all cases the problem is poor drainage of aqueous humor, not making too much of it. Normal pressure is about 10 to 22 mm Hg. Vision is lost from the edges inward, and what is lost cannot be restored, so glaucoma surgery protects the sight that is left.
- Open-angle glaucoma, the most common type, develops slowly in both eyes as the trabecular meshwork drains poorly.
- Angle-closure glaucoma happens when the iris lies against the drainage angle and blocks it. A sudden attack, with haloHAY-lohA ring shape: either a ring of light seen around lights, or a metal ring fixed to the skull to hold the neck still.Full entry or rainbow rings around lights, is an emergency, because the eye can go blind without quick treatment.
- Normal-tension glaucoma damages the nerve even though the pressure reads normal.
- Congenital glaucoma: the drainage system is abnormal at birth. The baby's eye stretches, the cornea turns hazy, and light hurts (photophobiafoh-toh-FOH-bee-uhDiscomfort or pain in the eyes caused by light; sensitivity to light.phot/o light-phobia fear, here used for avoidanceFull entry ), with heavy tearing. Surgery prevents blindness.
Macular degeneration
macular degenerationMAK-yuh-ler dih-jen-uh-RAY-shunAn eye disease in which the macula, the center of the retina used for sharp, straight-ahead vision, slowly breaks down.Full entry damages the macula, so central vision blurs while side vision stays. It is the leading cause of vision loss in people 50 and older. The dry form has no treatment; the wet (exudative) form, with leaking vessels, can be treated with laser.
Retinal detachment and diabetic retinopathy
In a retinalRET-ih-nulRelating to the retina, the thin layer at the back of the eye that senses light and sends images to the brain.retin/o retina-al relating toFull entry detachment, the light-sensing layer of the retina separates from the pigment layer beneath it. The warning signs are a sudden shower of floaters, flashes of light, and a curtain or shadow falling across part of the vision. It needs prompt repair, because vision is lost wherever the retina lifts, and the detachment can spread until all useful vision in that eye is gone.
- Rhegmatogenous, the most common type: a tear or hole lets fluid from the vitreous seep under the retina and lift it. Aging is the usual cause, as the shrinking vitreous pulls on the retina; nearsightedness, injury and earlier cataract surgery raise the risk.
- Tractional: scar tissue on the retina pulls it away, most often from diabetic retinopathydy-uh-BET-ik ret-ih-NOP-uh-theeDamage to the small blood vessels of the retina caused by diabetes.retin/o retina-pathy diseaseFull entry .
- Exudative (serousSEER-usThin, watery and clear to pale yellow, like the fluid part of blood.Full entry ): fluid collects behind the retina without a tear, as with inflammation, tumors or macular degeneration.
In diabetic retinopathy, hyperglycemiahy-per-gly-SEE-mee-uhA blood glucose level above normal, over 100 mg/dL when fasting.hyper- aboveglyc/o sugar-emia in the bloodFull entry damages the retina's vessels, which leak and swell the retina, and in the advanced (proliferative) stage fragile new vessels bleed into the vitreous and form scar tissue that can pull the retina loose. Laser treatment, drug injections into the eye and vitrectomy treat it.
Trauma
Eye injuries include blunt and sharp injuries to the lids, chemical and heat burns, foreign bodies, and a ruptured globe, which may tear where it was struck or, more often, at its weaker points such as the limbus. By one report, a third of serious eye injuries lead to blindness. Before repair, imaging rules out hidden damage: computed tomographykum-PYOO-tid toh-MOG-ruh-feeAn imaging test that uses x-rays and a computer to make cross-section pictures of the inside of the body.tom/o cut, slice-graphy process of recordingFull entry for foreign bodies and the bony orbit, ultrasound for a detached retina and for blood in the front of the eye (hyphema), and magnetic resonance imagingmag-NET-ik REZ-uh-nunts IM-uh-jingAn imaging test that uses a strong magnet and radio waves to make detailed pictures of the inside of the body.Full entry for wood and other plant material. Chapter 37 teaches orbital floor (blowout) fractures.
4Diagnostic tests
Most of these tests are done before the day of surgery. Know what each one does, because its results shape the plan and the supplies, such as the power of the lens implant.
- visual acuityVIZH-oo-ul uh-KYOO-ih-teeHow clearly and sharply a person can see.visu sightacu sharpFull entry and refraction: the patient reads an eye chart; a phoropter, a device holding many corrective lenses, finds the lens that gives the sharpest sight.
- Slit lamp: a microscope with a narrow beam of light for the front of the eye: the lid margins, conjunctivakon-junk-TY-vuhThe thin, clear layer that lines the inside of the eyelids and covers the white of the eye.Full entry , tear film, corneaKOR-nee-uhThe clear, dome-shaped layer at the front of the eye, over the iris and pupil.Full entry , iris and, with the pupil dilated, the lens and front of the vitreous.
- Fluorescein stain: a dye that turns scratched or bare areas of the cornea bright green under a cobalt blue light.
- Tonometry: measures the intraocular pressure, a key test in finding and following glaucomaglaw-KOH-muhAn eye disease in which the optic nerve is damaged, usually with raised pressure inside the eye, leading to loss of vision.Full entry .
- Ophthalmoscopy: a handheld ophthalmoscope magnifies the fundusFUN-dusThe rounded top or base of a hollow organ, most often the top of the uterus.Full entry , the back of the eye; an indirect binocular ophthalmoscope shows a wider view of the retinaRET-ih-nuhThe thin layer of light-sensing tissue at the back of the inside of the eye.Full entry and is used in the OR during retinalRET-ih-nulRelating to the retina, the thin layer at the back of the eye that senses light and sends images to the brain.retin/o retina-al relating toFull entry surgery. A dilated exam is the only way to find the exact cause of a retinal detachment.
- Fluorescein angiographyan-jee-OG-ruh-feeAn imaging test that shows blood vessels by injecting a contrast dye and taking x-ray, CT or MRI pictures.angi/o vessel-graphy process of recordingFull entry : dye injected into a vein lights up the vessels of the retina and choroid in a series of photos, to find leaks and plan laser treatment.
- Ultrasound: the A-scan shows tissue density as a wave and measures the eye's length and the depth of its front chamber; the B-scan draws a picture of the tissues in spots whose brightness shows their density.
- Biometry for a lens implant: before cataractKAT-uh-raktClouding of the lens of the eye.Full entry surgery, the surgeon measures the curve of the cornea (keratometry) and the eye's length from cornea to retina (axial length) and calculates the power of the intraocular lens (IOL). In a child this is done with an A-scan in an exam under anesthesiaan-us-THEE-zhuhLoss of feeling or sensation, often brought on by drugs so that surgery or a procedure can be done without pain.an- withoutesthesi/o feeling, sensation-ia conditionFull entry .
- Optical coherence tomographytoh-MOG-ruh-feeImaging that produces pictures of the body in thin slices.tom/o cut, slice-graphy process of recordingFull entry (OCT): high-resolution cross-section images of the retina, optic nerveOP-tik nervThe nerve that carries visual signals from the back of the eye to the brain; the second cranial nerve.Full entry and front of the eye, widely used to follow glaucoma.
- computed tomographykum-PYOO-tid toh-MOG-ruh-feeAn imaging test that uses x-rays and a computer to make cross-section pictures of the inside of the body.tom/o cut, slice-graphy process of recordingFull entry and magnetic resonance imagingmag-NET-ik REZ-uh-nunts IM-uh-jingAn imaging test that uses a strong magnet and radio waves to make detailed pictures of the inside of the body.Full entry : show the orbit and the structures behind it. CT can miss very small structures and ones of similar density.
- History and examination: for problems of the lids and surface, such as a chalazion, an entropion or a strabismus, the history and the physical exam usually make the diagnosis.
5Before the case: the patient, the room and the team
An awake patient who hears everything
Most eye operations are done with the eye numbed and the patient sedationsih-DAY-shunA calm, relaxed or sleepy state brought on by drugs, or the use of drugs to cause it.sed calm, settle-ation processFull entry but awake. The patient hears the room and can see shapes and instruments coming toward the eye. Many look forward to seeing better, yet fear quietly that something will go wrong and leave them blind.
A calm room helps the eye as well as the patient: anxiety raises the pressure inside the eye and can increase bleeding. Keep talking and movement to a minimum, because the patient is awake, and give simple warnings of what they will feel, such as the sting of an injection or pressure on the eye. The patient is asked to lie still throughout, because movement while instruments touch the eye can injure it.
Because so many of these patients are sedated, an extra nurse or an anesthesia provideran-us-THEE-zhuh pruh-VY-derThe licensed professional who gives anesthesia and watches over the client's breathing and vital functions during a procedure.Full entry is assigned to watch the patient and give support.
The right eye, the right lens
Eye surgery carries a high risk of errors, such as the wrong eye or the wrong lens, partly because so many cases are done. The patient is identified with at least two identifiers, never the room number, and states which eye is having surgery. The consent, the orders, the schedule and the surgeon's mark must all agree, and any difference is settled before the case. The mark near the eye can disappear under the drapes, so the team is especially careful at the time-outTYM-owtA pause just before a procedure when the whole team confirms the right client, procedure and site; also, a short break to calm a child.Full entry . A time-out is also done before a regional block is given to the eye.
An eye checklist adds items to the usual time-out. The surgeon and the nurse confirm that the implant style and power, any antineoplastican-tee-nee-oh-PLAS-tikA drug used to treat cancer by killing cancer cells or stopping them from growing and dividing.anti- againstneo- newplas growth, formation-tic relating toFull entry drug, devices, donor tissue, gas or silicone oil and dyes are available, and the counts and specimens are confirmed before the patient leaves.
The wrong intraocular lens (IOL) is one of the most serious errors in eye surgery. Treat the lens like a drug passed to the field. A typical protocol, based on the American Academy of Ophthalmology's:
- Before surgery, the surgeon chooses the IOL from the patient's records in the room, and its details are written where the whole team can see them, such as on a whiteboard.
- The circulator shows the surgeon the box and reads the model number and lens power aloud, and the surgeon confirms.
- The circulator repeats this with you.
- As you pass the lens, you state its model number and power aloud, and the team checks it once more just before it goes in.
The lens, like every implant, is recorded in the patient's chart. A secondary IOL is kept available, with an anterior vitrectomy handpiece, because a torn capsule can leave nothing to hold the planned lens.
Anesthesia, as the scrub sees it
Most eye surgery is done under regional anesthesiaan-us-THEE-zhuhLoss of feeling or sensation, often brought on by drugs so that surgery or a procedure can be done without pain.an- withoutesthesi/o feeling, sensation-ia conditionFull entry with monitored sedation (monitored anesthesia care, MAC). Chapter 13 teaches topical anesthesia, the retrobulbar block and MAC; here is what you will see, with the other eye blocks.
- Drops: dilating drops and a topical anesthetican-us-THET-ikA drug that causes loss of feeling, with or without loss of consciousness.an- withoutesthesi/o feeling, sensation-ic relating toFull entry , such as tetracaine or proparacaine, are put in the eye in the holding area or the OR, often more than once. lidocaineLY-doh-kaynA local anesthetic that numbs an area, also given by IV to treat some fast, abnormal heart rhythms.Full entry gel and preservative-free lidocaine injected into the anterior chamber can add to them. Topical anesthesia does not stop the eye from moving or the lids from closing.
- Blocks: a retrobulbar block (behind the globe, into the cone of muscles) or a peribulbar block (around the globe) numbs the eye and stops it moving; a sub-Tenon block puts the drug between the scleraSKLAIR-uhThe tough white outer layer of the eyeball.Full entry and Tenon capsule. The ophthalmologist or the anesthesia provider gives them. A retrobulbar block, now used only in selected patients, can bleed behind the eye, pierce the globe, or set off the oculocardiac reflexREE-fleksAn automatic body response to something that stimulates it, which happens without thought, such as the knee jerk.Full entry , a vagal response that slows the heart.
- Block setup: a separate setup holds the anesthetic, syringes, 25- to 27-gauge needles, transfer needles and sponges, as the surgeon prefers, with any adjunct the surgeon adds (see the eye drugs below). The circulator stays at the patient's side.
- general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry : used for children, usually for eye removal, and for long cases such as some retinalRET-ih-nulRelating to the retina, the thin layer at the back of the eye that senses light and sends images to the brain.retin/o retina-al relating toFull entry surgery.
an awake patient is listening. Keep the room quiet and still, and warn the patient before anything they will feel.
Position
- Supine, with the head on a gel donut or a headrest made for eye surgery, sometimes with a strip of tape across the forehead to the bed. A wrist rest at the head of the table steadies the surgeon's hands.
- Eye stretchers serve as both stretcher and operating table, so the patient does not have to be moved after surgery, when shifting can raise the eye pressure. With a regular stretcher, move the patient slowly and warn them about the narrow table.
- Arms are tucked at the sides away from the table frame, or the arm on the operative side is tucked and the other rests on an armboard. The safety strap goes on early.
- Comfort: support for the lower back and under the knees, padding as needed and warm blankets. An uncomfortable patient grows restless, and a patient who moves can be hurt. Older patients may have arthritis and not say they hurt, so watch their body language.
Prep
Dilute povidone-iodinePOH-vih-done EYE-uh-dineA brown antiseptic solution of iodine used to kill germs on the skin before procedures and on wounds.Full entry , 5 percent or as the surgeon orders, is the prep approved for use around the eye. Ask about iodineEYE-uh-dyneA mineral the thyroid gland uses to make thyroid hormone; it is also used to kill germs on the skin and in some contrast dyes.Full entry allergy first; for a patient with an iodine allergy, a mix of baby shampoo and balanced salt solution (BSS) may be used. Chlorhexidine (CHG) is never used on the face or in or around the eyes or ears, and alcohol preps never go near the eye, because they can badly injure the corneaKOR-nee-uhThe clear, dome-shaped layer at the front of the eye, over the iris and pupil.Full entry .
- Have the supplies ready before the block, so the prep is not delayed: small basins of prep solution and saline, towels, an adhesive towel drape, lint-free gauze, cotton balls, cotton-tipped applicators, eye sponges, a bulb syringe and BSS.
- Turn the head slightly toward the operative side, with a cotton ball at the ear opening and a small adhesive drape so solution cannot run into the ear.
- The surgeon may order one or two drops of 5 percent povidone-iodine into the eye first, after a drop of topical anesthetic to ease the sting, and left in place for at least 2 minutes, to cut down germs on the conjunctivakon-junk-TY-vuhThe thin, clear layer that lines the inside of the eyelids and covers the white of the eye.Full entry and the risk of infection inside the eye.
- Clean the lid margins and lashes with cotton-tipped applicators, then prep from the eyelid outward: the lids, the inner and outer corners, the brow and the face to the chin line, to about an inch from the hairline. The canthus, the corner of the eye, is treated as contaminated, so a sponge that touches it is thrown away. Repeat at least three times with fresh sponges, and squeeze extra solution from each sponge so it cannot run off or pool in the eye. Prep both sides of the face for both eyes, and for strabismus, so the eyes can be compared.
- Rinse with warm saline, flush the eye with BSS, and pat the skin dry so the adhesive drape will stick.
Eyebrows are never shaved, and long lashes are trimmed carefully with small scissors only when needed.
AST's 2008 skin prep standard rules out both CHG and iodine (iodophor) preps for the eye and face, because either can injure the cornea, and suggests a nontoxic agent such as PCMX with a warm sterile water rinse, kept out of the eyes.
Drape
Eye drapes repel water, shed no lint and leave the awake patient enough air to breathe comfortably.
- Globe and intraocular cases: a head drape, then an eye drape with a plastic, self-adhering section over the operative eye, large enough to cover the body. One scrubbed person spreads the lids with cotton-tipped applicators while the other presses the adhesive down, so the lashes stay under it and out of the field. Some eye drapes have a pouch that catches fluid. Press the edges down with sterile swabs rather than fingers, to protect the soft skin around the eye.
- Lid and conjunctiva cases: a head drape, such as an adhesive U drape around the site and a smaller sheet across the forehead, placed after the towels.
- The other eye, when both are exposed, is covered with a moist eye pad or taped shut.
6The microscope and the eye equipment
Chapter 23 teaches the operating microscope as equipment, how to move, set up, test and care for it, and introduces the phacoemulsifier and the cryotherapy unit; chapter 28 teaches draping the microscope. This section covers what is special about each machine in eye surgery.
The operating microscope
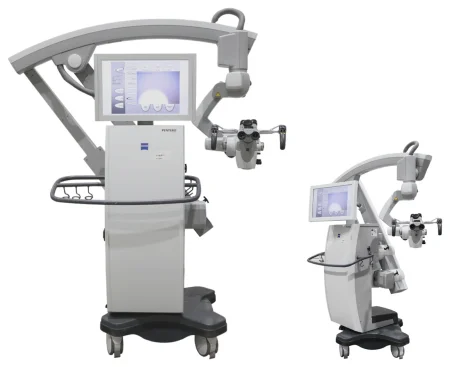
Most eye operations are done under the operating microscope. It magnifies the field, but the area the surgeon can see through it is very small. Set it up and care for it as chapter 23 teaches, and drape it as chapter 28 teaches; these points are particular to the eye.
- Use a microscope meant for the eye. Some microscopes built for other work, such as plastic surgery, have lights bright enough to damage the retinaRET-ih-nuhThe thin layer of light-sensing tissue at the back of the inside of the eye.Full entry .
- Set it for the right or left eye, and test it, before the patient comes in.
- Position it before the prep: for some cases the microscope is brought over the patient, adjusted by the surgeon, locked and swung out of the way until it is needed. A portable microscope comes in from the side opposite the operative eye.
- Never bump it. The patient and the field must be completely still, and the slightest jar of the microscope or of an instrument touching the eye can injure it.
- The room may be darkened to improve the view, and the scrub learns to work while looking through the microscope, to irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry the eye or cut a sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry .
The phacoemulsification system
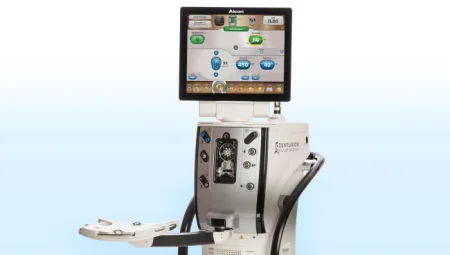
Phacoemulsification breaks up the lens with ultrasonic vibration and suctions it out through a handpiece, while balanced salt solution flows in to keep the front chamber filled. The handpieces and tips come in several sizes, straight or curved. Chapter 20 teaches ultrasound as an energy source.
- The settings for power, suction (vacuum), the height of the irrigation bottle and the foot pedal are set for each machine, each surgeon and each patient, and they cannot be copied from one brand to another.
- Everyone who runs the machine needs the knowledge and skill to use it correctly, by its maker's instructions.
- A machine that is not working properly can burnBURNAn injury to the skin or deeper tissues caused by heat, chemicals, electricity, radiation or friction.Full entry the corneaKOR-nee-uhThe clear, dome-shaped layer at the front of the eye, over the iris and pupil.Full entry , and some chopping tips run so fast that one wrong move can shatter the cataractKAT-uh-raktClouding of the lens of the eye.Full entry .
- Most phaco machines switch to a vitrectomy mode when vitreous comes forward during cataract surgery.

The vitrectomy machine
The vitrectomy machine draws the vitreous into a tiny port, cuts it and suctions it away, while an infusion of BSS flows in; raising or lowering the bottle changes the eye's pressure. It also supplies light inside the eye, and a unit can add an air-fluid exchange, diathermy and a laser. The vitreous is then replaced with saline, a gas bubble or silicone oil to hold the retina in place. Some units combine phaco and vitrectomy.

Cryotherapy, diathermy and lasers
- Cryotherapy unit: a probe chilled by a gas under pressure, such as nitrous oxide or carbon dioxideKAR-bun dy-OK-sideA gas made by the body's cells as waste, carried in the blood to the lungs and breathed out.Full entry , freezes tissue. In retinalRET-ih-nulRelating to the retina, the thin layer at the back of the eye that senses light and sends images to the brain.retin/o retina-al relating toFull entry surgery the frozen spot heals as a scar that seals a tear. The surgeon runs it with a foot switch.
- Diathermy: low-power heat applied to the scleraSKLAIR-uhThe tough white outer layer of the eyeball.Full entry over a retinal tear or detachment, which also leaves a sealing scar.
- Lasers: the argon and Nd:YAG lasers seal leaking vessels and retinal tears (photocoagulation), and the YAG laser also opens a capsule that clouds after cataract surgery. The excimer laser reshapes the cornea, and the femtosecond laser makes the cuts for cataract surgery. A laser on an ophthalmoscope, or one passed into the eye during vitrectomy, treats the retina.
Chapter 20 teaches laser safety: eyewear marked for the laser's wavelength; windows always covered for the argon, Nd:YAG and other lasers whose beams pass through glass, and for other lasers as facility policy sets; and, for argon or Nd:YAG under the microscope, a shutter that drops a filter into place to protect the surgeon's eyes.
Electrosurgery
Two kinds are common in eye surgery. A single-use, batteryBAT-uh-reeIn law, touching a person on purpose without their consent.Full entry -powered cautery pen has a fine wire tip that heats up and seals tiny vessels; it is a true cautery and cannot cut. bipolarby-POH-lerHaving two poles or two opposite ends; most often used as a short form of bipolar disorder.bi- twopolar having polesFull entry electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry , with fine bipolar forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry , gives precise cutting and coagulationkoh-ag-yuh-LAY-shunThe process by which blood changes from a liquid into a gel, forming a clot.coagul clot-ation processFull entry . Monopolar units may also be used. A smoke evacuator is used whenever energy devices make smoke.
7Microinstruments, sponges, sutures and supplies
Handling microinstruments
Eye instruments are small, delicate and expensive, and many have finishes that cut glare under the microscope light. A bent tip or a dull edge can damage the eye.
- Inspect before the case: tips aligned, edges smooth, scissor blades meeting properly, needle holder catches and springs working, suction tips open. Look for burrs (rough spots on sharp edges) under magnification, or run a lint-free microsurgical wipe gently along the edge to feel for one.
- Keep a fixed order: lay instruments on the Mayo in a set order and always put each one back in its place, so you can hand the next one without looking away.
- Pass in position of use, placed firmly in the surgeon's hand, because the surgeon must not look up from the microscope to take it. Looking away breaks the surgeon's concentration and the rhythm of the case.
- Keep them clean during the case: wipe off blood, tissue and viscoelastic with a lint-free instrument wipe moistened with sterile water, and flush instruments with channels with sterile water. Chapter 27 teaches how sterile processing cleans and protects microinstruments, and how leftover residue causes toxicitytok-SIS-ih-teeThe harm a substance does to the body, or a state in which a drug has built up to a harmful level.tox/o poison-icity state or quality ofFull entry anterior segment syndrome (TASS).
- Keep lint and powder out: powder-free gloves, lint-free drapes and sponges, and sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry kept off cloth towels. A clear plastic cover over the draped Mayo keeps dust off and protects the instruments. Lint or powder left in the eye can cause a granuloma, a small inflamed lump, after surgery.
- Steady hands: a tremorTREM-erShaking of a part of the body, such as the hands, in small rhythmic movements that the person cannot control.Full entry too small to notice is large under magnification, so keep your hand steady and make as little movement as possible near the field.
jar the microscope or an instrument while it touches the eye. Even a slight movement can injure the eye, so pass and take instruments with small, steady movements.
The instrument families
Eye sets vary by surgeon, but the same families appear in most of them.
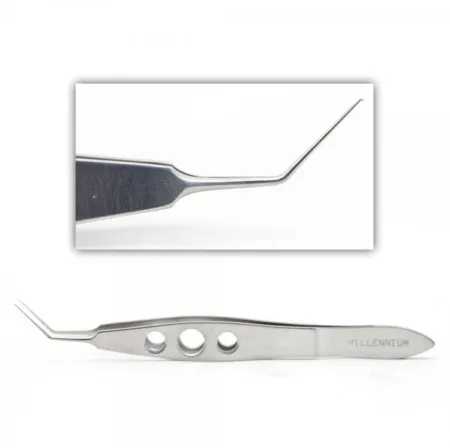
- speculumSPEK-yoo-lumAn instrument used to open and hold open a body opening, such as the vagina, so the inside can be seen.Full entry hold the lids open. A wire speculum, such as the Barraquer, is common for cataractKAT-uh-raktClouding of the lens of the eye.Full entry surgery; adjustable ones, such as the Castroviejo, Williams and Lieberman, spread the lids wider for strabismus and eye removal. A Desmarres retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry holds a lid by hand.
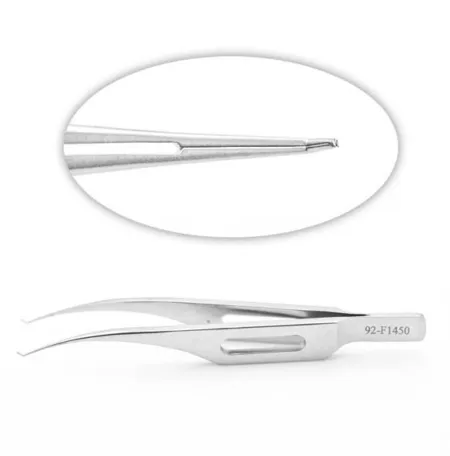
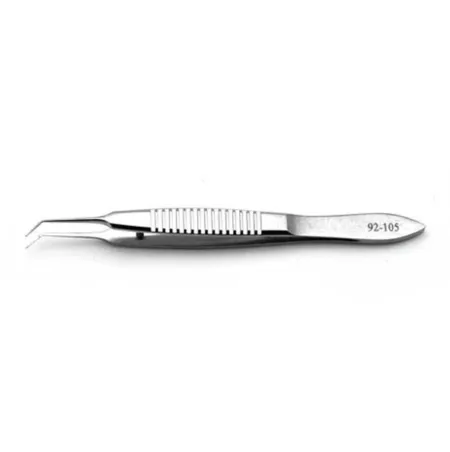
- Tissue forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry : Castroviejo suturing forceps have tiny teeth at the tip, 0.12, 0.3 or 0.5 mm, and a tying platform; Colibri forceps hold the cut edges of the corneaKOR-nee-uhThe clear, dome-shaped layer at the front of the eye, over the iris and pupil.Full entry and scleraSKLAIR-uhThe tough white outer layer of the eyeball.Full entry while the surgeon sews, and tie the suture on the platform behind the teeth; Bishop-Harmon forceps grasp delicate tissue.
- Tying forceps, such as the McPherson, have smooth platforms for tying fine sutures and are never used to grasp tissue, which they would crush.
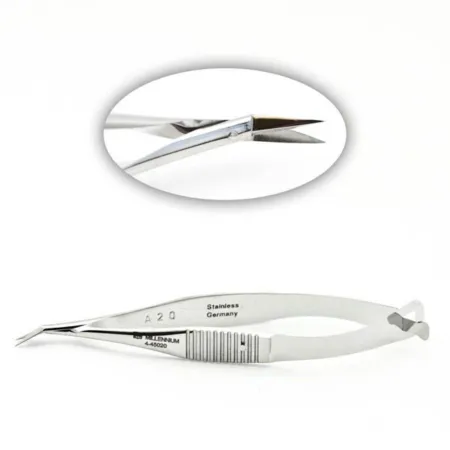
- Scissors: Westcott spring scissors to cut the conjunctivakon-junk-TY-vuhThe thin, clear layer that lines the inside of the eyelids and covers the white of the eye.Full entry , cornea, sclera and iris and to divide the muscles; Vannas spring micro scissors to cut into the capsule; corneal scissors to finish a corneal cut; Stevens tenotomy scissors for the muscles and tendons; and curved enucleation scissors to cut the optic nerveOP-tik nervThe nerve that carries visual signals from the back of the eye to the brain; the second cranial nerve.Full entry . Eye suture scissors cut suture only.
- Needle holders: the Castroviejo, locking or nonlocking; the McPherson, nonlocking; and the Barraquer, locking with curved jaws.
- Knives: diamond knives, disposable keratomes and slit knives for corneal incisions, and fine blades such as Beaver blades and microblades.
- Hooks, spatulas and cannulaKAN-yoo-luhA thin tube placed into the body or a body opening to deliver or remove fluid or air.Full entry : muscle hooks lift the eye muscles; a Sinskey hook moves the lens implant; an iris spatula sweeps the iris back into place; blunt cannulas on syringes irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry the eye and inject fluid or viscoelastic.
- Calipers measure the eye in millimeters, such as the Castroviejo caliper, 0 to 20 mm.





Eye sponges
Eye sponges are small spears of lint-free cellulose on a short plastic rod. Keep them apart from anything that sheds lint. To dry the field, touch the tip to the fluid and let it wick the fluid up; never wipe. A sponge is never used on the cornea.
Keeping the cornea wet
The open eye cannot keep itself moist during surgery. Irrigate the cornea with BSS as the surgeon wants, from a small squeeze bottle, an irrigating needle or a bulb syringe. Hold the tip over the eye without touching it, and let the fluid run from the inner corner to the outer corner so it does not pool; with the head turned toward the operative side, the runoff stays away from the other eye.
Sutures and needles
- Sizes: eye sutures are very fine, from 4-0 down to 10-0, and some references list sizes as small as 12-0. Fine suture causes less reaction and discomfort. Handle it as little as possible, keep it off cloth towels, and protect the needle points. Double-armed sutures, with a needle at each end, are common.
- Needles: the spatula needle, fine with a thin, flat profile, is the common needle for the cornea and sclera; other shapes, such as taper-cut and reverse cutting needles, are chosen for other tissues. Some eye needles are only about 4 mm at their widest. Inspect needles for burrs before use.
- Materials: nylon is the usual choice for the cornea, polypropylene for fixing a lens, polyester for the sclera in retinalRET-ih-nulRelating to the retina, the thin layer at the back of the eye that senses light and sends images to the brain.retin/o retina-al relating toFull entry surgery, silk for tractionTRAK-shunA steady pulling force applied to a body part with weights, ropes and pulleys.Full entry (bridle) sutures, and absorbable polyglactin or gut for the conjunctiva and lids.
- Loading: press a locking needle holder gently; too much pressure, or a needle too large for the holder, stops it locking.
- Cutting under the microscope: first bring the scissors into the microscope's field of view, then move the tips to the suture, rest your forefinger on the shank to steady the scissors, and lower the tips gently to cut.
- Passing sharps: the surgeon cannot look away from the microscope, so a hands-free pass into a neutral zone is not possible on the way in. Use a modified neutral zone, as chapter 25 teaches: tell the surgeon a sharp is coming, place the loaded needle holder in the surgeon's hand, say when your hand is out of the way, and the surgeon returns it to the neutral zone.
one reference has the scrub take used sharps back from the surgeon's hand in eye cases.
Counts
All sharps, including every suture needle however small, are counted and accounted for in every operation that uses them, and so are radiopaqueray-dee-oh-PAYKBlocking x-rays, so the material shows up white on an x-ray image.radi/o radiation, x-rayopaque not letting throughFull entry sponges and other soft goods. Instruments must be counted whenever a body cavity is open, which eye surgery does not do, so instrument counts follow facility policy. The eye checklist confirms the counts before the patient leaves the room. Chapter 28 teaches the count itself.
an older AST standard lists eye surgery among the cases where sponge counts may not be required.
Specialty supplies
The Core Curriculum's list of eye supplies:
- Conformer: a plastic shell placed over the implant, behind the lids, after an eye is removed; it supports the lids while the socket heals.
- Corneal shield: a collagenKOL-uh-jenThe main structural protein of the body, which gives strength to skin, bones, tendons, ligaments and scar tissue.coll/a glue-gen producingFull entry shield shaped like a contact lens that carries antibiotic or anti-inflammatory drug to the eye and protects it after surgery; it often falls out on its own within 4 to 12 hours, which is expected.
- Eye pad and eye shield: a soft, lint-free gauze pad absorptionub-ZORP-shunThe taking in of a substance, such as a drug or a nutrient, into the bloodstream.Full entry fluid and keeps debris out; a rigid perforationper-fuh-RAY-shunA hole that goes all the way through the wall of an organ or tissue.per- throughforat bored (a hole)-ion processFull entry metal or plastic shield, such as the Fox shield, is taped over it to protect the eye from bumps and pressure.
- Eye-port: the Core Curriculum names it in its list; check your facility's card for the product it uses.
- Intraocular lens: the artificial lens implant.
- Microblade: fine knife blades for eye incisions.
- Phacoemulsification kit: the phaco and irrigation-aspirationas-puh-RAY-shunBreathing food, liquid, saliva or stomach contents into the airway and lungs; also, drawing fluid out with suction or a needle.Full entry tips, BSS and the other supplies the phaco machine uses, as its card lists.
- Scleral buckle: silicone bands, sponges and tires sewn to the sclera in retinal detachment repair.
- Silastic tube or lacrimal endotracheal intubationen-doh-TRAY-kee-ul in-too-BAY-shunPutting a breathing tube through the mouth or nose into the windpipe (trachea).endo- withintrache/o windpipe-al relating toFull entry kit: soft silicone tubes on metal probes that stentstentA small tube, often of metal mesh, placed inside a vessel or duct to hold it open.Full entry the tear ducts.
- Sphere: the round implant that fills the socket after the eye is removed.
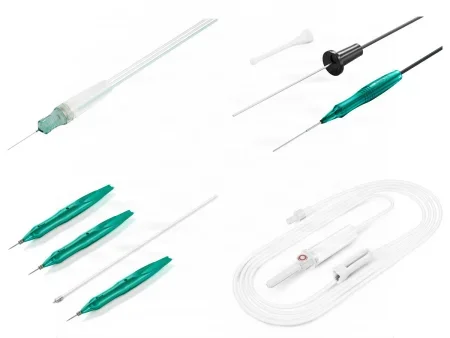
- Vitrectomy kit: the single-use cutter, infusion line, light pipe and tubing for the vitrectomy machine.

Dressings
Some eye operations need no dressing at all. For many, the surgeon or scrub cleans the area with saline-wet sponges, pats it dry and tapes on a sterile eye pad. After surgery inside the eye, where pressure on the eye could do harm, a perforated shield goes over the pad. A pressure dressing is used when the surgeon wants pressure, as after an eye removal. After lid or tear duct surgery, a thin layer of antibiotic ointment on the skin and lashes keeps the dressing from sticking.
8Eye drugs on the field
Chapter 12 teaches the drug classes and how every drug reaches the field: verified aloud by two people, labeled at once and tracked to the end. Eye drugs need all of that, and more. A single mistake can blind the patient, many eye drugs come in small single-dose bottles that look alike, and several go inside the eye, where any impurity does harm.
- Label every drug the moment it reaches the field, and know what each one is for, so you can pass it at the right moment without the surgeon looking up. State its name as you pass it; the surgeon acknowledges every drug.
- Keep intraocular drugs apart. Drugs and solutions that go inside the eye are set apart from those that do not, such as ointments and the prep.
- Preservative-free inside the eye. Drugs injected into the eye must be free of preservatives, often labeled MPF (methylparaben free). Preservatives, the wrong pH, too high a concentration of dissolved particles and contaminated drugs or dyes are among the causes of TASS.
- Know the cap colors, then read the label. The caps of eye drops are color coded by class, following the American Academy of Ophthalmology: red for drugs that dilate the pupil, dark green for miotics, pink for steroidSTAIR-oydA fat-based chemical built from cholesterol; the group includes hormones such as cortisol and estrogen, and many drugs.ster/o solid-oid likeFull entry , gray for nonsteroidal anti-inflammatory drugnon-STAIR-oy-dul an-tee-in-FLAM-uh-tor-ee DRUGA drug that relieves pain, fever and inflammation and is not a steroid, such as ibuprofen or naproxen.non- notanti- againstinflamm/o inflammationFull entry and tan for anti-infectivean-tee-in-FEK-tivA drug that kills or stops the growth of germs that cause infection.Full entry .
- Mix some drugs at the last minute. acetylcholineuh-see-tul-KOH-leenA chemical messenger that nerves release to signal muscles, glands and other nerves.Full entry (Miochol-E) is reconstituted immediately before use, and BSS Plus is made by adding its Part II to Part I with the transfer device and is used within 6 hours.
- Record every drug and amount used, and report the totals at the end of the case, for the intraoperativein-truh-OP-er-uh-tivHappening during surgery, from when the client is brought into the operating room until they are moved to recovery.intra- within, duringoperative of surgeryFull entry record.
- Watch the patient. Many drugs are used together, so report at once any change you see in the patient's appearance or behavior, or anything the patient says they feel.
The Core Curriculum lists these classes of eye drugs.
- Irrigating solutions: balanced salt solution (BSS) is a sterile irrigating fluid balanced to suit the eye's tissues. It keeps the corneaKOR-nee-uhThe clear, dome-shaped layer at the front of the eye, over the iris and pupil.Full entry moist and irrigates inside the eye. Small 15 and 30 mL bottles are used on the field, and 250 and 500 mL bottles run through tubing into the eye during phaco and vitrectomy. BSS Plus, enriched with bicarbonateby-KAR-buh-naytA base in the blood that balances acid; the kidneys control it, and its level is measured on blood gas and chemistry tests.Full entry , dextroseDEK-strohsA form of glucose sugar given by mouth or IV for energy or to raise a low blood sugar.Full entry and glutathione, supports the eye's tissues in long cases. Neither is ever given into a vein, and a bottle is used for one patient only. The surgeon may order preservative-free epinephrineep-ih-NEF-rinA hormone and drug, also called adrenaline, that raises heart rate and blood pressure and opens the airways.Full entry added to the bottle, to keep the pupil wide or to limit bleeding.
- Lubricants: ointments that keep the cornea moist and protected. They are used under general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry for any surgery, because the lids relax and the corneal reflexREE-fleksAn automatic body response to something that stimulates it, which happens without thought, such as the knee jerk.Full entry , which makes the eye blink, is gone; the lids are then taped shut. On waking, the patient's vision may be blurred by the ointment, and the patient must not rub the eyes.
- Mydriatics dilate the pupil (mydriasismih-DRY-uh-sisWidening (dilation) of the pupil of the eye.Full entry ) but still let the eye focus. phenylephrinefen-il-EF-rinA drug that tightens blood vessels, given IV to raise low blood pressure and used in nose sprays and eye drops.Full entry (2.5% or 10%) acts like the sympathetic nervous systemsim-puh-THET-ik NER-vus SIS-tumThe branch of the autonomic nervous system that gets the body ready for stress or danger ("fight or flight").Full entry , and it can raise the blood pressure.
- Cycloplegics dilate the pupil and also paralyze the focusing muscle (accommodationuh-kom-uh-DAY-shunThe eye's ability to change its focus from distant objects to near ones.Full entry ): tropicamide, cyclopentolate, atropineAT-roh-peenAn anticholinergic drug that blocks the parasympathetic nervous system, which speeds the heart rate and dries secretions.Full entry (which lasts 7 to 14 days), homatropine and scopolamineskoh-POL-uh-meenAn anticholinergic drug, most often used as a skin patch behind the ear to prevent motion sickness and nausea after surgery.Full entry . They block acetylcholine. Drugs that dilate the pupil may be contraindicationkon-truh-in-dih-KAY-shunA reason not to give a drug or do a treatment, because in that person it could cause harm.contra- againstindication a reason to useFull entry in angle-closure (narrow-angle) glaucomaglaw-KOH-muhAn eye disease in which the optic nerve is damaged, usually with raised pressure inside the eye, leading to loss of vision.Full entry , and pressing gently over the lacrimal sac after drops cuts the amount absorptionub-ZORP-shunThe taking in of a substance, such as a drug or a nutrient, into the bloodstream.Full entry into the body.
- Miotics constrict the pupil (miosismy-OH-sisNarrowing (constriction) of the pupil of the eye.Full entry ). Acetylcholine (Miochol-E) and carbachol (Miostat) are injected into the front chamber during surgery, for example right after the lens implant goes in, to constrict the pupil, which pulls the iris back into place and helps keep the lens in position; pilocarpinepy-loe-KAR-peenA cholinergic drug used as eye drops to lower pressure in the eye, and by mouth to treat dry mouth.Full entry and carbachol drops lower the pressure in glaucoma.
- Viscoelastics, also called ophthalmicoff-THAL-mikHaving to do with the eye, or describing a medicine made to be put in the eye.ophthalm/o eye-ic relating toFull entry viscosurgical devices (OVDs): thick gels such as sodium hyaluronate, or a mix of chondroitin and hyaluronate, that fill the front chamber, keep it deep, hold tissues apart and protect the cornea's inner lining; they can also coat the lens implant. They come in prefilled syringes with blunt cannulaKAN-yoo-luhA thin tube placed into the body or a body opening to deliver or remove fluid or air.Full entry . Many brands are kept refrigerated and need about 20 to 40 minutes to warm to room temperature, so plan ahead. They are washed out at the end of the case, because gel left behind raises the eye pressure.
- local anesthesiaLOH-kul an-es-THEE-zhuhNumbing medicine applied to or injected into one small area, so a procedure there is not felt while the person stays awake.Full entry adjuncts: hyaluronidase, an enzymeEN-zimeA protein that speeds up a chemical reaction in the body without being used up.Full entry mixed with the block's anesthetican-us-THET-ikA drug that causes loss of feeling, with or without loss of consciousness.an- withoutesthesi/o feeling, sensation-ic relating toFull entry so it spreads through the tissue, and not used in infected, inflamed or cancerous tissue; and epinephrine, which narrows vessels, makes the block last longer and reduces bleeding. The topical anesthetics and block drugs themselves are chapter 13, and the block drugs count toward the maximum doses that chapter 13 teaches.
- Enzymes and zonulysis: zonulysis (zonulolysis) is the use of an enzyme, alpha-chymotrypsin, to dissolve the zonules, so the whole lens can be lifted out in its capsule in an intracapsular cataractKAT-uh-raktClouding of the lens of the eye.Full entry extraction, an older operation rarely done today.
- Dyes and stains: trypan blue is injected into the front chamber to stain the lens capsule so the surgeon can see it to open it, and the extra is washed out at once; fluorescein strips stain the cornea; a marking pen with methylene blue can mark a retinalRET-ih-nulRelating to the retina, the thin layer at the back of the eye that senses light and sends images to the brain.retin/o retina-al relating toFull entry tear on the scleraSKLAIR-uhThe tough white outer layer of the eyeball.Full entry . Fluorescein and indocyanine green are also given into a vein for angiographyan-jee-OG-ruh-feeAn imaging test that shows blood vessels by injecting a contrast dye and taking x-ray, CT or MRI pictures.angi/o vessel-graphy process of recordingFull entry , a diagnostic test.
- Antibiotics: drops and ointments (such as polymyxin B with bacitracinbas-ih-TRAY-sinAn antibiotic used mostly as an ointment on the skin to prevent infection in minor cuts, scrapes and burns.Full entry , neomycinnee-oh-MY-sinAn aminoglycoside antibiotic used by mouth to reduce gut bacteria and on the skin in antibiotic ointments.Full entry combinations, gentamicinjen-tuh-MY-sinAn aminoglycoside antibiotic, usually given IV or IM, used for serious infections caused by certain bacteria.Full entry , tobramycintoh-bruh-MY-sinAn aminoglycoside antibiotic given by IV, by inhalation or as eye drops for serious gram-negative infections.Full entry and fluoroquinolones such as moxifloxacin), injections under the conjunctivakon-junk-TY-vuhThe thin, clear layer that lines the inside of the eyelids and covers the white of the eye.Full entry at the end of the case (such as cefazolinsef-AY-zoh-linA first-generation cephalosporin antibiotic given by injection into a vein or muscle.Full entry or gentamicin), and antibiotics injected into the front chamber (intracameral), which a review of the research found well supported by evidence for preventing endophthalmitis, an infection inside the eye.
Other drugs you will see in eye cases:
- Steroids and NSAIDs: dexamethasonedek-suh-METH-uh-zohnA strong, long-acting corticosteroid drug that reduces inflammation and calms the immune system.Full entry , betamethasonebay-tuh-METH-uh-zoneA strong, long-acting corticosteroid drug given as an injection or used on the skin.Full entry and methylprednisolonemeth-il-pred-NIS-oh-loneA corticosteroid drug given by mouth, IV or injection to reduce inflammation and calm the immune system.Full entry injected under the conjunctiva, and steroid drops, calm inflammation after surgery; some come combined with an antibiotic. NSAID drops such as ketorolacKEE-toh-roh-lakA strong NSAID pain drug, given by injection, by mouth or as a nasal spray, for short-term moderate to severe pain.Full entry reduce inflammation, and flurbiprofen helps keep the pupil from narrowing during surgery.
- Antimetabolites: mitomycin and fluorouracilflure-oh-YOOR-uh-silA cancer drug that blocks DNA building in fast-growing cells, given by IV or used as a skin cream.Full entry (5-FU) are applied on small sponges to slow scarring in glaucoma filtering surgery and pterygium excisionek-SIZH-unCutting out tissue, such as a growth or damaged area, during surgery.Full entry . They are hazardous drugs: handle and discard them by Occupational Safety and Health AdministrationOH-shuh (said as a word)The US federal agency, part of the Department of Labor, that sets and enforces rules to keep workplaces safe.Full entry rules and your facility's policy for antineoplastican-tee-nee-oh-PLAS-tikA drug used to treat cancer by killing cancer cells or stopping them from growing and dividing.anti- againstneo- newplas growth, formation-tic relating toFull entry , take the exposed instruments off the field in a basin, and change gloves.
- Pressure-lowering drugs: acetazolamide (Diamox) and mannitolMAN-ih-tolAn osmotic diuretic, given by IV, that draws water out of tissues into the blood so the kidneys can remove it.Full entry , given into a vein by the anesthesia provideran-us-THEE-zhuh pruh-VY-derThe licensed professional who gives anesthesia and watches over the client's breathing and vital functions during a procedure.Full entry , and timolol drops. A patient who receives mannitol often needs a urinary catheter.
- Gases and liquids that hold the retinaRET-ih-nuhThe thin layer of light-sensing tissue at the back of the inside of the eye.Full entry in place: sulfur hexafluoride (SF6) and perfluoropropane (C3F8) gases, silicone oil and liquid perfluorocarbons, taught with retinal surgery below.
9Cataract surgery: the lens
Phacoemulsification with an intraocular lens
What and why: cataractKAT-uh-raktClouding of the lens of the eye.Full entry extraction removes the cloudy lens and replaces it with an intraocular lens (IOL), restoring the focusing power the lens provided. More than three million lens extractions are done each year in the United States. Today it is almost always an extracapsular cataract extraction (ECCE): the nucleus and cortexKOR-teksThe outer layer of an organ, especially the folded gray outer layer of the brain.cortic/o cortex, outer layerFull entry come out and the capsule stays, as a bag to hold the new lens. Phacoemulsification, breaking up the lens with ultrasound and suctioningSUK-shun-ingRemoving mucus, saliva or other secretions from the mouth, nose or airway with a tube connected to a suction source.Full entry it out, is the usual way. Bilateral cataracts are done at separate times, usually 4 to 8 weeks apart, so the patient may see unevenly in between.
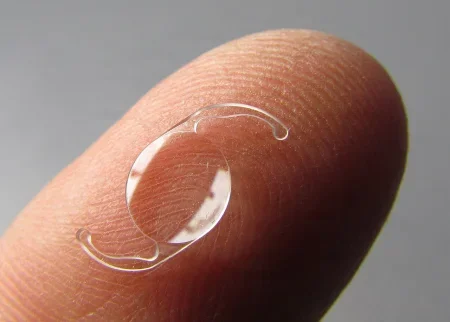
The intraocular lens: IOLs are made of silicone or acrylic and come in powers measured in diopters. The surgeon works out the power from the corneaKOR-nee-uhThe clear, dome-shaped layer at the front of the eye, over the iris and pupil.Full entry 's curve and the eye's length before the day of surgery.
- Types: a monofocal lens focuses at one distance, usually far, so the patient still wears glasses to read; multifocal and accommodating lenses give near and far vision; a toric lens also corrects astigmatism.
- Where it goes: a posterior chamber lens sits in the capsular bag behind the iris, its most natural place. An anterior chamber lens, in front of the iris, is used when there is no capsule to hold a lens, as after a torn capsule with vitreous loss.
- Folding it: foldable lenses go through an incision of 2.6 mm or less. The scrub folds the lens into the injector exactly as its maker directs, because a lens folded wrong can open upside down or backward, spoiling the result and inflaming the eye when the surgeon has to fix it. Some lenses come already loaded in their injector.

Before surgery: in the holding area, drops dilate the pupil (phenylephrinefen-il-EF-rinA drug that tightens blood vessels, given IV to raise low blood pressure and used in nose sprays and eye drops.Full entry , with a cycloplegic such as tropicamide), an nonsteroidal anti-inflammatory drugnon-STAIR-oy-dul an-tee-in-FLAM-uh-tor-ee DRUGA drug that relieves pain, fever and inflammation and is not a steroid, such as ibuprofen or naproxen.non- notanti- againstinflamm/o inflammationFull entry drop such as flurbiprofen helps keep it wide, and a topical anesthetican-us-THET-ikA drug that causes loss of feeling, with or without loss of consciousness.an- withoutesthesi/o feeling, sensation-ic relating toFull entry such as tetracaine numbs the eye. The patient keeps the eye closed so the cornea does not dry. In the OR, the patient is asked to look at the microscope light; if the patient cannot keep the eye open and still, the surgeon may give a facial nerveFAY-shul NERVThe seventh cranial nerve, which moves the muscles of the face and carries taste from the front of the tongue.Full entry or retrobulbar block. A patient on long-term glaucomaglaw-KOH-muhAn eye disease in which the optic nerve is damaged, usually with raised pressure inside the eye, leading to loss of vision.Full entry treatment or an alpha-blockerBLOK-erA drug that stops a receptor or channel in the body from being activated, so the usual effect does not happen.Full entry such as tamsulosintam-SOO-loh-sinAn alpha-1 blocker that relaxes the muscle of the prostate and bladder neck so urine flows more easily.Full entry , or with diabetes, is more prone to a floppy iris that prolapsePROH-lapsThe slipping or falling of an organ or part from its normal position.Full entry and a pupil that narrows despite the drops; the setup includes a pupil expander.
Position, prep and drape: supine, the head steady on its headrest; povidone-iodinePOH-vih-done EYE-uh-dineA brown antiseptic solution of iodine used to kill germs on the skin before procedures and on wounds.Full entry drops in the eye and a routine eye prep; a head drape and an adhesive eye drape.
Setup: a cataract set with the phaco handpiece and tips, the irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry and aspirationas-puh-RAY-shunBreathing food, liquid, saliva or stomach contents into the airway and lungs; also, drawing fluid out with suction or a needle.Full entry (I/A) handpiece and tips, BSS, capsulorhexis forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry or a cystotome, a hydrodissection cannulaKAN-yoo-luhA thin tube placed into the body or a body opening to deliver or remove fluid or air.Full entry , a chopper or second instrument, lens manipulators and a positioning hook such as the Sinskey, a pupil expander such as iris hooks or a ring, IOL forceps, and the IOL with its injector. On hold: an anterior vitrectomy handpiece, 10-0 nylon or polyglactin sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry and a second IOL.


Medications: BSS for irrigation, sometimes with epinephrineep-ih-NEF-rinA hormone and drug, also called adrenaline, that raises heart rate and blood pressure and opens the airways.Full entry added, preservative-free lidocaineLY-doh-kaynA local anesthetic that numbs an area, also given by IV to treat some fast, abnormal heart rhythms.Full entry for the front chamber, viscoelastic, trypan blue to make the capsule easier to see, a miosismy-OH-sisNarrowing (constriction) of the pupil of the eye.Full entry , an antibiotic for injection into the front chamber at the end, and antibiotic and steroidSTAIR-oydA fat-based chemical built from cholesterol; the group includes hormones such as cortisol and estrogen, and many drugs.ster/o solid-oid likeFull entry drops.
Key steps:
- The speculumSPEK-yoo-lumAn instrument used to open and hold open a body opening, such as the vagina, so the inside can be seen.Full entry goes in, and the surgeon makes a 1 mm side-port stab incision (a paracentesis) into the front chamber. Preservative-free lidocaine may be injected through it.
- The instant the chamber is opened, aqueous leaks out and its pressure falls, so the surgeon fills it with viscoelastic to keep it deep and protect the cornea's lining.
- The main incision is made with a keratome or diamond knife, in clear cornea or near the limbus. An incision in clear cornea can be placed to reduce the patient's astigmatism.
- Capsulorhexis: a continuous round opening is torn in the front of the capsule with capsulorhexis forceps or a cystotome. This step must give a round, stable opening into the bag.
- Hydrodissection: BSS squirted under the capsule through a fine blunt cannula frees the nucleus so it turns in the bag.
- Phaco: the probe sculpts or grooves the nucleus, and a chopper or second instrument passed through the side port helps crack it into quarters, which the probe emulsifies and suctions away. If the nucleus is too hard to emulsify, the surgeon can press it out by hand instead (a manual extracapsular extraction).
- The I/A tip strips the remaining cortex from the capsule, and the capsule may be polished. Working from the edges, not the center, avoids drawing vitreous forward.
- Viscoelastic fills the bag. You fold the lens into the injector, check it, and state its model and power as you pass it; the surgeon injects it into the bag, where it unfolds, and centers it with a hook or the I/A tip.
- The I/A tip washes out the viscoelastic. Many incisions seal themselves; others get a 10-0 nylon stitch. An antibiotic may be injected into the front chamber, a miotic may be used, and antibiotic or combination drops go on; protocols against TASS avoid ointment after cataract surgery, because it can slip into the front chamber.
Throughout the case, keep the cornea moist with BSS.
at the lens implant, you say the model and power out loud as you pass it. The lens is checked against the patient's record just before it goes in, every time.
Specimen, counts and dressing: the lens is suctioned away in fragments, and facility policy decides whether anything goes to pathologypuh-THOL-uh-jeeThe study of disease and its causes and effects, or the disease changes found in a person or tissue.path/o disease-logy study ofFull entry . Sharps are counted, and any sponges used. An eye pad and a shield, or a shield alone.
Wound class: I, clean.
After surgery: most patients go home within a few hours. Teach them to wear the shield as the surgeon directs, not to sleep on the operative side or the stomach for the first week, not to rub or squeeze the eye, and to avoid strenuous exercise for 2 to 3 weeks. Sudden pain, sudden loss of vision, light sensitivitysen-sih-TIV-ih-teeHow strongly something responds; in lab work, which drugs stop a germ, or how well a test finds people who have a disease.Full entry or a severe headache must be reported at once. Complications are rare: infection (endophthalmitis), bleeding, inflammation, high or low eye pressure, double vision and vision loss. Months or years later, cells can regrow on the capsule and cloud it; a YAG laser then opens a hole in the center of the capsule (a capsulotomy). Cataract surgery also raises the risk of retinalRET-ih-nulRelating to the retina, the thin layer at the back of the eye that senses light and sends images to the brain.retin/o retina-al relating toFull entry detachment.
When the capsule tears: anterior vitrectomy
If the back of the capsule tears, vitreous can push forward into the front chamber. The surgeon stops phaco and switches to vitrectomy, either with the phaco machine's vitrectomy mode or a separate cutter. With irrigation running, the cutter removes the vitreous from the front of the eye until none is left there and the iris falls back; vitreous can also be cut with Westcott scissors after drawing it up with a cellulose sponge. The pupil is constricted with acetylcholineuh-see-tul-KOH-leenA chemical messenger that nerves release to signal muscles, glands and other nerves.Full entry , the chamber is refilled, and a lens is placed where support allows. Have the vitrectomy setup ready on every cataract case.
Femtosecond laser-assisted cataract surgery (FLACS)
A femtosecond laser fires pulses one quadrillionth of a second long, which cut precisely without heat. Before phaco, the laser is docked on the eye through a cone, with a speculum in place, and it makes accurate incisions and an even, predictable capsulorhexis and can precut the nucleus. Less ultrasound energy is then needed, and one study found less damage to the cornea's lining and a faster return of sight. The laser helps most with hard, dense cataracts. It also helps with eyes that have had corneal surgery to correct vision, such as LASIK, and it can correct a small amount of astigmatism. Complication rates match those of standard surgery, but docking can leave the eye bloodshot for a few days. The phaco steps then follow as above, and the wound class (I, clean) and the aftercare are those of phacoemulsification.
Two more lens cases
- Intracapsular extraction (ICCE): the whole lens, capsule and all, is lifted out, once with a cryoprobe after an enzymeEN-zimeA protein that speeds up a chemical reaction in the body without being used up.Full entry had loosened the zonules. It leaves no capsule to hold a posterior chamber lens and is now rarely done, except for a dislocationdis-loh-KAY-shunAn injury in which the ends of bones that meet at a joint are forced out of their normal position.Full entry lens.
- Children's cataracts: a cataract that affects a child's sight is removed, because a child's vision develops only with clear images; otherwise amblyopia follows. After an exam under anesthesiaan-us-THEE-zhuhLoss of feeling or sensation, often brought on by drugs so that surgery or a procedure can be done without pain.an- withoutesthesi/o feeling, sensation-ia conditionFull entry with an A-scan, the soft lens is removed with a vitrector and an IOL is placed or the child is left without a lens; a child with an IOL wears bifocals, because the IOL cannot accommodate.
10The cornea, conjunctiva and iris
Penetrating keratoplasty (corneal transplant)
What and why: a penetrating keratoplasty replaces the full-thicknessful-THIK-nisGoing through every layer of the skin, or every layer of another tissue such as the wall of an organ.Full entry of a scarred or cloudy corneaKOR-nee-uhThe clear, dome-shaped layer at the front of the eye, over the iris and pupil.Full entry with a donor cornea, to restore sight when the retinaRET-ih-nuhThe thin layer of light-sensing tissue at the back of the inside of the eye.Full entry and optic nerveOP-tik nervThe nerve that carries visual signals from the back of the eye to the brain; the second cranial nerve.Full entry still work. The common reasons are burns, infection, scarring after injury, inherited corneal disease, swelling after earlier eye surgery and keratoconus. The cornea has no blood vessels, so donor tissue needs no antigenAN-tih-jenA substance, often a protein on a germ or cell, that the immune system recognizes and responds to.anti- against (short for antibody)-gen something that producesFull entry matching, and corneal transplants are among the most successful of all transplants.
Partial-thickness graftGRAFTTissue or a man-made material moved into place in surgery to replace or repair a damaged part.Full entry : when only some layers are diseased, the surgeon replaces just those. A deep anterior lamellar keratoplasty (DALK) replaces the front layers and keeps the patient's own endothelium, lowering the risk of rejection; it suits keratoconus and scars that do not go all the way through. An endothelial keratoplasty, such as Descemet stripping endothelial keratoplasty (DSEK), replaces only the inner layer, for diseases such as Fuchs dystrophyDIS-truh-feeA condition in which a muscle or other tissue weakens and wastes away over time.dys- bad-trophy nourishment or growthFull entry , in which the endothelial cells die and the cornea swells. It heals faster with less astigmatism, and an air bubble injected under the graft presses it into place.
The donor cornea: it comes from an eye bank, cut as a corneoscleral button or as a whole eye, refrigerated in a storage medium such as Optisol-GS, which keeps it up to 14 days. The donor is screened for diseases such as HIVaych-eye-VEE (said as letters)Human immunodeficiency virus: a virus that infects and destroys immune cells called CD4 T cells.Full entry and hepatitis Bhep-uh-TY-tis BEEA liver infection caused by the hepatitis B virus.hepat/o liver-itis inflammationFull entry and C. Handle it as the gift it is. Eye donation and recovery are taught with the eye removals below.

Before surgery: local anesthesiaLOH-kul an-es-THEE-zhuhNumbing medicine applied to or injected into one small area, so a procedure there is not felt while the person stays awake.Full entry with a block, often with a facial nerveFAY-shul NERVThe seventh cranial nerve, which moves the muscles of the face and carries taste from the front of the tongue.Full entry block, or general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry . The patient must not be able to squeeze the lids once the cornea is out, because pressure from behind can push the eye's contents out or cause bleeding inside the eye, so many surgeons give mannitolMAN-ih-tolAn osmotic diuretic, given by IV, that draws water out of tissues into the blood so the kidneys can remove it.Full entry beforehand to lower the pressure. If a block is planned, the skin behind the ear is prepped too. The microscope is positioned and locked before the prep, then swung aside.
Setup: a corneal transplant set with trephines, a punch block, corneal scissors, a fixation ring (such as a Flieringa ring), fine forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry , 10-0 nylon, viscoelastic and BSS. The donor tissue is prepared on its own separate table and Mayo, and instruments are not shared between the two, so nothing passes from one eye to the other.

Key steps:
- A speculumSPEK-yoo-lumAn instrument used to open and hold open a body opening, such as the vagina, so the inside can be seen.Full entry , then a fixation ring or bridle sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry to support the eye.
- The donor button is placed on a block with its outer surface down, and a trephine punches a disc a little larger than the opening to be made in the patient's eye, for a proper fit. A drop of storage medium keeps it moist until it is used, and some of the medium may go to the lab for culture.
- The surgeon trephines the patient's cornea, by hand or with a suction trephine, and finishes the cut with corneal scissors. Receive the patient's cornea as a specimen. The eye is now "open sky", wide open to contamination, so have the graft, the next instruments and the sutures ready at once.
- Any extra work is done now, such as a peripheral iridectomy or a cataractKAT-uh-raktClouding of the lens of the eye.Full entry extraction with a lens implant.
- The graft is laid in the opening and anchored with four stitches at the cardinal points, then sewn with interrupted or running 10-0 nylon.
- Air, BSS or viscoelastic re-forms the front chamber and keeps the iris off the suture line; the wound is checked for a leak.
- Antibiotic and steroidSTAIR-oydA fat-based chemical built from cholesterol; the group includes hormones such as cortisol and estrogen, and many drugs.ster/o solid-oid likeFull entry injections or drops, ointment, an eye pad and a shield.
Specimen: the patient's cornea, and a culture of the storage medium if the surgeon orders it.
Wound class: I, clean.
After surgery: full recovery of sight can take up to a year. The risks are bleeding, infection, glaucomaglaw-KOH-muhAn eye disease in which the optic nerve is damaged, usually with raised pressure inside the eye, leading to loss of vision.Full entry , swelling and rejection, which can happen weeks or years later. Pain, light sensitivitysen-sih-TIV-ih-teeHow strongly something responds; in lab work, which drugs stop a germ, or how well a test finds people who have a disease.Full entry , redness and dimming vision are warning signs that need care at once, because steroids started early can stop a rejection.
Laceration repair
- Cornea: a cut through the cornea is closed with 10-0 sutures placed edge to edge, or with a tissue adhesive approved for the eye, which sets on contact and seals the wound. Antibiotics may be injected under the conjunctivakon-junk-TY-vuhThe thin, clear layer that lines the inside of the eyelids and covers the white of the eye.Full entry before the dressing.
- Conjunctiva: tears, and gaps left after removing a growth, are usually closed by freeing the edges and sewing them.
- A ruptured globe: the eye is imaged first to look for foreign bodies and hidden damage. An eye too damaged to see again, or a blind, painful eye, may have to be removed.
- The repair: done under the microscope with 9-0 or 10-0 sutures. When a cut crosses both the cornea and the scleraSKLAIR-uhThe tough white outer layer of the eyeball.Full entry , a first stitch at the limbus lines up the edges, and the cornea is closed before the sclera. Antibiotic drops or ointment follow.
Wound class: a fresh accidental wound is Class III; an old one with dead (devitalized) tissue, or an infected one, is Class IV.
Pterygium excision
What and why: a pterygium is a fleshy, triangular growth of conjunctiva that spreads from the inner corner onto the cornea, more common in people who work outdoors. It is not cancer, but it tends to come back, so surgery usually waits until it affects vision.
Steps: under topical, peribulbar or retrobulbar anesthesiaan-us-THEE-zhuhLoss of feeling or sensation, often brought on by drugs so that surgery or a procedure can be done without pain.an- withoutesthesi/o feeling, sensation-ia conditionFull entry , the surgeon cuts the growth off the cornea and sclera, seals bleeding at the limbus with a batteryBAT-uh-reeIn law, touching a person on purpose without their consent.Full entry cautery or bipolarby-POH-lerHaving two poles or two opposite ends; most often used as a short form of bipolar disorder.bi- twopolar having polesFull entry , and may smooth the surface with a diamond burr. The bare sclera is covered with a graft of the patient's own conjunctiva or with amniotic membrane, held with fine sutures or fibrin glue. Mitomycin may be applied to lower the chance of regrowth, handled as a hazardous drug.
Wound class: I, clean; no tract is entered.
Iridotomy and iridectomy
What and why: both make an opening in the iris, so aqueous can pass from the posterior to the anterior chamber again. This relieves the block in angle-closure glaucoma: the iris falls back from the drainage angle and fluid can reach the trabecular meshwork. An iridotomy is a small hole, usually made with a laser; an iridectomy removes a piece of iris. A miosismy-OH-sisNarrowing (constriction) of the pupil of the eye.Full entry may be used to narrow the pupil for a laser iridotomy, and the pressure may rise or the eye may inflame afterward.
Before a surgical iridectomy: a retrobulbar block or general anesthesia, supine with the head on a headrest, and the routine eye prep and drape; if the pressure is very high, drugs to lower it are given before the incision.
Surgical peripheral iridectomy: done when a laser cannot be used, as with a cloudy cornea or an inflamed eye, and often as part of a trabeculectomy. The surgeon makes a small incision at the upper limbus or in clear cornea, draws a fold of iris out with forceps and snips it off, then settles the iris back in place by stroking the cornea gently with a blunt instrument, such as a spatula or muscle hook, or with a stream of BSS. The incision is closed with 10-0 nonabsorbable suture, or absorbable suture at the limbus, and an antibiotic may be injected into the front chamber before the eye pad.
Wound class: I, clean.
Refractive surgery
Laser vision correction, such as LASIK and PRK, reshapes the cornea with an excimer laser to correct nearsightedness, farsightedness and astigmatism. It is mostly done in physicians' offices or physician-owned centers rather than in hospitals or ambulateAM-byuh-laytTo walk, or to help a client walk.Full entry surgery centers.
11Glaucoma surgery
glaucomaglaw-KOH-muhAn eye disease in which the optic nerve is damaged, usually with raised pressure inside the eye, leading to loss of vision.Full entry operations lower the pressure in the eye, either by opening a new drain for aqueous humor or by making less of it. They save the sight that is left; they do not bring back what is lost. Glaucoma operations are clean cases, Class I.
Trabeculectomy
What and why: a trabeculectomy is a filtering operation. The surgeon removes a small block of tissue containing part of the trabecular meshwork, under a flap of scleraSKLAIR-uhThe tough white outer layer of the eyeball.Full entry , to make a new channel from the front chamber. Fluid seeps out under the flap into a small blister under the conjunctivakon-junk-TY-vuhThe thin, clear layer that lines the inside of the eyelids and covers the white of the eye.Full entry , the bleb, where the body absorptionub-ZORP-shunThe taking in of a substance, such as a drug or a nutrient, into the bloodstream.Full entry it. It is done when other treatment does not control the pressure, and it is often combined with cataractKAT-uh-raktClouding of the lens of the eye.Full entry extraction and a lens implant.
Before surgery: local anesthesiaLOH-kul an-es-THEE-zhuhNumbing medicine applied to or injected into one small area, so a procedure there is not felt while the person stays awake.Full entry with a retrobulbar block, or general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry ; if the pressure is very high, drugs to lower it are given before the incision.
Setup: trabeculectomy instruments with a diathermy or cautery unit, fine blades such as Beaver blades, Vannas scissors or a punch, the antimetabolite drug, eye sponges for applying it, and 10-0 nylon and absorbable sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry ; a drainage device on hold if the surgeon may need one.
Key steps:
- A speculumSPEK-yoo-lumAn instrument used to open and hold open a body opening, such as the vagina, so the inside can be seen.Full entry , and often a tractionTRAK-shunA steady pulling force applied to a body part with weights, ropes and pulleys.Full entry suture of 4-0 silk under the superior rectusREK-tusLatin for straight; the name of several straight muscles, such as the rectus abdominis of the abdomen and the rectus femoris of the thigh.Full entry muscle, to steady the eye.
- The conjunctiva and Tenon capsule are opened at the limbus with toothed forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry and a blade, then freed from the sclera with Westcott scissors to make a conjunctival flap; bleeding is sealed with bipolarby-POH-lerHaving two poles or two opposite ends; most often used as a short form of bipolar disorder.bi- twopolar having polesFull entry or cautery.
- The antimetabolite: small sponges soaked in mitomycin or fluorouracilflure-oh-YOOR-uh-silA cancer drug that blocks DNA building in fast-growing cells, given by IV or used as a skin cream.Full entry are placed between the flap and the sclera for the time the surgeon directs (the references give about 1 to 5 minutes), then removed and the area is washed with plenty of BSS. Hand off the instruments they touched, in a basin, and change gloves.
- A partial-thickness flap of sclera, square or triangular, is outlined with cautery and cut with a fine blade, then dissectdy-SEKT, or dih-SEKTTo cut apart or separate tissues carefully during surgery.Full entry forward from its tip.
- A small stab through the corneaKOR-nee-uhThe clear, dome-shaped layer at the front of the eye, over the iris and pupil.Full entry (a paracentesis) lets aqueous out and is used later to refill the chamber.
- Under the flap, a block of deep tissue at the limbus, including part of the meshwork, is cut out with Vannas scissors or a punch, opening the new channel into the front chamber.
- A peripheral iridectomy is made, and one is always made if the iris prolapsePROH-lapsThe slipping or falling of an organ or part from its normal position.Full entry into the wound.
- Interrupted 10-0 nylon sutures close the scleral flap; when you follow the suture, do not put too much tension on it. Tenon capsule and the conjunctiva are closed with fine absorbable suture. BSS is injected into the chamber, and an eye sponge held on the wound checks for a leak.
- Antibiotic and steroidSTAIR-oydA fat-based chemical built from cholesterol; the group includes hormones such as cortisol and estrogen, and many drugs.ster/o solid-oid likeFull entry injections under the conjunctiva, ointment, a pad and a shield.
After surgery: the operation works only if a bleb forms in the first days. A leaking bleb may need a bandage contact lens or repair, and a cataract may form later.
Laser trabeculoplasty
A trabeculoplasty is a laser treatment of the trabecular meshwork that helps aqueous drain out. It can be the first treatment for open-angle glaucoma or be used when drops fail or are not tolerated. Argon laser trabeculoplasty (alanine aminotransferaseAL-uh-neen uh-mee-noh-TRANS-fer-ayceAn enzyme found mostly in the liver, measured in the blood as a test of liver cell health.Full entry ) is one type; selective laser trabeculoplasty (SLT), with a frequency-doubled Nd:YAG laser, is preferred because it uses less energy and causes less inflammation, and it can be repeated. One review reports a good pressure drop at first in more than three quarters of eyes treated with the argon laser, but 30 percent to more than half need more surgery within 5 years.
Glaucoma drainage device (tube shunt)
What and why: when a filtering operation fails, the surgeon implants an aqueous shuntSHUNTA passage that moves blood or other fluid from one place to another, either made by a surgeon or present in the body.Full entry , or glaucoma drainage device: a fine tube whose tip sits in the front chamber, attached to a plate sewn to the sclera far back under the conjunctiva. Aqueous drains out through the tube to the plate, which acts as a reservoirREZ-er-vwarA place where germs live and multiply, such as a person, animal, water or soil.Full entry . Some devices have a valve and some do not.
Before surgery: usually local anesthesia with a retrobulbar or peribulbar block. The device and its patch graftGRAFTTissue or a man-made material moved into place in surgery to replace or repair a damaged part.Full entry (donor sclera or pericardiumpair-ih-KAR-dee-umThe thin, two-layered sac that surrounds the heart.peri- aroundcardi/o heart-um a structureFull entry ) may be soaked in an antibiotic solution, and both are recorded as implants.
Priming: one maker's valved device must be primed before it is implanted, by injecting about 1 mL of BSS or sterile water through the tube with a blunt 26-gauge cannulaKAN-yoo-luhA thin tube placed into the body or a body opening to deliver or remove fluid or air.Full entry ; a sharp needle can puncture the tube. A device that will not prime is not used. Follow the maker's instructions for the device in your room.
Key steps: the rectus muscles are looped with traction sutures, the conjunctiva is opened, and the plate is placed by measurement and sewn to the sclera. The surgeon checks that the tube is open, then may close it for now with an occluding suture. A needle makes a tunnel into the front chamber, the tube is trimmed, passed into the chamber and sewn down, and a patch graft covers it. The conjunctiva is closed, and an antibiotic may be injected under it before the pad.
After surgery: inflammation and a rise in pressure may follow, usually settling within 4 to 6 weeks. Pressure that drops too low, clogging, scarring around the plate, trouble moving the eye and injury to the cornea are the other risks.

Other glaucoma operations
- A stentstentA small tube, often of metal mesh, placed inside a vessel or duct to hold it open.Full entry at cataract surgery: for open-angle glaucoma, a tiny titanium tube can be placed in the trabecular meshwork through the cataract incision at the end of the case, viewed through a gonio prism with the head turned.
- Canaloplasty: a microcatheter is threaded into the canal of Schlemm and viscoelastic is injected to widen it.
- Children: in congenitalkun-JEN-ih-tulPresent at birth.con- withgen birth, origin-al relating toFull entry glaucoma, a goniotomy (cutting into the meshwork) or a trabeculotomy (opening the canal of Schlemm into the chamber from outside, through a scleral flap) comes first; trabeculectomy, drainage devices and cyclodestruction come next.
- Cyclodestruction: freezing (cryotherapy) or a diode laser destroys part of the ciliary body, so it makes less aqueous.
12The retina and vitreous
retinalRET-ih-nulRelating to the retina, the thin layer at the back of the eye that senses light and sends images to the brain.retin/o retina-al relating toFull entry surgery is often urgent, because a detached retinaRET-ih-nuhThe thin layer of light-sensing tissue at the back of the inside of the eye.Full entry threatens sight, and some of these cases are long.
Pars plana vitrectomy
What and why: a vitrectomy removes all or part of the vitreous. Through the pars plana, where there is no retina, the surgeon reaches the back of the eye with little risk of tearing the retina. It is done to clear blood or clouding from the vitreous, for advanced diabetic eye disease, severe injuries and foreign bodies, scar tissue on the retina, detachments from large tears, macular holes, infection inside the eye (endophthalmitis), and to take a sample of the vitreous. The surgeon may also peel membranes off the retina and seal vessels.
Before surgery: local anesthesiaLOH-kul an-es-THEE-zhuhNumbing medicine applied to or injected into one small area, so a procedure there is not felt while the person stays awake.Full entry with a retrobulbar block and sedationsih-DAY-shunA calm, relaxed or sleepy state brought on by drugs, or the use of drugs to cause it.sed calm, settle-ation processFull entry . A scleraSKLAIR-uhThe tough white outer layer of the eyeball.Full entry buckle may be needed in the same operation, so be ready for one.
Setup: the vitrectomy machine and pack, the microscope with a contact lens or a wide-angle viewing system mounted on it, small trocarTROH-karA sharp or bladed instrument inside a tube (cannula), used to pierce a body wall and leave the tube in place as a port.Full entry and cannulaKAN-yoo-luhA thin tube placed into the body or a body opening to deliver or remove fluid or air.Full entry (such as 23 or 25 gauge), a light pipe and sometimes a chandelier light, an infusion of buffered BSS, picks, microforceps and microscissors, an endolaser and cryoprobe, soft-tipped cannulas for draining fluid, scleral plugs, and the tamponade the surgeon plans: air, gas or silicone oil. Culture tubes are kept ready.
Your jobs: attach the handpieces to their sterile tubing and hand the ends off to be connected; prime the infusion line and clear every air bubble; test the cutter and the suction before it reaches the eye; know that the surgeon runs the cutter with a foot switch; and remember that the infusion is stopped before the instruments come out of the eye.
Key steps:
- A speculumSPEK-yoo-lumAn instrument used to open and hold open a body opening, such as the vagina, so the inside can be seen.Full entry . Three openings are made through the pars plana, about 3 to 4 mm behind the limbus, often with small trocar-cannulas: one for the infusion, one for the light and one for the cutter or other instruments. The infusion cannula's position inside the eye is checked.
- The microscope and viewing system are brought into place. If a dense cataractKAT-uh-raktClouding of the lens of the eye.Full entry blocks the view, the lens is removed first (a lensectomy).
- The surgeon cuts and removes the vitreous under direct view, then treats the problem: peeling membranes, sealing tears with the endolaser, draining fluid from under the retina and flattening it with a heavy liquid, then exchanging the fluid for air, gas or silicone oil.
- The cannulas come out; small sites often seal without sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry , and larger ones are closed with fine suture. Vitreous washings may go for culture.
- steroidSTAIR-oydA fat-based chemical built from cholesterol; the group includes hormones such as cortisol and estrogen, and many drugs.ster/o solid-oid likeFull entry or antibiotic injections under the conjunctivakon-junk-TY-vuhThe thin, clear layer that lines the inside of the eyelids and covers the white of the eye.Full entry , a pad and a shield.
Holding the retina in place (tamponade):
- Gas: sulfur hexafluoride (SF6) or perfluoropropane (C3F8), drawn through a 0.22-micron filter and mixed with filtered air; the stronger the mix, the longer the bubble lasts. Both gases expand after injection, SF6 to about 2.5 times its volume and C3F8 to about 4 times, over about 2 days, and the eye's own fluid slowly replaces them over weeks to a few months.
- Silicone oil: for complicated cases or patients who cannot keep their head down. It can stay in the eye, but it should be taken out within about a year once the retina is attached and stable, which needs another operation.
- Liquid perfluorocarbon: heavier than BSS, it presses the retina flat during surgery and is removed after the repair.
let nitrous oxide run when a gas bubble is in the eye. Nitrous oxide floods into the bubble, which can swell to three times its size and drive the eye pressure up. The anesthesia provideran-us-THEE-zhuh pruh-VY-derThe licensed professional who gives anesthesia and watches over the client's breathing and vital functions during a procedure.Full entry stops it at least 20 minutes before the gas is injected.
After surgery: a patient with a gas bubble must keep the head in a set position, often facedown, for days to weeks, so the bubble presses on the tear. The patient wears a wristband naming the gas and when it was placed, and must tell any anesthesia provider about it, and must not fly or travel to high places until the gas is gone, because lower air pressure makes the bubble swell. Complications include new retinal tears, cataract, high pressure, bleeding and infection.
Wound class: I, clean.
Scleral buckling
What and why: a scleral buckle repairs a retinal detachment from outside the eye. A piece of silicone, a sponge or a band, is sewn onto the sclera over the tear, so it pushes the wall of the eye in against the detached retina, and cryotherapy, diathermy or laser seals the tear with a scar. An encircling band around the whole eye also eases the vitreous's pull on the retina.
Before surgery: general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry , or MAC with a block; a long case may call for general anesthesia.
Setup: a scleral buckle set; the silicone bands, sponges, tires and sleeves the surgeon chooses, often soaked in an antibiotic; the cryotherapy unit; an indirect ophthalmoscope with handheld lenses and a headlight; nonabsorbable mattress sutures; gases; and a vitrectomy setup on hold.
Key steps:
- The conjunctiva is opened at the limbus, and the four rectusREK-tusLatin for straight; the name of several straight muscles, such as the rectus abdominis of the abdomen and the rectus femoris of the thigh.Full entry muscles are lifted on a muscle hook and looped with tractionTRAK-shunA steady pulling force applied to a body part with weights, ropes and pulleys.Full entry sutures, tagged with small clamps. You may steady the eye by the traction sutures.
- The surgeon finds the tear with the indirect ophthalmoscope while pressing on the sclera, and marks the spot on the sclera with diathermy or a marking pen.
- The cryoprobe freezes the area under direct view until an ice ball forms over the whole lesionLEE-zhunAn area of tissue that has been damaged or has changed from normal, such as a sore, wound, lump or spot.Full entry ; diathermy or laser are alternatives.
- The buckle is sewn to the sclera with double-armed nonabsorbable mattress sutures. For an encircling band, the band passes under all four muscles and is held with a sleeve at the size the surgeon wants.
- If needed, fluid under the retina is drained through a tiny opening in the sclera, and air or gas may be injected through the pars plana.
- The traction sutures come out, the conjunctiva is closed with fine absorbable suture, and an antibiotic or steroid may be injected under it before the pad.
After surgery: some discomfort is common. Vigorous activity is avoided for about a month, and no flying while gas is in the eye. Infection, inflammation, too little blood flow to the front of the eye and a detached choroid are possible complications.
Wound class: I, clean; no tract is entered.
Pneumatic retinopexy
In a pneumatic retinopexy, the surgeon injects a bubble of air or gas into the vitreous through the pars plana. The bubble rises against the retinal break and holds it shut, and after about 7 to 10 days of healing, laser or cryotherapy seals it. The patient's head position afterward depends on where the tear is, so the bubble floats onto it, and the same gas precautionprih-KAW-shunA step taken ahead of time to prevent harm, such as the infection-control practices used with every client.Full entry apply. It may be combined with a buckle or a vitrectomy. It enters no tract, so it is Class I, clean.
Laser treatment of the retina
For proliferative diabetic retinopathydy-uh-BET-ik ret-ih-NOP-uh-theeDamage to the small blood vessels of the retina caused by diabetes.retin/o retina-pathy diseaseFull entry , laser burns scattered over the retina (panretinal photocoagulation) are the main treatment; the laser is aimed through an ophthalmoscope or a slit lamp, or with a probe inside the eye during vitrectomy. In premature babies with retinopathyret-ih-NOP-uh-theeDisease or damage of the retina, the light-sensing layer at the back of the eye.retin/o retina-pathy diseaseFull entry of prematurity, a laser mounted on an indirect ophthalmoscope or drug injections into the eye are used, and a buckle or vitrectomy for the most advanced stage.
13Strabismus correction: recession and resection
What and why: strabismus surgery lines up the eyes by changing where an eye muscle pulls. A recession weakens a muscle by detaching it and sewing it back farther behind its original insertion. A resectionrih-SEK-shunSurgery to remove part of an organ or tissue.re- back, againsect to cut-ion processFull entry strengthens a muscle by cutting out a piece and sewing the shortened muscle back at its original insertion; a plication strengthens it by folding it instead. Glasses and eye exercises are the treatments without surgery, and any other eye problem, such as a cataractKAT-uh-raktClouding of the lens of the eye.Full entry , is treated before the strabismus. In children the goal is binocular vision before amblyopia sets in.
Before surgery: general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry for children, sometimes local anesthesiaLOH-kul an-es-THEE-zhuhNumbing medicine applied to or injected into one small area, so a procedure there is not felt while the person stays awake.Full entry for adults, and a retrobulbar block may be added. The patient lies supine with the shoulders slightly raised. Both sides of the face are prepped with 5 percent povidone-iodinePOH-vih-done EYE-uh-dineA brown antiseptic solution of iodine used to kill germs on the skin before procedures and on wounds.Full entry and both eyes are left exposed, so the surgeon can compare them; the eye not being operated on is covered with a moist pad or taped shut.
Setup: a strabismus set: a wide speculumSPEK-yoo-lumAn instrument used to open and hold open a body opening, such as the vagina, so the inside can be seen.Full entry , locking fixation forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry , Westcott and Stevens tenotomy scissors, muscle hooks of several sizes, a Jameson muscle clamp, a caliper and a sterile marking pen, cautery, 4-0 silk tractionTRAK-shunA steady pulling force applied to a body part with weights, ropes and pulleys.Full entry sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry and double-armed 6-0 muscle sutures, absorbable or nonabsorbable, on the needle the surgeon prefers.
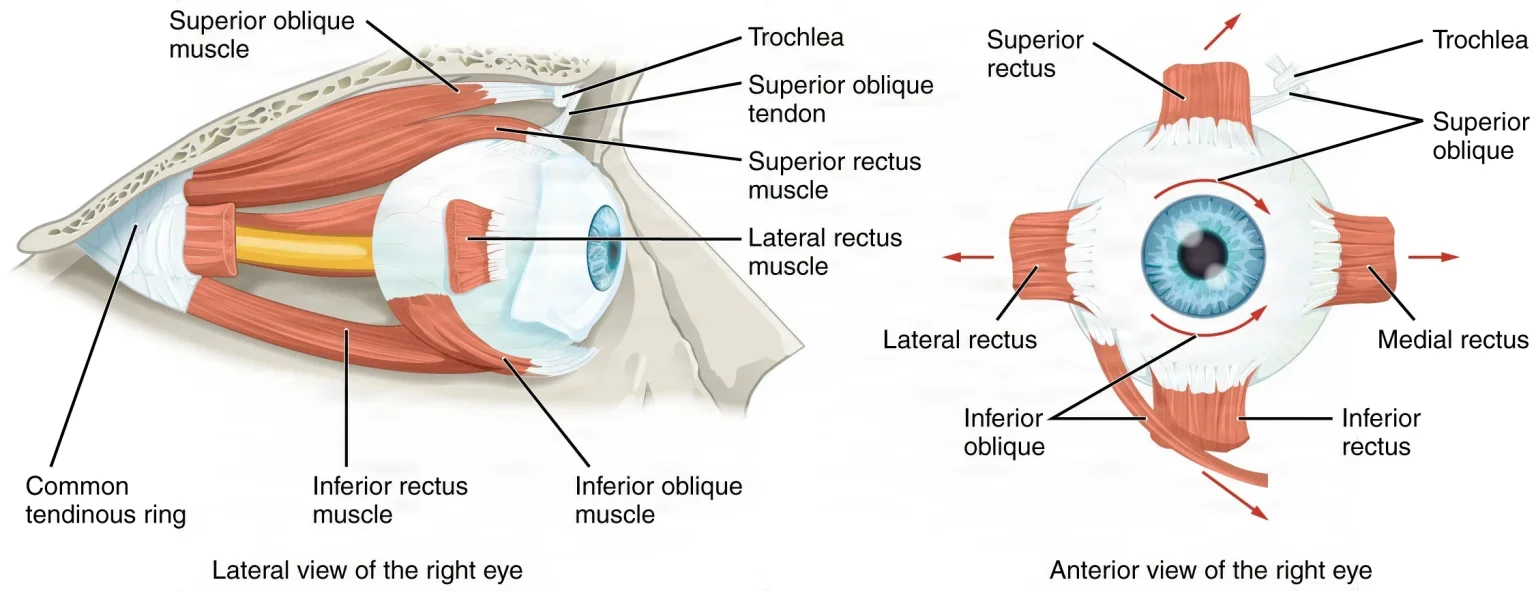



Key steps (recession):
- The speculum goes in, and the surgeon may move the eye with forceps in each direction to test whether it is held back (a forced duction test).
- Locking forceps at the limbus turn the eye, and the conjunctivakon-junk-TY-vuhThe thin, clear layer that lines the inside of the eyelids and covers the white of the eye.Full entry is opened over the muscle, at the limbus or in the fold behind it, with Westcott scissors.
- Tenon capsule is dissectdy-SEKT, or dih-SEKTTo cut apart or separate tissues carefully during surgery.Full entry down to bare scleraSKLAIR-uhThe tough white outer layer of the eyeball.Full entry , and a muscle hook is passed under the muscle and swept along it to free it from the sclera.
- A double-armed absorbable suture is woven through the muscle close to its insertion and locked at each edge. A small clamp may be left on the muscle for up to 3 minutes to stop bleeding.
- The muscle is cut from the globe with scissors.
- The caliper measures the new spot behind the old insertion, which is marked. The surgeon passes the sutures through the surface of the sclera there, pulls the muscle up to it and ties it, then measures again. Pass an empty needle holder and smooth forceps for tying.
- The conjunctiva is closed with fine absorbable suture, often on a spatula needle, and an antibiotic or combination ointment goes on. Many surgeons use no dressing; others add a pad and shield.
Resection: the first steps are the same. The surgeon measures the length to remove, places the sutures at that point behind a resection clamp, cuts the muscle in front of the clamp, removes the stump from the globe, and sews the shortened muscle back at its original insertion. The piece of muscle removed is a specimen.
Adjustable sutures: some surgeons tie the muscle with a slipknot left where it can be reached. Within about a day, with the patient awake and the eye numbed with drops, the surgeon adjusts the suture while the patient reports when the eyes line up, then ties it for good.
pulling on an eye muscle can set off the oculocardiac reflexREE-fleksAn automatic body response to something that stimulates it, which happens without thought, such as the knee jerk.Full entry , a vagal response that slows the heart. If the anesthesia provideran-us-THEE-zhuh pruh-VY-derThe licensed professional who gives anesthesia and watches over the client's breathing and vital functions during a procedure.Full entry calls a slow heart rate, the surgeon lets go of the muscle until the rate recovers.
Wound class: I, clean.
After surgery: nausea and vomiting are common, especially in children, from the vagal reflex during surgery; they are treated with antiemetican-tee-ih-MET-ikA drug that prevents or relieves nausea and vomiting.anti- againstemet vomit-ic relating toFull entry and pass on their own.
14The eyelid
Lid operations are often done under local anesthesiaLOH-kul an-es-THEE-zhuhNumbing medicine applied to or injected into one small area, so a procedure there is not felt while the person stays awake.Full entry , sometimes in the office. A head drape is used, and a corneaKOR-nee-uhThe clear, dome-shaped layer at the front of the eye, over the iris and pupil.Full entry shield or protector may be placed on the eye to guard it while the surgeon works on the lid. Chapter 38 teaches blepharoplasty and the other oculoplastic operations that plastic surgeons do.
Chalazion excision
What and why: a chalazion is a firm lump in the eyelid from a blocked meibomian gland. The trapped oil causes inflammation, and a granuloma (a lump of inflamed tissue) forms; it is not an infection, though it can become infected. Surgery is for one that does not settle with simpler treatment.
Before surgery: local anesthesia, with MAC for children and anxious adults.
Setup: a chalazion set: a chalazion clamp, chalazion curettekyoo-RETA surgical instrument with a small spoon- or loop-shaped tip used to scrape tissue.Full entry , fine-toothed forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry , a Beaver #67 or a #11 blade, Westcott scissors, a meibomian expression paddle, and bipolarby-POH-lerHaving two poles or two opposite ends; most often used as a short form of bipolar disorder.bi- twopolar having polesFull entry or a cautery pen.


Key steps:
- After local anestheticLOH-kul an-es-THET-ikA drug that blocks feeling in one part of the body without making the person unconscious.Full entry , the clamp grips the lid around the lump and everts it, which also controls bleeding and gives a firm surface to cut against.
- A vertical cut is made through the tarsal plate on the inner side of the lid; a chalazion near the skin may be opened from the outside instead.
- The contents are scraped out with a curette. Wipe the curette clean with a damp sponge between passes.
- Bleeding is sealed with bipolar or cautery; drops of BSS show the surgeon where it is bleeding. The wound is left open to drain or closed, and an eye pad goes on. The patient may put ice on it the first day.
Wound class: Class I by the CDC's definitions, because a chalazion is a chronic granuloma, not an acute inflammation or an infection, and no tract is entered; your facility's policy decides. One reference lists it as Class III, contaminated.
Entropion and ectropion repair
What and why: in an entropion the lid margin, usually the lower one, turns in, so the lashes rub the cornea (trichiasis), causing irritation, pain and tearing. The most common type comes with age, as the lid's supports loosen (involutional); scarring of the inner lid can also pull it in (cicatricial). In an ectropion the lower lid sags and turns out, so tears spill over and the exposed conjunctivakon-junk-TY-vuhThe thin, clear layer that lines the inside of the eyelids and covers the white of the eye.Full entry and cornea dry and grow irritated, and can ulcerate. It comes mostly with age, as the orbicularis muscle and the canthal tendons relax, but also from scarring, a facial nerveFAY-shul NERVThe seventh cranial nerve, which moves the muscles of the face and carries taste from the front of the tongue.Full entry paralysispuh-RAL-uh-sisLoss of the ability to move a part of the body, and sometimes loss of feeling in it.para- beside, abnormal-lysis looseningFull entry such as Bell palsybel PAWL-zeeSudden weakness or loss of movement on one side of the face, from a problem with the facial nerve.Full entry , or birth.
Before surgery: local anesthetic injected into the lid; general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry when needed. Both eyes may be prepped. A corneal shield protects the eye.
Setup: an oculoplastic set, a sterile marking pen, smooth and tying forceps, iris and tenotomy scissors, a #15 blade, needle-tip cautery or bipolar, and fine absorbable and nonabsorbable sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry .
Key steps: the repair fits the cause, and there are many methods.
- Tightening the lid at the outer corner (a lateral tarsal strip or canthal sling): the surgeon opens the outer corner, frees a strip of tarsal plate and tendon, pulls the lid out to the side to tighten it, and sews the strip to the periosteum on the inside of the outer orbital rim. This corrects both involutional entropion and ectropion.
- Plicating the lid's retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry muscles for entropion: through an incision just below the tarsal plate, the retractors are exposed and folded with sutures, and the extra skin is trimmed.
- Everting sutures (a Wies procedure) for scarring entropion: a full-thicknessful-THIK-nisGoing through every layer of the skin, or every layer of another tissue such as the wall of an organ.Full entry cut across the lid and mattress sutures that turn the margin back out.
- A wedge resectionrih-SEK-shunSurgery to remove part of an organ or tissue.re- back, againsect to cut-ion processFull entry for ectropion: a full-thickness wedge of lid is removed and the edges of the tarsal plate are sewn together to shorten and tighten the lid.
During the case, irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry the cornea and blot blood and fluid as the surgeon works. Antibiotic ointment goes on the wound, and an ice-cold compress helps the swelling.
Wound class: I, clean.
Eyelid laceration repair
What and why: a cut lid must be repaired exactly, because a lid margin that heals out of line can turn in or out. Deeper structures lie close under the skin: the tear drainage canals near the inner corner, the lacrimal gland, the orbicularis muscle, the angular artery and the levator muscle that lifts the lid. Fat showing in the wound means the levator may be injured. A cut through the canaliculus is stentstentA small tube, often of metal mesh, placed inside a vessel or duct to hold it open.Full entry to keep it open.
Before surgery: the whole eye is imaged first to rule out a hidden injury, such as a foreign body inside the eye, a retinalRET-ih-nulRelating to the retina, the thin layer at the back of the eye that senses light and sends images to the brain.retin/o retina-al relating toFull entry injury or a blowout fracture. Local anesthetic, with or without epinephrineep-ih-NEF-rinA hormone and drug, also called adrenaline, that raises heart rate and blood pressure and opens the airways.Full entry , is enough for most superficial cuts; general anesthesia is used when the tear system or bone is involved, and for children. The wound is cleaned (debridementdih-BREED-muntThe removal of dead, damaged or infected tissue from a wound so it can heal.Full entry ), the prep with dilute povidone-iodinePOH-vih-done EYE-uh-dineA brown antiseptic solution of iodine used to kill germs on the skin before procedures and on wounds.Full entry is very gentle, to protect the lid, and the eye is irrigated with BSS.
Key steps: the lid margin is lined up first with sutures, then the tarsal plate is closed with absorbable suture, and the skin and corner with fine nonabsorbable suture. A torn canaliculus is repaired around a rod or silicone stent passed through it.
Wound class: a fresh traumatic wound is Class III, and an old one with dead tissue, or an infected one, Class IV; one reference also lists Class II for a lid lacerationlas-uh-RAY-shunA cut or tear in the skin or other tissue, often with jagged edges.Full entry .
15Removing the eye
Losing an eye is a deep loss, and the patient may go home the same day, before much support is available. Be gentle and calm with the patient and family. general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry is preferred, though a facility's protocol may call for a regional block with sedationsih-DAY-shunA calm, relaxed or sleepy state brought on by drugs, or the use of drugs to cause it.sed calm, settle-ation processFull entry , and the time-outTYM-owtA pause just before a procedure when the whole team confirms the right client, procedure and site; also, a short break to calm a child.Full entry confirms the correct eye.
- Enucleation: the whole globe is removed, cutting its muscles and the optic nerveOP-tik nervThe nerve that carries visual signals from the back of the eye to the brain; the second cranial nerve.Full entry . It is done for a cancer inside the eye (such as retinoblastoma in children or melanomamel-uh-NOH-muhA cancer that starts in melanocytes, the cells that give skin its color.melan/o black, dark-oma tumorFull entry ), an eye too badly injured to save, or a blind eye that is painful or disfigured.
- eviscerationih-vis-er-AY-shunThe pushing out of internal organs, usually loops of bowel, through a surgical wound that has come open.e- outviscer/o internal organs-ation processFull entry : the contents of the eye are removed and the scleraSKLAIR-uhThe tough white outer layer of the eyeball.Full entry and its muscles are left in place, which gives a prostheticpros-THET-ikDescribes an artificial part made to replace a missing or damaged body part, such as a limb, joint, eye or heart valve.prosthe an addition (from Greek)-tic relating toFull entry eye better movement.
- Exenteration: all the contents of the orbit are removed, including the periosteum and sometimes the lids, usually for cancer of the globe or orbit.
Implants: a round implant, the sphere, fills the socket and later supports the artificial eye. Porous implants, of hydroxyapatite or porous polyethylene, let blood vessels grow into them; silicone and glass are still used. A hydroxyapatite sphere may be wrapped in donor sclera or synthetic material first, while porous polyethylene lets the surgeon sew the muscles straight to it, so the artificial eye moves better. Sizers and an introducer help choose and place it; adult sizes usually run 14 to 22 mm. A conformer over it shapes the socket. About 4 to 6 weeks later, an ocularist fits an artificial eye (a prosthesispros-THEE-sisAn artificial body part that replaces one that is missing or does not work, such as an artificial leg, joint, eye or heart valve.Full entry ), molded and painted to match the other one.
Setup: an enucleation set: speculumSPEK-yoo-lumAn instrument used to open and hold open a body opening, such as the vagina, so the inside can be seen.Full entry , curved enucleation scissors, a large curved hemostatHEE-moe-statA clamp with finger rings and a locking ratchet used in surgery to grasp and close off bleeding vessels.hem/o blood-stat stopping, standing stillFull entry for the optic nerve, an enucleation spoon, muscle hooks, sizers and the sphere, a conformer, an electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry and plenty of saline-soaked sponges.
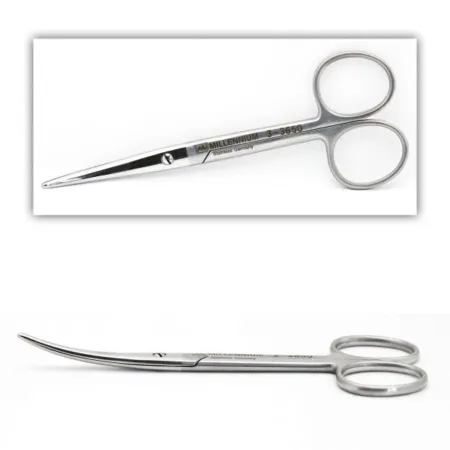



Key steps (enucleation):
- A speculum. The conjunctivakon-junk-TY-vuhThe thin, clear layer that lines the inside of the eyelids and covers the white of the eye.Full entry is cut all the way around the corneaKOR-nee-uhThe clear, dome-shaped layer at the front of the eye, over the iris and pupil.Full entry , as close to the limbus as possible to save it for the closure.
- The four rectusREK-tusLatin for straight; the name of several straight muscles, such as the rectus abdominis of the abdomen and the rectus femoris of the thigh.Full entry muscles are looped with sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry if they will be sewn to the implant, then cut from the globe, leaving a stump of the medial rectus to hold.
- Blunt curved scissors free the globe from Tenon capsule, and the surgeon turns the eye by the medial rectus stump.
- The surgeon slides a large curved hemostat behind the eye and clamps the optic nerve for about 60 seconds; then the enucleation scissors cut the nerve, and the oblique muscles are cut as the eye comes out.
- The socket is packed with saline-soaked sponges and pressed to stop the bleeding. Keep track of how many go in, so every one comes out.
- The implant goes into the cone of muscles, the muscles are sewn to it if planned, and Tenon capsule and the conjunctiva are closed in separate layers over it.
- A conformer goes in behind the lids, antibiotic ointment is applied, and a pressure dressing goes on.
Evisceration: the surgeon cuts in at the limbus and may remove the cornea, scoops out the eye's contents with a spoon, and scrapes the choroid from the inside of the shell with curettekyoo-RETA surgical instrument with a small spoon- or loop-shaped tip used to scrape tissue.Full entry . Two relieving cuts in the sclera ease its tension, the implant is placed inside the scleral shell, and the sclera and conjunctiva are closed over it.
Specimen: the eye, or its contents, received in a small specimen cup or basin.
Wound class: I, clean, for an elective removal. After an injury, Class III when the wound is fresh, and Class IV when it is old with dead tissue or infected.
After surgery: bleeding and infection are the main risks. Teach the patient to protect the remaining eye, with protective glasses for sports and yard work.
Recovering eyes from a deceased donor
Chapter 18 teaches eye donation; here is the team's part. Every death and every imminent death is reported to the organ procurement organization; a specially trained person, such as a procurement organization nurse, asks the family, never other staff, and the next of kin sign the consent. Most people can donate, whatever their age, blood typeBLUD typeThe group a person's blood belongs to, based on markers on the red blood cells: A, B, AB or O, and Rh positive or negative.Full entry or eye color, even with poor sight or cataractKAT-uh-raktClouding of the lens of the eye.Full entry . After death, the donor's head is raised on a pillow to limit swelling near the eyes, and saline-soaked gauze covers the eyes while the body waits in the morgue. The procurement team recovers the eyes within several hours of death.
some references still say the attending physician must ask the family, as some states' required request laws direct.
The recovery is done much like an enucleation, with the same sterile fieldSTAIR-ul feeldAn area set up with sterile drapes and supplies, kept free of all germs, for a sterile procedure.Full entry , drapes and instruments. Each eye is placed cornea up in a sterile eye cage or on gauze in a sterile jar labeled right or left eye, and the sockets are packed with cotton and the lids closed. The corneas are placed in a storage medium such as Optisol-GS, and each sealed jar is labeled with the donor's name or number, the time of death, the time of recovery and the date, then carried on crushed ice to the eye bank. Treat the tissue as the gift it is.
16Tear ducts
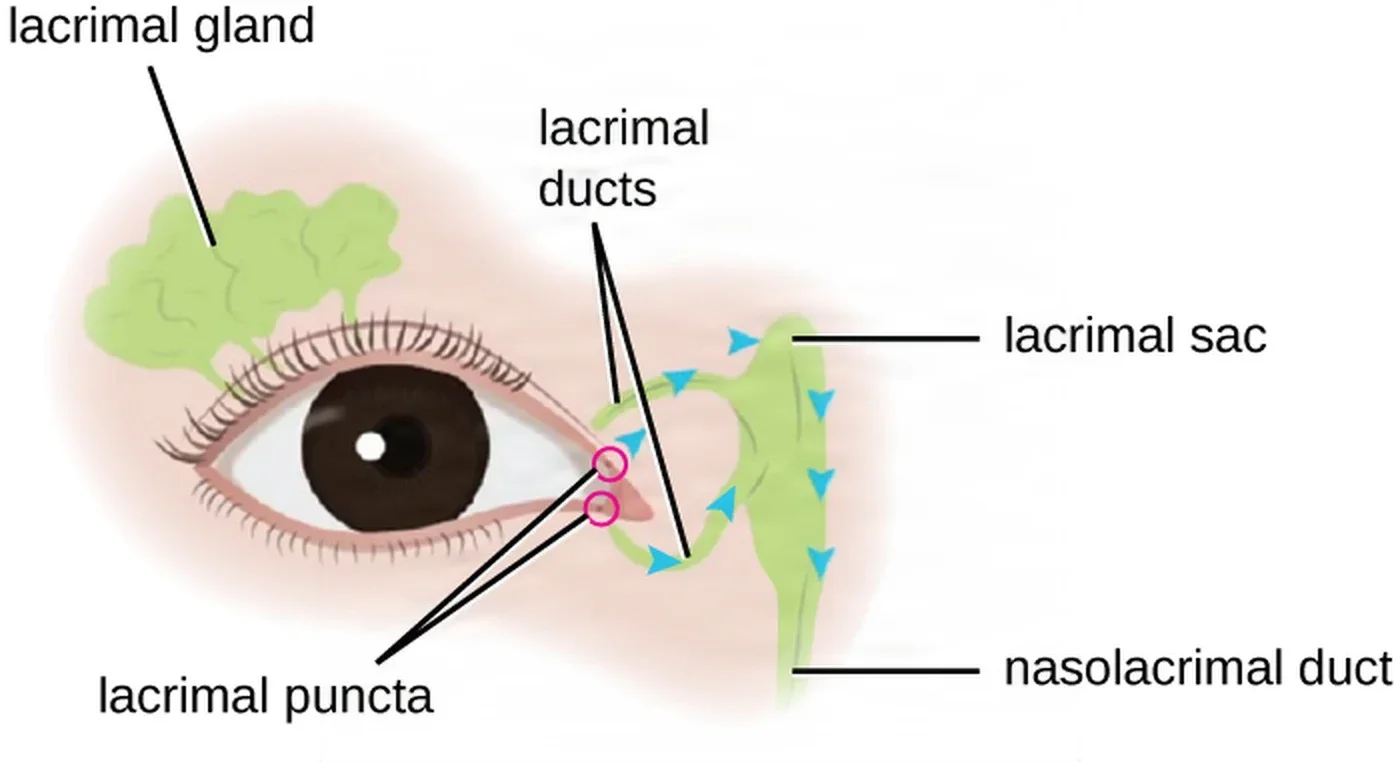
Probing, dilation and stents
What and why: a blocked tear drain makes tears overflow (epiphora) and can lead to infection of the lacrimal sac. Children can be born with a blocked nasolacrimal duct, which oculoplastic surgeons treat.
Before surgery: usually topical and local anesthesiaLOH-kul an-es-THEE-zhuhNumbing medicine applied to or injected into one small area, so a procedure there is not felt while the person stays awake.Full entry . A baby 6 months old or younger may have only numbing drops, wrapped snugly with the bony points padded; an older child usually has general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry . Drapes are optional.
Setup: punctal dilatorDY-lay-terAn instrument used to stretch or widen an opening, canal or passage in the body.Full entry , a set of lacrimal probes, a lacrimal cannulaKAN-yoo-luhA thin tube placed into the body or a body opening to deliver or remove fluid or air.Full entry on a syringe of saline, and a silicone stentstentA small tube, often of metal mesh, placed inside a vessel or duct to hold it open.Full entry or endotracheal intubationen-doh-TRAY-kee-ul in-too-BAY-shunPutting a breathing tube through the mouth or nose into the windpipe (trachea).endo- withintrache/o windpipe-al relating toFull entry set. Bowman probes come in sets of six, double-ended, each end a different size, with a flat plate in the middle to hold.

Key steps:
- A punctal dilator widens the opening at the inner end of the lid.
- A probe is passed through the punctum, the canaliculus, the lacrimal sac and the nasolacrimal duct into the nose, working up through the sizes.
- Saline flushed through the duct and suctioningSUK-shun-ingRemoving mucus, saliva or other secretions from the mouth, nose or airway with a tube connected to a suction source.Full entry from the nose shows that it is open.
- For a stent, a silicone tube on a fine metal rod or leader is passed through the punctum and down into the nose, where it is caught with a hook and drawn out, and left in place to lower the chance that the duct closes again.
- Fluorescein dye may be used to test that the duct is open, and antibiotic drops may go in at the end.
Wound class: the references give none for probing, so your facility's policy decides, from the CDC's definitions.
Dacryocystorhinostomy (DCR)
What and why: a DCR makes a new path for tears from the lacrimal sac straight into the nose, bypassing a nasolacrimal duct blocked by scarring after infection, a stone or an injury. Dacryocystitis, an infection of the lacrimal sac, shows as a painful, red swelling at the inner corner of the eye, sometimes with pus from the punctum; it is most common in adults over 40. The operation is done open, through a small skin incision beside the nose, or endoscopically through the nose, often by an ear, nose and throat surgeon.
Before surgery: usually general anesthesia, because the case can be long and bloody, sometimes with lowered blood pressure to reduce bleeding. The surgeon packs the nose with cottonoids soaked in a topical anesthetican-us-THET-ikA drug that causes loss of feeling, with or without loss of consciousness.an- withoutesthesi/o feeling, sensation-ic relating toFull entry and vasoconstrictor, such as cocaine or oxymetazoline, and injects lidocaineLY-doh-kaynA local anesthetic that numbs an area, also given by IV to treat some fast, abnormal heart rhythms.Full entry with epinephrineep-ih-NEF-rinA hormone and drug, also called adrenaline, that raises heart rate and blood pressure and opens the airways.Full entry . Cocaine is a topical drug only, never injected, and a Schedule II controlled substancekun-TROHLD SUB-stunsA drug whose making, prescribing and use are strictly regulated by law because it can be misused or cause dependence.Full entry . The head of the table may be raised.
Setup: a lacrimal or DCR set with a Freer elevator, Kerrison rongeurron-ZHURA strong surgical instrument with sharp, cup-shaped jaws used to bite away small pieces of bone.Full entry , a nasal speculumSPEK-yoo-lumAn instrument used to open and hold open a body opening, such as the vagina, so the inside can be seen.Full entry and bayonet forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry , a power drill with burs, bipolarby-POH-lerHaving two poles or two opposite ends; most often used as a short form of bipolar disorder.bi- twopolar having polesFull entry , Frazier suction, lacrimal probes, a silicone intubation set, gelatin sponge with thrombinTHROM-binAn enzyme in the blood that turns fibrinogen into fibrin, the threads that hold a blood clot together.thromb/o clot-in substanceFull entry , iodoform packing, and a nasal endoscopeEN-duh-skohpA thin tube with a light and a camera that is passed into the body to look inside an organ or cavity.endo- within-scope instrument for viewingFull entry for an endoscopicen-doh-SKOP-ikDone with an endoscope, a thin tube with a light and camera passed into the body.endo- within-scopic viewingFull entry case.
Key steps (open DCR):
- An incision beside the inner corner of the eye with a #15 blade; the orbicularis muscle is spread to the bone. Have cotton-tipped applicators ready to sponge, and suction going.
- The periosteum is lifted with a Freer elevator, and an opening is made through the thin lacrimal bone and widened with a Kerrison rongeur or a drill. Clean the bone bits from the rongeur's tip with a moist sponge between bites.
- A probe is passed through a punctum into the sac, the sac is opened over it, and the nasal lining is opened. Have suction ready when the sac is opened.
- The flaps of the sac and the nasal lining are sewn together to make the new channel.
- Silicone tubes are passed through the upper and lower puncta, through the new opening and out of the nose, where the ends are tied and trimmed so they sit inside the nostril.
- The muscle and skin are closed, ointment goes on the incision, and a gauze pad is taped under the nose.
Wound class: II, clean-contaminated, by the CDC's definitions, because the nasal cavity, part of the respiratory tract, is opened; one reference lists it as Class I.
After surgery: the silicone tubes stay in for up to 4 to 8 weeks, then are removed; one reference removes them at about 2 weeks. Ice and keeping the head raised help the swelling. Bleeding and infection are the risks, and the open approach leaves a scar.
17After eye surgery
Wound classes
No eye operation opens the respiratory, digestive, genital or urinary tract except a dacryocystorhinostomy, which opens the lining of the nose, so most eye surgery is Class I, clean. Trauma and infection change that, as chapter 11 teaches.
| Operation | Wound class |
|---|---|
| cataractKAT-uh-raktClouding of the lens of the eye.Full entry extraction, keratoplasty, iridotomy and iridectomy, glaucomaglaw-KOH-muhAn eye disease in which the optic nerve is damaged, usually with raised pressure inside the eye, leading to loss of vision.Full entry surgery, vitrectomy, scleraSKLAIR-uhThe tough white outer layer of the eyeball.Full entry buckle, pneumatic retinopexy, strabismus surgery, entropion and ectropion repair, pterygium excisionek-SIZH-unCutting out tissue, such as a growth or damaged area, during surgery.Full entry | I, clean |
| Elective enucleation or eviscerationih-vis-er-AY-shunThe pushing out of internal organs, usually loops of bowel, through a surgical wound that has come open.e- outviscer/o internal organs-ation processFull entry | I |
| Enucleation after an injury; corneaKOR-nee-uhThe clear, dome-shaped layer at the front of the eye, over the iris and pupil.Full entry , conjunctival and eyelid lacerationlas-uh-RAY-shunA cut or tear in the skin or other tissue, often with jagged edges.Full entry | III when fresh; IV when old with dead tissue, or infected (one reference also lists II for a lid laceration) |
| Dacryocystorhinostomy | II, because the nose is entered (one reference lists I) |
| Chalazion excision | I by the CDC's definitions (a chronic granuloma; no tract entered), as facility policy decides; one reference lists III |
The table rests on the CDC's definitions and the classes the references give for each operation.
Infection and inflammation inside the eye
- Endophthalmitis is an infection inside the eye, a dangerous complication. povidone-iodinePOH-vih-done EYE-uh-dineA brown antiseptic solution of iodine used to kill germs on the skin before procedures and on wounds.Full entry drops in the eye before surgery and antibiotics injected into the front chamber at the end help prevent it.
- toxicitytok-SIS-ih-teeThe harm a substance does to the body, or a state in which a drug has built up to a harmful level.tox/o poison-icity state or quality ofFull entry anterior segment syndrome (TASS), a sterile inflammation inside the front of the eye from something toxic that got in, is taught in chapter 27 with the instrument cleaning that prevents it. At the eye case, your part is the drugs: only preservative-free drugs and solutions go into the eye, intraocular drugs stay apart and labeled, and no ointment goes on after cataract surgery.
Going home
Most eye patients go home the same day. Before discharge, the patient and caregiver learn to put in the drops without touching the tip to the eye, to wear the shield, not to rub or squeeze the eye, to avoid straining, heavy lifting and bending as the surgeon directs, and to call at once for sudden pain, sudden loss of vision, light sensitivitysen-sih-TIV-ih-teeHow strongly something responds; in lab work, which drugs stop a germ, or how well a test finds people who have a disease.Full entry , a severe headache, nausea and vomiting, or swelling and redness. Sight may be blurry for a few days, so they take care not to fall.
keep the drugs that go inside the eye apart, preservative-free and labeled; keep the cornea moist; and never let anything jar the eye while an instrument is in it.
What to take from this chapter
- Eye surgery is microsurgery on an often awake patient: keep the room quiet, pass instruments into the surgeon's hand in position of use so the surgeon never looks up from the microscope, keep a fixed order on the Mayo, and keep the cornea moist with BSS.
- Prep with dilute povidone-iodine, never CHG or alcohol near the eye. Confirm the correct eye at the time-out, including the time-out before a block, and treat the intraocular lens like a drug: say its model and power aloud as you pass it.
- Eye drugs look alike and one error can blind. Label every one at once, keep intraocular drugs preservative-free and apart, and know the classes: mydriatics dilate, cycloplegics dilate and stop focusing, miotics constrict, viscoelastics hold the chamber open and must be washed out.
- In phacoemulsification the lens comes out in pieces and the capsule stays to hold the new lens; keep an anterior vitrectomy setup and a second lens ready in case the capsule tears.
- Keratoplasty replaces the cornea with donor tissue prepared on its own separate table; glaucoma surgery (trabeculectomy, trabeculoplasty, tube shunts, iridotomy) protects remaining sight, and mitomycin and 5-FU are hazardous drugs.
- Retinal detachments are repaired by vitrectomy, scleral buckling or pneumatic retinopexy; a gas bubble means no nitrous oxide, a wristband, head positioning and no flying.
- Strabismus surgery moves or shortens a muscle; pulling on it can slow the heart, so the surgeon lets go. Lid surgery fixes lids that turn in or out, removes chalazia and repairs lacerations with exact alignment of the margin.
- Enucleation removes the globe, evisceration its contents and exenteration the whole orbit; a sphere and conformer fill the socket. A DCR opens a new tear path into the nose and is Class II; most other eye cases are Class I.
Check yourself5 quick questions
Free for everyone. Pick an answer for each, then check them all at once.
In the ORWhere you'll use this
The chapter's whole question pool in sets of 10, with the answer explained after each one.
Part of the educators programThe chapter's words on spaced cards: the ones you miss come back sooner.
Part of the educators programGiven by your class's teacher. Each class draws its own 25 from the chapter's pool.
Part of the educators program
Suggest a fix
Something wrong, unclear or out of date in this chapter? Tell us and we will fix it for everyone. Your email is only used to reply.