Ear, nose and throat
Ears, sinuses, tonsils and the airway: the small, delicate cases of the head and neck, the anatomy under the microscope, and how to keep a shared airway safe.
1What ear, nose and throat surgery covers
Otorhinolaryngology is the specialty of the ear (oto), the nose (rhino) and the throat (laryngo). Its surgeons, called otolaryngologists or ENT surgeons, also operate on the mouth, the salivary glandSAL-ih-vair-ee GLANDA gland that makes saliva and releases it into the mouth.Full entry , the neck and the airway, and on the lymph nodelimf nohdA small, bean-shaped organ of the immune system that filters lymph fluid and holds white blood cells.Full entry that drain the head.
The cases run from simple ones, such as a myringotomy, to complex ones, such as a laryngectomy. Much of the work is microsurgery on tiny structures, with many special instruments and machines to learn.
Most ENT cases are outpatient (one report puts the share at 92 percent of otolaryngologic procedures), and three common ENT operations are done in children: ear tubes, tonsillectomy and adenoidectomy. Pain control is planned before the patient goes home.
The approach can be open, endoscopicen-doh-SKOP-ikDone with an endoscope, a thin tube with a light and camera passed into the body.endo- within-scopic viewingFull entry or robot-assisted. endoscopeEN-duh-skohpA thin tube with a light and a camera that is passed into the body to look inside an organ or cavity.endo- within-scope instrument for viewingFull entry reach the sinusSY-nusA hollow space in the body, most often one of the air-filled spaces in the skull bones around the nose.Full entry , the middle ear, the larynxLAIR-inksThe voice box: the part of the airway in the neck, above the windpipe, that holds the vocal cords.laryng/o larynxFull entry and the airway through natural openings, and a surgical robot can work through the open mouth, an approach called transoral robotic surgery (TORS). As in every specialty, any approach other than open counts as minimally invasive surgery (MIS), and cases that share instruments, positions and steps are taught together as co-related procedures.
Each case in this chapter links to its setup card, which holds the instrument list and every step. Here you get the reasons, the key steps and the moments when the scrub matters most. ENT is one of the specialties on your case log (chapter 14).
Sharing the airway
In much of ENT surgery the surgeon works in the same place the anesthesia provideran-us-THEE-zhuh pruh-VY-derThe licensed professional who gives anesthesia and watches over the client's breathing and vital functions during a procedure.Full entry is breathing for the patient: the nose, the mouth, the larynx and the tracheaTRAY-kee-uhThe windpipe: the tube that carries air from the throat to the lungs.Full entry . Keeping the airway open, safe and free of fire is a team job in every case. Chapter 13 teaches airway management and laryngospasmluh-RING-goh-spaz-umA sudden, involuntary closing of the vocal cords that partly or fully blocks air from entering the lungs.laryng/o larynx (voice box)-spasm sudden involuntary tighteningFull entry , a spasmSPAZ-umA sudden, involuntary tightening of a muscle or of the muscle in a hollow organ or tube.Full entry of the muscles of the larynx that can close the airway, a risk that comes back as the patient wakes.
Nitrous oxide is not used in middle ear surgery: it collects in closed air spaces and can push a graftGRAFTTissue or a man-made material moved into place in surgery to replace or repair a damaged part.Full entry on the tympanic membranetim-PAN-ik MEM-braynThe thin, cone-shaped sheet of tissue between the outer ear canal and the middle ear; the eardrum.Full entry out of place.
The patient
Many ear patients cannot hear well, and many throat patients cannot speak, or will not be able to after surgery. Chapter 18 teaches how to communicate with them: ask before the case how the patient communicates best, face the patient and speak slowly and clearly in few words, and have a dry-erase board, paper and pencil, or hand signals ready for a patient who cannot speak.
A patient may wear hearing aids into the OR; they come out at or after inductionin-DUK-shunThe starting of a process on purpose, such as bringing on labor or putting a client under anesthesia.Full entry , or stay in for a case done under local anesthesiaLOH-kul an-es-THEE-zhuhNumbing medicine applied to or injected into one small area, so a procedure there is not felt while the person stays awake.Full entry . Prescription glasses help a patient who lip-reads. Warn an awake patient before noises, such as the suction or the electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry , so a startle does not make them move.
Head and neck surgery can change how a patient looks, speaks, swallows and breathes. A patient facing a laryngectomy or a large cancer operation may grieve the loss of the voice or of part of the face, and needs support and time to talk about their fears.
Because the facial nerveFAY-shul NERVThe seventh cranial nerve, which moves the muscles of the face and carries taste from the front of the tongue.Full entry runs through the operative field in so many ENT cases, the nurse checks it afterward: the patient wrinkles the forehead, closes the eyes, puckers the lips, shows the teeth and puffs the cheeks, and both sides should move equally. Weakness that does not settle within 2 hours is reported to the surgeon.
2Anatomy that matters
Chapter 4 teaches the ear, chapter 6 the nose, sinusSY-nusA hollow space in the body, most often one of the air-filled spaces in the skull bones around the nose.Full entry , pharynxFAIR-inksThe throat: the passage behind the nose and mouth that carries air to the voice box and food to the esophagus.pharyng/o throatFull entry , larynxLAIR-inksThe voice box: the part of the airway in the neck, above the windpipe, that holds the vocal cords.laryng/o larynxFull entry and tracheaTRAY-kee-uhThe windpipe: the tube that carries air from the throat to the lungs.Full entry , chapter 7 the mouth and the salivary glandSAL-ih-vair-ee GLANDA gland that makes saliva and releases it into the mouth.Full entry , and chapter 9 the thyroid and parathyroid glandpair-uh-THY-royd glandOne of four small glands behind the thyroid that control the amount of calcium in the blood.para- besidethyr/o thyroid gland-oid likeFull entry . Here is what ENT surgery adds at the field.
The ear
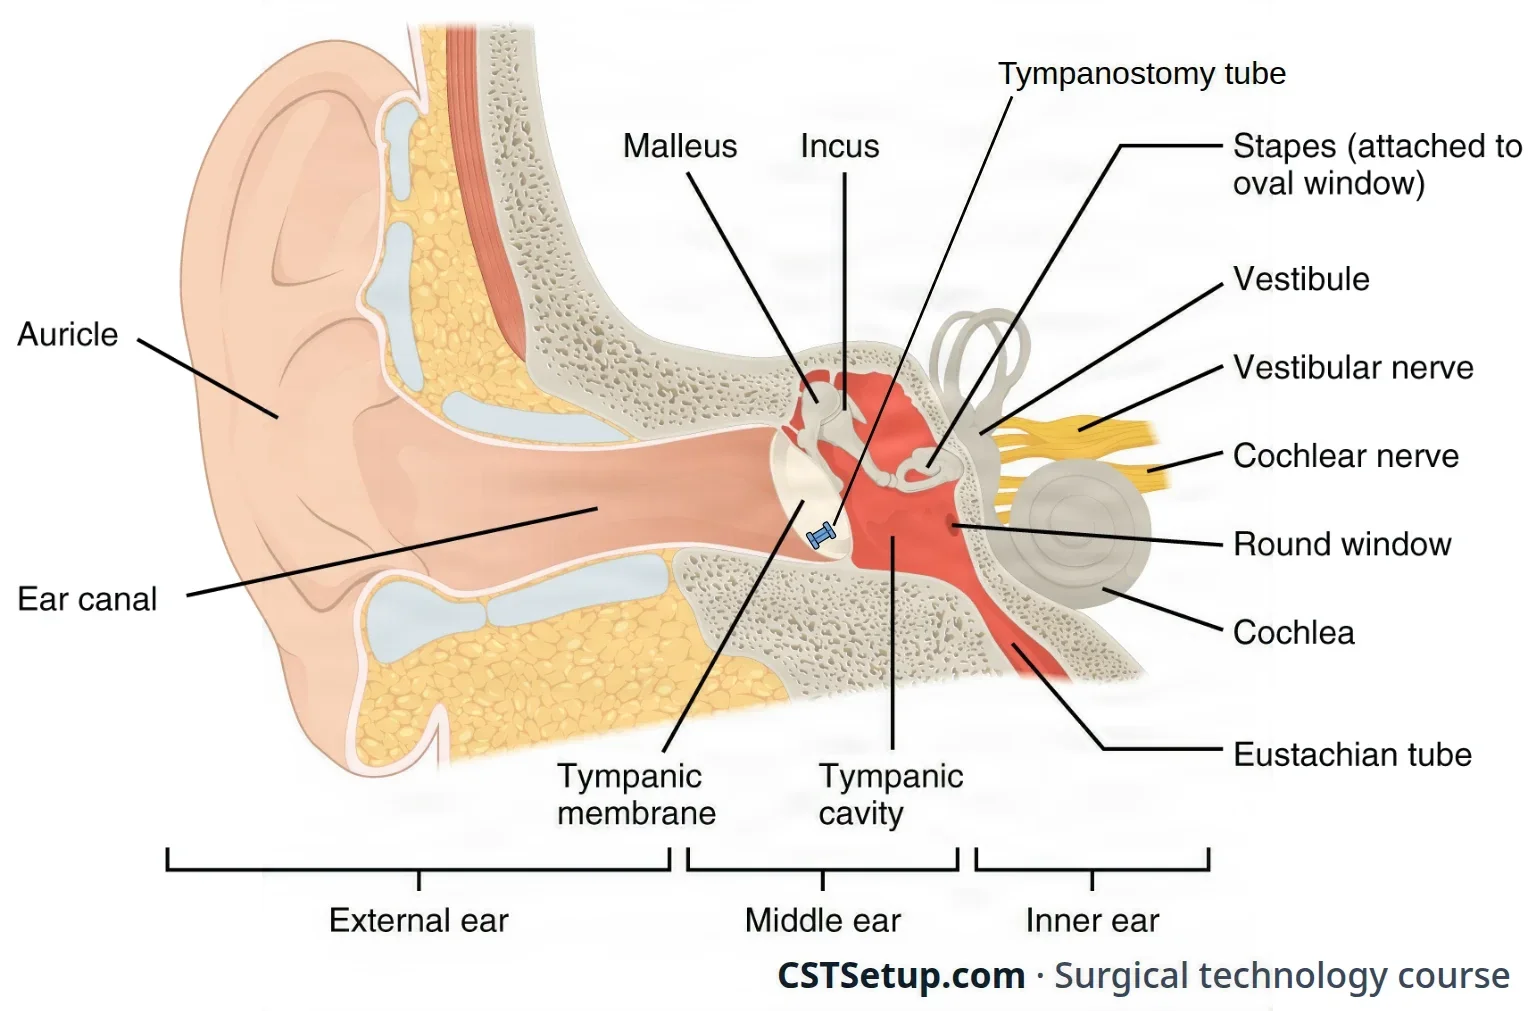
The figure shows the external, middle and inner earIN-er EERThe deepest part of the ear, inside the skull bone, which holds the organs of hearing and balance.Full entry , with a tympanostomy tube in the tympanic membranetim-PAN-ik MEM-braynThe thin, cone-shaped sheet of tissue between the outer ear canal and the middle ear; the eardrum.Full entry . Two things matter most in surgery.
Most of the gain in loudness comes from the eardrum being much larger than the oval window (references give about 17 to 20 times); the lever action of the ossicles adds a little more. That is why ear surgery rebuilds both the eardrum and a mobile chain of ossicles from it to the oval window.
The facial nerveFAY-shul NERVThe seventh cranial nerve, which moves the muscles of the face and carries taste from the front of the tongue.Full entry , cranial nerveKRAY-nee-ul NERVOne of the 12 pairs of nerves that come straight from the brain and brainstem rather than the spinal cord.Full entry VII, matters in every middle ear and mastoid case. It moves the muscles of the face. It runs through the temporal bone just above the oval window, turns down through the mastoid and leaves the skull through the stylomastoid foramen. Its chorda tympani branch carries taste from the front two-thirds of the tongue and passes along the inner surface of the eardrum.
The nose and the sinuses
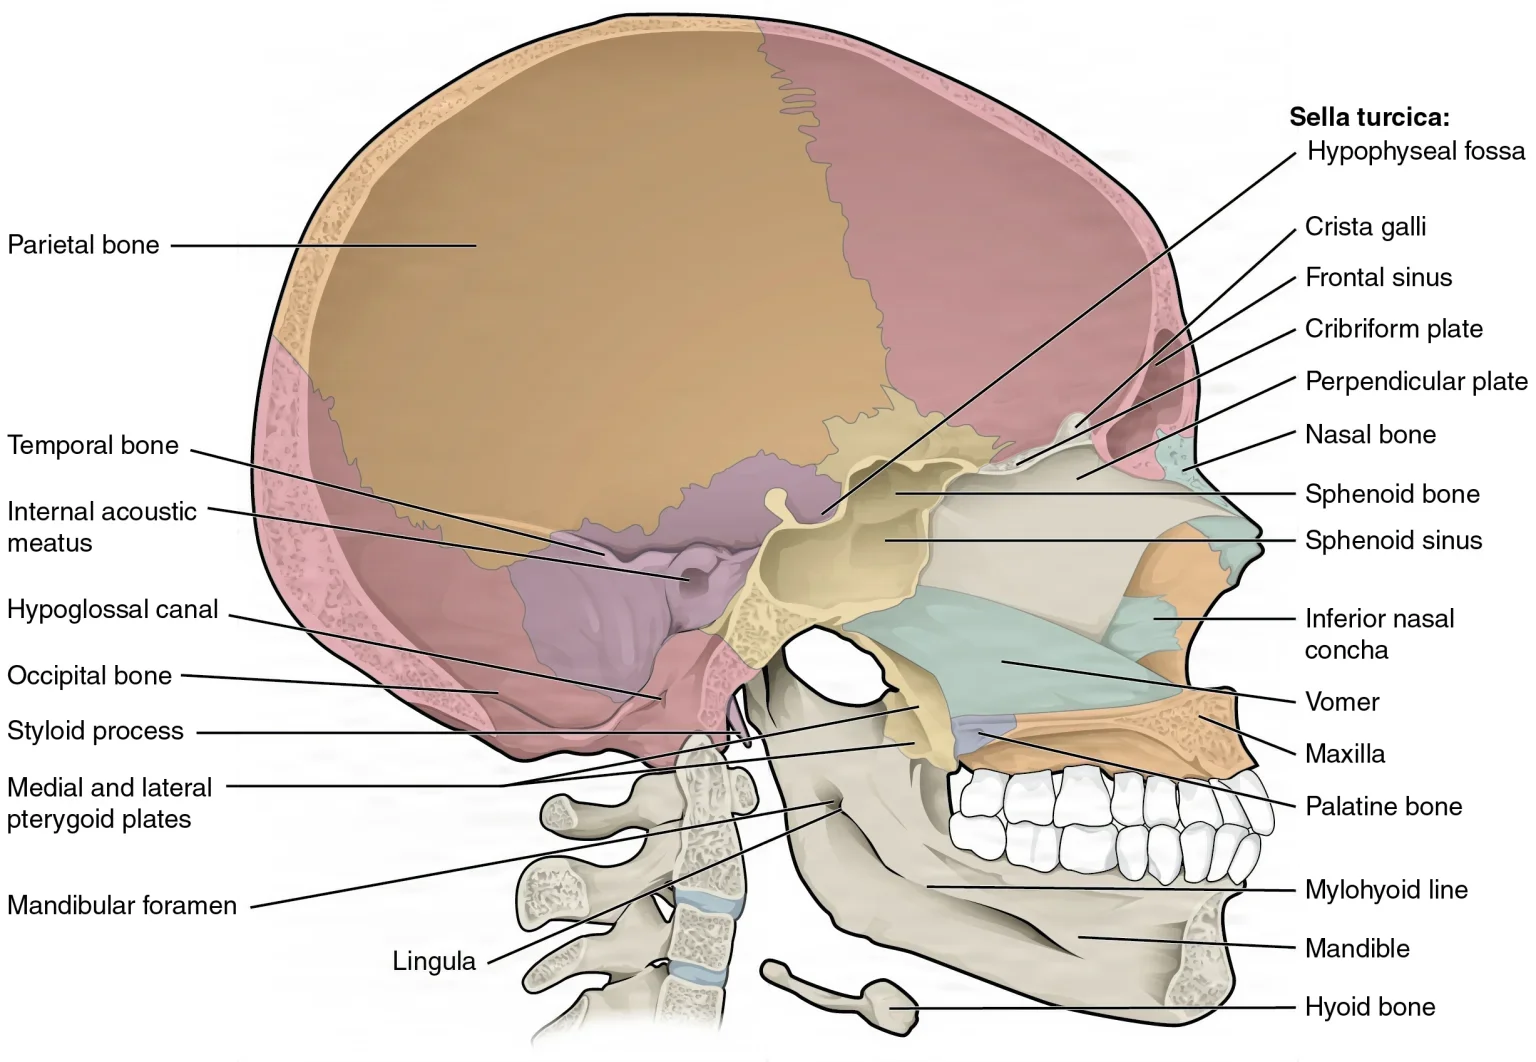
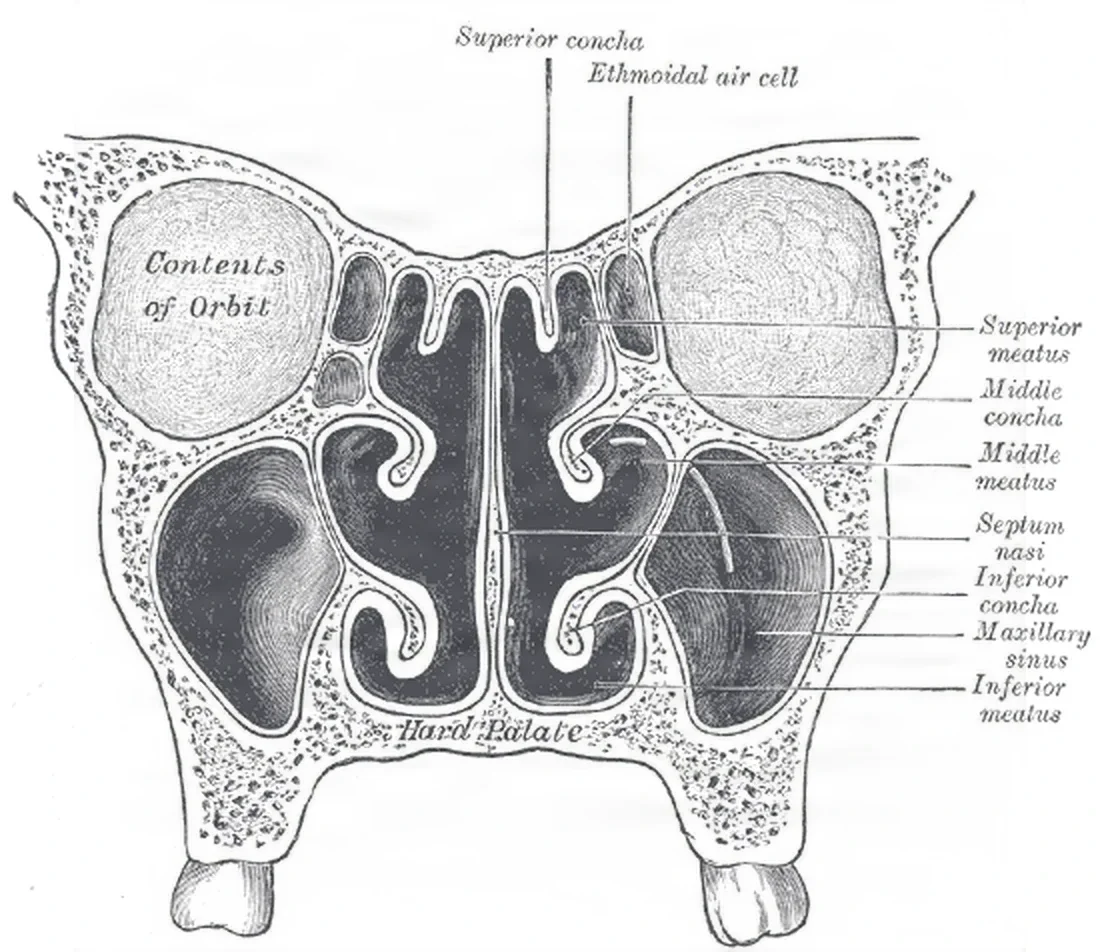
- The nasal septumNAY-zul SEP-tumThe wall of cartilage and bone that divides the inside of the nose into right and left sides.nas/o nosesept/o dividing wallFull entry is cartilageKAR-tih-lijFirm, smooth, rubbery tissue that cushions joints and gives shape to parts such as the ear, nose and windpipe.chondr/o cartilageFull entry in front and bone behind (the ethmoid's perpendicular plate and the vomer), covered on each side by mucoperichondrium, a lining of blood vessels and mucus-making cells. A septoplasty works under that lining.
- Structures that must not be injured: the thin cribriform plate in the roof of the nose is all that separates it from the brain, and the paranasal sinuses, the air-filled spaces in the bones around the nose, border the eye socket, the optic nerveOP-tik nervThe nerve that carries visual signals from the back of the eye to the brain; the second cranial nerve.Full entry and the carotidkuh-ROT-idHaving to do with the carotid arteries, the two large arteries on each side of the neck that carry blood to the head and brain.Full entry arteries, so sinus surgery works very close to them.
- Bleeding sites: a nosebleed that will not stop often comes from the Kiesselbach plexusPLEK-susA network of nerves or blood vessels that branch and join together.Full entry at the front of the septumSEP-tumA wall of tissue that divides two spaces or cavities, such as the two sides of the heart or nose.sept/o wall, partitionFull entry or from the sphenopalatine artery at the back of the nose.
The mouth, pharynx and larynx
- The mouth has two parts: the vestibule, between the lips and cheeks and the teeth, and the oral cavity proper, inside the teeth, roofed by the hard and soft palateSOFT PAL-itThe soft, muscular back part of the roof of the mouth, with no bone in it.Full entry .
- The tonsilTON-sulOne of the masses of lymph tissue at the back of the throat that help fight germs entering the mouth and nose.Full entry : each palatine tonsil sits in the side wall of the oropharynxor-oh-FAIR-inksThe middle part of the throat, behind the mouth, from the soft palate down to the top of the voice box.or/o mouthpharyng/o throatFull entry , in a fossaFOS-uhA shallow hollow or dip in a bone or on the body's surface.Full entry between two folds called the tonsillar pillars; the adenoids sit high in the nasopharynxnay-zoh-FAIR-inksThe top part of the throat, behind the nose and above the soft palate.nas/o nosepharyng/o throatFull entry , beside the openings of the eustachian tubes.
The vocal cords are moved by the recurrent laryngeal nerve, a branch of the vagus nerveVAY-gus nervThe 10th cranial nerve, which runs from the brain stem to the chest and belly and slows the heart and helps digestion.Full entry , which works every small muscle inside the larynx except one, the cricothyroid. That one is worked by the external branch of the superior laryngeal nerve. Cut one recurrent nerve and hoarseness follows at once; injure both and the cords can close the airway. Injury to the superior laryngeal nerve's branch makes it hard to shout or sing high notes. A cord that is partly paralysispuh-RAL-uh-sisLoss of the ability to move a part of the body, and sometimes loss of feeling in it.para- beside, abnormal-lysis looseningFull entry is said to have paresis, as in vocal cord paresis.
The neck and the salivary glands
The sternocleidomastoid muscle (SCM), from the mastoid to the sternum and clavicleKLAV-ih-kulThe long, slightly S-shaped bone that runs from the top of the breastbone to the shoulder; the collarbone.clavicul/o collarboneFull entry , divides each side of the neck into an anterior and a posterior triangle. Under it runs the carotid sheathSHEETHA covering that wraps around a structure; in procedures, a short hollow tube left in a blood vessel to pass catheters through.Full entry , holding the carotid artery, the vagus nerve and the internal jugular veinin-TUR-nul JUG-yuh-ler vaynA large vein deep on each side of the neck that carries blood from the brain, face and neck back toward the heart.Full entry . Cranial nerve XI, the spinal accessory nerve, runs across the posterior triangle, and the hypoglossal nerve, cranial nerve XII, which moves the tongue, lies in the submandibular triangle.
lymphLIMFThe clear fluid that flows through the lymphatic vessels and carries white blood cells.Full entry from the head and neck drains to the cervicalSER-vih-kulRelating to the neck, or to the cervix, the lower end of the uterus.cervic/o neck, cervix-al relating toFull entry lymph nodelimf nohdA small, bean-shaped organ of the immune system that filters lymph fluid and holds white blood cells.Full entry , which surgeons map in levels: level I under the chin and jaw, levels II to IV along the jugular veinJUG-yuh-ler VAYNOne of the large veins on each side of the neck that carry blood from the head back toward the heart.Full entry from top to bottom, level V in the posterior triangle, level VI in front of the trachea, and level VII in the upper chest. Cancers of the mouth, throat and larynx spread to these nodes.
The facial nerve passes through the parotid gland, splits there into its five branches (temporal, zygomatic, buccal, marginal mandibular and cervical) and divides the gland into a superficial and a deep lobe. The lingual and hypoglossal nerves lie beneath the submandibular gland, with the marginal mandibular branch of the facial nerve close by.
3Diseases and tests
Hearing loss
Hearing loss is sorted by where the sound is stopped.
- Conductive: sound cannot get through the outer or middle ear to the inner earIN-er EERThe deepest part of the ear, inside the skull bone, which holds the organs of hearing and balance.Full entry . Causes include wax or a foreign body in the canal, swelling, injury, infection, a hole in the tympanic membranetim-PAN-ik MEM-braynThe thin, cone-shaped sheet of tissue between the outer ear canal and the middle ear; the eardrum.Full entry , and otosclerosis or other fixing of the ossicles. Middle ear surgery treats many of these causes.
- Sensorineural: the problem is in the cochlea, the hearing nerve or the brain's hearing pathway. Causes include ototoxic drugs, loud noise, injury, Meniere disease, tumors, aging (presbycusisprez-bih-KYOO-sisHearing loss that comes on slowly with aging, in both ears.presby- old age-cusis hearingFull entry ) and infections such as measlesMEE-zulzA very contagious illness caused by the measles virus; also called rubeola.Full entry , mumpsMUMPSA contagious disease caused by the mumps virus that mainly infects the salivary glands in front of the ears.Full entry and meningitismen-in-JY-tisInflammation of the meninges, the membranes that cover the brain and spinal cord.mening/o meninges-itis inflammationFull entry .
- Mixed: both at once, such as aging of the ear together with impactedim-PAK-tidFirmly packed or wedged in place so it cannot move or pass normally.Full entry wax.
An ototoxic substance is one that can injure the ear. Drugs to note in the history include salicylates (aspirin), aminoglycosideuh-mee-noh-GLY-koh-sideA group of strong antibiotics, mostly given by IV or injection, that kill many gram-negative bacteria.Full entry antibiotics such as streptomycinstrep-toh-MY-sinAn aminoglycoside antibiotic given by injection, used mainly for tuberculosis and a few rare infections.Full entry , furosemidefyoo-ROH-suh-mideA loop diuretic: a drug that makes the kidneys remove more salt and water from the body.Full entry , ethacrynic acid and quinineKWY-nineAn antimalarial drug made from the bark of the cinchona tree, taken by mouth for malaria.Full entry .
Tests for the ear
| Test | What it shows |
|---|---|
| Otoscope | A lighted handheld scope for the first look at the canal and eardrum; most middle ear diseases change the eardrum's color, position or wholeness. Earwax (cerumensuh-ROO-menEarwax: the soft yellow or brown substance made by glands in the outer ear canal.Full entry ) is cleared first if needed |
| Microscope exam | A closer look at the eardrum through an ear speculumSPEK-yoo-lumAn instrument used to open and hold open a body opening, such as the vagina, so the inside can be seen.Full entry and the operating microscope |
| Tuning fork tests (Rinne and Weber) | A quick first check of hearing that tests bone conductionkun-DUK-shunThe passing of something, such as an electrical signal or heat, from one place to another through a material.Full entry and the cochlea's sensorineural function; a tuning fork can also show a gain during surgery under local anesthesiaLOH-kul an-es-THEE-zhuhNumbing medicine applied to or injected into one small area, so a procedure there is not felt while the person stays awake.Full entry |
| Audiometry (the audiogram) | Pure tones and speech at different pitches and volumes; the patient signals what they hear. It measures the loss and its type |
| Tympanometry | Changes the air pressure in the sealed ear canal and measures how the eardrum responds. It shows fluid behind the eardrum, fixed or broken ossicles, a hole in the eardrum, and whether a tympanostomy tube is open |
| Electronystagmography (ENG), caloric and balance tests | Balance: cool, then warm, water in the canal sets off rapid eye movements (nystagmusnih-STAG-musRapid, repeated movements of the eyes that the person cannot control, side to side, up and down, or in circles.Full entry ), which are recorded to show how the inner ear's balance system works; head-positioning tests look for benign paroxysmal positional vertigoVER-tih-gohA false feeling that you or the room around you is spinning or moving.Full entry |
| Auditory brain stemBRAYN STEMThe lowest part of the brain, which connects it to the spinal cord and controls breathing, heart rate and other automatic functions.Full entry response (ABR) | Measures the electrical response of the brain stem's hearing pathway; it is one of the tests used to judge a child for a cochlear implant |
| computed tomographykum-PYOO-tid toh-MOG-ruh-feeAn imaging test that uses x-rays and a computer to make cross-section pictures of the inside of the body.tom/o cut, slice-graphy process of recordingFull entry and magnetic resonance imagingmag-NET-ik REZ-uh-nunts IM-uh-jingAn imaging test that uses a strong magnet and radio waves to make detailed pictures of the inside of the body.Full entry | CT is the study of choice for the temporal bone; MRI is the standard for the internal auditory canal and the facial nerveFAY-shul NERVThe seventh cranial nerve, which moves the muscles of the face and carries taste from the front of the tongue.Full entry canal, where an acoustic neuroma grows |
Diseases of the ear
The Core Curriculum's list for the ear: otitis externaoh-TY-tis ek-STUR-nuhInflammation or infection of the outer ear canal, often called swimmer's ear.ot/o ear-itis inflammationexterna outerFull entry and media, otosclerosis, mastoiditis, Meniere disease, tinnitusTIN-ih-tus, or tih-NY-tusA ringing, buzzing, roaring or hissing sound in the ears that does not come from outside.Full entry , a ruptured eardrum, vertigo and cholesteatoma.
| Condition | What it is | Surgery you may see |
|---|---|---|
| Otitis externa | A superficial infection of the outer ear and canal, called swimmer's ear | Rarely surgical |
| otitis mediaoh-TY-tis MEE-dee-uhInflammation or infection of the middle ear, the space behind the eardrum.ot/o ear-itis inflammationmedia middleFull entry | Infection or inflammation of the middle ear, acute or chronic, most common in children, especially those around cigarette smoke. A blocked eustachian tube leaves negative pressureNEG-uh-tiv PRESH-erPressure that is lower than the pressure around it, so air or fluid is drawn in.Full entry and fluid (an effusionih-FYOO-zhunFluid that has leaked out and collected in a body space, such as around the lungs, the heart or in a joint.Full entry ) behind the eardrum; left alone, the effusion can lead to infection, mastoiditis, hearing loss or a perforationper-fuh-RAY-shunA hole that goes all the way through the wall of an organ or tissue.per- throughforat bored (a hole)-ion processFull entry | Myringotomy and tubes when fluid lasts more than 8 to 12 weeks with hearing loss, or an infection does not answer to antibiotics |
| Ruptured tympanic membrane | A tear or hole (perforation) in the eardrum, most often from infection; also from a blow to the ear, a blast, a head injury, a cotton swab or other object in the canal, or a hole left after a tube comes out | Myringoplasty or tympanoplasty when it does not heal |
| Cholesteatoma | A growth of skin (squamous epitheliumep-ih-THEE-lee-umThe tissue that covers the body's surfaces and lines its organs, vessels and cavities.Full entry ) and its shed keratin trapped in the middle ear, sometimes a cyst. It is benign but slowly destroys bone: it is the most common cause of a broken ossicle chain, and it can cause drainage, infection, hearing loss and facial nerve paralysispuh-RAL-uh-sisLoss of the ability to move a part of the body, and sometimes loss of feeling in it.para- beside, abnormal-lysis looseningFull entry | Tympanoplasty and mastoidectomy, which must remove it all |
| Mastoiditis | Infection of the mastoid air cells, usually with severe otitis media; rare where antibiotics are easy to get. Chronic disease can follow cholesteatoma or a blocked eustachian tube | Mastoidectomy |
| Otosclerosis | Abnormal bone growth around the footplate of the stapes that locks it in place, so it cannot pass vibration to the inner ear. It usually starts around age 30 and worsens with age | Stapedectomy or stapedotomy |
| Meniere disease | Of unknown cause: attacks of vertigo lasting hours, low-pitched sensorineural hearing loss and tinnitus | Labyrinthectomy or vestibular nerve section for disabling vertigo |
| Tinnitus | Ringing or other sounds in the ear; it may have no known cause or be a sign of many ear diseases | Treats the cause |
| Vertigo | A sensation of dizziness; balance tests look for its cause | Treats the cause |
| Acoustic neuroma (vestibular schwannoma) | A benign tumor of the Schwann cells of the vestibular part of nerve VIII. The usual signs are hearing loss and tinnitus in one ear; a large one presses on the brain stem and the other cranial nerveKRAY-nee-ul NERVOne of the 12 pairs of nerves that come straight from the brain and brainstem rather than the spinal cord.Full entry . Tumors in both ears are the hallmark of neurofibromatosis type 2 | Removal through the temporal bone or skull, with the facial nerve monitored |
Diseases of the nose, sinuses and throat
The Core Curriculum's list for the upper airway: congenitalkun-JEN-ih-tulPresent at birth.con- withgen birth, origin-al relating toFull entry subglottic stenosisstuh-NOH-sisNarrowing of a passage or opening in the body, such as a blood vessel, heart valve or the spinal canal.sten/o narrow-osis conditionFull entry , laryngitislair-in-JY-tisInflammation of the larynx, the voice box.laryng/o larynx-itis inflammationFull entry , nasal polypPOL-ipA growth that sticks out from the lining of a hollow organ, such as the colon, nose or uterus.Full entry , sinusitissy-nuh-SY-tisInflammation of the lining of the sinuses, the air spaces around the nose.sinus sinus-itis inflammationFull entry , and tonsillitiston-sih-LY-tisInflammation of the tonsils, the two lumps of lymph tissue at the back of the throat.tonsill/o tonsil-itis inflammationFull entry and adenoiditis.
| Condition | What it is | Surgery you may see |
|---|---|---|
| Sinusitis | Inflammation or infection of the paranasal sinusSY-nusA hollow space in the body, most often one of the air-filled spaces in the skull bones around the nose.Full entry , from bacteria or fungi, often with a deviated septumSEP-tumA wall of tissue that divides two spaces or cavities, such as the two sides of the heart or nose.sept/o wall, partitionFull entry or poor drainage. It may be acute, recurrent or chronic. Invasive fungal sinusitis is often fatal | endoscopicen-doh-SKOP-ikDone with an endoscope, a thin tube with a light and camera passed into the body.endo- within-scopic viewingFull entry sinus surgery when antibiotics fail |
| Nasal polyps | Benign, grapelike growths of lining and connective tissuekuh-NEK-tiv TISH-ooBody tissue that supports, binds together and protects other tissues and organs.Full entry in the nose and sinuses. Large ones block airflow and drainage and change the voice. An inverting papilloma, a benign tumor of the lining, often comes back | Polypectomy, often with sinus surgery |
| Deviated septum | A septum bent off the midlineMID-lineAn imaginary line down the center of the body; also, a type of IV catheter placed in a vein of the upper arm.Full entry by injury (birth injury included), infection or a tumor. It blocks the nose, disturbs sleep, causes headaches and can lead to sinus disease and polyps | Septoplasty |
| Turbinate hypertrophyhy-PER-truh-feeAn increase in the size of an organ or tissue because its cells grow larger.hyper- above, excessive-trophy nourishment, growthFull entry | A chronically swollen inferior turbinate, or a middle turbinate malformed from birth (concha bullosa), that blocks airflow | Turbinate reduction |
| epistaxisep-ih-STAK-sisBleeding from the nose; a nosebleed.epi- upon-staxis drippingFull entry | Bleeding from the nasal cavity. Slow oozing is often treated with pressure and a spray; brisk or persistent bleeding needs packing or surgery | Packing, cautery, or endoscopic tying off of the bleeding artery |
| Choanal atresia | A bony or membranous plate that closes one or both choanae from birth. Newborns breathe through the nose, so a baby with both sides closed cannot breathe well and needs surgery at once | Choanal atresia repair |
| Tonsillitis and adenoiditis | Repeated or chronic infection of the tonsilTON-sulOne of the masses of lymph tissue at the back of the throat that help fight germs entering the mouth and nose.Full entry and adenoids, which also enlarge (hypertrophy). Enlarged adenoids can block the eustachian tubes and cause otitis media; they usually shrink by the teenage years | Tonsillectomy and adenoidectomy |
| Peritonsillar abscessAB-sesA closed pocket of pus in tissue, walled off by the body.Full entry | An abscess in the tissue around the tonsil's capsule; repeated ones can enlarge the tonsil | Tonsillectomy |
| obstructive sleep apneaub-STRUK-tiv SLEEP AP-nee-uhA sleep disorder in which the upper airway closes again and again during sleep, stopping or reducing breathing.a- without-pnea breathingFull entry (OSA) | During deep sleep the tongue and soft palateSOFT PAL-itThe soft, muscular back part of the roof of the mouth, with no bone in it.Full entry fall back and block the throat for 10 seconds to 2 minutes at a time, dropping the oxygen and waking the patient over and over. Over time it brings high blood pressure, heart rhythm problems and other harm. In children, big tonsils and adenoids are the most common risk factor | Tonsillectomy and adenoidectomy in children; UPPP and other palate surgery in adults |
| Laryngitis | Inflammation of the larynxLAIR-inksThe voice box: the part of the airway in the neck, above the windpipe, that holds the vocal cords.laryng/o larynxFull entry , a sign of many different throat diseases | Rarely surgical |
| Subglottic stenosis | A narrowing of the airway below the vocal cords. Congenital stenosis, from a malformed cricoid, is the third most common birth defect of the larynx; acquired stenosis, more common, follows long endotracheal intubationen-doh-TRAY-kee-ul in-too-BAY-shunPutting a breathing tube through the mouth or nose into the windpipe (trachea).endo- withintrache/o windpipe-al relating toFull entry | dilationdy-LAY-shunThe widening or opening up of a body part, such as the cervix during labor, the pupils or a blood vessel.dilat widen-ion processFull entry , airway reconstruction or a tracheostomytray-kee-OS-tuh-meeA surgical opening through the front of the neck into the windpipe, usually holding a tube that the person breathes through.trache/o windpipe-stomy surgical openingFull entry |
| lesionLEE-zhunAn area of tissue that has been damaged or has changed from normal, such as a sore, wound, lump or spot.Full entry of the larynx | Benign ones include vocal cord polyps and noduleNOD-yoolA small, firm, rounded lump of tissue that can be felt or seen, in or under the skin or in an organ.Full entry , papillomas, leukoplakia (a benign lesion of the lining) and a web of tissue across the airway. Cancer of the larynx is often linked to tobacco and alcohol | Laryngoscopy with biopsy or removal; laryngectomy for cancer |
Diseases of the mouth and salivary glands
- Cancer of the mouth and throat: often squamous cell carcinomaSKWAY-mus SEL kar-sih-NOH-muhA cancer that starts in squamous cells, the thin, flat cells of the skin's outer layer and the linings of some organs.Full entry , linked to tobacco, alcohol and the human papillomavirusHYOO-mun pap-ih-LOH-muh-vy-rusA common group of viruses spread by close skin-to-skin contact, most often during sex.Full entry (HPV; one reference links HPV to 70 to 90 percent of oropharynxor-oh-FAIR-inksThe middle part of the throat, behind the mouth, from the soft palate down to the top of the voice box.or/o mouthpharyng/o throatFull entry cancers). These cancers spread to the neck nodes, so their surgery often adds a neck dissectiondy-SEK-shunA tear in the inner layer of an artery wall that lets blood split the layers apart; also, the cutting apart of tissue in surgery.Full entry , and the defect may need a flap.
- salivary glandSAL-ih-vair-ee GLANDA gland that makes saliva and releases it into the mouth.Full entry disorders: inflammation (bacterial parotitis, or mumps, the most common viral cause), blockage by stones (calculi) and tumors. Most salivarySAL-ih-vair-eeRelating to saliva, the watery fluid in the mouth, or to the glands that make it.Full entry tumors are benign, slow-growing lumps, but they can turn malignant, so they are removed whole.
- Birth defects of the mouth, such as cleft lipkleft lipA split or opening in the upper lip that is present at birth.Full entry and palate, infections and injuries of the mouth and jaw, and tumors of the jaw are taught in chapter 37.
Thyroid and parathyroid disease
The Core Curriculum's thyroid and parathyroid glandpair-uh-THY-royd glandOne of four small glands behind the thyroid that control the amount of calcium in the blood.para- besidethyr/o thyroid gland-oid likeFull entry diseases (thyroid cancer, goiterGOY-terAn enlarged thyroid gland, seen or felt as a swelling at the front of the neck.Full entry , hyperthyroidismhy-per-THY-roy-diz-umA condition in which the thyroid gland makes too much thyroid hormone.hyper- above, overthyr/o thyroid gland-ism conditionFull entry such as Graves diseaseGRAYVZ dih-ZEEZAn autoimmune disease in which antibodies make the thyroid gland overactive.Full entry , hypothyroidismhy-poh-THY-roy-diz-umA condition in which the thyroid gland makes too little thyroid hormone.hypo- below, underthyr/o thyroid gland-ism conditionFull entry such as Hashimoto thyroiditishah-shee-MOH-toh thy-roy-DY-tisAn autoimmune disease in which the immune system attacks the thyroid gland, slowly reducing its hormone output.thyr/o thyroid-itis inflammationFull entry , and hyperparathyroidismhy-per-pair-uh-THY-roy-diz-umOveractivity of the parathyroid glands, which make too much parathyroid hormone.hyper- excessivepara- besidethyroid -ism conditionFull entry ) are taught in chapter 9, and with the operations that treat them in chapter 32.
Tests for the nose, throat and neck
- endoscopyen-DOS-kuh-peeA procedure that uses a thin, flexible tube with a light and camera to look inside the body.endo- within-scopy looking with an instrumentFull entry : a nasal endoscopeEN-duh-skohpA thin tube with a light and a camera that is passed into the body to look inside an organ or cavity.endo- within-scope instrument for viewingFull entry or a flexible nasolaryngoscope passed through the nose shows the nose, the sinuses, the adenoids and the larynx, often in the office; rigid endoscopy under anesthesiaan-us-THEE-zhuhLoss of feeling or sensation, often brought on by drugs so that surgery or a procedure can be done without pain.an- withoutesthesi/o feeling, sensation-ia conditionFull entry (laryngoscopy, bronchoscopybrong-KOS-kuh-peeA procedure in which a thin, lighted tube with a camera is passed through the nose or mouth to look inside the airways.bronch/o airway (bronchus)-scopy looking with an instrumentFull entry ) can take biopsies, or wash the lining with saline and brush off cells.
- Imaging: CT is the study of choice for the sinuses, and the scans for sinus surgery are planned on it and shown in the room; CT also stages cancer of the larynx and its neck nodes. MRI shows soft tissue best, such as the tongue and the throat. Ultrasound is usually the first test for thyroid and parathyroid lumps, helps with many salivary gland problems, and guides needle biopsies.
- Fine-needle aspirationas-puh-RAY-shunBreathing food, liquid, saliva or stomach contents into the airway and lungs; also, drawing fluid out with suction or a needle.Full entry (FNA): a thin needle draws cells from a neck or salivary lump before any surgery.
- Sleep study (polysomnogram): proves the sleep-disordered breathing that tonsil, adenoid or palate surgery is meant to treat.
4Position, prep and drape
Position
Almost every ENT case is supine. The head is the work site, so it is supported, steadied and turned with care: extreme stretching or twisting of the neck can injure the brachial plexusPLEK-susA network of nerves or blood vessels that branch and join together.Full entry or the cervicalSER-vih-kulRelating to the neck, or to the cervix, the lower end of the uterus.cervic/o neck, cervix-al relating toFull entry spine. Apply a safety strap, because the table is often tilted or rotated.
- Ear: the head is turned so the operative ear is up, with the patient close to the edge of the table on that side. The other ear rests in the hole of a doughnut or horseshoe headrest so nothing presses on it (endoscopicen-doh-SKOP-ikDone with an endoscope, a thin tube with a light and camera passed into the body.endo- within-scopic viewingFull entry ear surgery uses no headrest). For a long case such as a mastoidectomy, tape across the head to the table frame may hold it still, and tilting the table away from the surgeon cuts down how far the neck must turn. The head may be raised (reverse Trendelenburg positionree-VERS tren-DEL-un-burg puh-ZISH-unA position lying on the back on a bed or table that is tilted so the head is higher than the feet, with the body kept straight.Full entry ) to reduce bleeding.
- The table turned around: for most microscope cases the table is reversed or turned 180 degrees, so the patient's head is at the foot end. That leaves room under the table for the legs of the seated surgeon and assistant and for the microscope's floor stand. Gather enough adjustable stools for everyone who will sit.
- Nose and sinusSY-nusA hollow space in the body, most often one of the air-filled spaces in the skull bones around the nose.Full entry : a headrest supports the head yet lets it turn from side to side, the table is turned 180 degrees, and the head is raised about 30 degrees (reverse Trendelenburg) so bleeding and congestion drain away. For a right-handed surgeon working from the patient's right, the right arm is tucked; the other arm, with the IV, goes on an armboard or is tucked.
- Mouth, throat and neck: a doughnut headrest, the arms tucked, and often a shoulder roll under the shoulder blades to extend the neck. Place the roll carefully, so it does not press on the nerves of the neck. For a tonsillectomy, the table is turned 90 degrees so the surgeon has the whole head; for a neck dissectiondy-SEK-shunA tear in the inner layer of an artery wall that lets blood split the layers apart; also, the cutting apart of tissue in surgery.Full entry or parotidectomy, the head turns away from the operative side.

Prep
Hair: hair left near the site is a fire risk, so it is clipped if it must go, or coated with water-soluble gel and held back with nonmetal ties; an incision behind the ear, or one that runs up from the ear canal, needs the hair about 1 to 2 cm clear of it.
The ear: the circulator checks the solution before the prep starts, and a sterile cotton ball goes in the canal so prep cannot run in. The prep covers the ear and the skin around and behind it, out to the cheek, the back of the head, the temple and the upper neck, with a second site prepped if a graftGRAFTTissue or a man-made material moved into place in surgery to replace or repair a damaged part.Full entry will be taken.
use chlorhexidine (CHG) on the face, in or around the eyes or ears, or in the mouth. It is ototoxic: if it drains into the middle ear through the incision or a hole in the tympanic membranetim-PAN-ik MEM-braynThe thin, cone-shaped sheet of tissue between the outer ear canal and the middle ear; the eardrum.Full entry , it can damage hearing. Alcohol-based preps are not used in the ear, the mouth or the eyes either. An iodineEYE-uh-dyneA mineral the thyroid gland uses to make thyroid hormone; it is also used to kill germs on the skin and in some contrast dyes.Full entry prep without alcohol, such as povidone-iodinePOH-vih-done EYE-uh-dineA brown antiseptic solution of iodine used to kill germs on the skin before procedures and on wounds.Full entry , may be used on the outer ear, but not on the structures inside it, once the patient is checked for iodine sensitivitysen-sih-TIV-ih-teeHow strongly something responds; in lab work, which drugs stop a germ, or how well a test finds people who have a disease.Full entry .
The AST skin prep standard counts iodine (iodophor) preps as ototoxic too, and it rules out both CHG and iodophors for eye and facial preps, with cotton balls placed in the ears; it and a 2014 skills checklist keep CHG off all mucous membranes.
The nose, mouth and throat: the nose and mouth are not sterile places, and a case done entirely through them is often done without a skin prep, by the surgeon's choice and facility policy. When the face is prepped, it runs from the forehead to the upper neck, and the eyes are protected with eye shields, ointment and tape, or clear dressings.
The neck: from the chin to the nipples, including the sides of the neck and the shoulders, with a solution safe on the face. A laryngectomy or a neck dissection widens it: the lower face, the neck and the upper chest, and a donor site for a graft or flap when one may be needed. Keep saline ready so the surgeon can wipe prep off a flap to check its color.
Drape
- Ear: four towels around the ear, then a clear plastic drape with an opening (or a U-drape) that keeps the hair out, then a fenestrated ear drape or a split sheet. The surgeon may leave part of the face uncovered to watch it twitch if the facial nerveFAY-shul NERVThe seventh cranial nerve, which moves the muscles of the face and carries taste from the front of the tongue.Full entry is touched. Drilling cases add a pouch that catches the irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry . Use lint-free drapes: lint carried into the ear on instruments can cause granulomas and lasting hearing loss.
- Nose: a head drape. A small sheet with a towel on top goes under the head; the towel wraps around the head and is clipped at the hairline with a nonpenetrating clamp. Two towels go in a V at the neck, and a split sheet covers the body with its tails brought up beside the head.
- Mouth and throat: little draping, chiefly to protect the eyes and face: a head drape and a sheet over the chest.
- Neck: towels clipped or stapled in place, often a clear adhesive drape over them, then a thyroid sheet or a split sheet around the head. A towel and a magnetic drape on the chest keep instruments from sliding to the floor.
The microscope is draped too: see Equipment below.
5Instruments and equipment
Ear instruments
Ear instruments are built for a narrow canal: a short fulcrum (the hinge section), long, very delicate shanks, and working tips only 2 to 5 mm long. The set holds ear speculumSPEK-yoo-lumAn instrument used to open and hold open a body opening, such as the vagina, so the inside can be seen.Full entry in several sizes, knives with different blade shapes, picks, elevators, curettekyoo-RETA surgical instrument with a small spoon- or loop-shaped tip used to scrape tissue.Full entry , cup and alligator forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry , and fine scissors, with a few plastic surgery instruments (skin hooks, mosquito clamps, a #15 knife, delicate forceps) and small spring retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry .
- Keep them in their rack on the back table or Mayo, tips visible, and protect them from any knock; aim a separate light over the Mayo so you can tell them apart.
- Instruments used under the microscope or near a laser may have a dark, nonreflective finish to cut glare.
- The surgeon does not look away from the microscope, so pass each instrument already turned the way it will be used, and guide it into the surgeon's hand and view.
- Suction and irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry : in a field this small, a speck of blood or tissue can hide everything. Fine suction tips (Frazier and Baron types, about size 3 to 7 French) keep it dry; keep the tip open by suctioningSUK-shun-ingRemoving mucus, saliva or other secretions from the mouth, nose or airway with a tube connected to a suction source.Full entry water through it or clearing it with its stylet. A suction irrigator, one instrument or two, gives a fine stream of saline or lactated Ringer's solutionLAK-tay-tid RING-erz suh-LOO-shunAn isotonic IV fluid containing water, sodium, chloride, potassium, calcium and lactate.Full entry to wash away blood and bone dust and to cool the drill.






Nose instruments
Nasal instruments must reach deep into the nose from outside, so their hinge sits much farther from the finger rings than on general surgery instruments, and many tips are angled. Some are for soft tissue and some for bone and cartilageKAR-tih-lijFirm, smooth, rubbery tissue that cushions joints and gives shape to parts such as the ear, nose and windpipe.chondr/o cartilageFull entry , and the surgeon switches between them often.
- Specula and retractors: a nasal speculum (such as the Killian) opens the nostril; fine hooks, an alar retractor or an Aufricht retractor lift the skin.
- Knives: a #15 blade on a #7 handle for the first cut inside the nostril, then a Cottle, Ballenger swivel or button knife deeper in.
- Elevators: the Cottle, Freer and Lempert lift the lining off cartilage and bone; their edges are beveled but not sharp.
- Forceps: Takahashi forceps, with small cupped tips, cut and remove tissue; Blakesley forceps, Jackson alligator and cup forceps, Wilde forceps and Asch septumSEP-tumA wall of tissue that divides two spaces or cavities, such as the two sides of the heart or nose.sept/o wall, partitionFull entry forceps grasp, cut or straighten; bayonet forceps handle cottonoids and packing.
- Bone instruments: double-action rongeurron-ZHURA strong surgical instrument with sharp, cup-shaped jaws used to bite away small pieces of bone.Full entry such as the Jansen-Middleton, Kerrison and Takahashi rongeurs; a small gouge, chisel or osteotome struck with a mallet; a rasp to shave bone and an angled bayonet saw to trim small defects. Chapter 24 teaches how each is shaped.

Mouth, throat and airway instruments
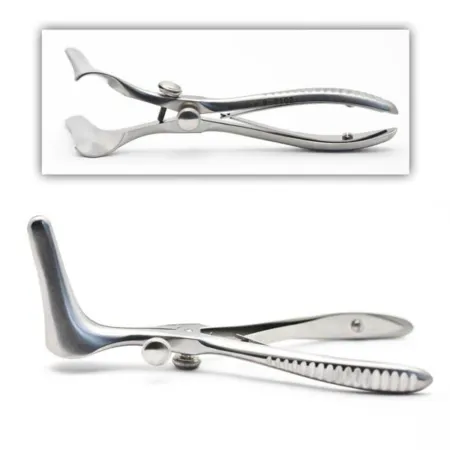
- Mouth gags: a Crowe-Davis, McIvor or Davis gag with a tongue blade of the right size holds the mouth open and is hooked to the edge of the Mayo standMAY-oh standA small tray on an adjustable stand placed over or beside the patient during surgery to hold the instruments used most often.Full entry . Once it is attached, the Mayo must not be moved or bumped, because that can injure the patient.
- tonsilTON-sulOne of the masses of lymph tissue at the back of the throat that help fight germs entering the mouth and nose.Full entry instruments: tonsil forceps or a tenaculum to grasp the tonsil, a curved tonsil knife and a dissector with a pillar retractor to free it, a snare, tonsil hemostatHEE-moe-statA clamp with finger rings and a locking ratchet used in surgery to grasp and close off bleeding vessels.hem/o blood-stat stopping, standing stillFull entry such as the Schnidt, and tonsil sponges on sponge forceps. Energy devices have replaced much of this cold set, though some surgeons still use it.
- Laryngoscopy instruments: rigid laryngoscopes with light carriers, a holder that suspends the scope so the surgeon has both hands free, long suction tips and cup biopsy forceps, and microlaryngeal instruments about 22 cm long, long enough to keep the surgeon's hands out of the microscope's view.
- tracheotomytray-kee-OT-uh-meeThe surgical cut made into the windpipe through the front of the neck.trache/o windpipe-tomy cutting, incisionFull entry instruments: a tracheaTRAY-kee-uhThe windpipe: the tube that carries air from the throat to the lungs.Full entry hook to lift the trachea, a tracheal dilatorDY-lay-terAn instrument used to stretch or widen an opening, canal or passage in the body.Full entry to spread the opening, and the tracheostomytray-kee-OS-tuh-meeA surgical opening through the front of the neck into the windpipe, usually holding a tube that the person breathes through.trache/o windpipe-stomy surgical openingFull entry with its obturatorOB-too-ray-terA smooth-tipped rod that fits inside a tube, such as a tracheostomy tube or cannula, to guide it in and then is taken out.Full entry .


Neck instruments
Neck cases use general surgery instruments with a thyroid or neck dissectiondy-SEK-shunA tear in the inner layer of an artery wall that lets blood split the layers apart; also, the cutting apart of tissue in surgery.Full entry set: neck retractors, fine and right-angle clamps, and many hemostats, because the neck is shallow but full of blood vessels. Penrose drains or vessel loops pull gently on nerves and large vessels, and vascular clamps are added for a radical neck dissection.
Equipment
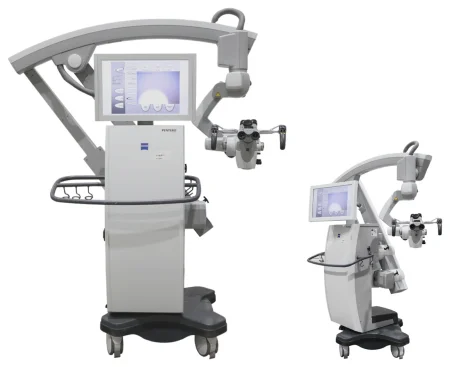
- Operating microscope: can be used in every middle and inner earIN-er EERThe deepest part of the ear, inside the skull bone, which holds the organs of hearing and balance.Full entry operation, and in larynxLAIR-inksThe voice box: the part of the airway in the neck, above the windpipe, that holds the vocal cords.laryng/o larynxFull entry microsurgery. The usual objective lens is 250 mm for the ear (some surgeons choose 200, 300 or 400 mm) and 400 mm for the larynx. The coarse adjustments are made before surgery and it is draped within an hour of use; chapter 23 teaches its care. Take care not to throw out the eyepieces with the used drape.
- High-speed drill: needed in every ear case that removes bone, to open the mastoid, widen the bony canal or make a hole in the stapes footplate. Burrs from 0.5 to 7 mm are cutting burrs, which remove bone fast, or diamond burrs, which grind slowly and are safer near the facial nerveFAY-shul NERVThe seventh cranial nerve, which moves the muscles of the face and carries taste from the front of the tongue.Full entry and other vital structures. Irrigate the burr tip the whole time it runs, with the suction irrigator or a 3 to 5 mL syringe on an 18-gauge angiocatheter, to keep the bone from heating, wash away bone dust and keep the burr from clogging; clean a clogged burr with a sterile wire brush.
- Microdebrider (shaver): a powered handpiece with rotating blades that cuts small pieces of tissue and suctions them away at once, so it clears blood and debris as it works. Blades come straight or bent at 15 or 30 degrees. It is used in sinusSY-nusA hollow space in the body, most often one of the air-filled spaces in the skull bones around the nose.Full entry , nasal, adenoid and laryngeal surgery.
- endoscopeEN-duh-skohpA thin tube with a light and a camera that is passed into the body to look inside an organ or cavity.endo- within-scope instrument for viewingFull entry : angled sinus scopes of 4 to 5 mm (see FESS below) and thinner ear scopes of 2.7 to 4 mm.
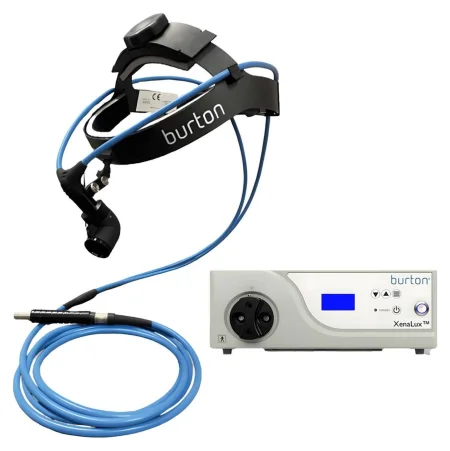
- Headlight: most nose and throat surgeons wear one. Check the light source before the case.
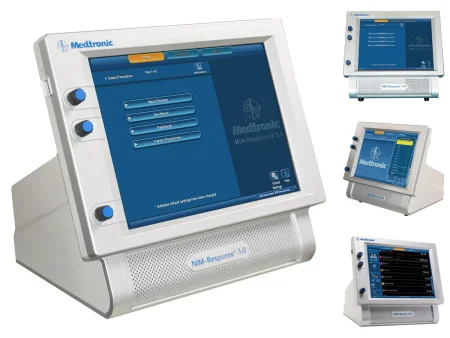
- Nerve monitor: a nerve integrity monitor records the muscles a nerve supplies (electromyographyih-lek-troh-my-OG-ruh-feeA test that records the electrical activity of muscles, usually through thin needles placed in the muscle.electr/o electricitymy/o muscle-graphy recordingFull entry , EMG) and sounds an alert when an instrument comes near the nerve; a stimulator probe on the field finds the nerve. Details are with each case below.
- Energy: monopolar and bipolarby-POH-lerHaving two poles or two opposite ends; most often used as a short form of bipolar disorder.bi- twopolar having polesFull entry electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry , a suction coagulator for the throat and adenoids, radiofrequency and coblation devices (the Core Curriculum lists the Coblator handpiece), ultrasonic shears, and lasers (carbon dioxideKAR-bun dy-OK-sideA gas made by the body's cells as waste, carried in the blood to the lungs and breathed out.Full entry , KTP, Nd:YAG and Er:YAG), the CO2 laser often fitted to the microscope through a micromanipulator. A smoke evacuator is used with the ESU and the laser.
- Navigation: an image-guided system that tracks instruments on the patient's computed tomographykum-PYOO-tid toh-MOG-ruh-feeAn imaging test that uses x-rays and a computer to make cross-section pictures of the inside of the body.tom/o cut, slice-graphy process of recordingFull entry , used most in sinus and skull base surgery; see the sinus surgery section.



Medications on the field
The small, crowded spaces of the nose, ear and throat bleed easily, and a little blood hides everything, so most ENT cases use drugs that shrink blood vessels (vasoconstrictors) as well as numb.
- Injected: a local anestheticLOH-kul an-es-THET-ikA drug that blocks feeling in one part of the body without making the person unconscious.Full entry with epinephrineep-ih-NEF-rinA hormone and drug, also called adrenaline, that raises heart rate and blood pressure and opens the airways.Full entry , usually 1% lidocaineLY-doh-kaynA local anesthetic that numbs an area, also given by IV to treat some fast, abnormal heart rhythms.Full entry with epinephrine 1:100,000, injected into the lining or the skin. Have a 10 mL Luer-lock syringe and fine needles (such as 25 or 27 gauge) ready, with extra labeled local on the field.
- Topical: cottonoids soaked in a vasoconstrictor are packed into the nose with bayonet forceps and a small nasal speculum, often before the prep: cocaine 4% or 10% (a topical anesthetican-us-THET-ikA drug that causes loss of feeling, with or without loss of consciousness.an- withoutesthesi/o feeling, sensation-ic relating toFull entry and vasoconstrictor, for topical use only, no more than 1 mg/kg), oxymetazoline 0.05% (Afrin), epinephrine 1:1,000, or phenylephrinefen-il-EF-rinA drug that tightens blood vessels, given IV to raise low blood pressure and used in nose sprays and eye drops.Full entry . vasoconstrictionvay-zoh-kun-STRIK-shunThe narrowing of blood vessels when the muscle in their walls tightens.vas/o vesselconstriction narrowingFull entry peaks about 10 to 12 minutes after epinephrine. In the ear, the scrub soaks small cotton balls, 2 to 4 mm across, in topical epinephrine; up to 10 are made and counted before the case.
- Antibiotic and steroidSTAIR-oydA fat-based chemical built from cholesterol; the group includes hormones such as cortisol and estrogen, and many drugs.ster/o solid-oid likeFull entry drops or ointments: such as ofloxacin ear drops after a tube, antibiotic and steroid drops in the canal, antibiotic ointment on nasal packing (mupirocinmyoo-PEER-oh-sinAn antibiotic ointment or cream used on the skin or inside the nose.Full entry is one), and bacitracinbas-ih-TRAY-sinAn antibiotic used mostly as an ointment on the skin to prevent infection in minor cuts, scrapes and burns.Full entry ointment, applied with a sterile applicator or cotton swab.
- hemostatichee-moh-STAT-ikStopping bleeding; also, a product or agent used to stop bleeding.hem/o blood-stasis stopping, standing still-ic relating toFull entry : absorbable gelatin sponge, cut into tiny pieces and used alone or soaked in epinephrine, packs the ear and holds graftGRAFTTissue or a man-made material moved into place in surgery to replace or repair a damaged part.Full entry ; oxidized cellulose and microfibrillar collagenKOL-uh-jenThe main structural protein of the body, which gives strength to skin, bones, tendons, ligaments and scar tissue.coll/a glue-gen producingFull entry may also be used, and a gelatin matrix and topical thrombinTHROM-binAn enzyme in the blood that turns fibrinogen into fibrin, the threads that hold a blood clot together.thromb/o clot-in substanceFull entry are ready for a large neck dissection.
let topical epinephrine 1:1,000 be confused with the 1:100,000 strength mixed into a local anesthetic. The topical strength is for the surface only. Label epinephrine the moment it reaches the back table, keep it in its own area, and check the drug, its strength and the amount aloud each time you receive it and pass it.
Cocaine and epinephrine can raise the heart rate and blood pressure and trigger abnormal rhythms; the anesthesia provideran-us-THEE-zhuh pruh-VY-derThe licensed professional who gives anesthesia and watches over the client's breathing and vital functions during a procedure.Full entry watches for this and treats it, often with esmolol, metoprololmeh-TOH-proh-lolA beta blocker that slows the heart rate and lowers blood pressure.Full entry or labetalolluh-BAY-tuh-lolA drug that blocks both alpha and beta receptors to lower blood pressure, given IV or by mouth.Full entry . The topical drugs are set up on a separate small prep table before the patient arrives, and the cottonoids used for them are counted. Chapter 12 teaches drugs on the field, and chapter 13 the maximum doses of local anesthetics.
Sponges, counts and specimens
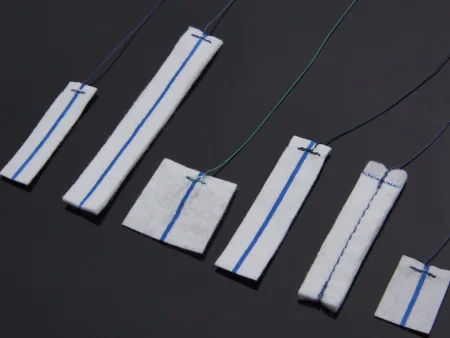
Cottonoids (flat patties), cotton balls and round gauze sponges are the usual sponges. In the nose, mouth and throat, every sponge has a string sewn into it so it can be found and pulled out, and the patties show on an X-ray, because a sponge left behind can be swallowed or breathed in, causing injury or death. A patty slid back along the floor of the nose can slip past the palate. Count them before and after, in every ear case too, however small.
One reference leaves the count for a myringotomy to facility policy.
A throat pack, gauze with a radiopaqueray-dee-oh-PAYKBlocking x-rays, so the material shows up white on an x-ray image.radi/o radiation, x-rayopaque not letting throughFull entry thread, is moistened and placed in the back of the throat to keep blood and secretionsih-KREE-shunA substance a gland or cell makes and releases, such as mucus, saliva, sweat or a hormone.Full entry from running down, where it must be easy to retrieve. It is counted, its placement is announced so the whole team knows it is there, and its removal is confirmed before the breathing tube comes out. Some references do not count it with the sponges, so facility policy decides how it is recorded.

Specimens are many and small. Keep each separate and labeled with its exact site and side (right and left tonsil, each biopsy from the larynx), pick every bit of tissue off the tips of biopsy forceps, and have cups, labels and a marking pen on the field.
Dressings
- Ear: a cotton ball in the canal for small cases. After a bigger case, a mastoid dressing: fluffed gauze over the ear and incision, held by rolled gauze wrapped around the head, or a ready-made Glasscock dressing, gauze held under a molded plastic shield with Velcro straps.
- Nose: packing is a dressing placed into a body space. In the nose it is a 1/4 or 1/2 inch gauze strip, which may carry an antibacterial ointment, to absorptionub-ZORP-shunThe taking in of a substance, such as a drug or a nutrient, into the bloodstream.Full entry drainage and control bleeding. Soft splints go inside the nose and a firm splint (metal, foam or fiberglass) outside it, with a "mustache" dressing, a folded gauze taped under the nose to catch drainage.
- Mouth and throat: no dressing.
- Neck: a tracheotomy gets split drain sponges and tracheostomy ties; other neck wounds get a nonadherent dressing and a clear film or gauze, with a suction drain after a large dissection.

6Fire, lasers and smoke in the airway
Chapter 20 teaches fire, laser and smoke safety in full. Airway fires are more common in head and neck and ENT surgery, tracheostomytray-kee-OS-tuh-meeA surgical opening through the front of the neck into the windpipe, usually holding a tube that the person breathes through.trache/o windpipe-stomy surgical openingFull entry and tonsillectomy included, because the oxygen flowing to the airway, the heat of the electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry , a laser, a light cable or the drill, and the fuel of drapes, sponges, hair and the breathing tube all meet in one small space.
- Before an ignition source is used in or near the airway, the surgeon tells the anesthesia provideran-us-THEE-zhuh pruh-VY-derThe licensed professional who gives anesthesia and watches over the client's breathing and vital functions during a procedure.Full entry , who turns the oxygen down to the least the patient needs; the surgeon waits for it to fall, and the airway is suctioningSUK-shun-ingRemoving mucus, saliva or other secretions from the mouth, nose or airway with a tube connected to a suction source.Full entry first.
- Pack the back of the throat with wet sponges, and keep wet towels or sponges around the tube and the site. Keep sterile saline on the field to cool hot devices and to put out a fire.
The laser airway: in laser surgery of the mouth, throat or airway, the anesthesia provider uses a laser-resistant breathing tube made for that laser, within its power limits. Its cuff is filled with saline tinted with methylene blue: the saline soaks up heat, and the blue shows at once if the beam bursts the cuff. Counted wet pledgets are placed around the tube and kept wet, the oxygen is kept between 21 and 30 percent, and nitrous oxide is not used.
Some references describe wrapping a standard breathing tube in metallic foil before laser surgery of the airway, and a 2014 textbook fills the cuff with sterile water and names a halon extinguisher for laser fires.
If a fire starts: the team follows chapter 20's steps for a fire on the patient or in the airway, and your first job is to hand over the saline or water at once.
Smoke: evacuate it at its source, as chapter 20 teaches, keeping the wand out of the laser beam's path; where a larynxLAIR-inksThe voice box: the part of the airway in the neck, above the windpipe, that holds the vocal cords.laryng/o larynxFull entry case makes little plume, wall suction with an in-line filter may do.
7The ear
Approaches to the ear
Most ear operations go in through the ear canal or from behind the ear.
- Transcanal: through the canal, with a speculumSPEK-yoo-lumAn instrument used to open and hold open a body opening, such as the vagina, so the inside can be seen.Full entry , lifting a flap of canal skin together with the tympanic membranetim-PAN-ik MEM-braynThe thin, cone-shaped sheet of tissue between the outer ear canal and the middle ear; the eardrum.Full entry (a tympanomeatal flap). It serves the eardrum and the middle ear, as in a stapedectomy or ossiculoplasty.
- Endaural: two short cuts at the opening of the canal, with a #15 blade, for the canal, the eardrum and stapes surgery.
- Postauricular: a curved incision 2 to 5 mm behind the ear, in the fold where the ear meets the head. It gives a wide view and is used for most tympanoplasties and for the mastoid.
The microscope has long been the tool for these cases; the endoscopeEN-duh-skohpA thin tube with a light and a camera that is passed into the body to look inside an organ or cavity.endo- within-scope instrument for viewingFull entry is now used too. In endoscopicen-doh-SKOP-ikDone with an endoscope, a thin tube with a light and camera passed into the body.endo- within-scopic viewingFull entry ear surgery the scope goes down the canal and its angled lenses look around corners the microscope cannot see, but the surgeon works one-handed and loses depth perceptionper-SEP-shunThe brain's way of taking in and making sense of what the senses detect; also a person's own view or understanding of something.Full entry . No scope holder is used, because a holder knocked out of place could badly injure the ear. Keep a microscope ready in every endoscopic case, and stand where you can see the monitor without blocking the surgeon's view of it.
In endoscopic ear surgery the light source must not go above 50 percent, because the light can burnBURNAn injury to the skin or deeper tissues caused by heat, chemicals, electricity, radiation or friction.Full entry the canal and middle ear; the setting is checked at the time-outTYM-owtA pause just before a procedure when the whole team confirms the right client, procedure and site; also, a short break to calm a child.Full entry . Wipe the lens with a lens wipe soaked in saline, never a gauze sponge, which scratches it.
Myringotomy with tubes
What and why: a myringotomy is a small cut in the pars tensa, the tight main part of the eardrum, to let trapped fluid drain. A tympanostomy tube (also called a pressure equalization or ventilationven-tuh-LAY-shunAir moving in and out of the lungs as a person breathes.Full entry tube) is placed in the cut so it stays open and air reaches the middle ear. It is mostly a child's operation, done when fluid behind the eardrum lasts more than 8 to 12 weeks with hearing loss, which can slow speech and language, or when an infection does not answer to antibiotics or causes complications such as facial nerveFAY-shul NERVThe seventh cranial nerve, which moves the muscles of the face and carries taste from the front of the tongue.Full entry paralysispuh-RAL-uh-sisLoss of the ability to move a part of the body, and sometimes loss of feeling in it.para- beside, abnormal-lysis looseningFull entry . It is often done with an adenoidectomy.
Before surgery: an adult may have it under topical anesthesiaan-us-THEE-zhuhLoss of feeling or sensation, often brought on by drugs so that surgery or a procedure can be done without pain.an- withoutesthesi/o feeling, sensation-ia conditionFull entry ; a child usually has general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry , often given by mask. The patient lies supine with the head turned, the ear up, the head steadied on a foam headrest. The skin prep is usually left out, and draping is small, a few towels. A small microscope on a floor stand with a 250 mm lens is enough.
One reference treats a myringotomy as a clean rather than sterile case, with only a Mayo standMAY-oh standA small tray on an adjustable stand placed over or beside the patient during surgery to hold the instruments used most often.Full entry and sterile gloveSTAIR-ul gluvA glove that has been sterilized and packed so it can touch a sterile field or an open body area without bringing in germs.Full entry but no gown; follow your facility's policy.
Setup: a myringotomy knife (a disposable spear, lancet or sickle blade on its handle), ear specula in several sizes, ear curettekyoo-RETA surgical instrument with a small spoon- or loop-shaped tip used to scrape tissue.Full entry , a fine suction tip and tubing, alligator forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry , a fine pick or needle, a culture tube if cultures are wanted, and the tubes the surgeon chose. Tubes are made to stay in for different lengths of time, from a few months to years.
Key steps:
- The surgeon places the speculum (pass the size that fits the canal) and clears wax with a curette; wipe the curette clean on a sponge between passes.
- A small curved or radial cut is made in the front lower part of the pars tensa (one reference places it in the back lower part).
- The fluid is suctioningSUK-shun-ingRemoving mucus, saliva or other secretions from the mouth, nose or airway with a tube connected to a suction source.Full entry , and a culture may be taken. The fluid is often thick, so keep the suction tip clear.
- Pick up the tube in the jaws of the alligator forceps, without touching the tube itself, and pass it. The surgeon sets it in the cut and seats it with a fine needle or pick.
- Antibiotic drops, such as ofloxacin ear drops, or antibiotic and steroidSTAIR-oydA fat-based chemical built from cholesterol; the group includes hormones such as cortisol and estrogen, and many drugs.ster/o solid-oid likeFull entry drops may go in the canal, then a cotton ball.
- For both ears, the head is turned and the team changes sides.
The tubes are implants: they are recorded in the patient's chart as facility policy and the federal rules for medical devices require.
Wound class: one reference classes a myringotomy as Class II. When the cut drains pus from an infection already present, it fits the CDC's Class IV; follow your facility's policy.
After surgery: most children go home within about an hour. The ear canal is kept dry while the tubes are in. Complications include more infections, a tube that stays in and must be removed, and a hole in the eardrum that does not heal once the tube falls out.

Myringoplasty and tympanoplasty
What and why: a myringoplasty closes a small hole in the eardrum that will not heal, without entering the middle ear. A tympanoplasty repairs the eardrum and the middle ear, and rebuilds the chain of ossicles when it is broken. It treats conductive hearing loss from injury or infection, a perforationper-fuh-RAY-shunA hole that goes all the way through the wall of an organ or tissue.per- throughforat bored (a hole)-ion processFull entry , a broken ossicle chain, chronic or recurring otitis mediaoh-TY-tis MEE-dee-uhInflammation or infection of the middle ear, the space behind the eardrum.ot/o ear-itis inflammationmedia middleFull entry , an eardrum pulled in by a blocked eustachian tube, and cholesteatoma; some patients want it so they can bathe and swim without water entering the ear.
Before surgery: general anesthesia in most cases. Supine, head turned, the arm on the operative side tucked. The ear and any graftGRAFTTissue or a man-made material moved into place in surgery to replace or repair a damaged part.Full entry site are prepped and draped as for an ear case, and the microscope is draped. An audiogram is in the room.
Grafts: the most common graft is the patient's own temporalis fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry , the tough covering of the temporalis muscle above the ear, which is easy to reach and heals well. Others are loose connective tissuekuh-NEK-tiv TISH-ooBody tissue that supports, binds together and protects other tissues and organs.Full entry , the perichondrium of the tragus, a vein, or a small plug of fat from the earlobe for a small myringoplasty. A donated eardrum (a homograft) carries a risk of passing on disease. The fascia is laid on a fascia press or a Teflon block to flatten and dry so it can be trimmed: leave the press open unless the surgeon says otherwise, and keep the graft safe on the back table.
Two ways to place the graft: in the underlay method, the graft goes under the eardrum remnant, held up by gelatin sponge packed in the middle ear; it suits a small perforation with little infection. In the overlay method, the canal skin and the skin of the eardrum remnant are removed, the bony canal may be widened with the drill, and the graft goes on the outside; it suits a large perforation, a badly damaged eardrum or widespread infection.
Setup: a tympanoplasty set with ear specula, sickle knives, picks, a Rosen needle and House elevators, cup and alligator forceps, Bellucci scissors, a malleus nipper and an incudostapedial joint knife; the fascia press or block; the drill; fine suction; ossicle prosthesispros-THEE-sisAn artificial body part that replaces one that is missing or does not work, such as an artificial leg, joint, eye or heart valve.Full entry on hold.
Medications: lidocaineLY-doh-kaynA local anesthetic that numbs an area, also given by IV to treat some fast, abnormal heart rhythms.Full entry with epinephrineep-ih-NEF-rinA hormone and drug, also called adrenaline, that raises heart rate and blood pressure and opens the airways.Full entry injected behind the ear and in the canal; tiny gelatin sponge pieces soaked in epinephrine for bleeding; a steroid and antibiotic solution for the packing.
Key steps:
- Lidocaine with epinephrine is injected, and the ear is opened through the canal, an endaural incision or a postauricular incision.
- The temporalis fascia is taken and set to dry.
- The canal skin and eardrum are lifted as a flap (or removed, for an overlay graft), and the edges of the hole are scraped fresh with a sickle knife, pick or cup forceps so the graft will heal to them.
- Overhanging bone may be drilled or curetted away, the middle ear is explored, and each ossicle is checked; a diseased one may be removed and replaced with a prosthesis (below).
- The graft is trimmed, picked up with alligator forceps and placed with a fine needle or elevator; small gelatin sponge pieces hold it in place.
- The flap is laid back, the canal is packed with gelatin sponge or ointment, and the incision is closed (deep layers 3-0 absorbable, skin 4-0 absorbable).
- A mastoid or pressure dressing goes on for the first day.
Myringoplasty steps: under the microscope (250 mm lens, often undraped), the canal is cleared, and the surgeon everts (turns back) the edges of the hole and scores them with a fine needle or right-angle pick so they will heal. A patch goes over the hole: gelatin foam, or a small fat graft from a 5 to 8 mm cut behind the earlobe, kept moist in a little saline until it is placed. The canal is packed with gelatin sponge soaked in a steroid and antibiotic solution, and a Glasscock dressing goes on.
Wound class: Class I, clean.
After surgery: the canal packing stays 1 to 2 weeks and is removed in the office. The patient avoids blowing the nose hard, sneezes with the mouth open, avoids straws, keeps the ear dry, avoids sudden head movements and heavy lifting, and expects some popping and crackling in the ear. The nurse checks the facial nerve.
Ossicular chain reconstruction
What and why: an ossiculoplasty rebuilds the chain of ossicles when one is eroded or separated, after long-lasting infection, an injury or a cholesteatoma. Most often the incus is replaced. It is often part of a tympanoplasty, and in cholesteatoma it may wait for a second, planned operation, when the surgeon also checks that the disease has not come back.
Materials: the patient's own ossicle (the incus or the head of the malleus), reshaped with the drill, is often used in children without cholesteatoma. Otherwise a prosthesis is used: a partial ossicular replacement prosthesis (PORP) runs from the head of the stapes to the eardrum or graft; a total ossicular replacement prosthesis (TORP) runs from the stapes footplate to the eardrum. Hydroxyapatite is close to bone in mineral content and is well tolerated but brittle; titanium is stiff and light. The surgeon trims the prosthesis to fit the gap.

Key steps: the patient is prepped and draped as for a stapedotomy or a tympanoplasty, and the steps are those of a stapedotomy (below), except that the stapes footplate is left closed. The aftercare is the teaching for every ear operation: no hard nose blowing, sneezing with the mouth open, no straws and dry ears. A prosthesis is an implant: have the one the surgeon chose ready before the case, and record its serial and lot numbers as facility policy directs.
Wound class: Class I, as for a tympanoplasty.
Stapedectomy and stapedotomy
What and why: these operations treat otosclerosis, in which bone fixes the stapes so it cannot move. In a stapedotomy, the upper part of the stapes (the superstructure) is removed, a tiny hole is made in the footplate, and a prosthesis is hooked to the incus with its other end in the hole. In a stapedectomy, now done less often, the whole stapes comes out, a graft covers the oval window, and the prosthesis rests on the graft. In one reference's figures, about 90 percent of patients keep a lasting gain in hearing and about 1 percent lose hearing for good.
Before surgery: an adult often has local anesthesiaLOH-kul an-es-THEE-zhuhNumbing medicine applied to or injected into one small area, so a procedure there is not felt while the person stays awake.Full entry with sedationsih-DAY-shunA calm, relaxed or sleepy state brought on by drugs, or the use of drugs to cause it.sed calm, settle-ation processFull entry , so the surgeon can test the hearing before the end; a child or a very anxious patient has general anesthesia. Supine, head turned, the arm on that side tucked.
Setup: a stapes set with a speculum holder (so the surgeon has both hands free), picks, footplate hooks, a joint knife, Bellucci scissors, cup and alligator forceps and a crimper; a microdrill with a 1 mm burr or a laser (carbon dioxideKAR-bun dy-OK-sideA gas made by the body's cells as waste, carried in the blood to the lungs and breathed out.Full entry , or argon in one reference) for the footplate; prosthesis sizers or a measuring rod; and the prosthesis, of stainless steel, titanium, platinum, nitinol or Teflon, often a piston or bucket-handle design. Use only very fine suction tips (18 to 26 gauge): a large tip can pull fluid (perilymph) out of the inner earIN-er EERThe deepest part of the ear, inside the skull bone, which holds the organs of hearing and balance.Full entry through the open oval window and cause permanent hearing loss.
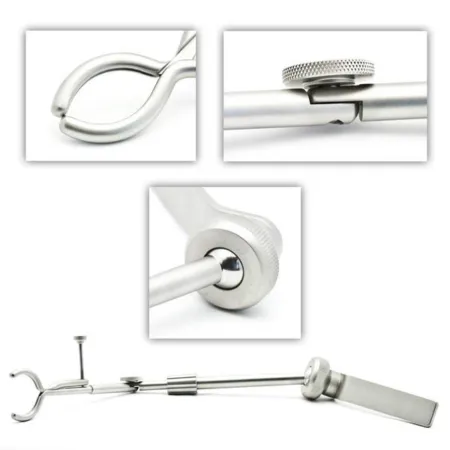
Key steps:
- A small graft (fascia, fat, perichondrium or vein) may be taken first, to cover the oval window.
- Lidocaine with epinephrine goes into the canal, the speculum is fixed in its holder, and the canal is cleaned with fine suction.
- A tympanomeatal flap is raised and the eardrum folded forward. Bone in the way may be curetted or drilled. The surgeon tries to save the chorda tympani nerve, because it carries taste.
- The distance from the incus to the footplate is measured.
- The joint between the incus and stapes is separated with a joint knife, the stapedius tendon is cut with Bellucci scissors, and the crura are broken (or lasered) and the superstructure removed with alligator or cup forceps.
- A hole is made in the footplate with a laser, a pick or the microdrill (or, for a stapedectomy, the footplate is removed).
- Load the measured prosthesis on smooth alligator forceps or a hook and pass it. The surgeon places it and crimps its wire around the long process of the incus.
- Under local anesthesia the surgeon may whisper to test the hearing. Tiny pieces of graft are packed around the base of the prosthesis to steady it, the flap goes back, the canal is packed with gelatin sponge, and cotton and a small dressing go on.
Wound class: Class I.
After surgery: usually outpatient, but nausea or dizziness may keep the patient overnight. The patient avoids sudden movements, loud noise and water in the ear until healed, and for a few days avoids pressure on the ear: blowing the nose, heavy lifting, swimming and flying. vertigoVER-tih-gohA false feeling that you or the room around you is spinning or moving.Full entry , tinnitusTIN-ih-tus, or tih-NY-tusA ringing, buzzing, roaring or hissing sound in the ears that does not come from outside.Full entry , a change in taste, hearing loss, a hole in the eardrum and brief facial weakness are the complications. A stainless steel prosthesis can shift in an magnetic resonance imagingmag-NET-ik REZ-uh-nunts IM-uh-jingAn imaging test that uses a strong magnet and radio waves to make detailed pictures of the inside of the body.Full entry scanner, so the implant record matters.
Mastoidectomy and tympanomastoidectomy
What and why: a mastoidectomy removes diseased bone, the mastoid air cells and their lining. Before antibiotics it was done for infection; today it is done mostly for cholesteatoma, and for chronic infection that antibiotics have not cleared. A tympanomastoidectomy adds a tympanoplasty in the same operation.
Types:
- Simple (cortexKOR-teksThe outer layer of an organ, especially the folded gray outer layer of the brain.cortic/o cortex, outer layerFull entry ): the diseased mastoid bone is removed, and the ossicles, eardrum and canal wall are kept.
- Canal-wall-up: the posterior wall of the ear canal is kept, so the ear looks and works normally.
- Modified radical (canal-wall-down): some ossicles and the canal wall are removed, while the eardrum and some ossicles stay so the patient can hear.
- Radical: the canal wall, the ossicles and the eardrum are removed; rarely done except for disease that cannot otherwise be removed.
After a modified radical or radical mastoidectomy, the opening of the canal is widened (a meatoplasty) so the open cavity can be cleaned; a canal-wall-down cavity needs cleaning at least once a year.
Before surgery: general anesthesia; supine, head turned and taped if needed, the arm on that side tucked. A skin graft, if planned, is taken before the ear prep. The facial nerve monitor's electrodes go in before the prep, and the drapes include a pouch for the irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry .
Setup: a mastoid set (the tympanoplasty instruments plus mastoid retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry such as a small Weitlaner, elevators and curettes), the drill with cutting and diamond burrs, the suction irrigator, the facial nerve monitor, a graft block, gelatin sponge and the microscope.
Key steps:
- The incision site is injected with lidocaine and epinephrine, a postauricular incision is made, and the periosteum is lifted with an elevator; a self-retaining retractor holds the wound.
- A temporalis fascia graft is taken and kept safe on the back table.
- The surgeon drills the mastoid, starting with a large cutting burr and changing to smaller and diamond burrs near the facial nerve and other vital structures. Run the suction irrigator steadily the whole time, keep burrs ready, and lock the drill's safety before every burr change so it cannot start in your hand.
- The cholesteatoma and any diseased ossicles are removed with a Rosen needle and picks; the ossicles and the cholesteatoma are specimens. Clean the microinstrument tips with lens wipes, not sponges.
- The ossicles are rebuilt now, or at a planned second operation.
- The graft is placed as for a tympanoplasty, and the cavity and canal are packed with tiny squares of gelatin sponge soaked in saline, antibiotic solution or thrombinTHROM-binAn enzyme in the blood that turns fibrinogen into fibrin, the threads that hold a blood clot together.thromb/o clot-in substanceFull entry .
- The incision is closed in layers, and a mastoid dressing goes on.
Wound class: Class I, clean; an ear that is actively infected fits the CDC's Class IV, dirty-infected.
After surgery: the patient keeps the ear dry, does not blow the nose hard until it has healed, and is back to normal activity in about 2 weeks. Facial nerve damage, infection and meningitismen-in-JY-tisInflammation of the meninges, the membranes that cover the brain and spinal cord.mening/o meninges-itis inflammationFull entry are the serious complications, so the facial nerve check after surgery matters.
Cochlear implant
What and why: a cochlear implant gives a sense of sound to a patient with severe to profound sensorineural hearing loss, whose hair cells in the cochlea are damaged or missing but whose hearing nerve works. The causes include infection, loud noise, ototoxic drugs, autoimmune diseaseaw-toh-ih-MYOON dih-ZEEZA disease in which the immune system attacks the body's own healthy tissue.auto- selfimmune protectedFull entry , stroke and tumors, and many children are born deaf. A sound processor worn behind the ear picks up sound and sends it to a receiver implanted under the skin, which sends signals to electrodes inside the cochlea; they stimulate the auditory nerve.
Adults are considered when hearing aids no longer help them understand speech; children from about 12 months of age when they are profoundly deaf and hearing aids have not helped (one reference says surgery waits until age 2). Implants in both ears, and for deafness in one ear, are now done too. computed tomographykum-PYOO-tid toh-MOG-ruh-feeAn imaging test that uses x-rays and a computer to make cross-section pictures of the inside of the body.tom/o cut, slice-graphy process of recordingFull entry or MRI checks the inner ear, the facial nerve and the hearing nerve beforehand. A child who was deaf before learning to talk develops speech with the implant; an older patient must learn to make sense of the new sounds, with extensive training.
Before surgery: general anesthesia; supine, head turned. The hair over the temple may be clipped, and the surgeon outlines the incision with a marking pen, injects lidocaine with epinephrine 1:100,000 and places the facial nerve monitoring electrodes, all before the prep.
Setup: a cochlear implant set with the major ear and minor instruments, the drill and burrs, bipolarby-POH-lerHaving two poles or two opposite ends; most often used as a short form of bipolar disorder.bi- twopolar having polesFull entry forceps, the implant, and the electrode positioner from the implant kit.
Key steps:
- A postauricular incision is made; the flap of skin and muscle is raised with a needle-tip electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry and held with skin hooks and a self-retaining retractor.
- A shallow bed for the receiver is drilled in the skull bone behind the ear, checked against the template, and finished with a diamond burr; small tunnels are drilled for the sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry that will hold it.
- A mastoidectomy is done, keeping the bony ear canal, and the facial recess is opened to reach the middle ear.
- The implant is opened (see the warning below).
- The receiver goes into its bed, and the electrode is passed through the facial recess and the round window, or a small opening drilled into the cochlea (a cochleostomy), into the cochlea, and secured, for example with a piece of temporalis fascia.
- The receiver is tied down with sutures (such as 2-0 polypropylene) through the bone tunnels. Bleeding is controlled with the bipolar only.
- The layers are closed and a mastoid dressing applied.
use the monopolar ESU once the implant is in. Its current could pass through the receiver and damage it. Bipolar only.
Opening the implant: static electricity can damage the electrodes. The circulator peels the outer package open slowly over the back table, and the inner sterile package may be put in a basin of saline and opened under the surface. Record the implant's serial and lot numbers.
Wound class: Class I.
After surgery: the implant is switched on and programmed about 2 to 4 weeks later, once the wound has healed, and turned up slowly. Nausea or dizziness may keep a patient overnight. Infection, a hole in the eardrum, facial nerve damage, vertigo and meningitis are the complications.
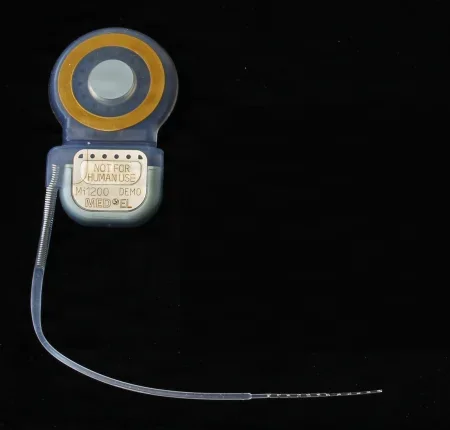
Bone-anchored hearing implant
What and why: a bone-anchored hearing implant (such as the Baha or Ponto systems) sends sound through the skull bone straight to the inner ear, bypassing the ear canal and the middle ear. It suits patients who cannot use an ordinary hearing aid: those with chronic ear infections or drainage, a missing or closed ear canal from birth (canal atresia), a tiny outer ear (microtia), or deafness in one ear. It has three parts: a titanium implant that fuses with the bone (osseointegration), an abutment that comes through the skin, and an electronic sound processor.
Before surgery: an outpatient case under local or general anesthesia, positioned as for other ear cases.
Key steps (one minimally invasive method):
- The implant site is marked about 50 to 55 mm behind the ear canal, level with the top of the ear, and a 20 to 30 mm incision is planned 10 mm in front of it.
- The thickness of the soft tissue is measured with a needle to choose the length of the abutment.
- The incision goes down to the periosteum, which is cut and lifted off the bone at the implant site.
- A 3 to 4 mm hole is drilled in the skull behind the ear and widened at the top with a countersink.
- The titanium implant with its abutment is drilled in at low torque.
- A punch makes a small hole in the skin for the abutment, the incision is closed, and a healing cap goes on.
After surgery: the most common complication is a skin reaction or infection where the abutment comes through; the patient cleans the site routinely. Methods that disturb less skin and soft tissue have lowered the rate of skin problems and speeded healing.
Wound class: Class I, since no tract is entered.
Surgery on the eighth cranial nerve
The Core Curriculum's acoustic neurectomy cuts the balance part of the eighth cranial nerveKRAY-nee-ul NERVOne of the 12 pairs of nerves that come straight from the brain and brainstem rather than the spinal cord.Full entry (a vestibular neurectomy) to stop disabling vertigo, as in Meniere disease. Most often it is chosen to keep the useful hearing in that ear, so the surgeon reaches the nerve without entering the inner ear: through the middle cranialKRAY-nee-ulRelating to the skull, or toward the head end of the body.crani/o skull-al relating toFull entry fossaFOS-uhA shallow hollow or dip in a bone or on the body's surface.Full entry , behind the labyrinth (retrolabyrinthine) or behind the sigmoidSIG-moydShaped like the letter S; most often short for the sigmoid colon, the S-shaped last part of the colon before the rectum.Full entry sinusSY-nusA hollow space in the body, most often one of the air-filled spaces in the skull bones around the nose.Full entry (retrosigmoid). Once that hearing is lost, a labyrinthectomy, which removes the balance organs and leaves no hearing, is usually chosen, most often through the mastoid; the nerve can be cut through the same opening (a translabyrinthine vestibular neurectomy), though this is rarely done.
The route through the labyrinth (translabyrinthine), also used to remove an acoustic neuroma, is set up as a mastoidectomy, with the eye on that side lubricated and closed under a clear dressing: under the microscope the surgeon drills away the semicircular canals to reach the internal auditory canal, with the facial nerve monitor running and a neurectomy knife or scissors and bipolar forceps ready, then packs the cavity with fat, fascia or muscle against a leak of cerebrospinal fluidser-uh-broh-SPY-nul FLOO-idThe clear, watery fluid that bathes and cushions the brain and spinal cord.cerebr/o brainspin spine-al relating toFull entry (CSF). It is Class I. The patient may be very dizzy for days; a CSF leak, bleeding inside the skull and meningitis are the risks. Chapter 42 teaches the middle fossa approach, through a temporal craniotomykray-nee-OT-uh-meeSurgery in which a piece of the skull is removed to reach the brain, and usually put back at the end.crani/o skull-tomy cutting intoFull entry .
8The nose and sinuses
Nasal and sinusSY-nusA hollow space in the body, most often one of the air-filled spaces in the skull bones around the nose.Full entry cases share the position, prep and drape above, topical vasoconstrictor patties placed before the prep, a headlight or endoscopeEN-duh-skohpA thin tube with a light and a camera that is passed into the body to look inside an organ or cavity.endo- within-scope instrument for viewingFull entry , and a basic nasal set. Most are outpatient. Many can be done under local anesthesiaLOH-kul an-es-THEE-zhuhNumbing medicine applied to or injected into one small area, so a procedure there is not felt while the person stays awake.Full entry with sedationsih-DAY-shunA calm, relaxed or sleepy state brought on by drugs, or the use of drugs to cause it.sed calm, settle-ation processFull entry , which means an awake patient: keep noise and talk low, keep the drapes off the face so the patient does not feel closed in, and warn the patient before the vibration of a mallet or chisel.
Rhinoplasty, reshaping the outside of the nose, is taught in chapter 38, and the open repair of facial fractures in chapter 37. Chapter 42 teaches surgery on the pituitary glandpih-TOO-ih-tair-ee glandA gland the size of a pea, hanging below the brain, whose hormones control many other glands.Full entry through the sphenoid sinus (the transsphenoidal approach).
Septoplasty
What and why: a septoplasty (also called a submucous resectionrih-SEK-shunSurgery to remove part of an organ or tissue.re- back, againsect to cut-ion processFull entry , SMR) straightens a deviated septumSEP-tumA wall of tissue that divides two spaces or cavities, such as the two sides of the heart or nose.sept/o wall, partitionFull entry , or repairs one damaged by injury or with a hole in it, so air passes freely through both sides and the sinuses drain. The surgeon works under the lining (submucosal): the lining and its perichondrium are lifted off, the bent cartilageKAR-tih-lijFirm, smooth, rubbery tissue that cushions joints and gives shape to parts such as the ear, nose and windpipe.chondr/o cartilageFull entry or bone is removed, reshaped or put back straight, and the lining is laid back. Care is taken not to make a hole through the septum or weaken it. It is often done with a sinus operation, a turbinate reduction or a rhinoplasty.
Before surgery: general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry , or local anesthesia with sedation (MAC). Supine on a headrest, arms tucked; the skin prep is usually left out; a head drape. The surgeon packs the nose with cottonoids soaked in a vasoconstrictor (such as 4% cocaine, epinephrineep-ih-NEF-rinA hormone and drug, also called adrenaline, that raises heart rate and blood pressure and opens the airways.Full entry 1:1,000 or oxymetazoline) and injects 1% lidocaineLY-doh-kaynA local anesthetic that numbs an area, also given by IV to treat some fast, abnormal heart rhythms.Full entry with epinephrine 1:100,000. Most surgeons wear a headlight.
Setup: a septoplasty set: nasal speculumSPEK-yoo-lumAn instrument used to open and hold open a body opening, such as the vagina, so the inside can be seen.Full entry , a #15 blade on a #7 handle, Freer and Cottle elevators, Cottle and Ballenger knives, Takahashi and Jansen-Middleton forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry , septum-cutting and straightening forceps (such as the Asch), a small chisel or osteotome and mallet, suction with a 10 Fr Frazier tip, bayonet forceps, and splints.

Key steps:
- The patties placed before the prep are removed with the speculum and bayonet forceps, and counted to make sure all are out.
- A cut is made through the lining and perichondrium of the septum with the #15 blade.
- The lining is lifted off the cartilage and bone with the Freer or Cottle elevator, usually the sharp end of the Freer.
- Bent cartilage and bony spurs are trimmed or removed with forceps, a punch, or a chisel or gouge and mallet; the surgeon may ask you to tap the chisel with the mallet. Pieces are pulled out with Takahashi or bayonet forceps, and some cartilage may be reshaped and put back for support.
- Bleeding is controlled with patties soaked in a hemostatichee-moh-STAT-ikStopping bleeding; also, a product or agent used to stop bleeding.hem/o blood-stasis stopping, standing still-ic relating toFull entry or with the electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry .
- The cut is closed with fine absorbable sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry (such as 4-0), and soft plastic or silicone splints may be sutured inside each side of the nose to prevent scar bands (adhesionad-HEE-zhunA band of scar tissue that joins two surfaces inside the body that are normally separate.ad- towardhes stick-ion conditionFull entry ) and a blood clot in the septum (septal hematomahee-muh-TOH-muhA collection of blood, often clotted, that has leaked out of the blood vessels into the tissue.hem/o blood (here as hemat-)-oma swelling or massFull entry ).
- Packing or a mustache dressing, and sometimes an outside splint and an ice pack, go on. The throat is suctioningSUK-shun-ingRemoving mucus, saliva or other secretions from the mouth, nose or airway with a tube connected to a suction source.Full entry so no blood is breathed in.
Wound class: Class II, clean-contaminated, because the respiratory tract is entered.
After surgery: bruising and swelling around the nose and eyes are expected, packing means breathing through the mouth, and the packing comes out in the office 1 to 3 days later. The patient sniffs gently instead of blowing the nose, sneezes with the mouth open, and expects some blood in the nose and throat for the first hours. Bleeding and infection are the complications.
Turbinectomy and turbinate reduction
What and why: a chronically swollen inferior turbinate, or a middle turbinate malformed from birth (concha bullosa), blocks airflow. A turbinectomy removes part of the turbinate bone; a turbinate reduction shrinks it while trying to keep its lining working. It is often done with a septoplasty or sinus surgery, and its preparation, setup and aftercare are the same as a septoplasty's.
Methods:
- Submucosal resection: the lining at the front of the turbinate is cut with a #15 blade and lifted off the bone with a Freer or Cottle elevator; part of the bone is removed with forceps, and the lining may be closed with 3-0 chromic suture.
- Infracture and trimming: an elevator under the turbinate lifts it and fractures it toward the midlineMID-lineAn imaginary line down the center of the body; also, a type of IV catheter placed in a vein of the upper arm.Full entry (infracture), angled scissors and a rongeurron-ZHURA strong surgical instrument with sharp, cup-shaped jaws used to bite away small pieces of bone.Full entry cut away bone and soft tissue, and insulated electrocautery and packing stop the bleeding.
- Energy: a sharp two-prong bipolarby-POH-lerHaving two poles or two opposite ends; most often used as a short form of bipolar disorder.bi- twopolar having polesFull entry electrode, coblation (radiofrequency) or a laser shrinks the tissue from inside; a microdebrider can remove it through a small cut.
Wound class: Class II, as for a septoplasty.
After surgery: bleeding is the main complication, with dryness and crusting, infection and adhesions.
Closed reduction of a nasal fracture
What and why: the nose sits in the middle of the face and breaks easily; a blow from the front usually breaks and flattens both nasal bones and pushes the septal cartilage out of place. A closed reduction puts the bones back by hand and with an elevator, without cutting the skin. Occasionally an open reduction, wiring the bone fragments, is needed. A computed tomographykum-PYOO-tid toh-MOG-ruh-feeAn imaging test that uses x-rays and a computer to make cross-section pictures of the inside of the body.tom/o cut, slice-graphy process of recordingFull entry may be done to check the sinuses around it.

Key steps:
- The nose is packed with cottonoids soaked in 4% cocaine, and local anestheticLOH-kul an-es-THET-ikA drug that blocks feeling in one part of the body without making the person unconscious.Full entry is injected. A simple fracture can be done under topical or local anesthesia; an anxious patient may need general anesthesia.
- A Boies elevator is slid inside the nostril, under the pushed-in bone, while the surgeon's other hand molds the nose from outside. The surgeon may first lay the elevator along the outside of the nose to mark how deep it goes.
- Packing or an outside splint (such as a Denver splint) holds the bones in place.
After surgery: the care after other nasal cases applies: bruising and swelling are expected, the patient sniffs gently instead of blowing the nose, and sneezes with the mouth open.
Wound class: no incision is made, but the instruments work inside the nose, part of the respiratory tract, so by the CDC's definitions it fits Class II, clean-contaminated, like other cases done through the nose. No reference gives its class, so follow your facility's policy.
Nasal valve reconstruction
What and why: airflow through the nose is controlled by two narrow places, the nasal valves. The internal valve is where the septum meets the upper lateral cartilages; the angle between them should be at least 10 to 15 degrees to keep the nose open. The external valve is formed by the lower lateral cartilages of the nostril, and when it is weak, the nostril can collapse even on a gentle breath in, often after an earlier rhinoplasty. In the Cottle test, the examiner pulls the cheek outward with a finger; if breathing improves sharply, the internal valve needs repair.
Key steps: the internal valve is widened with spreader graftGRAFTTissue or a man-made material moved into place in surgery to replace or repair a damaged part.Full entry , pieces of cartilage placed between the septum and the upper lateral cartilages, or with flaring sutures; a piece of cartilage cut from the septum can serve as the graft. A collapsing external valve is braced with alar batten grafts of septal or ear cartilage sewn to the lower lateral cartilages. The repair is part of a septoplasty or a rhinoplasty (chapter 38), and is set up, positioned and cared for afterward as they are, so keep any cartilage removed earlier in the case: it may become the graft.
Wound class: Class II, as for a rhinoplasty, since the nose is entered.
Choanal atresia repair
What and why: the choanae are the two openings at the back of the nasal cavity into the nasopharynxnay-zoh-FAIR-inksThe top part of the throat, behind the nose and above the soft palate.nas/o nosepharyng/o throatFull entry . Choanal atresia is a bony or membranous plate that blocks one or both choanae from birth, because the tissue between the nose and the throat failed to break open before birth. Newborns breathe through the nose, so a baby with both sides blocked struggles to breathe and needs surgery as an emergency. It is suspected when an 8 Fr catheter cannot be passed through the nose into the throat, or a mirror under the nostrils does not fog, and CT confirms it.
Before surgery and setup: the child is prepared as for a septoplasty, with septoplasty instruments, a small (pediatric) sinus scope such as a 4 mm 30-degree scope, a microdebrider and a drill with burrs, small rongeurs, and stentstentA small tube, often of metal mesh, placed inside a vessel or duct to hold it open.Full entry .
Key steps: in the endoscopicen-doh-SKOP-ikDone with an endoscope, a thin tube with a light and camera passed into the body.endo- within-scopic viewingFull entry repair, the surgeon views the blockage through the scope and removes it with the microdebrider or burrs; in the transseptal repair, a cut in the septum reaches the blockage under the microscope. A stent may be placed to keep the new opening open while it heals. Simply punching through is rarely done, because it fails often.
Wound class: Class II.
After surgery: the child usually goes home the same day if breathing is normal, and the parents watch closely for any trouble breathing. Infection, bleeding, a return of the blockage, a hole in the palate and a disturbance of facial growth are the complications. Care of the child in the OR is in chapters 13 and 18.
Endoscopic sinus surgery (FESS)
What and why: functional endoscopic sinus surgery (FESS) treats chronic sinusitissy-nuh-SY-tisInflammation of the lining of the sinuses, the air spaces around the nose.sinus sinus-itis inflammationFull entry , polypPOL-ipA growth that sticks out from the lining of a hollow organ, such as the colon, nose or uterus.Full entry and other sinus disease that medicine has not cured. Through the nostrils, with an endoscope and a monitor, the surgeon removes the diseased tissue and the small bones that block the sinuses' natural openings, so the sinuses drain and fill with air again, while keeping the normal lining and its function. It has replaced most of the old open sinus operations. Because the sinuses border the eye socket and the brain, it is demanding surgery.
Before surgery: general anesthesia or MAC. Position, prep and drape as for other nasal cases. The CT scans are in the room and on the navigation system. The video tower and monitors go at the head of the table; the surgeon stands on the patient's right, the scrub at the surgeon's right and an assistant across the table.
Setup: a basic nasal set, sinus endoscopes of 4 or 5 mm at 0, 30 and 70 degrees (90 and 120 degrees on some sets), the camera, light source and light cord, antifog, endoscopic forceps (straight and angled Blakesley, backbiting and cutting forceps, biopsy forceps), suction tips and suction elevators, the microdebrider, a suction-irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry system, and the navigation system. The topical and local anesthetics are set up on a separate small table.
Key steps:
- The topical anesthetican-us-THET-ikA drug that causes loss of feeling, with or without loss of consciousness.an- withoutesthesi/o feeling, sensation-ic relating toFull entry is placed and the local injected; the 0-degree scope, wiped with antifog, goes in.
- The middle turbinate is gently pushed toward the midline to show the middle meatusmee-AY-tusAn opening or passage in the body, such as the urinary opening or the ear canal.Full entry , and a small curved plate of bone there, the uncinate process, is removed.
- The natural opening of the maxillary sinus is enlarged (a maxillary antrostomy) with a probe, a backbiting forceps or the microdebrider, and polyps and diseased lining are removed.
- The ethmoid cells are opened one by one (an ethmoidectomy), turning the honeycomb into one large cavity that drains. This can be a long, slow step in a darkened room: stay alert.
- If the CT shows disease there, the sphenoid sinus is opened (a sphenoidotomy) with the 30-degree scope, and the frontalFRUN-tulRelating to the front of the body, or to the forehead and the bone or brain area behind it.Full entry recess with the 70-degree scope.
- No skin incision is made, so no sutures are needed. Bleeding is controlled through the scope and with patties soaked in a vasoconstrictor; absorbable gelatin film or packing, a dissolving steroidSTAIR-oydA fat-based chemical built from cholesterol; the group includes hormones such as cortisol and estrogen, and many drugs.ster/o solid-oid likeFull entry -releasing implant, or nonabsorbable packing with antibiotic ointment may be left in the middle meatus, and a mustache dressing goes on.
Change lenses carefully when the surgeon moves to a new sinus, and wipe on antifog every time the scope comes out and goes back in. Pass instruments closed and never over the patient's face, so the surgeon's eyes never leave the monitor.
The eyes stay uncovered and in view the whole case, because the orbit is just beyond the thin walls of the ethmoid sinus. Put each piece of tissue the surgeon removes in a small labeled cup of saline. If a piece floats, it may be orbital fat: tell the surgeon at once. Yellow fat on the monitor, or a bulging or moving eyeball, also means the orbit has been entered.
Navigation (image-guided sinus surgery): chapter 21 teaches how navigation works. In sinus and skull base surgery it shows the tip of the surgeon's instrument on the patient's own CT scan. It is most useful in revision surgery, when earlier operations or long infection have destroyed the usual landmarks, and many surgeons will not do a revision without it. The CSTsee-es-tee (said as letters)Certified Surgical Technologist, a credential for surgical technologists; in maternity care, contraction stress test.Full entry may set up the system, load the CT scan into it and test it. Once it is registered, nothing may bump the reference frame on the head. Even then the screen is not exact: one reference gives a difference of about 0.9 to 2.4 mm at the skull base between where the tip is shown and where it truly is.
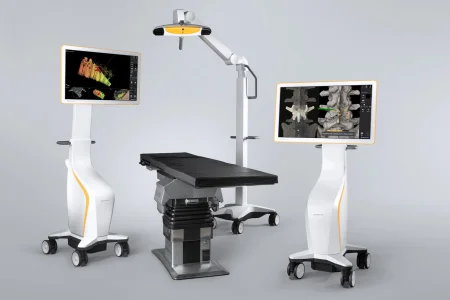
Wound class: Class II, since the respiratory tract is entered.
After surgery: the patient sniffs gently instead of blowing the nose, sneezes with the mouth open, avoids straws, expects blood-tinged drainage for the first hours and nausea or dark stools from swallowed blood, and uses a humidifier. The serious complications are injury to the eye socket (a blood clot in the orbit) and to the skull base, with a leak of cerebrospinal fluidser-uh-broh-SPY-nul FLOO-idThe clear, watery fluid that bathes and cushions the brain and spinal cord.cerebr/o brainspin spine-al relating toFull entry , which shows as clear fluid running from the nose.
Balloon sinuplasty
What and why: an alternative to FESS for a blocked sinus opening. Through the nostril, the surgeon passes a guide wire and a catheter carrying a tiny balloon into the blocked opening, gently inflates the balloon to widen it, flushes the sinus with saline and withdraws the device, leaving the sinus open to drain. The Core Curriculum lists the balloon sinuplasty kit among the ENT supplies.
Nasal polypectomy
What and why: removes nasal polyps that block the nose and the sinus openings, usually through the endoscope and often with sinus surgery. Polyps often come back, inverting papillomas especially, so many patients need repeat operations.
Before surgery and setup: prepared as for a septoplasty, with the endoscopic nasal setup, polyp forceps, Wilde forceps, a polyp snare and the microdebrider. Load the snare's wire when you set up. Aftercare is as for a septoplasty.
Key steps: the microdebrider cuts the polyps into small pieces and suctions them away while controlling bleeding, which is much faster than pulling each piece out by hand; a #12 Frazier suction removes the cut-up tissue. A snare can also loop its wire around a polyp and cut it off as the surgeon pulls it forward with polyp forceps. The polyps are specimens. Packing is usually not needed.
Wound class: Class II, since the respiratory tract is entered.
Radical antrostomy (Caldwell-Luc)
What and why: the Caldwell-Luc operation opens the maxillary sinus through the mouth, in the groove between the upper lip and the gum (the gingivobuccal sulcus), to drain an abscessAB-sesA closed pocket of pus in tissue, walled off by the body.Full entry , remove diseased tissue, cysts or tumors under direct view, make a large opening for drainage into the nose below the inferior turbinate, or reach the maxillary artery in a severe nosebleed. Endoscopic surgery has largely replaced it.
Open sinus operations such as the Caldwell-Luc, an external ethmoidectomy and obliteration of the frontal sinus were once the usual treatment for sinus disease; most references now teach endoscopic surgery first.
Before surgery and setup: general anesthesia (local anesthesia can also be used), with lidocaine and epinephrine injected, and the position, prep and drape of other nasal cases; the CT scans are in the room. It is not done in a child whose permanent teeth have not yet come down. Set up a submucous resection (nasal) set with a Caldwell-Luc retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry , periosteal elevators, the drill or a small osteotome, Kerrison rongeurs, Takahashi and Wilde forceps, small bone curettekyoo-RETA surgical instrument with a small spoon- or loop-shaped tip used to scrape tissue.Full entry , an antrum trocarTROH-karA sharp or bladed instrument inside a tube (cannula), used to pierce a body wall and leave the tube in place as a port.Full entry or rasp for the window into the nose, and 3-0 absorbable suture.
Key steps:
- The upper lip is lifted with a gauze sponge or retractor, and the gum line is cut with the ESU or a #15 blade from about the lateral incisor to the second molar, down to the periosteum.
- The periosteum is lifted off the canine fossaFOS-uhA shallow hollow or dip in a bone or on the body's surface.Full entry up to the infraorbital nerve, which is found and protected.
- The front wall of the sinus is opened with the drill or a small osteotome and widened with Kerrison rongeurs.
- Cysts, polyps and diseased tissue are removed with cutting forceps and curettes, and the sinus is irrigated.
- A window may be made into the nose below the inferior turbinate for drainage, the sinus may be packed, and the gum is closed with 3-0 absorbable suture.
Wound class: Class II, since the mouth and sinus are entered.
After surgery: ice packs and a soft diet; bleeding and infection are the complications.
Treating a nosebleed
A slow nosebleed is treated first with direct pressure and an oxymetazoline spray; one that keeps going is sealed with a silver nitrateNY-traytA drug, such as nitroglycerin, that relaxes and widens blood vessels.Full entry stick or packed, with gelatin sponge packing, a nasal tampon or a balloon pack. When packing fails, the bleeding is sealed through the endoscope or an artery is tied off, such as the sphenopalatine artery.
9Endoscopy of the airway and food passage
These cases look inside the larynxLAIR-inksThe voice box: the part of the airway in the neck, above the windpipe, that holds the vocal cords.laryng/o larynxFull entry , the tracheaTRAY-kee-uhThe windpipe: the tube that carries air from the throat to the lungs.Full entry and bronchusBRONG-kusOne of the large air tubes that branch from the windpipe into each lung.bronch/o airwayFull entry , and the esophagusih-SOF-uh-gusThe muscular tube that carries food and liquid from the throat to the stomach.esophag/o esophagusFull entry through rigid or flexible scopes passed through the mouth, to find disease, take biopsies and treat it. No incision is made, but the scopes enter the airway or the food passage through the body's own openings, so by the CDC's definitions they fit Class II, clean-contaminated, as other endoscopyen-DOS-kuh-peeA procedure that uses a thin, flexible tube with a light and camera to look inside the body.endo- within-scopy looking with an instrumentFull entry of a tract does. bronchoscopybrong-KOS-kuh-peeA procedure in which a thin, lighted tube with a camera is passed through the nose or mouth to look inside the airways.bronch/o airway (bronchus)-scopy looking with an instrumentFull entry is always done with sterile instruments.
Laryngoscopy and microlaryngoscopy
What and why: a laryngoscopy is a direct look at the larynx. In the office, the surgeon may use a mirror held against the uvula (indirect laryngoscopy), asking the patient to speak (phonation) to watch the cords move, or a flexible scope through the nose. In the OR, a rigid lighted laryngoscope passed through the mouth shows the larynx so the surgeon can take a biopsy, remove secretionsih-KREE-shunA substance a gland or cell makes and releases, such as mucus, saliva, sweat or a hormone.Full entry or a foreign body, or treat a lesionLEE-zhunAn area of tissue that has been damaged or has changed from normal, such as a sore, wound, lump or spot.Full entry : cancer, polypPOL-ipA growth that sticks out from the lining of a hollow organ, such as the colon, nose or uterus.Full entry and noduleNOD-yoolA small, firm, rounded lump of tissue that can be felt or seen, in or under the skin or in an organ.Full entry , papillomas, leukoplakia or a web.

Before surgery: general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry in most cases; topical lidocaineLY-doh-kaynA local anesthetic that numbs an area, also given by IV to treat some fast, abnormal heart rhythms.Full entry , tetracaine, cocaine or benzocaine and tetracaine for a patient who cannot have it. Note any loose teeth, dentures and dental work, and any stiffness of the neck. The patient is supine, with a shoulder roll if the neck needs to extend a little, the head on a doughnut headrest, and the table may be tilted head up. The eyes are protected, and the draping is small: a head drape and a sheet.
Setup: laryngoscopes with light carriers, telescopes, long suction tips (open or velvet tipped), cup biopsy forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry , sponge carriers, a tooth guard, specimen cups, and the local anestheticLOH-kul an-es-THET-ikA drug that blocks feeling in one part of the body without making the person unconscious.Full entry setup. For a suspension laryngoscopy, the laryngoscope is held by a self-retaining holder, resting on a platform on the bed or on a Mayo standMAY-oh standA small tray on an adjustable stand placed over or beside the patient during surgery to hold the instruments used most often.Full entry over the chest, so the surgeon has both hands free; add microlaryngeal instruments (22 cm long) and the microscope with a 400 mm lens.

Key steps:
- A tooth guard is placed to protect the teeth.
- The surgeon passes the laryngoscope in at the right side of the mouth, lifts the tongue to show the epiglottisep-ih-GLOT-isA leaf-shaped flap of cartilage at the back of the throat that covers the windpipe during swallowing.epi- upon, overglott/o the opening of the larynxFull entry , and advances the scope to the larynx and the vocal cords, looking below them and at the top of the trachea too.
- Secretions are suctioningSUK-shun-ingRemoving mucus, saliva or other secretions from the mouth, nose or airway with a tube connected to a suction source.Full entry . Guide each instrument into the laryngoscope and advance it a short way, so the surgeon, watching through the scope or microscope, does not have to look away.
- Suspicious tissue is biopsied with cup forceps. Keep every specimen separate, labeled by its exact site and side, and collect every bit of tissue from the forceps tips.
- Bleeding is controlled with flat pledgets soaked in a vasoconstrictor, such as epinephrineep-ih-NEF-rinA hormone and drug, also called adrenaline, that raises heart rate and blood pressure and opens the airways.Full entry , oxymetazoline or cocaine, and the scope is withdrawn.
Microlaryngoscopy adds the operating microscope, to remove polyps or nodules from the vocal cords (phonosurgery). The patient will be on complete voice rest afterward, so set up a pencil and paper or a writing board before the case.
Laser surgery of the larynx: the carbon dioxideKAR-bun dy-OK-sideA gas made by the body's cells as waste, carried in the blood to the lungs and breathed out.Full entry laser, fitted to the microscope through a micromanipulator, removes webs, papillomas and carcinomakar-sih-NOH-muhA cancer that starts in the cells that line the skin or the inside and outside surfaces of organs.carcin/o cancer-oma tumorFull entry in situ (cancer still confined to the lining) with little damage around them. All instruments are ebonized (dark and nonreflective), the laser beam is tested before use, a smoke evacuator runs, the team wears fit-tested N95en-NINE-tee-fiveA close-fitting respirator mask that filters at least 95% of tiny particles from the air the wearer breathes.Full entry respiratorRES-pih-ray-terA close-fitting mask or hood that filters the air a person breathes to protect them from germs or harmful particles.Full entry , and the laser airway steps above apply. The microscope's drape for laser work has an opening at the micromanipulator so the beam cannot burnBURNAn injury to the skin or deeper tissues caused by heat, chemicals, electricity, radiation or friction.Full entry it.

Keep the laryngoscopy setup in the room, ready, until the patient has left for PACU. If laryngospasmluh-RING-goh-spaz-umA sudden, involuntary closing of the vocal cords that partly or fully blocks air from entering the lungs.laryng/o larynx (voice box)-spasm sudden involuntary tighteningFull entry closes the airway as the patient wakes, the anesthesia provideran-us-THEE-zhuh pruh-VY-derThe licensed professional who gives anesthesia and watches over the client's breathing and vital functions during a procedure.Full entry may need to endotracheal intubationen-doh-TRAY-kee-ul in-too-BAY-shunPutting a breathing tube through the mouth or nose into the windpipe (trachea).endo- withintrache/o windpipe-al relating toFull entry again at once.
After surgery: nothing to eat or drink until the gag reflexREE-fleksAn automatic body response to something that stimulates it, which happens without thought, such as the knee jerk.Full entry is back and swallowing is easy. The patient is watched for swelling of the airway, with the head of the bed raised.
Bronchoscopy
What and why: a bronchoscopy looks into the trachea and bronchi to find tumors and other disease, take biopsies, brushings and washings, and treat: removing a foreign body, opening a narrowing, cutting away a tumor with a laser or cryotherapy, or placing an airway stentstentA small tube, often of metal mesh, placed inside a vessel or duct to hold it open.Full entry . In ENT it may be done in one session with a laryngoscopy and an esophagoscopy (panendoscopy, below). A rigid bronchoscope, used under general anesthesia, carries the anesthesiaan-us-THEE-zhuhLoss of feeling or sensation, often brought on by drugs so that surgery or a procedure can be done without pain.an- withoutesthesi/o feeling, sensation-ia conditionFull entry circuit and large instruments, so it is used for foreign bodies, laser work and other large-bore jobs. A flexible scope, passed through the mouth or nose after the throat is numbed and the patient sedationsih-DAY-shunA calm, relaxed or sleepy state brought on by drugs, or the use of drugs to cause it.sed calm, settle-ation processFull entry , with a bite block to protect it, reaches the smaller bronchi. Both are often used in one case.
Setup: rigid scopes in several sizes with their telescopes, light carriers and airway adapter; flexible scopes; suction; grasping forceps, baskets, biopsy forceps and brushes; a laser fiber if needed; a tooth guard; and a Lukens trap, a small container in the suction line that collects washings (the Core Curriculum's sputumSPYOO-tumMucus and other material coughed up from the lungs and lower airways.Full entry collection container). Set the rigid and flexible instruments on separate tables so the team can switch quickly.


Key steps (rigid):
- Supine with the neck slightly extended, a tooth guard in, the eyes covered and a body drape; an eyepiece adapter shields the surgeon from the patient's fluids.
- The surgeon passes the scope into the trachea; guide instruments into its side channels when asked.
- For washings, saline goes in through the side channel and is suctioned back into the Lukens trap: keep the trap upright, or the specimen is lost.
- Lift biopsy tissue off the cup forceps gently onto a moist Telfa pad; a foreign body comes out in a basket or grasping forceps. The airway is suctioned clear and the scope withdrawn.
With a flexible scope, a hypodermic needle helps lift tissue off the biopsy forceps, and a brush is wiped on a slide that goes straight into fixative. A laser fiber must stick out at least 1 cm beyond the end of the scope and be in view before the laser fires (one reference asks for more than an inch).
After surgery: the most important complication of rigid bronchoscopy is injury to the trachea or bronchi if the patient moves, as when the gag reflex makes the patient cough and arch.
Esophagoscopy and panendoscopy
An esophagoscopy looks into the esophagus to find cancer and its spread, take biopsies, remove a swallowed object, or stretch a narrowing with a bougie (the esophageal dilatorDY-lay-terAn instrument used to stretch or widen an opening, canal or passage in the body.Full entry on the Core Curriculum's ENT supply list). Chapter 32 teaches it, with its rigid setup. In ENT the rigid scope is passed at the right side of the tongue with the head turned slightly to the left, and after a biopsy the area is checked for bleeding before the scope comes out.
When a laryngoscopy, a bronchoscopy and an esophagoscopy are done in one session, it is called triple endoscopy or panendoscopy. It is usually done to look for cancer and to stage it before a partial or total laryngectomy, so have every scope set up and working, and keep the specimens from each site apart.
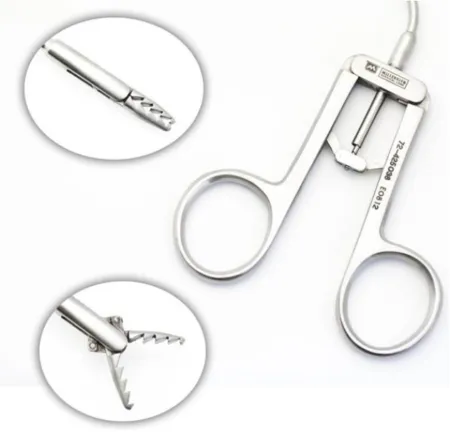
10The throat
Tonsillectomy and adenoidectomy
What and why: a tonsillectomy removes the palatine tonsilTON-sulOne of the masses of lymph tissue at the back of the throat that help fight germs entering the mouth and nose.Full entry ; an adenoidectomy removes the adenoids from the nasopharynxnay-zoh-FAIR-inksThe top part of the throat, behind the nose and above the soft palate.nas/o nosepharyng/o throatFull entry , and the two are often done together (a T&A). Enlarged tonsils and adenoids are the most common risk factor for obstructive sleep apneaub-STRUK-tiv SLEEP AP-nee-uhA sleep disorder in which the upper airway closes again and again during sleep, stopping or reducing breathing.a- without-pnea breathingFull entry in children, and removing them is the first treatment for it. Other reasons are infections that keep coming back (current guidelines count seven or more in the past year, five or more in each of the past 2 years, or three or more in each of the past 3 years), chronic tonsillitiston-sih-LY-tisInflammation of the tonsils, the two lumps of lymph tissue at the back of the throat.tonsill/o tonsil-itis inflammationFull entry , a peritonsillar abscessAB-sesA closed pocket of pus in tissue, walled off by the body.Full entry , trouble swallowing, and a marked difference in size between the two tonsils, which can, rarely, be a lymphomalim-FOH-muhA cancer of lymphocytes, the white blood cells of the lymph system.lymph/o lymph-oma tumorFull entry . Enlarged adenoids cause mouth breathing, a blocked nose and a "closed" (hyponasal) voice, and can block the eustachian tubes and cause ear infections, so an adenoidectomy is often done with ear tubes.
Methods: the oldest way is the cold knife and snare, with the electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry , sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry or packing for bleeding. Many surgeons now use energy that cuts and seals at once, so less blood is lost: the ESU, ultrasonic (harmonic) shears, whose blade vibrates about 55,000 times a second, or a bipolarby-POH-lerHaving two poles or two opposite ends; most often used as a short form of bipolar disorder.bi- twopolar having polesFull entry radiofrequency (coblation) wand with suction built in. The adenoids may be removed with a curettekyoo-RETA surgical instrument with a small spoon- or loop-shaped tip used to scrape tissue.Full entry , the suction coagulator, a radiofrequency wand or the microdebrider.
Before surgery: general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry with a breathing tube; the anesthesia provideran-us-THEE-zhuh pruh-VY-derThe licensed professional who gives anesthesia and watches over the client's breathing and vital functions during a procedure.Full entry uses a tube with a preformed bend (such as a RAE tube) so the surgeon can see the throat. Supine on a doughnut headrest, the neck extended with a shoulder roll or by lowering the head of the table, arms tucked, and the table turned 90 degrees. The face is not prepped; a head drape and a body sheet.
Setup: a tonsil and adenoid set: a mouth gag (Crowe-Davis, McIvor or Davis) with tongue blades in several sizes, tonsil forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry or a tenaculum, a curved tonsil knife and a Hurd dissector and pillar retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry , Metzenbaum scissors, a snare with wires, tonsil hemostatHEE-moe-statA clamp with finger rings and a locking ratchet used in surgery to grasp and close off bleeding vessels.hem/o blood-stat stopping, standing stillFull entry (such as the Schnidt), tonsil sponges, adenoid curettes, a dental mirror with antifog, a 12 or 14 Fr red rubber (Robinson) catheter, suction, the suction coagulator and the energy device.
Key steps (tonsillectomy):
- The surgeon places the mouth gag, keeping the tongue in the middle and the breathing tube protected under the tongue blade, and hooks the gag to the edge of the Mayo standMAY-oh standA small tray on an adjustable stand placed over or beside the patient during surgery to hold the instruments used most often.Full entry . From now on, do not move or bump the Mayo, and have suction in hand the whole case.
- The back and side walls of the throat are checked and felt for an unusually placed artery.
- A red rubber catheter is passed through the nose and out of the mouth and clamped, pulling the soft palateSOFT PAL-itThe soft, muscular back part of the roof of the mouth, with no bone in it.Full entry forward, and a moist throat pack goes in the back of the throat.
- The tonsil is grasped and pulled toward the midlineMID-lineAn imaginary line down the center of the body; also, a type of IV catheter placed in a vein of the upper arm.Full entry , and the surgeon cuts along its edge with the tonsil knife, the ESU or the energy device, then frees it from its bed (the tonsillar fossaFOS-uhA shallow hollow or dip in a bone or on the body's surface.Full entry ) from top to bottom, with the pillar retractor if needed.
- The last attachmentuh-TACH-mentThe deep emotional bond between an infant and a parent or caregiver.Full entry is cut, or a snare is closed around it. The tonsils are separate specimens, labeled right and left.
- Bleeding is stopped with the energy device, the suction coagulator, or clamps and 3-0 absorbable ties or stitches, and tonsil sponges are pressed into the fossa. Suction the smoke as the surgeon works.
- The gag is released for a short time and opened again, so the surgeon can see any bleeding from vessels it was pressing; the throat is irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry with 50 to 60 mL of saline while the tube's cuff is up, so fluid cannot run into the lungs.
- The catheter and the throat pack come out, and the gag is removed with care so the breathing tube is not pulled out. The teeth, jaw joint and lips are checked for injury.
Key steps (adenoidectomy): the soft palate is pulled forward with a red rubber catheter, and the surgeon looks at the adenoids with a dental mirror dipped in antifog. They are removed with an adenoid curette sized to the nasopharynx, or treated with the suction coagulator; the area is irrigated, checked with the mirror for bleeding and any adenoid left behind, and the gag is released.

Counts: every sponge, the tonsil sponges included, is counted by routine policy. The throat pack is counted and announced, and its removal is confirmed before the breathing tube comes out; facility policy decides how it is recorded.
Wound class: Class II; the CDC lists operations on the oropharynxor-oh-FAIR-inksThe middle part of the throat, behind the mouth, from the soft palate down to the top of the voice box.or/o mouthpharyng/o throatFull entry as clean-contaminated.
After surgery: as the patient wakes, blood and secretionsih-KREE-shunA substance a gland or cell makes and releases, such as mucus, saliva, sweat or a hormone.Full entry in the throat can set off gagging and bucking, which can turn into an airway emergency within moments. Keep every instrument, the suction, the ESU and the mouth gag sterile and ready until the patient has been extubated and taken to PACU, where help is close by if bleeding starts. Bleeding is the main concern after a tonsillectomy. Swallowed blood can cause nausea and dark stools, and a soft, bland diet follows. Pain control is planned before the patient goes home, with non-opioid analgesicOH-pee-oyd an-ul-JEE-zikA strong drug that relieves moderate to severe pain by acting on the brain and spinal cord.Full entry medicines where they work, because an outpatient has fewer chances to have the plan adjusted.
Uvulopalatopharyngoplasty (UPPP)
What and why: a UPPP removes extra tissue of the uvula and the soft palate and tightens the tissue of the oropharynx to treat obstructive sleep apnea and loud snoring. It does not replace a CPAPSEE-papContinuous positive airway pressure: a steady flow of pressurized air through a mask that keeps the airway open.Full entry (continuous positive airway pressure) machine, but may be chosen when CPAP has failed. It is considered when the patient has two or more of these: oxygen falling below 80 percent in sleep, more than 20 episodes of stopped or shallow breathing an hour, heavy daytime sleepiness, snoring loud enough to cause social or relationship problems, and heart rhythm problems in sleep (other than a fast or slow heartbeat). The tonsils come out too if they are still there.
Before surgery: some of these patients have obesity and are hard to endotracheal intubationen-doh-TRAY-kee-ul in-too-BAY-shunPutting a breathing tube through the mouth or nose into the windpipe (trachea).endo- withintrache/o windpipe-al relating toFull entry , so the anesthesia provider chooses the safest way to place the tube, such as a fiberoptic scope or a video laryngoscope. Have emergency tracheotomytray-kee-OT-uh-meeThe surgical cut made into the windpipe through the front of the neck.trache/o windpipe-tomy cutting, incisionFull entry and bronchoscopybrong-KOS-kuh-peeA procedure in which a thin, lighted tube with a camera is passed through the nose or mouth to look inside the airways.bronch/o airway (bronchus)-scopy looking with an instrumentFull entry supplies in the room, and a range of tracheostomytray-kee-OS-tuh-meeA surgical opening through the front of the neck into the windpipe, usually holding a tube that the person breathes through.trache/o windpipe-stomy surgical openingFull entry tubes, extra-long ones included; some patients have a tracheostomy at the same time, kept until the swelling has passed. Positioned as for a tonsillectomy, with a shoulder roll; no skin prep.
Key steps:
- A McIvor gag is placed, and the tonsils are removed if present.
- The tissue to be removed is outlined with the ESU; the uvula may be grasped with an Allis clamp.
- The extra soft palate and uvula are cut away with the ESU or a #15 or #12 blade, in front of the tonsillar pillars (or behind them if the tonsils are already out); vessels are clamped or sealed with the suction coagulator.
- The edges of the lining are sewn together with 2-0 or 3-0 absorbable suture on long needle holders, the throat is irrigated and checked, and the gag is released. The tonsils and the uvula are separate specimens.
Wound class: Class II, as for the oropharynx.
After surgery: some patients stay overnight to watch the airway, which can swell and block. Keep the instruments ready until the patient reaches PACU, in case of bleeding. The patient avoids straws, rinses the mouth gently several times a day, and the incision is not pushed on with a tongue blade.
11The airway
Tracheotomy and tracheostomy
What and why: a tracheotomytray-kee-OT-uh-meeThe surgical cut made into the windpipe through the front of the neck.trache/o windpipe-tomy cutting, incisionFull entry is an opening into the front of the tracheaTRAY-kee-uhThe windpipe: the tube that carries air from the throat to the lungs.Full entry , usually temporary, for a tube; a tracheostomytray-kee-OS-tuh-meeA surgical opening through the front of the neck into the windpipe, usually holding a tube that the person breathes through.trache/o windpipe-stomy surgical openingFull entry , strictly, is a permanent opening, a stomaSTOH-muhAn opening on the surface of the body made by surgery, such as the end of bowel brought out through the belly wall.stoma mouth, openingFull entry whose lining is sewn to the skin. The two words are often used for the same thing. It is done for a patient who needs a mechanical ventilationmeh-KAN-ih-kul ven-tuh-LAY-shunBreathing support from a machine, a ventilator, that pushes air into the lungs through a tube or a mask.Full entry for a long time (long endotracheal intubationen-doh-TRAY-kee-ul in-too-BAY-shunPutting a breathing tube through the mouth or nose into the windpipe (trachea).endo- withintrache/o windpipe-al relating toFull entry can scar the larynxLAIR-inksThe voice box: the part of the airway in the neck, above the windpipe, that holds the vocal cords.laryng/o larynxFull entry into subglottic stenosisstuh-NOH-sisNarrowing of a passage or opening in the body, such as a blood vessel, heart valve or the spinal canal.sten/o narrow-osis conditionFull entry ), for an upper airway blocked by a tumor, swelling, an injury, a foreign body, sleep apneasleep AP-nee-uhA sleep disorder in which breathing stops and starts again and again during sleep.Full entry or paralysispuh-RAL-uh-sisLoss of the ability to move a part of the body, and sometimes loss of feeling in it.para- beside, abnormal-lysis looseningFull entry of both vocal cords (signs include stridorSTRY-derA high-pitched, harsh sound made while breathing, usually heard when breathing in.Full entry , a harsh, high-pitched sound as the patient breathes in), for a patient who cannot clear secretionsih-KREE-shunA substance a gland or cell makes and releases, such as mucus, saliva, sweat or a hormone.Full entry , and to protect the airway before or after big head and neck surgery when heavy swelling is expected. It may be done in the OR, the ICU or the emergency department.
Before surgery: general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry when possible, local in an emergency. Supine, a shoulder roll to extend the neck, the head on a doughnut headrest, arms tucked. The surgeon marks a midlineMID-lineAn imaginary line down the center of the body; also, a type of IV catheter placed in a vein of the upper arm.Full entry site between the sternal notch and the cricoid. The prep runs from the chin to the nipple line and well out to the sides. Open a sterile suction catheterSUK-shun KATH-uh-terA thin, flexible tube attached to suction, used to remove mucus and other secretions from the airway.Full entry .
Setup: a tracheotomy set: a #15 (and #10 or #11) blade, skin hooks, small retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry such as Army-Navy or a blunt Weitlaner, hemostatHEE-moe-statA clamp with finger rings and a locking ratchet used in surgery to grasp and close off bleeding vessels.hem/o blood-stat stopping, standing stillFull entry , the electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry , a tracheal hook, a tracheal dilatorDY-lay-terAn instrument used to stretch or widen an opening, canal or passage in the body.Full entry , the tracheostomy tube of the size ordered, with its obturatorOB-too-ray-terA smooth-tipped rod that fits inside a tube, such as a tracheostomy tube or cannula, to guide it in and then is taken out.Full entry and inner cannulaKAN-yoo-luhA thin tube placed into the body or a body opening to deliver or remove fluid or air.Full entry , a spare tube of the same size, sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry , split sponges and ties.
Check the tube before it is needed: have it on the back table before the incision, with its obturator in place, and test a cuffed tube by inflating the cuff and deflating it again to show it has no leak. A cuffed tube is used for a patient at risk of aspirationas-puh-RAY-shunBreathing food, liquid, saliva or stomach contents into the airway and lungs; also, drawing fluid out with suction or a needle.Full entry or on a ventilator.

Key steps:
- lidocaineLY-doh-kaynA local anesthetic that numbs an area, also given by IV to treat some fast, abnormal heart rhythms.Full entry with epinephrineep-ih-NEF-rinA hormone and drug, also called adrenaline, that raises heart rate and blood pressure and opens the airways.Full entry is injected, and a transversetrans-VERSLying across something, at a right angle to its length.Full entry (or vertical) skin cut is made over the trachea, about two fingerbreadthFING-ger-bredthThe width of one finger, about 1 to 2 centimeters, used as a quick bedside measure.Full entry above the inner ends of the collarbones.
- The platysma is divided, and the strap muscles are separated in the midline with a hemostat or the ESU and held apart with retractors.
- The thyroid isthmus is pulled up out of the way, or clamped, divided and tied.
- The tracheal hook lifts the trachea at the cricoid. The surgeon opens the trachea with the knife, never the ESU, usually at the second to fourth rings: references describe a cut through the second and third rings, a cut into the second ring, or one between the second and third or the third and fourth rings. In an adult a square of cartilageKAR-tih-lijFirm, smooth, rubbery tissue that cushions joints and gives shape to parts such as the ear, nose and windpipe.chondr/o cartilageFull entry may be removed from the front of the trachea; in an infant the cut is a vertical slit with no cartilage removed. A dilator spreads the opening.
- Hand, in quick order: the hook, the knife, the dilator, then the tube with its obturator in place. As the trachea is opened, the anesthesia provideran-us-THEE-zhuh pruh-VY-derThe licensed professional who gives anesthesia and watches over the client's breathing and vital functions during a procedure.Full entry pulls the breathing tube back to just above the opening; the new tube goes in, the obturator comes out, the inner cannula goes in, the tube is suctioningSUK-shun-ingRemoving mucus, saliva or other secretions from the mouth, nose or airway with a tube connected to a suction source.Full entry , the cuff is inflated, and the breathing circuit is moved to it. Only when breathing through it is confirmed is the old tube taken out.
- The tube's plate is sewn to the skin (such as 2-0 nonabsorbable suture) and tied around the neck; split drain sponges go under it. Two stay sutures may be left in the tracheal edges, taped to the chest and marked (one knot on the upper, two on the lower), to pull the opening open if the tube comes out before the first change, about 5 to 7 days later.
let the patient leave the room without the obturator. It goes with the patient, with a spare tube of the same size, for as long as the tube is in: if the tube comes out or clogs, the obturator is needed to put a new one back in.
Wound class: Class II, since the trachea is opened.
After surgery: the patient cannot speak at first and needs a pencil and paper or a message board; later they learn to cover the opening briefly to speak. A replacement inner cannula is kept at hand in case the tube clogs. Swelling, bleeding, infection and injury to nearby structures are the complications.

Laryngectomy
What and why: a laryngectomy removes part or all of the larynx, most often for cancer, which is staged first by panendoscopy and biopsy; less often for a severe injury to the larynx or to separate the airway from the food passage completely in a patient who keeps aspirating.
- Partial laryngectomy removes only part, for a cancer confined to one cord or close by (a vertical hemilaryngectomy, a supraglottic or a supracricoid laryngectomy). The patient keeps a voice, usually hoarse, and normal swallowing. The surgeon tells the patient before surgery that a total laryngectomy may be needed if the tumor proves too large.
- Total laryngectomy removes the whole larynx, the hyoid bone and the strap muscles attached to it, with the tumor. The trachea is brought out to the skin of the neck as a permanent stoma, and the patient breathes only through it, never again through the nose or mouth; the voice box is gone. A neck dissectiondy-SEK-shunA tear in the inner layer of an artery wall that lets blood split the layers apart; also, the cutting apart of tissue in surgery.Full entry is often added.
Speaking again: the patient may learn esophagusih-SOF-uh-gusThe muscular tube that carries food and liquid from the throat to the stomach.esophag/o esophagusFull entry speech, swallowing air and bringing it back up to talk, use an artificial larynx, or have a tracheoesophageal puncture, a small opening made between the trachea and the esophagus, at the same operation or later, for a voice valve (prosthesispros-THEE-sisAn artificial body part that replaces one that is missing or does not work, such as an artificial leg, joint, eye or heart valve.Full entry ). Losing the voice is traumatic for the patient and family, so teaching and support start before surgery.
Before surgery: an awake tracheostomy may be done first to secure the airway, and a cuffed, wire-reinforceree-in-FORSTo repeat and support teaching or care that has already been started, so the client remembers and follows it.Full entry flexible tube is used. Supine, a shoulder roll, arms tucked; the prep covers the front and sides of the neck out to the shoulders and the upper chest (one reference preps from the nose to the umbilicus, the face included). The setup combines a neck dissection set, a vascular set and a thyroid set, with vessel loops, clips, a nerve stimulator, and laryngectomy and tracheostomy tubes.
Key steps (total laryngectomy):
- An apron-shaped incision is made across the neck, and the skin flaps are raised and held back with hooks or sutures.
- The strap muscles are divided, the carotidkuh-ROT-idHaving to do with the carotid arteries, the two large arteries on each side of the neck that carry blood to the head and brain.Full entry sheathSHEETHA covering that wraps around a structure; in procedures, a short hollow tube left in a blood vessel to pass catheters through.Full entry is moved aside, and the thyroid isthmus is divided; the thyroid lobe on the side of the tumor may be removed with the specimen, and the recurrent laryngeal nerve on that side is cut.
- The superior laryngeal nerves and vessels are tied, the muscles are freed from the thyroid cartilage, and the hyoid bone is freed and cut.
- The trachea is opened below the tumor, the old breathing tube comes out, a cuffed, wire-reinforced tube is placed in the lower trachea from the field, and the anesthesiaan-us-THEE-zhuhLoss of feeling or sensation, often brought on by drugs so that surgery or a procedure can be done without pain.an- withoutesthesi/o feeling, sensation-ia conditionFull entry circuit is moved to it; have that tube ready on the field.
- The pharynxFAIR-inksThe throat: the passage behind the nose and mouth that carries air to the voice box and food to the esophagus.pharyng/o throatFull entry is entered above the epiglottisep-ih-GLOT-isA leaf-shaped flap of cartilage at the back of the throat that covers the windpipe during swallowing.epi- upon, overglott/o the opening of the larynxFull entry , and the larynx is cut free from the esophagus and removed in one piece (en bloc).
- A enteral feeding tubeEN-ter-ul FEE-ding toobA tube placed into the stomach or small intestine to give liquid food, water and drugs to a person who cannot eat enough by mouth.Full entry is passed through the nose into the esophagus, and the pharynx is closed in two layers.
- The stoma is made by sewing the trachea to the skin, suction drains are placed, the neck is closed, and a laryngectomy tube goes into the stoma.
Wound class: Class II, because the pharynx and the airway are opened (one reference lists Class I).
After surgery: the ICU for airway monitoring; the air breathed through the stoma is no longer moistened by the nose, so the patient needs humidified air to keep secretions from drying and crusting, and must keep water and objects out of the stoma. Bleeding, infection and return of the cancer are the risks. antineoplastican-tee-nee-oh-PLAS-tikA drug used to treat cancer by killing cancer cells or stopping them from growing and dividing.anti- againstneo- newplas growth, formation-tic relating toFull entry and radiationray-dee-AY-shunEnergy that travels as waves or particles, such as X-rays, used to make images or treat cancer; also pain that spreads from its starting point.radi/o rays, radiation-ation processFull entry often follow once the wound heals.
12The neck and the salivary glands
Neck surgery is shallow but crowded with vessels and nerves, so the scrub's job is many fine hemostatHEE-moe-statA clamp with finger rings and a locking ratchet used in surgery to grasp and close off bleeding vessels.hem/o blood-stat stopping, standing stillFull entry and ties, soft retractionrih-TRAK-shunA drawing back or pulling in of tissue; in breathing, the skin sinking in between, below or above the ribs with each breath.Full entry (vessel loops and Penrose drains), the nerve stimulator, and a steady, quiet hand. Have hemostatichee-moh-STAT-ikStopping bleeding; also, a product or agent used to stop bleeding.hem/o blood-stasis stopping, standing still-ic relating toFull entry such as a gelatin matrix and topical thrombinTHROM-binAn enzyme in the blood that turns fibrinogen into fibrin, the threads that hold a blood clot together.thromb/o clot-in substanceFull entry ready for a large dissectiondy-SEK-shunA tear in the inner layer of an artery wall that lets blood split the layers apart; also, the cutting apart of tissue in surgery.Full entry .
Parotidectomy
What and why: a parotidectomy removes part or all of the parotid gland, most often for a tumor; it is also done for stones that block its duct, or for parotitis that keeps coming back. Most parotid tumors are benign and grow in the superficial lobe; a tumor in the deep lobe is more often malignant. The facial nerveFAY-shul NERVThe seventh cranial nerve, which moves the muscles of the face and carries taste from the front of the tongue.Full entry runs through the gland between its two lobes and splits into its branches inside it, so the whole operation is built around finding and saving the nerve. The consent covers the risk of facial weakness, and the possibility of a larger operation if a cancer is found.
Before surgery: general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry without neuromuscular blocking agentnoor-oh-MUS-kyuh-ler BLOK-ing AY-juntA drug that blocks signals from nerves to skeletal muscles, so the muscles relax completely and cannot move.Full entry (muscle relaxants), so the facial nerve can be found by stimulating it; the facial nerve monitor's electrodes go in before the prep. Supine, the head turned so the operative side is up, arms tucked, on a doughnut headrest; the table may be turned. A cotton ball in the ear keeps the prep out. The prep covers that side of the face, the ear and the neck; the drapes leave the corner of the eye and the mouth in view, so the surgeon can see the face twitch.
Setup: a neck dissection or major set with a plastic set, a thyroid set, nerve hooks, single and double skin hooks, extra right-angle clamps, vessel loops and clips, monopolar and bipolarby-POH-lerHaving two poles or two opposite ends; most often used as a short form of bipolar disorder.bi- twopolar having polesFull entry electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry , a nerve stimulator or nerve monitor, a fine facial nerve dissector (such as the McCabe), and lacrimal probes if the duct will be explored.

Key steps:
- The incision starts in front of the ear and curves down behind the earlobe into the upper neck below the jaw. Skin flaps are raised and held with skin hooks or rakes; you may be asked to hold the hooks.
- The gland is freed from the SCM and from the cartilageKAR-tih-lijFirm, smooth, rubbery tissue that cushions joints and gives shape to parts such as the ear, nose and windpipe.chondr/o cartilageFull entry of the ear canal, and the great auricular nerve is found.
- The trunk of the facial nerve is found where it leaves the skull, with the help of landmarks such as the tragal pointer, a point of the ear canal cartilage (the nerve lies about 1 cm deep to it), and the nerve stimulator.
- The surgeon follows each branch forward with a mosquito clamp and bipolar ESU or the facial nerve dissector, lifting the superficial lobe off the nerve. To loop a vessel loop around the nerve, pass it held in the tip of a right-angle clamp, then clamp its ends with a mosquito.
- If the deep lobe must come out, the nerve is gently lifted aside on vessel loops and the deep lobe is freed beneath it, with Allis clamps for countertraction. Ask whether the superficial and deep lobes go as separate specimens.
- The wound is irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry , a closed suction drain is placed, and the wound is closed in layers; a fat graftGRAFTTissue or a man-made material moved into place in surgery to replace or repair a damaged part.Full entry may fill a hollow, and a bulky pressure dressing goes on.
Wound class: Class I, clean.
After surgery: the head of the stretcher is raised to limit swelling. The facial nerve is checked at once; weakness may be temporary or lasting. Bleeding and infection are the other complications.
Excision of the submandibular gland
The submandibular gland is removed for tumors, or for stones with long-lasting inflammation. Through an incision below and parallel to the jaw, the surgeon lifts the gland, holding the marginal mandibular branch of the facial nerve aside and keeping the lingual and hypoglossal nerves safe; the duct (the Wharton duct) and the facial artery are tied and divided, and a drain is placed. Have a nerve stimulator and bipolar ready, with lacrimal probes if the duct will be explored. It is Class I unless the mouth is entered.
Neck dissection
What and why: a neck dissection removes the lymph nodelimf nohdA small, bean-shaped organ of the immune system that filters lymph fluid and holds white blood cells.Full entry of the neck, with the fat around them, when cancer of the head and neck (the mouth, throat, larynxLAIR-inksThe voice box: the part of the airway in the neck, above the windpipe, that holds the vocal cords.laryng/o larynxFull entry , skin or thyroid) has spread there or is likely to. It is often part of a larger cancer operation and stages the cancer to guide treatment after surgery.
- Radical neck dissection: removes, in one piece, the nodes and all the soft tissue on that side from the jaw to the clavicleKLAV-ih-kulThe long, slightly S-shaped bone that runs from the top of the breastbone to the shoulder; the collarbone.clavicul/o collarboneFull entry , together with the SCM, the internal jugular veinin-TUR-nul JUG-yuh-ler vaynA large vein deep on each side of the neck that carries blood from the brain, face and neck back toward the heart.Full entry and the spinal accessory nerve. It is rarely done now.
- Modified radical neck dissection: removes all the node-bearing tissue but spares one or more of those three structures (the SCM, the jugular veinJUG-yuh-ler VAYNOne of the large veins on each side of the neck that carry blood from the head back toward the heart.Full entry and the spinal accessory nerve). It is preferred unless the cancer is very advanced, and it leaves the shoulder working better.
- Selective neck dissection: removes only the node groups most at risk, such as the upper jugularJUG-yuh-lerRelating to the neck, especially the large veins in the neck.Full entry chain, and keeps the nerves, vessels and muscles.
A prophylaxisproh-fuh-LAK-sisTreatment given to prevent a disease or problem, rather than to treat one that is already present.pro- beforephylax guardFull entry (elective) neck dissection is one done when no cancer can yet be found in the nodes. A sentinel node biopsy may be done with it.
Before surgery: general anesthesia; supine on a doughnut or Mayfield headrest, a shoulder roll, the head turned away and the head of the table raised a little to reduce venous bleeding. The anesthesia provideran-us-THEE-zhuh pruh-VY-derThe licensed professional who gives anesthesia and watches over the client's breathing and vital functions during a procedure.Full entry works behind a sterile barrier on the other side. The prep is wide: the neck, the lower face and the upper chest, plus a thigh if a skin graft may be needed.
Setup: neck dissection instruments with vascular clamps, many right-angle clamps and hemostats, a tracheotomytray-kee-OT-uh-meeThe surgical cut made into the windpipe through the front of the neck.trache/o windpipe-tomy cutting, incisionFull entry set, vessel loops, clips, silk ties and sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry ligatures, retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry (skin hooks, Army-Navy and a vein retractor), the nerve stimulator, closed suction drains and hemostatic agents.
Key steps (radical):
- A Y-shaped, H-shaped or three-limbed incision; the skin and platysma flaps are raised with the knife and ESU and held back.
- The SCM is cut from the sternum and clavicle (or, in a modified dissection, freed and held aside), and the omohyoid muscle is divided.
- The carotidkuh-ROT-idHaving to do with the carotid arteries, the two large arteries on each side of the neck that carry blood to the head and brain.Full entry sheathSHEETHA covering that wraps around a structure; in procedures, a short hollow tube left in a blood vessel to pass catheters through.Full entry is opened. The internal jugular vein is clamped twice, tied twice and divided, with a stitch through its lower end. The carotid artery and the vagus nerveVAY-gus nervThe 10th cranial nerve, which runs from the brain stem to the chest and belly and slows the heart and helps digestion.Full entry are found and protected.
- The fat, fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry and nodes are swept off the floor of the neck, from the front edge of the trapezius forward, past the brachial plexusPLEK-susA network of nerves or blood vessels that branch and join together.Full entry , tying the small branches of the arteries and veins as they come.
- The submandibular triangle is cleared, the submandibular gland comes out with the specimen, the upper end of the jugular vein is divided, and the whole specimen is removed in one piece.
- The field is checked for bleeding and irrigated with warm saline. If needed, a skin graft may cover the fork of the carotid artery. Closed suction drains are placed, the flaps are closed, and a bulky dressing may go on. A tracheotomy is done if needed.
Specimen: several may come off, such as nodes from different levels and extra margins; keep each separate and labeled exactly as the surgeon names it.
Wound class: Class I when the mouth, throat and airway are not opened; Class II when the dissection is joined to an operation that opens them, such as a laryngectomy or removal of a mouth cancer.
After surgery: the patient stays at least a day to be watched for swelling, bleeding or a hematomahee-muh-TOH-muhA collection of blood, often clotted, that has leaked out of the blood vessels into the tissue.hem/o blood (here as hemat-)-oma swelling or massFull entry . Bleeding in the neck is an airway emergency, because a growing blood clot squeezes the tracheaTRAY-kee-uhThe windpipe: the tube that carries air from the throat to the lungs.Full entry . radiationray-dee-AY-shunEnergy that travels as waves or particles, such as X-rays, used to make images or treat cancer; also pain that spreads from its starting point.radi/o rays, radiation-ation processFull entry or antineoplastican-tee-nee-oh-PLAS-tikA drug used to treat cancer by killing cancer cells or stopping them from growing and dividing.anti- againstneo- newplas growth, formation-tic relating toFull entry often follows.
Cancer of the mouth and its reconstruction
A cancer of the tongue, the floor of the mouth or the tonsilTON-sulOne of the masses of lymph tissue at the back of the throat that help fight germs entering the mouth and nose.Full entry area is removed with a margin of healthy tissue. A partial glossectomy (hemiglossectomy) removes less than half of the tongue: under general anesthesia, with a head and neck prep, the tongue is pulled forward with a heavy silk tractionTRAK-shunA steady pulling force applied to a body part with weights, ropes and pulleys.Full entry stitch or towel clips, the tumor is cut out with a wide margin using the ESU, and the defect is closed with 3-0 absorbable suture or a split-thickness skin graft. A neck dissection is often added, and extensive disease may need a tracheostomytray-kee-OS-tuh-meeA surgical opening through the front of the neck into the windpipe, usually holding a tube that the person breathes through.trache/o windpipe-stomy surgical openingFull entry and a enteral feeding tubeEN-ter-ul FEE-ding toobA tube placed into the stomach or small intestine to give liquid food, water and drugs to a person who cannot eat enough by mouth.Full entry . A total glossectomy almost always comes with a total laryngectomy. It is Class II, since the mouth is entered. Chapter 37 teaches the jaw split that reaches a larger cancer (a mandibulotomy), and chapter 38 the flaps that fill large defects.
Thyroidectomy and parathyroidectomy
Chapter 32 teaches both operations step by step: minimally invasive video-assisted thyroidectomythy-roy-DEK-tuh-meeSurgery to remove all or part of the thyroid gland in the neck.thyr/o thyroid-ectomy surgical removalFull entry (MIVAT), now a standard operation, with the open set ready, and the open thyroidectomy through a collar incision, kept for selected cases such as a very large gland or a MIVAT that must be converted; and the parathyroidectomy guided by hormone levels measured during the case. The Core Curriculum lists them with ENT as well, and general surgeons commonly do them. Here is what ENT adds.
other references still teach the open thyroidectomy through a collar incision as the standard operation.
- Nerve monitoring: the anesthesia provider places a breathing tube with built-in sensors (an electromyographyih-lek-troh-my-OG-ruh-feeA test that records the electrical activity of muscles, usually through thin needles placed in the muscle.electr/o electricitymy/o muscle-graphy recordingFull entry tube), and the monitor warns when the dissection comes near the laryngeal nerves. It is a help, never a substitute for seeing the nerve.
- The laryngeal nerves (see the anatomy above): the ESU is not used near the recurrent or superior laryngeal nerve, because its current spreads.
- Robotic remote access: a robotic thyroidectomy reaches the gland from away from the front of the neck, such as the armpit, behind the ear or through the mouth; chapter 32 teaches it and the cases that rule it out.
- The parathyroid glandpair-uh-THY-royd glandOne of four small glands behind the thyroid that control the amount of calcium in the blood.para- besidethyr/o thyroid gland-oid likeFull entry : usually four tiny glands behind the thyroid that control blood calcium. A removed gland stays in sterile saline on the back table until the hormone result is back; a normal one taken by mistake is cut into tiny pieces and replanted in a muscle of the neck.
- After surgery: a neck hematoma can squeeze the airway, so the back table and Mayo stay sterile until the patient leaves the room, and a tracheotomy tray goes with the patient to PACU. Numbness and tingling, then twitching, mean low calcium.
Wound class: Class I, since no tract is entered.
13Temporomandibular joint arthroscopy
What and why: the temporomandibular joint (TMJ) joins the jaw to the temporal bone. An avascular disc glides between the bones as the jaw opens and closes. Arthroscopy looks into the joint to diagnose a temporomandibular disorder, most often a disc slipped forward that will not move back when the mouth closes, causing pain and limited jaw movement. The disorder may come from the muscles, as from clenching, or from the joint itself, and it is second only to toothache as a cause of pain in the face. Chapter 37 teaches open surgery of the joint and the fractures of the face and jaw.
Before surgery: general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry ; supine with the head turned so the joint is up, a doughnut headrest, arms tucked. The hair is held back in a head wrap, the face, chin and neck are prepped, and an incise drape with a fluid pouch goes over the joint; the mouth and nose are covered. Both sides may be done. computed tomographykum-PYOO-tid toh-MOG-ruh-feeAn imaging test that uses x-rays and a computer to make cross-section pictures of the inside of the body.tom/o cut, slice-graphy process of recordingFull entry are in the room.
Setup: a TMJ arthroscopy set with 0, 30 and 70-degree arthroscopes, the camera and light cord, a trocarTROH-karA sharp or bladed instrument inside a tube (cannula), used to pierce a body wall and leave the tube in place as a port.Full entry and sheathSHEETHA covering that wraps around a structure; in procedures, a short hollow tube left in a blood vessel to pass catheters through.Full entry with sharp and blunt obturatorOB-too-ray-terA smooth-tipped rod that fits inside a tube, such as a tracheostomy tube or cannula, to guide it in and then is taken out.Full entry , a small joint shaver and its power unit, a fluid system with lactated Ringer's solutionLAK-tay-tid RING-erz suh-LOO-shunAn isotonic IV fluid containing water, sodium, chloride, potassium, calcium and lactate.Full entry , an 18-gauge needle, a #11 blade, bipolarby-POH-lerHaving two poles or two opposite ends; most often used as a short form of bipolar disorder.bi- twopolar having polesFull entry electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry , and small probes, graspers, scissors and sickle knives.
Key steps:
- The jaw is moved to find the entry points, which are marked on the skin.
- lidocaineLY-doh-kaynA local anesthetic that numbs an area, also given by IV to treat some fast, abnormal heart rhythms.Full entry with epinephrineep-ih-NEF-rinA hormone and drug, also called adrenaline, that raises heart rate and blood pressure and opens the airways.Full entry , or lactated Ringer's, is injected into the joint to swell it open.
- A stab wound is made with a #11 blade, the sharp trocar and sheath go in, the trocar is swapped for the blunt obturator, and then the telescope (often 30 degrees) goes in.
- Fluid runs through the joint to clear the view, and the joint is examined and photographed.
- For treatment, a second puncture takes the probes, shaver or graspers.
- The fluid is drained from the joint, the instruments come out, and the punctures are closed with fine sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry or skin strips.
Wound class: Class I, clean.
After surgery: pain and swelling, helped by ice; a liquid or soft diet for some days; jaw movement may be limited. Removing the breathing tube can be difficult, so have suction and emergency airway supplies ready. The disorder can return if the clenching or grinding goes on.
14Wound classes in ENT
The CDC's rule decides the class: Class I when no tract is entered, Class II when the respiratory or digestive tract is entered under control, and the CDC names the oropharynxor-oh-FAIR-inksThe middle part of the throat, behind the mouth, from the soft palate down to the top of the voice box.or/o mouthpharyng/o throatFull entry as an example of Class II. A fresh injury is Class III, and an infection already present is Class IV.
| Case | Class | Why |
|---|---|---|
| Tympanoplasty, myringoplasty, ossiculoplasty, stapes surgery, mastoidectomy, cochlear and bone-anchored implants, eighth-nerve surgery | I | Done through skin and bone, with no tract entered; an ear that is actively infected is Class IV |
| Myringotomy | II in one reference | Fluid or pus is drained from the middle ear; when an infection is already present, the CDC's Class IV fits |
| Septoplasty, turbinate surgery, closed nasal fracture reduction, valve repair, FESS, polypectomy, Caldwell-Luc, choanal atresia repair | II | The nose and sinusSY-nusA hollow space in the body, most often one of the air-filled spaces in the skull bones around the nose.Full entry are part of the respiratory tract; no reference gives a class for a closed fracture reduction, so it follows the CDC |
| Tonsillectomy, adenoidectomy, UPPP, glossectomy | II | The mouth or oropharynx is entered |
| Laryngoscopy, bronchoscopybrong-KOS-kuh-peeA procedure in which a thin, lighted tube with a camera is passed through the nose or mouth to look inside the airways.bronch/o airway (bronchus)-scopy looking with an instrumentFull entry , esophagoscopy | II | A tract entered through its own opening |
| tracheotomytray-kee-OT-uh-meeThe surgical cut made into the windpipe through the front of the neck.trache/o windpipe-tomy cutting, incisionFull entry , laryngectomy | II | The airway is opened (one reference lists a laryngectomy as Class I) |
| Parotidectomy, submandibular gland excisionek-SIZH-unCutting out tissue, such as a growth or damaged area, during surgery.Full entry , neck dissectiondy-SEK-shunA tear in the inner layer of an artery wall that lets blood split the layers apart; also, the cutting apart of tissue in surgery.Full entry alone, thyroidectomythy-roy-DEK-tuh-meeSurgery to remove all or part of the thyroid gland in the neck.thyr/o thyroid-ectomy surgical removalFull entry , parathyroidectomy, TMJ arthroscopy | I | No tract is entered; II when the neck operation opens the mouth or throat |
15After ENT surgery
- The airway first: oral, throat and larynxLAIR-inksThe voice box: the part of the airway in the neck, above the windpipe, that holds the vocal cords.laryng/o larynxFull entry surgery can make the airway swell, so the head of the bed is raised, and the PACU nurse is told about the case. Repeated swallowing can mean blood running down from the back of the nose or mouth. Keep the instruments and suction ready until the patient leaves the room, and send the obturatorOB-too-ray-terA smooth-tipped rod that fits inside a tube, such as a tracheostomy tube or cannula, to guide it in and then is taken out.Full entry and a spare tube with a tracheostomytray-kee-OS-tuh-meeA surgical opening through the front of the neck into the windpipe, usually holding a tube that the person breathes through.trache/o windpipe-stomy surgical openingFull entry patient.
- Hearing and balance: dizziness, nausea and vertigoVER-tih-gohA false feeling that you or the room around you is spinning or moving.Full entry can follow ear surgery; vertigo lasting more than 24 to 48 hours is reported.
- A leak of cerebrospinal fluidser-uh-broh-SPY-nul FLOO-idThe clear, watery fluid that bathes and cushions the brain and spinal cord.cerebr/o brainspin spine-al relating toFull entry : clear fluid from the nose or ear after sinusSY-nusA hollow space in the body, most often one of the air-filled spaces in the skull bones around the nose.Full entry , skull base or ear surgery is reported at once.
- Teaching: the head raised about 30 degrees for the first day at home, no straining, no hard nose blowing, sneezing with the mouth open, no straws, and a call to the surgeon for fever, bleeding, trouble breathing or swallowing, or clear drainage. Patients who cannot hear or speak get written instructions with pictures, and every patient gets the name and telephone number of someone to contact with questions.
What to take from this chapter
- ENT surgery shares the airway with anesthesia. Fires start more easily in the head and neck: low oxygen, wet sponges, a laser-resistant tube with a blue saline cuff for laser work, and saline on the field. After a tonsillectomy, a laryngoscopy, a UPPP or a thyroidectomy, the setup and suction stay ready until the patient leaves the room.
- Many ENT patients cannot hear or speak. Agree on a way to communicate before surgery, and check the facial nerve after ear, mastoid and parotid cases.
- Ear cases: the head turned with the ear up, the table often turned around for the microscope, a cotton ball in the canal and never chlorhexidine. The instruments are tiny and live in their rack; pass them turned for use, because the surgeon does not look away from the microscope.
- The drill is irrigated the whole time it runs, diamond burrs go near the facial nerve, and the safety is locked before every burr change. A cochlear implant is opened under saline against static, and once it is in, bipolar only.
- Nose and sinus cases start with counted cottonoids soaked in a vasoconstrictor. Epinephrine 1:1,000 is topical only; label every strength the moment it reaches the field. In FESS the eyes stay in view, and tissue that floats in saline may be orbital fat.
- A myringotomy tube, an ossicle or stapes prosthesis and a cochlear implant are implants: confirm, record and handle them as their makers direct.
- A tracheostomy patient never leaves without the obturator and a spare tube; the trachea is opened with a knife, never the ESU. A total laryngectomy leaves a permanent stoma and no larynx, so the patient breathes only through the neck.
- Wound classes follow the CDC: ear, parotid, thyroid and neck operations that open no tract are Class I; the nose, sinuses, mouth, throat and airway are Class II.
Check yourself5 quick questions
Free for everyone. Pick an answer for each, then check them all at once.
In the ORWhere you'll use this
The chapter's whole question pool in sets of 10, with the answer explained after each one.
Part of the educators programThe chapter's words on spaced cards: the ones you miss come back sooner.
Part of the educators programGiven by your class's teacher. Each class draws its own 25 from the chapter's pool.
Part of the educators program
Suggest a fix
Something wrong, unclear or out of date in this chapter? Tell us and we will fix it for everyone. Your email is only used to reply.