Genitourinary surgery
Scopes through the urethra, stones, kidneys, bladders, prostates and the male genitals: the cases of urology, the fluids and catheters they run on, and how to stay one step ahead of the surgeon.
1What genitourinary surgery covers
genitourinaryjen-ih-toh-YOOR-ih-nair-eeRelating to the genital (reproductive) organs and the urinary organs together.genit/o reproductive organsurin/o urine-ary relating toFull entry (GU) surgery, or urology, treats the urinary tract: the kidneys, the ureterYOOR-uh-terOne of the two tubes that carry urine from the kidneys down to the bladder.Full entry , the bladder and the urethrayoo-REE-thruhThe tube that carries urine from the bladder out of the body.Full entry . It also treats the adrenal glanduh-DREE-nul GLANDOne of two small glands that sit on top of the kidneys and make hormones such as cortisol, aldosterone and epinephrine.ad- toward, nearren/o kidney-al relating toFull entry , perched on top of each kidney, and the male reproductive organs: the prostatePROS-taytA walnut-sized gland below the bladder in males that surrounds the urethra and makes part of the fluid in semen.Full entry , the testes, the scrotumSKROH-tumThe pouch of skin and muscle that holds the testicles.Full entry and the penis. Because diseases of the prostate are so common, more urology patients are male, and many are older adults.
Urologists reach these organs in several ways, and you will meet all of them:
- Transurethral: a rigid or flexible scope passed up the urethra reaches the urethra, prostate, bladder and ureters with no incision at all. It is the usual way into the bladder and the prostate.
- Percutaneous: through the skin. In a percutaneous nephrolithotomy, for example, a scope enters the kidney through a small incision in the flank.
- Open: an incision in the abdomen, the flank or the perineumpair-ih-NEE-umThe area of skin and muscle between the genitals and the anus.perine/o perineumFull entry , including approaches that stay behind the peritoneumpair-ih-toh-NEE-umThe thin membrane that lines the belly cavity and covers most of the organs inside it.peri- aroundton stretched-eum a structureFull entry .
- laparoscopiclap-uh-roh-SKOP-ikDone through a few small cuts in the abdomen with a thin camera and long instruments, instead of one large opening.lapar/o abdomen-scopic viewingFull entry and robotic: ports in the abdomen, as in general surgery. Many operations that were once open are now done this way; the robotic prostatectomy and the robotic nephrectomy are the most common.
Any approach other than open counts as minimally invasive surgery (MIS), and scopes through a natural opening count too. Cases that share instruments, positions and steps are taught together as co-related procedures. Learn a cystoscopy once and every transurethral case starts the same way; learn a nephrectomy and the partial nephrectomy, the radical nephrectomy and the donor nephrectomy are mostly new middles. Each case links to its setup card, which holds the full instrument list and every step.
Genitourinary is one of the specialties in your clinical case count. A plain cystoscopy is a diagnostic case, and diagnostic cases count only in the second scrub role, up to ten of the 120. Once something is done through the scope, such as placing a ureteral stentstentA small tube, often of metal mesh, placed inside a vessel or duct to hold it open.Full entry , the case becomes operative.
The cysto room
Transurethral cases usually happen in a cystoscopy ("cysto") room built for them, with a cystoscopy table, the scopes and their supplies close at hand, often a place to process the scopes, and a way to get rid of large amounts of fluid. Many facilities have a cysto assistant, a surgical technologistSUR-jih-kul tek-NOL-uh-jistA member of the operating room team who prepares the sterile field and instruments and hands them to the surgeon.Full entry or nurse who works mainly in this room. The assistant sets up the sterile table, then often circulates, because the urologist does not always need a scrubbed assistant. When the patient has general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry or monitored anesthesiaan-us-THEE-zhuhLoss of feeling or sensation, often brought on by drugs so that surgery or a procedure can be done without pain.an- withoutesthesi/o feeling, sensation-ia conditionFull entry care, a registered nurse circulator must be present, and facility policy may require one for every case.
The circulating cysto assistant stays in the room, connects the nonsterile ends of cords and tubing, opens supplies, keeps the irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry bags full and notes how much is used, receives and labels specimens, and checks vital signs every 15 minutes when the patient has only a local anestheticLOH-kul an-es-THET-ikA drug that blocks feeling in one part of the body without making the person unconscious.Full entry .
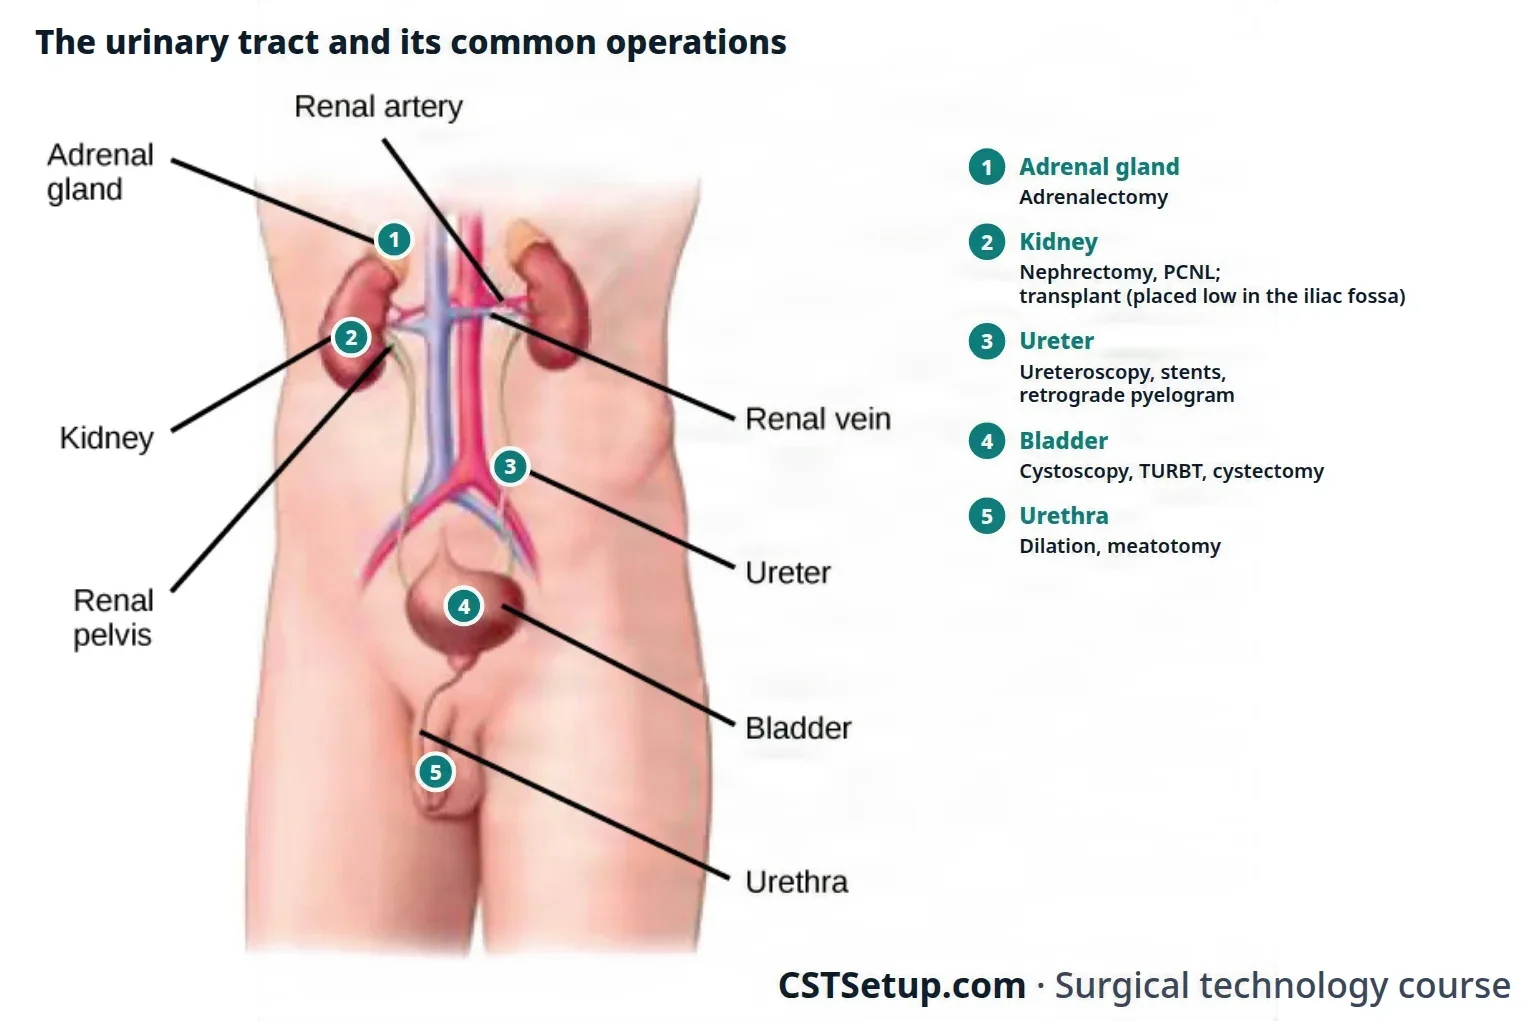
2Anatomy that matters
Chapter 8 teaches the kidneys, the bladder and the male organs in full, including the nephronNEF-ronThe tiny filtering unit of the kidney, where blood is filtered and urine is made.nephr/o kidneyFull entry , how urine is made, the seminal vesicleVES-ih-kulA small, raised blister on the skin filled with clear fluid, less than 1 cm across.Full entry and the bulbourethral glands. Here is only what the operations in this chapter lean on.
Kidneys and adrenal glands
The kidneys lie behind the peritoneumpair-ih-toh-NEE-umThe thin membrane that lines the belly cavity and covers most of the organs inside it.peri- aroundton stretched-eum a structureFull entry , in the retroperitoneal space beside the spine, from about the 12th thoracicthuh-RAS-ikRelating to the chest, or to the middle part of the spine.thorac/o chest-ic relating toFull entry to the 3rd lumbarLUM-barHaving to do with the lower back, the part of the spine between the ribs and the pelvis.Full entry vertebra, so the surgeon can reach them through the flank or through the abdomen. Each sits in a mass of fat inside the renal fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry (Gerota fascia). The renal artery and vein, with their nerves and lymphLIMFThe clear fluid that flows through the lymphatic vessels and carries white blood cells.Full entry vessels, form the pediclePED-ih-kulA narrow stem or stalk that attaches a structure, such as a tumor or a skin flap, to the body.Full entry of the kidney, which the surgeon controls before a kidney comes out; the renal pelvis, the funnel that collects urine, lies behind the vessels at the hilum.
An adrenal glanduh-DREE-nul GLANDOne of two small glands that sit on top of the kidneys and make hormones such as cortisol, aldosterone and epinephrine.ad- toward, nearren/o kidney-al relating toFull entry caps the top of each kidney. The right adrenaluh-DREE-nulHaving to do with the adrenal glands, the two small glands that sit on top of the kidneys.ad- nearren/o kidney-al relating toFull entry vein drains straight into the inferior vena cavain-FEER-ee-er VEE-nuh KAY-vuhThe large vein that carries blood from the lower body back to the right atrium of the heart.inferior lowervena veincava hollowFull entry ; the left drains into the left renal vein. Chapter 9 teaches the glands and their hormones.
Ureters, bladder and urethra
Each ureterYOOR-uh-terOne of the two tubes that carry urine from the kidneys down to the bladder.Full entry runs about 25 to 30 cm from the renal pelvis down to the bladder, lying on the psoas muscle. The bladder sits behind the pubic symphysisSIM-fih-sisA joint where two bones are joined firmly by a pad of cartilage that allows only a little movement.Full entry , outside the peritonealper-ih-toh-NEE-ulHaving to do with the peritoneum, the thin lining of the belly cavity and the organs inside it.Full entry cavity, so a suprapubic incision can reach it without opening the peritoneum. On its floor, the trigone is the triangle between the two ureteral openings and the bladder neck: the landmarks the surgeon finds at every cystoscopy.
The male urethrayoo-REE-thruhThe tube that carries urine from the bladder out of the body.Full entry is about 20 to 25 cm long. It runs through the prostatePROS-taytA walnut-sized gland below the bladder in males that surrounds the urethra and makes part of the fluid in semen.Full entry (the prostatic urethra, where the ejaculatory ducts open on a small mound, the verumontanum), then through the pelvic floor and the penis; strictureSTRIK-cherA narrowed section of a hollow body passage, such as the urethra, esophagus or bowel, that is tighter than normal.Full entry form most often in its bulbar part. The female urethra is only about 3 to 5 cm long. The urinary tract holds no germs except near the end of the urethra, so every instrument and catheter passed up the urethra must be sterile, or it carries germs up into the bladder.
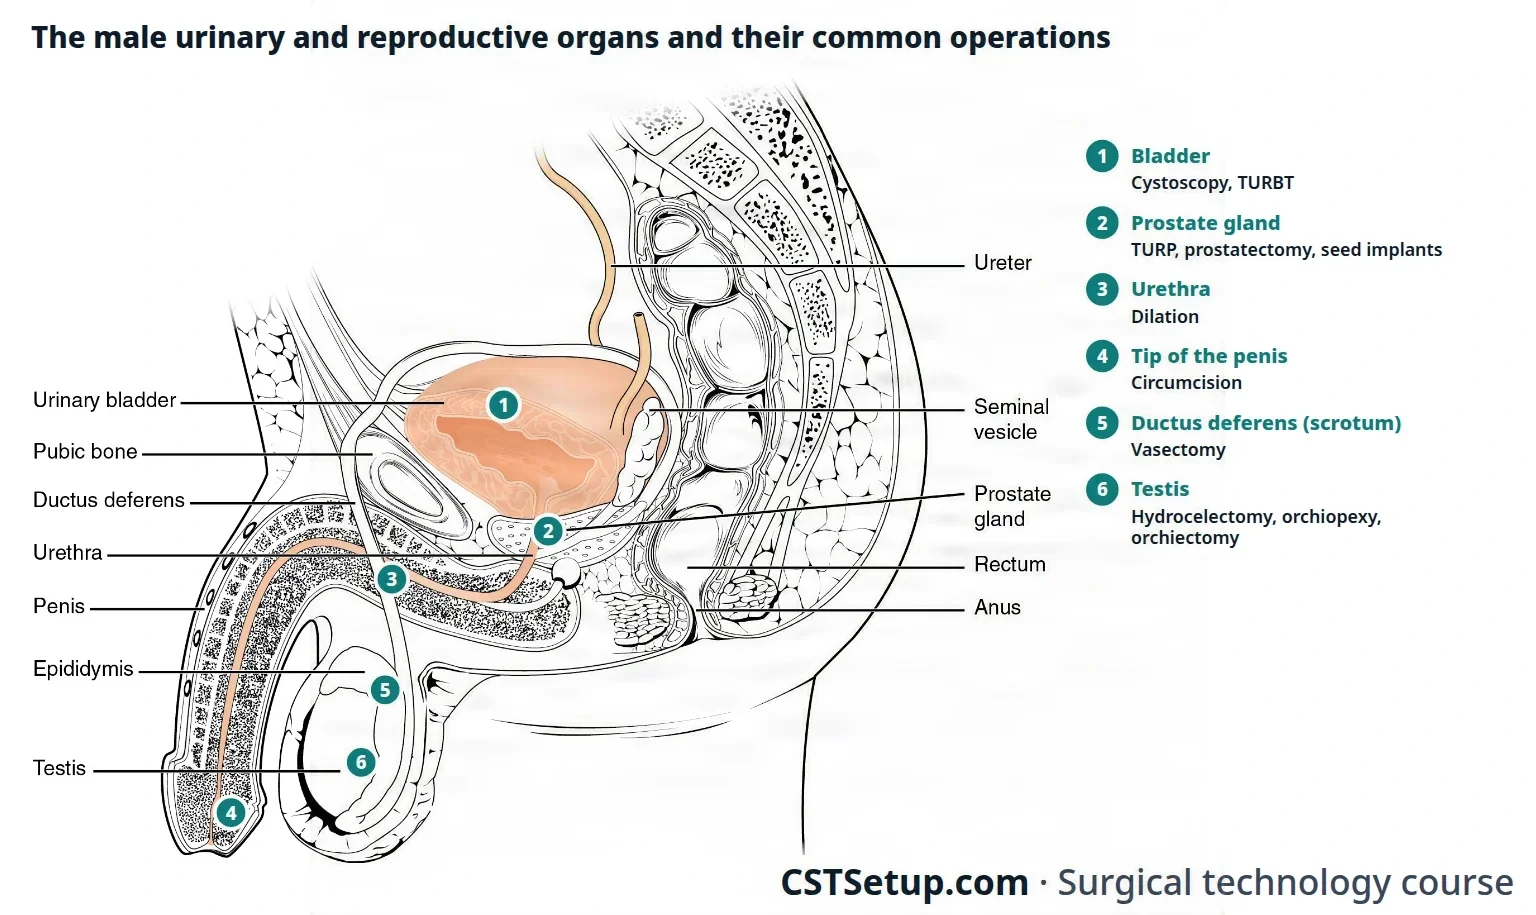
Prostate
The prostate is a walnut-shaped gland of about 20 to 30 g that wraps around the urethra just below the bladder neck, in front of the rectum. It is described in zones, two major (peripheral and central) and two minor (transitional and periurethral), but many clinicians still speak of lobes: two lateral lobes, a median lobe and a posterior lobe. Benign enlargement usually starts in the transitional zone, around the urethra; the posterior lobe, which can be felt on a rectalREK-tulRelating to the rectum, the last part of the large intestine; also, given or measured through the rectum.rect/o rectum, straight-al relating toFull entry exam, is prone to cancer. The nerves for erection run in bundles beside the gland, which is why surgeons try to spare them.
Scrotum, testes and penis
Each testis hangs in the scrotumSKROH-tumThe pouch of skin and muscle that holds the testicles.Full entry inside the tunica vaginalis, a smooth sac that holds a little clear fluid, and its Leydig cells make testosteronetes-TOS-tuh-rohnThe main male sex hormone, made mostly in the testes and in small amounts by the ovaries and adrenal glands.test/o testis-sterone steroid hormoneFull entry . The epididymisep-ih-DID-ih-misA coiled tube on the back of each testis where sperm mature and are stored.epi- upondidym testis (twin)Full entry runs along the back of the testis, and the vas deferens carries sperm up inside the spermatic cord, with the testicular vessels, nerves, lymph vessels and the cremaster muscle, through the inguinalING-gwih-nulRelating to the groin, the fold where the thigh meets the lower abdomen.Full entry canal.
The penis has two corpora cavernosa, the columns that fill with blood in an erection, and the corpus spongiosum, which surrounds the urethra and ends as the glans. The prepuce (foreskin) covers the glans, and Buck fascia wraps the erectile bodies.
3Diagnostic tests
Tests show both how well the kidneys work and where the structural problem lies.
Urine: a urinalysis looks for normal and abnormal substances in the urine, and a culture and sensitivityKUL-cher and sen-sih-TIV-ih-teeA lab test that grows the germs from a sample to identify them and see which antibiotics work against them.Full entry may confirm an infection and pick the antibiotic; chapter 8 teaches how to read them, urine specific gravityYOOR-in speh-SIF-ik GRAV-ih-teeA urine test that measures how concentrated the urine is, compared with the weight of plain water.Full entry (how concentrated the urine is) included. Normal urine output in an adult is about 0.5 to 1 mL per kg of body weight an hour; during surgery, less than 30 mL an hour is reported.
Blood: creatininekree-AT-uh-neenA waste product of muscle that the kidneys remove from the blood; its blood level is used to measure how well the kidneys work.Full entry , a waste of muscle that the kidneys filter, shows how well they work. The glomerular filtration rategloh-MER-yuh-ler fil-TRAY-shun RAYTHow much blood the kidneys filter each minute, used as the main measure of kidney function.Full entry (GFR), about 125 mL a minute in a healthy adult, measures how fast creatinine is cleared, and blood creatinine starts to rise only when the GFR has fallen to about half. blood urea nitrogenblud yoo-REE-uh NY-truh-jenA blood test that measures urea nitrogen, a waste product made when the body breaks down protein.Full entry (BUN) rises in renal failureREE-nul FAYL-yerLoss of the kidneys' ability to filter waste and extra fluid from the blood.ren kidney-al relating toFull entry but also with protein intake, age and dehydration. Electrolytes, a blood count and clottingKLOT-ingThe process by which blood thickens into a gel to plug a damaged vessel and stop bleeding; also called coagulation.Full entry studies are routine before surgery.
prostate-specific antigenPROS-tayt spuh-SIF-ik AN-tih-junA protein made by the prostate gland, measured in a blood test to screen for and follow prostate problems.Full entry (PSA): a blood test that screens for prostate cancerPROS-tayt KAN-serCancer that starts in the prostate, the gland below the bladder in males that helps make semen.Full entry . The blood is drawn before the digital rectalREK-tulRelating to the rectum, the last part of the large intestine; also, given or measured through the rectum.rect/o rectum, straight-al relating toFull entry exam (DRE), because handling the gland can change the result. An enlarged prostatePROS-taytA walnut-sized gland below the bladder in males that surrounds the urethra and makes part of the fluid in semen.Full entry or prostatitispros-tuh-TY-tisInflammation of the prostate gland.prostat/o prostate-itis inflammationFull entry can also raise the PSA, and PSA alone misses some cancers, so a raised value usually leads to a needle biopsy guided by transrectal ultrasound.
Imaging:
- computed tomographykum-PYOO-tid toh-MOG-ruh-feeAn imaging test that uses x-rays and a computer to make cross-section pictures of the inside of the body.tom/o cut, slice-graphy process of recordingFull entry : the preferred study for kidney tumors; a CT without contrastKON-trastA dye or other substance given before an imaging test so body parts show up more clearly.Full entry is the usual way to find stones, because it shows stones of every type, even small ones.
- KUB: a plain X-ray of the kidneys, ureterYOOR-uh-terOne of the two tubes that carry urine from the kidneys down to the bladder.Full entry and bladder. It shows many stones larger than about 2 mm.
- Intravenous urography (IVPeye-vee-PEE (said as letters)An abbreviation with more than one meaning, most often IV push or intravenous pyelogram.Full entry ): contrast injected into a vein outlines the renal pelvis, calyces and ureters on a series of X-rays.
- Retrograde pyelography: contrast instilled through a catheter passed up the ureter during cystoscopy outlines the renal pelvis from below. "Retrograde" means against the normal flow.
- Voiding cystourethrogram: contrast fills the bladder through a catheter, and X-rays are taken while the patient voids.
- Ultrasound, magnetic resonance imagingmag-NET-ik REZ-uh-nunts IM-uh-jingAn imaging test that uses a strong magnet and radio waves to make detailed pictures of the inside of the body.Full entry and nuclear scans: ultrasound is often the first study; MRI gives fine detail; a radioisotope scan looks for cancer that has spread.
endoscopyen-DOS-kuh-peeA procedure that uses a thin, flexible tube with a light and camera to look inside the body.endo- within-scopy looking with an instrumentFull entry and function: cystoscopy and ureteroscopy let the urologist see the lining and take biopsies, brushings and bladder washings for cytologysy-TOL-uh-jeeThe study of cells, or a lab test that looks at cells under a microscope.cyt/o cell-logy study ofFull entry . Urodynamic studies measure the bladder's pressures as it fills and empties.
4Diseases the surgeon treats
These are the urinary and male reproductive diseases the Core Curriculum lists. Each one points to the operation that treats it later in the chapter.
Kidney
| Disease | What it is |
|---|---|
| Kidney cancer | Renal cell carcinomakar-sih-NOH-muhA cancer that starts in the cells that line the skin or the inside and outside surfaces of organs.carcin/o cancer-oma tumorFull entry is the most common kidney cancer in adults, more than 9 in 10 of them in one review's figures; smoking is its strongest risk factor, and the same review reports that over half are found by chance on imaging. Treated by nephrectomy. |
| Wilms tumorVILMZ TOO-merA cancer of the kidney that develops in young children.Full entry (nephroblastoma) | The most common kidney cancer of children, usually found between ages 2 and 5; taught with pediatric genitourinaryjen-ih-toh-YOOR-ih-nair-eeRelating to the genital (reproductive) organs and the urinary organs together.genit/o reproductive organsurin/o urine-ary relating toFull entry surgery below. |
| glomerulonephritisgloh-mair-yoo-loh-neh-FRY-tisInflammation of the glomeruli, the tiny filtering units of the kidneys.glomerul/o glomerulusnephr/o kidney-itis inflammationFull entry | A general name for inflammation of the glomerulusgloh-MAIR-yuh-lusA tiny ball of capillaries in the kidney that filters the blood as the first step in making urine.Full entry , from infection or an autoimmune diseaseaw-toh-ih-MYOON dih-ZEEZA disease in which the immune system attacks the body's own healthy tissue.auto- selfimmune protectedFull entry . |
| Hydronephrosis | A swollen renal pelvis and ureterYOOR-uh-terOne of the two tubes that carry urine from the kidneys down to the bladder.Full entry that loses function because urine is backed up behind a blockage, such as a strictureSTRIK-cherA narrowed section of a hollow body passage, such as the urethra, esophagus or bowel, that is tighter than normal.Full entry , stone or tumor. |
| Nephrosclerosis | Hardening of the small arteries of the kidney, caused by high blood pressure and atherosclerosisath-er-oh-skluh-ROH-sisA buildup of fatty deposits (plaque) inside the walls of the arteries.ather/o fatty pastescler/o hard-osis conditionFull entry . |
| Polycystic kidney disease | An inherited disease: cysts full of fluid grow in the kidneys and crowd out the working tissue. |
| pyelonephritispy-uh-loh-nuh-FRY-tisA bacterial infection of the kidney, usually spread up from the bladder.pyel/o renal pelvisnephr/o kidney-itis inflammationFull entry | A bacterial infection of the kidney, usually a urinary tract infection that has climbed up the ureter. |
| Renal calculi | Stones formed when minerals and salts settle out of filtrate that holds more than it can dissolve (below). |
| renal failureREE-nul FAYL-yerLoss of the kidneys' ability to filter waste and extra fluid from the blood.ren kidney-al relating toFull entry | Kidneys that no longer clear the blood. end-stage renal diseaseEND-stayj REE-nul dih-ZEEZThe last stage of chronic kidney disease, when the kidneys have lost almost all of their function for good.ren/o kidney-al relating toFull entry cannot be reversed; diabetes and high blood pressure are common causes. Treated by dialysisdy-AL-ih-sisA treatment that removes wastes and extra fluid from the blood when the kidneys can no longer do it.dia- through, apart-lysis separation, looseningFull entry or a transplant. |
| Kidney trauma | Usually a blow to the flank or back, as in contact sports or violence. |
Bladder and lower tract
| Disease | What it is |
|---|---|
| Bladder cancer | The most common urinary tract cancer, usually from the transitional cells of the lining (urothelium); it recurrencerih-KER-ensThe return of a disease or symptom after a period when it had gone away.re- againcur run-ence state ofFull entry more often than almost any other cancer. hematuriahee-muh-TOOR-ee-uhBlood in the urine, either seen by eye or found only by a test.hemat/o bloodur/o urine-ia conditionFull entry is the usual first sign. |
| Bladder calculi | Stones in the bladder, often behind a blockage such as an enlarged prostatePROS-taytA walnut-sized gland below the bladder in males that surrounds the urethra and makes part of the fluid in semen.Full entry or a foreign body. |
| cystitissis-TY-tisInflammation of the urinary bladder.cyst/o bladder, sac-itis inflammationFull entry and urinary tract infection | Infection of the bladder and lower tract, commonly from Escherichia coliesh-uh-RIK-ee-uh KOH-lyeA rod-shaped bacterium that normally lives in the human intestine, some strains of which cause infection.Full entry at the end of the urethrayoo-REE-thruhThe tube that carries urine from the bladder out of the body.Full entry ; chronic infection can scar the urethra. |
| Neurogenic bladder | Loss of bladder function from nerve damage, such as a spinal cord injurySPY-nul KORD IN-juh-reeDamage to the spinal cord that disrupts signals between the brain and the body below the injury.Full entry , stroke or brain lesionLEE-zhunAn area of tissue that has been damaged or has changed from normal, such as a sore, wound, lump or spot.Full entry . |
| urinary retentionYUR-ih-nair-ee rih-TEN-shunBeing unable to empty the bladder completely, or at all.Full entry | Being unable to empty the bladder. |
| urinary incontinenceYOOR-ih-nair-ee in-KON-tih-nunsLeaking of urine that a person cannot control.Full entry | Loss of urine control, most often from a weak sphincterSFINGK-terA ring of muscle that tightens to close an opening or passage in the body and relaxes to open it.Full entry at the bladder neck after childbirth or with age; an enlarged prostate can cause it too. |
| Urinary reflux | Urine flowing backward, up toward the kidney. |
| Bladder trauma | Most often from a vehicle crash with a pelvic fracture. |
Male reproductive organs
| Disease | What it is |
|---|---|
| benign prostatic hyperplasiabee-NINE proh-STAT-ik hy-per-PLAY-zhuhA prostate gland that has grown larger than normal, from growth that is not cancer.hyper- more than normalplas growth or formation-ia conditionFull entry (BPH), also called benign prostatic hyperplasia | Benign growth of the prostate with age, which squeezes the urethra and causes voiding problems, retention, reflux and infection. Treated by transurethral resection of the prostatetrans-yoo-REE-thrul rih-SEK-shun of the PROS-taytSurgery that removes part of the prostate gland with an instrument passed up through the urethra.trans- throughurethr/o urethra-al relating toresection cutting outFull entry or prostatectomy. |
| prostate cancerPROS-tayt KAN-serCancer that starts in the prostate, the gland below the bladder in males that helps make semen.Full entry | Usually an adenocarcinoma, often slow-growing and silent until late; the most often diagnosed cancer in males. |
| prostatitispros-tuh-TY-tisInflammation of the prostate gland.prostat/o prostate-itis inflammationFull entry | Inflammation or infection of the prostate. |
| Testicular cancer | The most common solid cancer in males aged 15 to 35, usually from the germ cells; it usually shows as a painless lump or swelling. |
| Testicular torsion | The testis twists on its cord and loses its blood supply, which can kill it within hours: an emergency. |
| cryptorchidismkrip-TOR-kih-diz-umA condition in which one or both testicles have not moved down into the scrotum.crypt/o hiddenorch/o testis-ism conditionFull entry | A testis that never came down into the scrotumSKROH-tumThe pouch of skin and muscle that holds the testicles.Full entry ; left alone, it can cause infertilityin-fer-TIL-ih-teeNot being able to become pregnant after a year of regular sex without birth control, or after six months for women over 35.Full entry . |
| Hydrocele | Fluid collecting in the tunica vaginalis around the testis. |
| Spermatocele | A fluid-filled cyst of the epididymisep-ih-DID-ih-misA coiled tube on the back of each testis where sperm mature and are stored.epi- upondidym testis (twin)Full entry or cord. |
| Varicocele | Swollen, widened veins of the testis (the pampiniform plexusPLEK-susA network of nerves or blood vessels that branch and join together.Full entry ). |
| Epididymitis and orchitis | Inflammation of the epididymis or of the testis, often from infection. |
| Balanoposthitis | Inflammation of the glans and foreskin, often from infection. |
| Phimosis and paraphimosis | In phimosis the foreskin is too tight to pull back over the glans; in paraphimosis it is pulled back and cannot return. |
| hypospadiashy-poh-SPAY-dee-usA birth defect in which the opening of the urethra is on the underside of the penis instead of at the tip.hypo- below-spadias a tear, an openingFull entry and epispadiasep-ih-SPAY-dee-usA birth defect in which the urethra opens on the top side of the penis instead of at the tip, or in a female, too far forward.epi- upon, above-spadias an opening (from a Greek word for tearing)Full entry | Birth defects in which the urethra opens on the underside of the penis (hypospadias) or on its top (epispadias). |
| Penile cancer | Rare in Western countries; one reference reports that about 30 percent are linked to human papillomavirusHYOO-mun pap-ih-LOH-muh-vy-rusA common group of viruses spread by close skin-to-skin contact, most often during sex.Full entry (HPV). |
| erectile dysfunctionih-REK-tile dis-FUNK-shunRepeated trouble getting or keeping an erection firm enough for sex.dys- difficult, abnormalfunction workingFull entry | Being unable to get or keep an erection, from nerve or blood vessel disease, diabetes or psychological causes. |
The adrenal glanduh-DREE-nul GLANDOne of two small glands that sit on top of the kidneys and make hormones such as cortisol, aldosterone and epinephrine.ad- toward, nearren/o kidney-al relating toFull entry 's diseases that lead to surgery, such as tumors and the overactivityoh-ver-ak-TIV-ih-teeMore activity than normal, in a person, an organ or a body system.Full entry glands of Cushing syndromeKUSH-ing SIN-drohmA condition caused by too much cortisol in the body over a long time.Full entry , are listed with the adrenalectomy below; chapter 9 explains the hormones.
5Kidney failure and dialysis
When the kidneys fail, toxinTOK-sinA poison made by a living thing, such as a bacterium, plant or animal.Full entry from the body's own chemistry build up quickly. dialysisdy-AL-ih-sisA treatment that removes wastes and extra fluid from the blood when the kidneys can no longer do it.dia- through, apart-lysis separation, looseningFull entry takes over the kidney's cleaning job until a transplant, or for life. People on dialysis live with a hard schedule and a shortage of donor kidneys, and they may feel hopeless: they need your patience.
- Hemodialysis: blood runs through a machine, given heparinHEP-uh-rinAn anticoagulant drug, given by injection or IV, that keeps blood clots from forming or growing.Full entry so it does not clot, where membranes and a dialyzing solution filter it before it returns to the body. A session takes about 3 hours, three or four times a week.
- Vascular access: an arteriovenous fistulaar-teer-ee-oh-VEE-nus FIS-chuh-luhA connection made by surgery between an artery and a vein, usually in the arm, to give access for hemodialysis.arteri/o arteryven/o vein-ous relating tofistula an abnormal passage between two body partsFull entry (AV fistula, or AV shuntSHUNTA passage that moves blood or other fluid from one place to another, either made by a surgeon or present in the body.Full entry ) joins an artery, usually the radial, to a vein, or a graftGRAFTTissue or a man-made material moved into place in surgery to replace or repair a damaged part.Full entry is placed between them, so the dialysis needles have a strong, lasting vessel to use. A working fistulaFIS-choo-luhAn abnormal passage between two organs or vessels, or between an organ and the skin.Full entry has a buzz you can feel (a thrillTHRILA buzzing or vibrating feeling felt with the fingertips over a blood vessel or the heart.Full entry ) and a rushing sound you can hear (a bruitbroo-EEA whooshing or blowing sound heard with a stethoscope over a blood vessel.Full entry ). Patients guard the access closely and take care to keep it from any injury. Chapter 40 teaches the operation.
- peritoneal dialysispair-ih-toh-NEE-ul dy-AL-ih-sisA kind of dialysis that uses the lining of the abdomen as a filter, with fluid run in and out through a catheter.peritone/o peritoneum-al relating todia- through, apart-lysis loosening, separatingFull entry : dialysatedy-AL-ih-sateThe fluid used in dialysis to pull waste products and extra fluid out of the blood.dia- through-lysis loosening, breaking apartFull entry runs through a soft tube placed in the abdomen, stays for hours while the peritoneumpair-ih-toh-NEE-umThe thin membrane that lines the belly cavity and covers most of the organs inside it.peri- aroundton stretched-eum a structureFull entry acts as the filter, and is drained out. The patient can do it at home.

6Positions, prep and drape
Chapter 31 teaches each position, its padding and the prep steps. Urology uses nearly all the positions, often pushed further than usual to reach the organ; these are its own uses.
- lithotomylih-THOT-uh-meeA position lying on the back with the hips and knees bent and the legs raised and spread apart, often in stirrups.lith/o stone-tomy cutting intoFull entry for every transurethral case: the buttocks right at the edge of the lower break, so the table does not block the scope, and boot stirrups, with the foot pulses checked. The head of the table may tilt up slightly so the prep solution drains into the collecting pan; pooled under the patient, it irritates the skin and can burnBURNAn injury to the skin or deeper tissues caused by heat, chemicals, electricity, radiation or friction.Full entry it if the electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry is used.
- Lateral (flank or kidney) position for open kidney surgery: operative side up, the flank over the table's middle break or kidney rest, the table flexed to widen the flank and straightened before the wound is closed; a vacuum positioner (beanbag) can hold the patient. The lower lung and the vena cavaVEE-nuh KAY-vuhOne of the two large veins that return oxygen-poor blood from the body to the right atrium of the heart.Full entry can be squeezed. A laparoscopiclap-uh-roh-SKOP-ikDone through a few small cuts in the abdomen with a thin camera and long instruments, instead of one large opening.lapar/o abdomen-scopic viewingFull entry or robotic kidney case uses a modified lateral position through the abdomen.
- Prone or modified prone for a percutaneous nephrolithotomy, the operative side raised on a foam wedge; the patient is put to sleep on the stretcher, then turned.
- Supine for open bladder and prostatePROS-taytA walnut-sized gland below the bladder in males that surrounds the urethra and makes part of the fluid in semen.Full entry surgery, usually with a bolster under the pelvis and sometimes with the head tilted down so the bowel falls away from the pelvis, and for scrotumSKROH-tumThe pouch of skin and muscle that holds the testicles.Full entry and penile cases and the kidney transplant. Low lithotomy with steep Trendelenburg positiontren-DEL-en-burg puh-ZISH-unA position in which the client lies on the back with the bed tilted so the head is lower than the feet.Full entry , the arms tucked, is the robotic prostatectomy's; exaggerated lithotomy, which strains the back, hips and sacrumSAY-krumThe large, triangle-shaped bone at the base of the spine, between the two hip bones.sacr/o sacrumFull entry , the rare perinealper-ih-NEE-ulHaving to do with the perineum, the area between the genitals and the anus.Full entry prostatectomy's.
- Prep: povidone-iodinePOH-vih-done EYE-uh-dineA brown antiseptic solution of iodine used to kill germs on the skin before procedures and on wounds.Full entry or chlorhexidine on the perineumpair-ih-NEE-umThe area of skin and muscle between the genitals and the anus.perine/o perineumFull entry and genitals, never an alcohol prep, which injures the genitals. In a female patient, the strokes go downward and a sponge that touches the vagina or anus is thrown away, so germs are not carried from the rectum to the urethrayoo-REE-thruhThe tube that carries urine from the bladder out of the body.Full entry . A flank prep runs from the axilla to the thigh, front and back; a robotic prostatectomy's from mid-chest to mid-thigh, with the perineum.
- Drapes: transurethral cases use a lithotomy drape with leggings and a built-in screen and fluid pouch, which has ports to drain the irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry away. For a transurethral resection of the prostatetrans-yoo-REE-thrul rih-SEK-shun of the PROS-taytSurgery that removes part of the prostate gland with an instrument passed up through the urethra.trans- throughurethr/o urethra-al relating toresection cutting outFull entry , some surgeons add a drape with a rectalREK-tulRelating to the rectum, the last part of the large intestine; also, given or measured through the rectum.rect/o rectum, straight-al relating toFull entry sheathSHEETHA covering that wraps around a structure; in procedures, a short hollow tube left in a blood vessel to pass catheters through.Full entry , which lets a finger in the rectum lift the prostate during the resectionrih-SEK-shunSurgery to remove part of an organ or tissue.re- back, againsect to cut-ion processFull entry . Open cases use a flank or laparotomylap-uh-ROT-uh-meeSurgery that opens the abdomen through a large cut to reach the organs inside.lapar/o abdomen-tomy cutting intoFull entry drape.
- fluoroscopyfloo-ROS-kuh-peeAn x-ray method that shows moving pictures of the inside of the body in real time.fluor/o glowing (from the fluorescent screen)-scopy looking, viewingFull entry : many stone and ureterYOOR-uh-terOne of the two tubes that carry urine from the kidneys down to the bladder.Full entry cases use a C-arm, on a table X-rays pass through. Keep body parts that need no imaging out of the beam, and shield the thyroid and chest with lead whenever the shield will not spoil the image; in urology the reproductive organs generally cannot be shielded. Chapter 22 teaches radiationray-dee-AY-shunEnergy that travels as waves or particles, such as X-rays, used to make images or treat cancer; also pain that spreads from its starting point.radi/o rays, radiation-ation processFull entry safety.
- Before the case: the patient usually voids just before coming to the OR; the time and amount are recorded, so the urine left in the bladder can be judged. For an awake cystoscopy, the urethra is numbed with 1% or 2% viscous lidocaineLY-doh-kaynA local anesthetic that numbs an area, also given by IV to treat some fast, abnormal heart rhythms.Full entry , held in a male patient with a penile clamp. local anestheticLOH-kul an-es-THET-ikA drug that blocks feeling in one part of the body without making the person unconscious.Full entry with epinephrineep-ih-NEF-rinA hormone and drug, also called adrenaline, that raises heart rate and blood pressure and opens the airways.Full entry is avoided or used with great care on the scrotum, testes and penis, because these end organs can lose their blood supply.
7Scopes and their parts
Much of urology happens through a scope. Know the parts by name, assemble them ahead of time, and hand them over ready to go.
The French scale
Catheters, sheathSHEETHA covering that wraps around a structure; in procedures, a short hollow tube left in a blood vessel to pass catheters through.Full entry , sounds and scopes are sized on the French (Fr) scale. Each French unit is about a third of a millimeter of diameter, so 3 Fr is about 1 mm, and a 24 Fr sheath is about 8 mm across. The bigger the number, the wider the tube.
Cystoscope
The rigid cystoscope (cystourethroscope) is a stainless steel set of four parts:
- Sheath: the hollow tube that goes into the bladder and carries the irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry in and out. Diagnostic sheaths are about 15 to 17 Fr; working sheaths go up to about 28 Fr for larger instruments.
- obturatorOB-too-ray-terA smooth-tipped rod that fits inside a tube, such as a tracheostomy tube or cannula, to guide it in and then is taken out.Full entry : a smooth, round-tipped rod that fills the sheath while it is passed, so its edge does not injure the urethrayoo-REE-thruhThe tube that carries urine from the bladder out of the body.Full entry . A visual obturator lets the surgeon watch through a telescope while passing it.
- Telescope (lens): carries the light and the image. Telescopes are made with viewing angles from 0 degrees, straight ahead, to 120 degrees, looking backward; a 30-degree and a 70-degree lens are the usual pair.
- Bridge: joins the telescope to the sheath and has one or two working channels for wires, catheters and stentstentA small tube, often of metal mesh, placed inside a vessel or duct to hold it open.Full entry . An Albarrán bridge has a lever that bends the tip of a catheter or wire to steer it into a ureterYOOR-uh-terOne of the two tubes that carry urine from the kidneys down to the bladder.Full entry opening.



The flexible cystoscope is more comfortable and less traumatic to the urethra and can be used with a local anestheticLOH-kul an-es-THET-ikA drug that blocks feeling in one part of the body without making the person unconscious.Full entry , even at the bedside, or for a patient who cannot lie in lithotomylih-THOT-uh-meeA position lying on the back with the hips and knees bent and the legs raised and spread apart, often in stirrups.lith/o stone-tomy cutting intoFull entry . Its channels are smaller, so it does less work. A digital flexible scope has its camera chip and light built into the tip, so it needs no separate camera or light cord.
Resectoscope
The resectoscope cuts and coagulationkoh-ag-yuh-LAY-shunThe process by which blood changes from a liquid into a gel, forming a clot.coagul clot-ation processFull entry tissue piece by piece through the urethra, for a transurethral resection of the prostatetrans-yoo-REE-thrul rih-SEK-shun of the PROS-taytSurgery that removes part of the prostate gland with an instrument passed up through the urethra.trans- throughurethr/o urethra-al relating toresection cutting outFull entry or a bladder tumor. Adult resectoscopes are about 24 to 28 Fr. The parts are the sheath and its obturator, the working (operating) element, which slides a cutting loop back and forth, a foroblique telescope, and the electrodes: cutting loops and a roller ball for coagulation. A continuous-flow resectoscope has an inner inflow channel and an outer outflowOWT-flohThe flow of a fluid out of an organ, space or vessel.Full entry channel connected to suction, so the surgeon does not have to stop to empty the bladder. Monopolar resectoscopes need a fluid without electrolytes; bipolarby-POH-lerHaving two poles or two opposite ends; most often used as a short form of bipolar disorder.bi- twopolar having polesFull entry ones work in saline.



Ureteroscopes
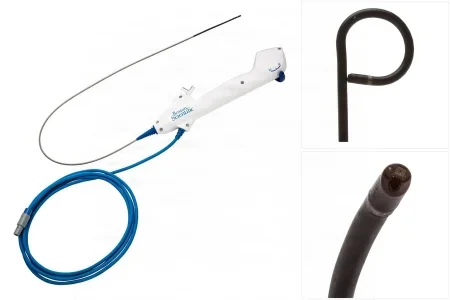
A ureteroscope goes up through the bladder into the ureter and the renal pelvis. The semirigid ureteroscope looks much like a rigid scope and is sturdier than a flexible one, has channels for irrigation and instruments, and is used to pass stents and to stretch the lower ureter; small ones are under 7.5 Fr. The flexible ureteroscope, about 6.9 to 9 Fr, has a tip that bends into the calyces of the kidney. Surgeons often use both in one case.

Nephroscope
The nephroscope enters the kidney through a tract in the flank. The rigid one, about 24 Fr, has an offset eyepiece, angled 45 or 90 degrees, and its channel takes lithotripter probes, graspers, baskets, stents and catheters. A flexible nephroscope reaches the upper calyces the rigid one cannot see.

Your job with the scopes
- Assemble and check the rigid scope before the surgeon needs it, and keep the setup in clear view and neatly organized.
- Guide instruments, wires and catheters into the scope's channels, and keep their far ends on the sterile fieldSTAIR-ul feeldAn area set up with sterile drapes and supplies, kept free of all germs, for a sterile procedure.Full entry . Receive each one as it comes out so it does not bend or kink.
- Lensed instruments are fragile and costly: handle them as little as possible, on their own trays. Chapter 27 teaches their cleaning.
- Darken the room for a clear picture on the monitor, but leave enough light for people to move safely.
8Irrigation and distention fluid
Fluid runs into the bladder all through a transurethral case. It stretches the bladder open so the surgeon can see the lining, and it washes away blood and bits of tissue. It comes in 1 L and 3 L sealed plastic bags with closed tubing, run by a pump or by gravity; Y tubing lets two bags hang together so the flow never stops. The fluid runs out again through the scope into the drape's pouch and on to a waste system.
Choosing the fluid
Chapter 21 teaches why the fluid must suit the energy device: a fluid with electrolytes, such as saline, spreads monopolar current, so the loop cannot cut. In urology:
- Sterile water: a diagnostic cystoscopy, a retrograde pyelogram, a simple fulguration and often a TURBT, a short resectionrih-SEK-shunSurgery to remove part of an organ or tissue.re- back, againsect to cut-ion processFull entry that opens few vessels, where loose cancer cells swell and burst in water instead of implanting.
- Glycine 1.5% or sorbitol 3%: a monopolar transurethral resection of the prostatetrans-yoo-REE-thrul rih-SEK-shun of the PROS-taytSurgery that removes part of the prostate gland with an instrument passed up through the urethra.trans- throughurethr/o urethra-al relating toresection cutting outFull entry . They carry no electrolytes, and they are near enough to the blood's concentration not to burst red cells; 3 to 5 L hang in tandem.
- Normal saline: a bipolarby-POH-lerHaving two poles or two opposite ends; most often used as a short form of bipolar disorder.bi- twopolar having polesFull entry resection, the holmium laser and most ureteroscopy, where it is the safe choice if fluid leaks out of a torn ureterYOOR-uh-terOne of the two tubes that carry urine from the kidneys down to the bladder.Full entry .
run sterile water during a TURP. The prostatePROS-taytA walnut-sized gland below the bladder in males that surrounds the urethra and makes part of the fluid in semen.Full entry 's veins are open, and water drawn into the blood bursts the red cells (hemolysishee-MOL-ih-sisThe breaking apart of red blood cells, which releases hemoglobin into the blood.hem/o blood-lysis breaking downFull entry ), which can damage the kidneys.
Warm the fluid to body temperature, 37°C, and no warmer, as chapter 21 teaches: cold fluid can chill the patient and cause bladder spasmSPAZ-umA sudden, involuntary tightening of a muscle or of the muscle in a hollow organ or tube.Full entry , and warmed fluid may slow clottingKLOT-ingThe process by which blood thickens into a gel to plug a damaged vessel and stop bleeding; also called coagulation.Full entry . Check the warmer often, confirm the surgeon's order for the type and temperature, keep the bags full and note every bag used.
AST's 2019 normothermia guideline warms irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry to 33 to 40°C as the fluid's maker allows, and one reference's care plan keeps it below 40.5°C (105°F).
When fluid gets into the blood
During a TURP the resection opens the veins of the prostate, and some of the irrigation is absorptionub-ZORP-shunThe taking in of a substance, such as a drug or a nutrient, into the bloodstream.Full entry into the bloodstream. Absorbed glycine or sorbitol dilutes the blood's sodium, causing hyponatremiahy-poh-nuh-TREE-mee-uhA blood sodium level below normal, under 135 mEq/L.hypo- belownatr sodium (from its Latin name, natrium)-emia in the bloodFull entry . Severe low sodium from absorbed irrigation is called TURP (or TUR) syndrome.
- Early signs, best seen in an awake patient under spinal anesthesiaan-us-THEE-zhuhLoss of feeling or sensation, often brought on by drugs so that surgery or a procedure can be done without pain.an- withoutesthesi/o feeling, sensation-ia conditionFull entry : restlessness, apprehension, irritability, confusion, nausea and vomiting, a slow pulse and rising blood pressure.
- Late signs: seizureSEE-zherA sudden burst of abnormal electrical activity in the brain that changes movement, feeling, behavior or awareness.Full entry , comaKOH-muhA deep state of unconsciousness in which a person cannot be woken and does not respond with purpose.Full entry , blindness, heart rhythm problems, fluid in the lungs and heart failurehart FAYL-yerA long-term condition in which the heart cannot pump enough blood to meet the body's needs.Full entry . Glycine also breaks down into ammoniauh-MOH-nyuhA waste product of protein breakdown that the liver normally changes into urea; its blood level is measured in a lab test.Full entry , which can cloud the brain further.
- Prevention: the irrigation runs at as low a pressure as possible, the bladder is emptied before it is full, minimal IV fluid is given, and the urine output is watched. A bipolar resection in saline all but removes the risk. A TURP can take from 30 minutes to 3 hours, depending on the size of the gland. If absorption is suspected, a serum sodium is sent from the OR, and the anesthesia provideran-us-THEE-zhuh pruh-VY-derThe licensed professional who gives anesthesia and watches over the client's breathing and vital functions during a procedure.Full entry may give furosemidefyoo-ROH-suh-mideA loop diuretic: a drug that makes the kidneys remove more salt and water from the body.Full entry to clear the extra fluid.
Track the fluid going in and coming out, and the difference, the fluid deficit, all through the case. Record the volumes, and tell the surgeon and the anesthesia provider when the deficit reaches the limits chapter 21 gives.
A bladder that has been torn shows itself differently: fluid escapes into the tissues around it, the lower abdomen becomes rigid and swollen, and the patient's breathing and comfort change. The procedure stops, and an X-ray of the bladder (a cystogram) is taken. A catheter is usually all it needs; a large tear is closed through an incision.
Getting rid of the fluid
Urology uses a lot of fluid, and the cysto room is built for it. A waste system may pipe the fluid straight from the drape to a filtering and suction unit, with no canisters and no contact between staff and waste; or a disposable pouch on the end of the table drains by gravity into the facility's drain.
9Catheters, stents and other GU supplies
Urology uses a great many catheters, wires and tubes, and most come sterile and disposable in peel packs. Read the label: type, tip, French size and length. Chapter 25 teaches drains in general and chapter 31 placing a urinary catheter; here are the urology supplies the Core Curriculum lists.
Urethral catheters
- indwelling urinary catheterin-DWEL-ing YUR-ih-nair-ee KATH-uh-terA tube passed through the urethra into the bladder and left in place to drain urine into a bag.Full entry (two-way): the usual retention catheter, with one channel to drain urine and one to fill its balloon with sterile water. A catheter left in place to drain continuously, in the urethrayoo-REE-thruhThe tube that carries urine from the bladder out of the body.Full entry or the ureterYOOR-uh-terOne of the two tubes that carry urine from the kidneys down to the bladder.Full entry , is called indwellingIN-dwel-ingPlaced inside the body and left there for a period of time.Full entry .
- Three-way Foley: a third channel runs irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry into the bladder or instills a drug. Its large balloon, 30 or 75 mL, acts as a tamponade after prostatePROS-taytA walnut-sized gland below the bladder in males that surrounds the urethra and makes part of the fluid in semen.Full entry surgery: filled and pulled gently down against the bladder neck, it presses on the bleeding prostate bed. It must sit in the bladder, never inflated inside the empty prostate cavity, where it would make the bleeding worse. A hematuriahee-muh-TOOR-ee-uhBlood in the urine, either seen by eye or found only by a test.hemat/o bloodur/o urine-ia conditionFull entry catheter, for heavy clottingKLOT-ingThe process by which blood thickens into a gel to plug a damaged vessel and stop bleeding; also called coagulation.Full entry , is a three-way Foley reinforceree-in-FORSTo repeat and support teaching or care that has already been started, so the client remembers and follows it.Full entry with a spiral wire, so its channel does not collapse under vigorous irrigation.
- Coudé: a bent tip that gets through the urethra past an enlarged prostate or another narrowing. An olive tip eases insertion in a male.
- Straight (Robinson or red rubber): no balloon; drains the bladder once.
- Whistle tip: an elongated opening at the tip, for drainage or for instilling contrastKON-trastA dye or other substance given before an imaging test so body parts show up more clearly.Full entry .
- Materials: catheters are made of latexLAY-teksNatural rubber made from the sap of the rubber tree, used in some gloves, catheters and other medical supplies.Full entry , premature ventricular contractionpree-muh-CHOOR ven-TRIK-yuh-ler kun-TRAK-shunAn extra heartbeat that starts early from a ventricle instead of from the heart's normal pacemaker.Full entry or silicone; a patient allergic to latex gets silicone.
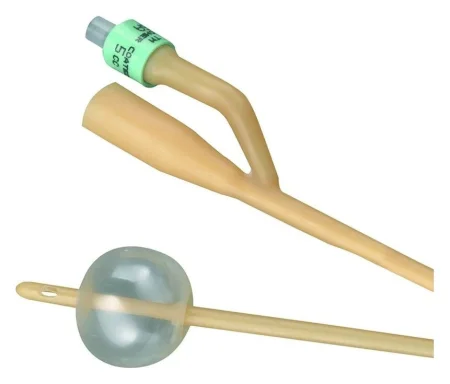
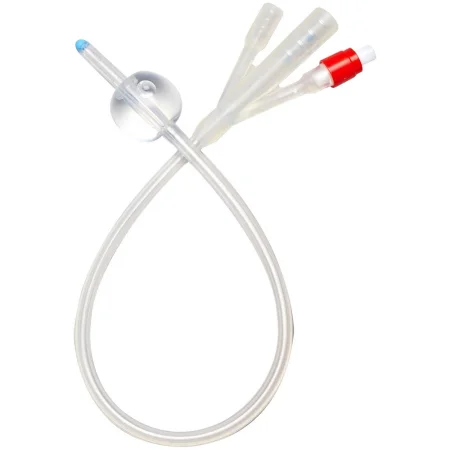
the Foley balloon is filled with sterile water, never air or saline, in the amount the maker's instructions give and never less, and the surgeon decides the volume of a large tamponade balloon after prostate surgery. One reference describes filling a prostate surgery catheter's balloon with saline: use sterile water.
Suprapubic catheters
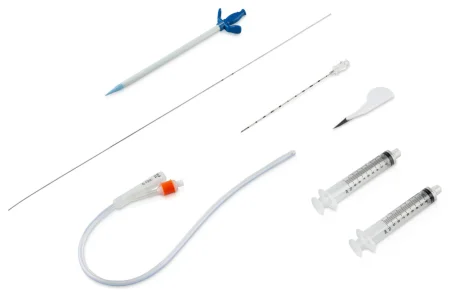
A suprapubic catheter drains the bladder through the lower abdominal wall instead of the urethra. The Pezzer (mushroom) catheter has a mushroom-shaped tip that keeps it in place; the four-winged Malecot is used the same way and as a nephrostomy tube to drain the kidney. A Foley often does either job.

Ureteral catheters
Ureteral catheters are thin, marked with graduations so the surgeon knows how far up the ureter they are, and come with different tips: open-ended, whistle, round, olive, spiral and cone (acorn or bulb). A cone tip plugs the ureteral opening so contrast can be injected for a retrograde study. They are used for retrograde pyelograms, to drain a blocked kidney, and to mark the ureters during pelvic or bowel surgery so the surgeon can find and protect them. An adapter connects an indwelling one to a drainage bag.

Ureteral stents
A stentstentA small tube, often of metal mesh, placed inside a vessel or duct to hold it open.Full entry is a supportive tube left in a duct so fluid can pass while it heals. A ureteral stent keeps the ureter open past a stone, tumor or narrowing, drains a kidney swollen behind a blockage, and splints the ureter after it is repaired. It is an emergency when both ureters are blocked or the blocked kidney is infected.
- The double-J (double-pigtail) stent has a curl at each end. It is threaded over a guidewire, straight, and when the wire comes out the ends curl in the renal pelvis and in the bladder, so it cannot slip up or down. A pusher slides it into place.
- Stents run from about 3 to 8.5 Fr and are made of polyurethane and other polymers or metal, often coated to slide in easily and resist crusting and germs.
- Many have a string that comes out through the meatusmee-AY-tusAn opening or passage in the body, such as the urinary opening or the ear canal.Full entry , so the stent can be pulled out later without another cystoscopy; otherwise a scope is used. A stent left in too long can become infected, blocked or crusted, so its removal is scheduled.

Guidewires, sheaths and dilators
- Guidewires are the rails of ureteral surgery. Passed under fluoroscopyfloo-ROS-kuh-peeAn x-ray method that shows moving pictures of the inside of the body in real time.fluor/o glowing (from the fluorescent screen)-scopy looking, viewingFull entry , they let stents, catheters and scopes slide precisely into place over them. They are steel or nitinol, plain or coated. A hydrophilic "glide" wire is very slippery: it slips past a stone or tight spot, and once access is gained it is often swapped for a stiffer working wire. A second safety wire is often left beside the working wire to keep the way open if something goes wrong. When asked, keep slight tension on the wire, and keep its far end on the sterile fieldSTAIR-ul feeldAn area set up with sterile drapes and supplies, kept free of all germs, for a sterile procedure.Full entry .
- sheathSHEETHA covering that wraps around a structure; in procedures, a short hollow tube left in a blood vessel to pass catheters through.Full entry : an introducer sheath or a ureteral access sheath gives instruments a smooth path up the ureter; telescoping dilatorDY-lay-terAn instrument used to stretch or widen an opening, canal or passage in the body.Full entry sheaths widen a tract into the kidney.
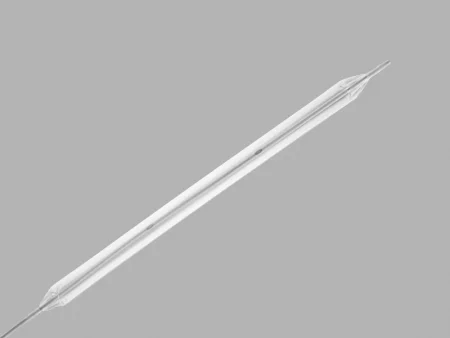
- Ureteral dilators: a balloon dilator, inflated with a pressure syringe, stretches a narrowing; graduated solid dilators widen the ureter step by step.
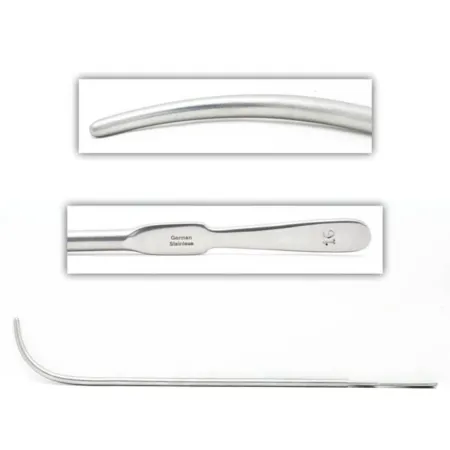
- Urethral dilators: metal sounds such as the Van Buren, Otis or LeFort stretch the male urethra. They are sized in even French numbers and laid out on the back table from smallest to largest. A filiform, a very fine soft-tipped guide, is passed first through a tight strictureSTRIK-cherA narrowed section of a hollow body passage, such as the urethra, esophagus or bowel, that is tighter than normal.Full entry , and graduated followers are screwed onto it one after another. A female urethra is dilated with short straight metal dilators or hollow McCarthy dilators.


For stones and specimens
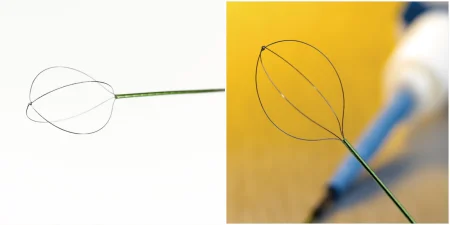
- Stone baskets: a wire basket, often nitinol, passes closed through the scope, opens beyond the stone, and closes around it to draw it out.
- Graspers and biopsy forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry : cup forceps and brushes take tissue; swish a brush in saline in its container to free the cells.
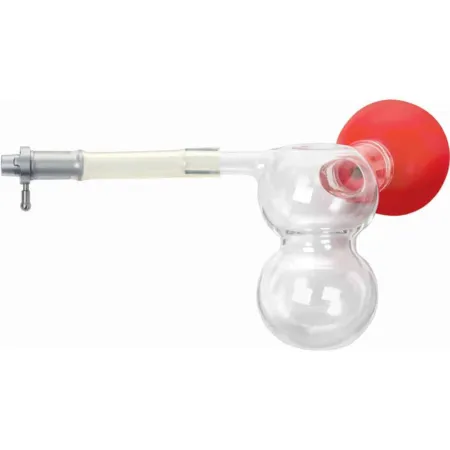
- Ellik evacuator: an evacuator that fits onto the resectoscope sheath once the working element is out. Squeezing its bulb and letting go rinses the bladder in and out and washes the chips of tissue and the clots out of it. A Toomey syringe does the same job. Every chip goes to pathologypuh-THOL-uh-jeeThe study of disease and its causes and effects, or the disease changes found in a person or tissue.path/o disease-logy study ofFull entry .
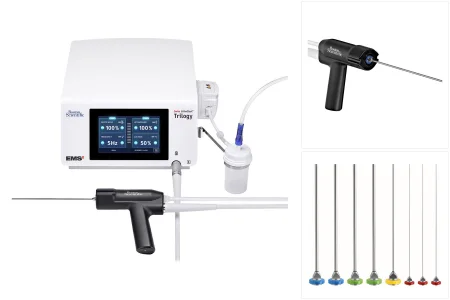
- Laser fibers and lithotripters: chapter 20 teaches lasers. The holmium laser, through a thin fiber, breaks up stones and treats tumors; ultrasonic, electrohydraulic and pneumatic lithotripters break stones too. The fiber tip must stick out at least 1 cm beyond the end of the scope and be in view before the laser fires.

Implants
Penile prosthesispros-THEE-sisAn artificial body part that replaces one that is missing or does not work, such as an artificial leg, joint, eye or heart valve.Full entry , the incontinencein-KON-tih-nensLoss of control over the bladder or bowel, so urine or stool leaks out without the person meaning it to.in- notcontin/o to hold back-ence state ofFull entry devices (artificial urinary sphincterSFINGK-terA ring of muscle that tightens to close an opening or passage in the body and relaxes to open it.Full entry and slings) and testicular implants are implants, and many are measured and ordered ahead. Confirm the type and size with the surgeon before you open one, handle it as little as possible, and keep lint off its surface. Each is taught with its operation.
Open instruments
Open urology uses a general or laparotomylap-uh-ROT-uh-meeSurgery that opens the abdomen through a large cut to reach the organs inside.lapar/o abdomen-tomy cutting intoFull entry set with specialty instruments added:
- Atraumatic clamps such as the Babcock for the delicate ureter, and right-angle and Schnidt (tonsilTON-sulOne of the masses of lymph tissue at the back of the throat that help fight germs entering the mouth and nose.Full entry ) clamps to clamp vessels and dissectdy-SEKT, or dih-SEKTTo cut apart or separate tissues carefully during surgery.Full entry bluntly; vessel loops to lift vessels and the ureter.
- For the kidney, pediclePED-ih-kulA narrow stem or stalk that attaches a structure, such as a tumor or a skin flap, to the body.Full entry clamps with angled jaws that reach behind the pedicle, vascular clamps for the renal vessels, kidney stoneKID-nee STOHNA hard, pebble-like lump of minerals that forms inside the kidney.Full entry forceps, fine-tipped needle holders and vascular forceps.
- For the bladder and prostate, bladder retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry , prostate retractors and grasping clamps, and long right-angle clamps.
- For the genitals, a minor plastic set with fine scissors, forceps and hemostatHEE-moe-statA clamp with finger rings and a locking ratchet used in surgery to grasp and close off bleeding vessels.hem/o blood-stat stopping, standing stillFull entry ; Allis and Babcock clamps hold the tissue layers well. Vasectomy repair and penile reconstruction need microsurgical instruments.


10Medications on the urology field
Chapter 12 teaches these drugs as drugs; here is what reaches the urology field. Label every drug and solution, track how much irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry goes in, and report the totals at the end of the case.
- Irrigation fluids, above, are drugs too: glycine is used with caution in liver diseaseLIV-er dih-ZEEZAny condition that damages the liver or keeps it from working normally.hepat/o liverFull entry , and sorbitol can raise the blood sugar of a patient with diabetes.
- local anestheticLOH-kul an-es-THET-ikA drug that blocks feeling in one part of the body without making the person unconscious.Full entry : lidocaineLY-doh-kaynA local anesthetic that numbs an area, also given by IV to treat some fast, abnormal heart rhythms.Full entry gel or viscous lidocaine for an awake cystoscopy; local anesthetic without epinephrineep-ih-NEF-rinA hormone and drug, also called adrenaline, that raises heart rate and blood pressure and opens the airways.Full entry , or with it only with great care, on the penis, scrotumSKROH-tumThe pouch of skin and muscle that holds the testicles.Full entry and testes, such as a penile block with bupivacainebyoo-PIV-uh-kaynA long-acting local anesthetic used to numb an area, block nerves, or give epidural and spinal anesthesia.Full entry after a circumcisionsur-kum-SIZH-unSurgery to remove the foreskin, the skin that covers the tip of the penis.Full entry or 2% lidocaine for a vasectomy.
- contrastKON-trastA dye or other substance given before an imaging test so body parts show up more clearly.Full entry and dye: contrast for retrograde pyelograms, ureteroscopy and PCNL, injected through a catheter or added to the irrigation; indigo carmine, given by vein, turns the urine blue so the surgeon can see it come from the ureterYOOR-uh-terOne of the two tubes that carry urine from the kidneys down to the bladder.Full entry openings or spot a leak.
- Kidney surgery and transplant: mannitolMAN-ih-tolAn osmotic diuretic, given by IV, that draws water out of tissues into the blood so the kidneys can remove it.Full entry and furosemidefyoo-ROH-suh-mideA loop diuretic: a drug that makes the kidneys remove more salt and water from the body.Full entry keep the urine flowing; heparinHEP-uh-rinAn anticoagulant drug, given by injection or IV, that keeps blood clots from forming or growing.Full entry goes to the donor before the kidney's vessels are clamped, and heparin solution rinses the vessels at a transplant.
- Antibiotics: a preventive dose within an hour before the incision; antibiotic irrigation for implants; antibiotic saline in the bladder at a transplant.
- Into the bladder: antineoplastican-tee-nee-oh-PLAS-tikA drug used to treat cancer by killing cancer cells or stopping them from growing and dividing.anti- againstneo- newplas growth, formation-tic relating toFull entry such as mitomycin C, or BCGbee-see-JEE (said as letters)Bacille Calmette-Guérin: a live, weakened bacterium used as a tuberculosis vaccine and as a bladder cancer treatment.Full entry , after a bladder tumor resectionrih-SEK-shunSurgery to remove part of an organ or tissue.re- back, againsect to cut-ion processFull entry .
- Others: hemostatichee-moh-STAT-ikStopping bleeding; also, a product or agent used to stop bleeding.hem/o blood-stasis stopping, standing still-ic relating toFull entry for the raw surface of a partial nephrectomy or the prostatePROS-taytA walnut-sized gland below the bladder in males that surrounds the urethra and makes part of the fluid in semen.Full entry bed; papaverine, injected into the erectile tissue to cause an artificial erection, which at a penile implant helps the surgeon judge the size; phenylephrinefen-il-EF-rinA drug that tightens blood vessels, given IV to raise low blood pressure and used in nose sprays and eye drops.Full entry for priapism, an erection that will not go down.
11Cystoscopy and the ureter
Diagnostic cystoscopy
What and why: a cystoscopy looks inside the urethrayoo-REE-thruhThe tube that carries urine from the bladder out of the body.Full entry , the bladder and the ureterYOOR-uh-terOne of the two tubes that carry urine from the kidneys down to the bladder.Full entry openings; in a male it also shows the verumontanum, the bladder neck and the lobes of the prostatePROS-taytA walnut-sized gland below the bladder in males that surrounds the urethra and makes part of the fluid in semen.Full entry . It finds the cause of hematuriahee-muh-TOOR-ee-uhBlood in the urine, either seen by eye or found only by a test.hemat/o bloodur/o urine-ia conditionFull entry , retention, infections, incontinencein-KON-tih-nensLoss of control over the bladder or bowel, so urine or stool leaks out without the person meaning it to.in- notcontin/o to hold back-ence state ofFull entry , fistulaFIS-choo-luhAn abnormal passage between two organs or vessels, or between an organ and the skin.Full entry and bladder stones, looks for cancer of the bladder or urethra, keeps watch on a cancer of the upper tract's lining, and removes small stones and foreign bodies. It is done alone, often under local anestheticLOH-kul an-es-THET-ikA drug that blocks feeling in one part of the body without making the person unconscious.Full entry or none, and it opens every transurethral case. A blue light cystoscopy, after a dye has sat in the bladder for an hour, makes tumors that ordinary light misses glow pink.
Before surgery: lithotomylih-THOT-uh-meeA position lying on the back with the hips and knees bent and the legs raised and spread apart, often in stirrups.lith/o stone-tomy cutting intoFull entry ; a perinealper-ih-NEE-ulHaving to do with the perineum, the area between the genitals and the anus.Full entry prep; a cystoscopy drape pack. Have the patient's imaging in the room. Setup: the cystoscope sheathSHEETHA covering that wraps around a structure; in procedures, a short hollow tube left in a blood vessel to pass catheters through.Full entry and obturatorOB-too-ray-terA smooth-tipped rod that fits inside a tube, such as a tracheostomy tube or cannula, to guide it in and then is taken out.Full entry , a bridge, 30- and 70-degree telescopes, a light cord, irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry tubing with sterile water, a stopcock and water-soluble lubricant. Keep ready: specimen tubes, a measuring container for the urine left in the bladder, an Albarrán bridge, ureteral catheters, 10- and 20-mL syringes, contrastKON-trastA dye or other substance given before an imaging test so body parts show up more clearly.Full entry , labels, an electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry with its pad and a Bugbee electrode.
Key steps:
- The urethra is numbed with anesthetican-us-THET-ikA drug that causes loss of feeling, with or without loss of consciousness.an- withoutesthesi/o feeling, sensation-ic relating toFull entry gel if the patient is awake, and dilated with sounds or filiforms if it is tight.
- The lubricated sheath goes in with its obturator. The obturator comes out, the bladder drains, and the leftover urine is measured and may be saved for culture.
- The irrigation is connected and the telescope locked in. The surgeon fills the bladder and controls the flow with the stopcock, then looks over the urethra and bladder in a set order.
- Biopsies are taken with cup forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry or brushes, and the bladder may be washed with saline to collect cells for cytologysy-TOL-uh-jeeThe study of cells, or a lab test that looks at cells under a microscope.cyt/o cell-logy study ofFull entry . Each sample goes in its own labeled container.
- A small lesionLEE-zhunAn area of tissue that has been damaged or has changed from normal, such as a sore, wound, lump or spot.Full entry may be burned (fulgurated) with a Bugbee electrode. The scope comes out and the bladder is drained.
Your role: guide the instruments into the scope and keep their far ends sterile; take them back without kinking; swish a cytology brush in saline to free the cells.
Wound class: II. No incision is made, but the urinary tract is entered under control; one textbook also allows Class I.
Retrograde pyelogram
What and why: an X-ray of the ureter and renal pelvis, filled with contrast from below during a cystoscopy. It shows stones, tumors, narrowings and leaks of the upper tract, and is often added to a bladder tumor resectionrih-SEK-shunSurgery to remove part of an organ or tissue.re- back, againsect to cut-ion processFull entry to check the upper tract for lesions.
Key steps: through the cystoscope and an Albarrán bridge, the surgeon passes a ureteral catheter into the ureteral opening; a cone-tipped catheter plugs the opening. Contrast is injected and the whole upper tract is watched under fluoroscopyfloo-ROS-kuh-peeAn x-ray method that shows moving pictures of the inside of the body in real time.fluor/o glowing (from the fluorescent screen)-scopy looking, viewingFull entry . Chapter 12 teaches contrast as a drug, and chapter 22 radiationray-dee-AY-shunEnergy that travels as waves or particles, such as X-rays, used to make images or treat cancer; also pain that spreads from its starting point.radi/o rays, radiation-ation processFull entry safety.
Wound class: II, as for cystoscopy.
Ureteroscopy, stone baskets and laser
What and why: a ureteroscope passed up through the bladder looks inside the ureter and renal pelvis. It finds the cause of blood in the urine, a blockage or a filling defect on imaging, takes biopsies of tumors there, treats narrowings, and breaks up and removes stones.
Before surgery: lithotomy, on a table X-rays can pass through, with a C-arm. Setup: the cystoscopy setup plus semirigid and flexible ureteroscopes, guidewires, ureteral dilatorDY-lay-terAn instrument used to stretch or widen an opening, canal or passage in the body.Full entry and balloon dilators, stone baskets of 3 to 5 Fr, graspers, biopsy forceps, catheters, stentstentA small tube, often of metal mesh, placed inside a vessel or duct to hold it open.Full entry , a three-way stopcock, 20- and 50-mL syringes, contrast and, as needed, the holmium laser. Saline is the irrigant unless electrosurgery is used, often under a pressure bag to give a clear view.
Key steps:
- Under fluoroscopy, the surgeon passes a guidewire up the ureter, irrigating as it goes; you keep slight tension on the wire when asked. A second, safety wire is placed.
- The ureter may be dilated with a balloon or graduated dilators, and the ureteroscope rides up over the working wire.
- The surgeon inspects the ureter and renal pelvis and biopsies anything suspicious.
- A small stone is caught in a basket and drawn out. A larger one is broken up first (lithotripsy) and the pieces removed with graspers, a basket and irrigation. The energy may be ultrasound through a probe, an electrohydraulic spark, a pneumatic "jackhammer" or the holmium laser, with every laser precautionprih-KAW-shunA step taken ahead of time to prevent harm, such as the infection-control practices used with every client.Full entry in place (chapter 20); the fiber tip sits at least 1 cm past the scope and in view before firing. These methods have replaced open surgery for removing stones.
- The ureter is checked for a tear, and a stent is placed over the safety wire.
Specimens: stones go to the lab dry, in a dry container, never in saline or formalinFOR-muh-linA solution of formaldehyde in water used to preserve tissue specimens for the pathology lab.Full entry , so their chemistry can be analyzed. Biopsies and urine for cytology go in their own containers.
Wound class: II.
After surgery: most go home the same day and are back at work in about a week. The stent comes out on a set date, because a stent left too long can block, crust or become infected. Complications include bleeding, a later narrowing of the ureter, a tear (perforationper-fuh-RAY-shunA hole that goes all the way through the wall of an organ or tissue.per- throughforat bored (a hole)-ion processFull entry ), a stone that cannot be retrieved and, rarely, the ureter torn away from the kidney (avulsion).
Stent placement and balloon dilation
A stent goes in through a cystoscope or ureteroscope: a guidewire is placed under fluoroscopy, the stent slides over it, pushed by a stent pusher, and the wire is pulled so the stent's ends curl. Placing a stent is urgent when both ureters are blocked or a blocked kidney is infected. A cystoscopy with a stent counts as an operative case.
A narrowed ureter may be stretched with a balloon dilator: the balloon is passed over a guidewire into the narrow segment under fluoroscopy and filled with a pressure syringe.
Wound class: II.
12Stones
How stones form
Stones form when the urine holds more of certain salts than it can dissolve, so crystals settle out and clump together. Their jagged crystals cause severe pain and nausea. Most small stones pass on their own, but a stone stuck in the upper tract can block urine flow and cause anuriaan-YOOR-ee-uhMaking little or no urine: less than about 50 to 100 mL in 24 hours in an adult.an- without-uria urineFull entry , a kidney abscessAB-sesA closed pocket of pus in tissue, walled off by the body.Full entry and sepsisSEP-sisA severe whole-body response to an infection that damages the body's own organs.Full entry , so it can be an emergency. Stones rarely start in the bladder.
There are four main kinds:
- Calcium oxalate or calcium phosphate: the most common.
- uric acidYUR-ik AS-idA waste product made when the body breaks down purines, measured with a blood test.Full entry : forms when the urine is too acidic.
- Struvite (magnesiummag-NEE-zee-umA mineral in the blood that the nerves, muscles and heart need, measured with a blood test.Full entry ammonium phosphate): linked to some urinary infections.
- Cystine: from an inherited disorder.
A stone tends to stick where the ureterYOOR-uh-terOne of the two tubes that carry urine from the kidneys down to the bladder.Full entry narrows: where it leaves the kidney (the UPJ), where it crosses the iliacIL-ee-akHaving to do with the ilium, the large, wing-shaped upper part of the hip bone.Full entry vessels, and where it enters the bladder (the UVJ). A staghorn stone is a large, branching stone that fills the renal pelvis and calyces. A plain computed tomographykum-PYOO-tid toh-MOG-ruh-feeAn imaging test that uses x-rays and a computer to make cross-section pictures of the inside of the body.tom/o cut, slice-graphy process of recordingFull entry without contrastKON-trastA dye or other substance given before an imaging test so body parts show up more clearly.Full entry is the usual way to find stones, and a KUB just before surgery confirms where the stone sits.
a stone goes to the lab dry, in a dry container, with nothing added. Saline or formalinFOR-muh-linA solution of formaldehyde in water used to preserve tissue specimens for the pathology lab.Full entry can change it, and the lab needs its chemistry to prevent the next one.
Shock wave lithotripsy (ESWL)
What and why: extracorporeal shockshokA life-threatening state in which blood flow is too low to bring enough oxygen to the body's tissues.Full entry wave lithotripsy breaks a stone with shock waves sent from outside the body, with no incision. It suits stones under about 2 cm, works less well on cystine and calcium oxalate stones, and the machine has a weight limit, about 300 pounds (135 kg). The patient lies against a water-filled cushion, and fluoroscopyfloo-ROS-kuh-peeAn x-ray method that shows moving pictures of the inside of the body in real time.fluor/o glowing (from the fluorescent screen)-scopy looking, viewingFull entry aims the shock waves at the stone and checks the pieces at intervalIN-ter-vulThe time or space between two events, such as between two contractions in labor or between two waves on an ECG.Full entry . A session runs about 30 minutes to 2 hours. Each pulse makes a loud pop, so the patient and the team may wear earplugs. Newer machines need only sedationsih-DAY-shunA calm, relaxed or sleepy state brought on by drugs, or the use of drugs to cause it.sed calm, settle-ation processFull entry .
A stentstentA small tube, often of metal mesh, placed inside a vessel or duct to hold it open.Full entry may be placed first, especially for a stone 1.5 cm or larger, so the fragments can drain. hematuriahee-muh-TOOR-ee-uhBlood in the urine, either seen by eye or found only by a test.hemat/o bloodur/o urine-ia conditionFull entry is expected and clears in a day or two; a bruise or blood collection around the kidney is a less common problem. ESWL is often combined with ureteroscopy or PCNL when the gravel does not pass.
Wound class: none for the shock waves themselves, which make no incision; the wound classes sort operative wounds. A stent placed first is a cystoscopic case, Class II.
Percutaneous nephrolithotomy (PCNL)
What and why: the surgeon reaches the kidney through a tract made in the flank and removes or breaks up the stones through a nephroscope. It is chosen for very large stones, more than about 2.5 cm, such as a staghorn stone; when other treatment has failed; when the patient is over the ESWL weight limit; when a ureteroscope cannot reach the stone; and for an infected stone, because the infected material can be removed at the same time.
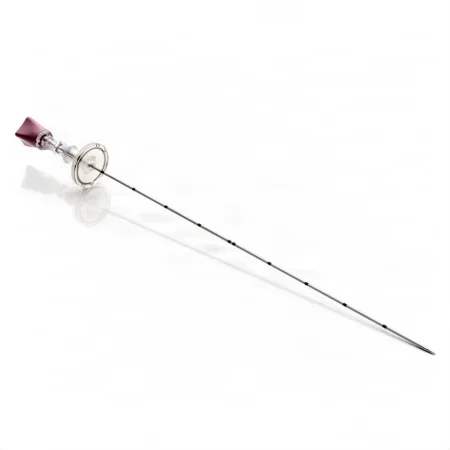
Before surgery: a ureteral catheter is placed by cystoscopy first, and an occlusionuh-KLOO-zhunA blockage or closing off of a passage, such as a blood vessel, tube or IV line.Full entry balloon catheter may block the top of the ureter so fragments cannot wash down it. The patient is anesthetized on the stretcher, then turned prone or modified prone onto the table, with the operative side raised; prep and drape for the flank. Setup: rigid and flexible nephroscopes, an 18-gauge access needle, guidewires (including a stiff Amplatz wire), fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry and coaxial dilatorDY-lay-terAn instrument used to stretch or widen an opening, canal or passage in the body.Full entry or a balloon dilator with its sheathSHEETHA covering that wraps around a structure; in procedures, a short hollow tube left in a blood vessel to pass catheters through.Full entry , an ultrasonic lithotripter, stone graspers, a nitinol basket, stents, contrast, and a nephrostomy tube. Watch the patient's temperature, and be ready for sudden heavy bleeding.
Key steps:
- Under fluoroscopy, the surgeon passes the access needle with its sheath into a calyx and injects contrast to confirm the spot.
- A slippery wire goes into the renal pelvis and is swapped for a stiff working wire; a second, safety wire keeps the way open.
- The tract is widened with dilators, and a working sheath is left in it.
- Through the nephroscope, the stones are broken with an ultrasonic probe, the holmium laser or a pneumatic lithotripter, and the pieces are removed with graspers, a basket or irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry . The flexible scope checks the upper calyces, and contrast shows any pieces left.
- A nephrostomy tube (Malecot, Pezzer or loop) is placed over the wire and stitched to the skin.
Wound class: II; if infected material is found, it is an infection already present, Class IV.
Open stone removal
Scopes and shock waves have largely replaced open stone surgery, but you may still meet it. A ureteropyelithotomy, the Core Curriculum's name for removing a stone from the ureter and renal pelvis, is now usually done from inside with a ureteroscope, as above; done open, it follows the steps below.
- Pyelolithotomy removes a stone from the renal pelvis. With the patient lateral on the kidney rests and prepped from the axilla to mid-thigh, the surgeon makes a flank incision, removing the 12th rib if needed. A vessel loop around the upper ureter stops the stone from slipping down it. The renal pelvis is opened over the stone between two tractionTRAK-shunA steady pulling force applied to a body part with weights, ropes and pulleys.Full entry sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry , the stone is lifted out with stone forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry , the pelvis is irrigated to flush out small pieces, and it is closed with fine absorbable suture over a drain. Urine may leak from the wound for a few days.
- Ureterolithotomy removes a stone through a cut in the ureter: Babcock clamps or vessel loops hold the stone still, Randall forceps lift it out, a catheter flushed up and down proves the ureter is open, and fine absorbable sutures close it.
- Wound class: II, because the urinary tract is opened.
13Kidney operations
Nephrectomy
What and why: a nephrectomy removes a kidney. Reasons include a tumor, severe hydronephrosis or blockage, stones with infection, an abscessAB-sesA closed pocket of pus in tissue, walled off by the body.Full entry , injury, and a kidney given by a living donor.
- Simple nephrectomy: the kidney alone.
- Radical nephrectomy: for cancer, the kidney with its fat, the adrenal glanduh-DREE-nul GLANDOne of two small glands that sit on top of the kidneys and make hormones such as cortisol, aldosterone and epinephrine.ad- toward, nearren/o kidney-al relating toFull entry , Gerota fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry and the nearby lymph nodelimf nohdA small, bean-shaped organ of the immune system that filters lymph fluid and holds white blood cells.Full entry , all in one piece. The surgeon ties the pediclePED-ih-kulA narrow stem or stalk that attaches a structure, such as a tumor or a skin flap, to the body.Full entry before handling the kidney, so tumor cells are not squeezed into the blood, and never opens Gerota fascia.
- Partial nephrectomy: only a tumor with a rim of normal kidney, saving the rest, as is done for a small tumor or a patient with one kidney.
- Nephroureterectomy: the kidney, the whole ureterYOOR-uh-terOne of the two tubes that carry urine from the kidneys down to the bladder.Full entry and a small cuff of bladder, for tumors of the lining of the collecting system and ureter.
Approach: most nephrectomies are now laparoscopiclap-uh-roh-SKOP-ikDone through a few small cuts in the abdomen with a thin camera and long instruments, instead of one large opening.lapar/o abdomen-scopic viewingFull entry or robotic, through the abdomen, with the patient in a modified lateral position. The open operation goes through the flank, often removing the 11th or 12th rib, or through the abdomen; a large upper tumor may need a thoracoabdominal incision that opens the chest.
an open flank incision with the patient fully lateral, as several references still teach step by step for a simple nephrectomy.
Before surgery: a indwelling urinary catheterin-DWEL-ing YUR-ih-nair-ee KATH-uh-terA tube passed through the urethra into the bladder and left in place to drain urine into a bag.Full entry goes in before positioning. For the open flank approach, the patient lies lateral with the flank over the kidney rest and the table flexed, held with a safety strap or beanbag; the prep runs from the axilla to the thigh, front and back. Setup: a laparotomylap-uh-ROT-uh-meeSurgery that opens the abdomen through a large cut to reach the organs inside.lapar/o abdomen-tomy cutting intoFull entry set with kidney instruments (long instruments, pedicle clamps with angled jaws that reach around the pedicle, Satinsky and bulldog vascular clamps, vascular forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry , clips), a self-retaining retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry , vessel loops, hemostatichee-moh-STAT-ikStopping bleeding; also, a product or agent used to stop bleeding.hem/o blood-stasis stopping, standing still-ic relating toFull entry , rib instruments if a rib comes out, and chest drainage if the chest is opened.
Key steps (open):
- A flank incision just above the 12th rib through the muscles; a rib may be removed.
- Gerota fascia is opened and the kidney freed from its fat and from the adrenal gland, spleenspleenAn organ in the upper left abdomen that filters the blood and helps fight infection.splen/o spleenFull entry , pancreasPAN-kree-usA long, flat gland behind the stomach that makes digestive enzymes and the hormones insulin and glucagon.pan- allcreas fleshFull entry or liver. Save any perirenal fat in a small basin of saline: the surgeon may use it as a bolster.
- The ureter is found, often slung in a narrow Penrose drain, then clamped, divided and tied.
- The renal artery is clamped, divided and tied first, then the vein; each is tied more than once. Pass the pedicle clamps in pairs.
- The kidney comes out into a basin. The fossaFOS-uhA shallow hollow or dip in a bone or on the body's surface.Full entry is irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry and checked for bleeding, the table is straightened, a drain is placed, and the wound is closed in layers.
Laparoscopic and robotic: through several ports, the colon is moved aside, the ureter is found and lifted, and the renal artery and vein are cleared all the way around and divided between clips. The ureter is clipped and cut, the kidney goes into a retrieval bag and out through a port site, and the fascia at the larger ports is closed. An open setup stays in the room in case the case must convert.
Partial nephrectomy: the surgeon marks a margin of about 0.5 to 1 cm around the tumor, sometimes with ultrasound to see its depth. mannitolMAN-ih-tolAn osmotic diuretic, given by IV, that draws water out of tissues into the blood so the kidneys can remove it.Full entry is given and the hilum clamped, for no more than about 30 minutes; longer, and the kidney is cooled with ice slush to protect it. The tumor is cut out, any opening into the collecting system is sewn shut, and bolsters and a hemostatic agent help stop the bleeding before the clamp comes off.
Specimen: the kidney or tumor, sent as the surgeon orders; a cancer specimen keeps its fat and fascia intact for the pathologist.
Wound class: dividing the ureter or opening the collecting system enters the urinary tract under control, which meets Class II; one textbook lists a nephrectomy as Class I.
After surgery: the patient goes to PACU or the ICU. Pain from a flank incision can make breathing shallow, so oxygen levels are watched, and a chest tubechest toobA tube placed through the chest wall into the space around the lung to drain air, blood or fluid.Full entry is placed when the chest was opened. Bleeding and infection are the main risks. At home, the patient walks, avoids lifting anything heavier than about a gallon of milk, and calls for a fever, hematuriahee-muh-TOOR-ee-uhBlood in the urine, either seen by eye or found only by a test.hemat/o bloodur/o urine-ia conditionFull entry or a catheter that stops draining.
Kidney transplant
What and why: a kidney from a living or a deceased donor is placed in the recipient's iliacIL-ee-akHaving to do with the ilium, the large, wing-shaped upper part of the hip bone.Full entry fossa, low in the pelvis and outside the peritoneumpair-ih-toh-NEE-umThe thin membrane that lines the belly cavity and covers most of the organs inside it.peri- aroundton stretched-eum a structureFull entry , to treat end-stage renal diseaseEND-stayj REE-nul dih-ZEEZThe last stage of chronic kidney disease, when the kidneys have lost almost all of their function for good.ren/o kidney-al relating toFull entry . The patient's own kidneys usually stay, unless they cause trouble such as repeated infection, stones or severe reflux. The donor and the recipient must match in blood typeBLUD typeThe group a person's blood belongs to, based on markers on the red blood cells: A, B, AB or O, and Rh positive or negative.Full entry (ABO) and tissue type (HLA), with a negative type and crossmatchTYPE and KROS-machBlood tests done before a transfusion to find a person's blood type and check that donor blood will not react with it.Full entry ; the Rh factorar-AYCH FAK-terA protein that may be present on the surface of red blood cells; people who have it are Rh-positive and those without it are Rh-negative.Full entry does not have to match. Chapter 18 teaches organ donation.
Patients are screened carefully. A transplant may be ruled out by cancer that has spread, infection that cannot be cleared, serious heart or blood vessel disease that cannot be treated, or repeated failure to follow medical treatment. Every source of infection, such as the teeth, the bladder, the sinusSY-nusA hollow space in the body, most often one of the air-filled spaces in the skull bones around the nose.Full entry and the skin, is treated first.
The living donor: a relative, a friend or an altruistic stranger. Two rooms side by side are prepared, and the donor and recipient operations run at the same time. The left kidney is usually taken, because its vein is longer. The donor nephrectomy is open or hand-assisted laparoscopic, with extra care for the length of the ureter, artery and vein. heparinHEP-uh-rinAn anticoagulant drug, given by injection or IV, that keeps blood clots from forming or growing.Full entry and mannitol are given before the vessels are clamped. The time without blood flow (warm ischemiais-KEE-mee-uhToo little blood flow to a part of the body, so the tissue does not get enough oxygen.isch- hold back-emia blood conditionFull entry time) is kept as short as possible: the kidney goes straight into iced saline on a sterile back table, is flushed with cold preservation solution through its artery, and is carried, covered, to the recipient's room.
Before surgery (recipient): supine; a Foley catheter, through which the bladder is rinsed several times with antibiotic saline, then left filled and clamped until the ureter is connected; a prep from the nipples down. Setup: a major laparotomy set, a vascular set, fine vascular suction tips, long instruments, clamp shods (bumpers), vessel loops, sterile ice and a separate sterile setup to prepare the kidney.
Key steps (recipient):
- A curved or straight incision low on one side of the abdomen (a lower quadrant incision); one reference describes a midlineMID-lineAn imaginary line down the center of the body; also, a type of IV catheter placed in a vein of the upper arm.Full entry incision. The surgeon stays behind the peritoneum and places a self-retaining retractor.
- The iliac artery and vein are freed and looped, and the lymphLIMFThe clear fluid that flows through the lymphatic vessels and carries white blood cells.Full entry vessels over them are tied and divided.
- On its own sterile setup, the donor kidney, wrapped in a moist lap in an ice basin, has its vessels trimmed and is flushed with heparinized solution.
- A side-biting clamp goes on the iliac vein, and the renal vein is sewn end to side to it with fine polypropylene. The renal artery is then joined to the iliac artery. A hole punch may shape the opening in the artery. The vessels are flushed with heparinized saline before the last stitches.
- The clamps come off, and the kidney's surface and hilum are checked for bleeding and for any part without blood flow. diureticdy-yoo-RET-ikA drug that makes the kidneys pass more water and salt out of the body as urine.dia- throughur/o urine-etic relating toFull entry may be given.
- The ureter is tunneled into the bladder and sewn to its lining (ureteroneocystostomy) over a stentstentA small tube, often of metal mesh, placed inside a vessel or duct to hold it open.Full entry .
- Drains are placed and the wound is closed in layers.
Wound class: the bladder and ureter are opened under control, which meets Class II.
After surgery: the patient is watched closely for rejection, bleeding and infection, and a urine meter on the Foley measures the output. Some ureteral stents come out through the urethrayoo-REE-thruhThe tube that carries urine from the bladder out of the body.Full entry in a day or two; others are removed by cystoscopy 4 to 6 weeks later.
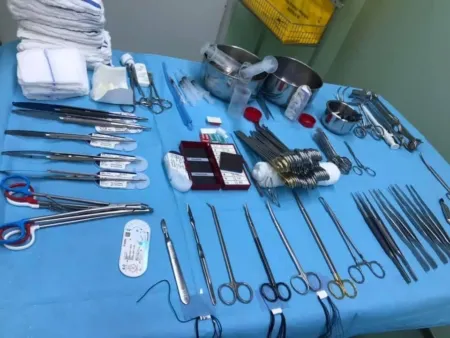
Recovery from a deceased donor is taught in chapter 18; the recovery team usually takes both kidneys together, with segments of the aorta and vena cavaVEE-nuh KAY-vuhOne of the two large veins that return oxygen-poor blood from the body to the right atrium of the heart.Full entry , and flushes them cold at once.
14Adrenalectomy
What and why: an adrenalectomy removes one or both adrenal glanduh-DREE-nul GLANDOne of two small glands that sit on top of the kidneys and make hormones such as cortisol, aldosterone and epinephrine.ad- toward, nearren/o kidney-al relating toFull entry , or part of one, for a gland that makes too much hormone, such as in Cushing syndromeKUSH-ing SIN-drohmA condition caused by too much cortisol in the body over a long time.Full entry or aldosteronism, for a tumor of the gland, or to remove hormones that feed some cancers. Chapter 9 teaches the hormones.
A pheochromocytoma, a tumor of the adrenal medullauh-DREE-nul meh-DUL-uhThe inner part of each adrenal gland, which releases epinephrine and norepinephrine.medulla inner part (Latin for marrow)Full entry , floods the blood with stress hormones when it is handled. The blood pressure can spike, with a fast pulse, so the surgeon ties the adrenaluh-DREE-nulHaving to do with the adrenal glands, the two small glands that sit on top of the kidneys.ad- nearren/o kidney-al relating toFull entry vein early, before handling the gland. Once the tumor is out, the blood pressure and the blood sugar can fall, so the anesthesia provideran-us-THEE-zhuh pruh-VY-derThe licensed professional who gives anesthesia and watches over the client's breathing and vital functions during a procedure.Full entry is ready with drugs that raise the pressure (vasopressorvay-zoh-PRES-erA drug that narrows the blood vessels to raise the blood pressure.Full entry ), and the patient is watched closely in the ICU.
Approach: the operation may be laparoscopiclap-uh-roh-SKOP-ikDone through a few small cuts in the abdomen with a thin camera and long instruments, instead of one large opening.lapar/o abdomen-scopic viewingFull entry or open; the laparoscopic one generally means fewer complications and a shorter hospital stay. For one gland, the patient lies on the side or on the back, depending on the approach; for both glands, on the back or face down. For an approach through the back, the patient lies face down in a jackknife position of about 35 degrees, with the kidney rest under the lower edge of the front of the rib cage. Open approaches go through the flank or the back, often over the 11th or 12th rib, or through the abdomen.
Setup: a laparoscopylap-uh-ROS-kuh-peeSurgery or an exam done through small cuts in the belly, using a thin, lighted tube with a camera.lapar/o abdomen-scopy looking with an instrumentFull entry set with a fan retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry for the liver, spleenspleenAn organ in the upper left abdomen that filters the blood and helps fight infection.splen/o spleenFull entry or pancreasPAN-kree-usA long, flat gland behind the stomach that makes digestive enzymes and the hormones insulin and glucagon.pan- allcreas fleshFull entry , clip appliers, a specimen bag and, for an open case, kidney and rib instruments and vascular instruments.
Key steps (laparoscopic, behind the peritoneumpair-ih-toh-NEE-umThe thin membrane that lines the belly cavity and covers most of the organs inside it.peri- aroundton stretched-eum a structureFull entry ):
- A small incision near the tip of the 12th rib; a balloon dissector opens a space behind Gerota fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry , and the other ports are placed along the rib margin.
- Gerota fascia is opened near the kidney, and the adrenal arteries are clipped and divided.
- The adrenal vein is clipped and divided. On the right it is short and drains straight into the vena cavaVEE-nuh KAY-vuhOne of the two large veins that return oxygen-poor blood from the body to the right atrium of the heart.Full entry , so it is handled with great care; on the left it drains into the left renal vein.
- The gland is freed and removed in a specimen bag, and the ports are closed.
Wound class: I, because no tract is entered.
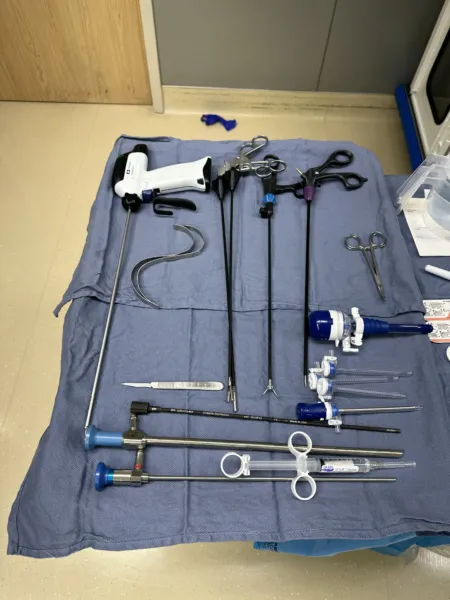
15Bladder operations
Transurethral resection of a bladder tumor (TURBT)
What and why: a TURBT removes a bladder tumor through the urethrayoo-REE-thruhThe tube that carries urine from the bladder out of the body.Full entry with a resectoscope. It is the first step in diagnosing and stagingSTAY-jingWorking out how large a cancer is and how far it has spread in the body.Full entry a bladder cancer, and it treats tumors that have not grown deep into the wall. The surgeon also takes a piece of the muscle under the tumor, so the pathologist can tell whether the cancer has invaded it, and may take biopsies of normal-looking lining to look for flat cancer cells (carcinomakar-sih-NOH-muhA cancer that starts in the cells that line the skin or the inside and outside surfaces of organs.carcin/o cancer-oma tumorFull entry in situ). A tumor deep in the muscle needs a partial or total cystectomy.
Before surgery: lithotomylih-THOT-uh-meeA position lying on the back with the hips and knees bent and the legs raised and spread apart, often in stirrups.lith/o stone-tomy cutting intoFull entry , a perinealper-ih-NEE-ulHaving to do with the perineum, the area between the genitals and the anus.Full entry prep and lithotomy drapes, under general, spinal or regional anesthesiaan-us-THEE-zhuhLoss of feeling or sensation, often brought on by drugs so that surgery or a procedure can be done without pain.an- withoutesthesi/o feeling, sensation-ia conditionFull entry . Setup: the transurethral resection of the prostatetrans-yoo-REE-thrul rih-SEK-shun of the PROS-taytSurgery that removes part of the prostate gland with an instrument passed up through the urethra.trans- throughurethr/o urethra-al relating toresection cutting outFull entry setup below: a resectoscope with its sheathSHEETHA covering that wraps around a structure; in procedures, a short hollow tube left in a blood vessel to pass catheters through.Full entry , obturatorOB-too-ray-terA smooth-tipped rod that fits inside a tube, such as a tracheostomy tube or cannula, to guide it in and then is taken out.Full entry , working element, telescope and cutting loops, an Ellik evacuator, cup biopsy forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry , a Bugbee electrode, specimen containers and a indwelling urinary catheterin-DWEL-ing YUR-ih-nair-ee KATH-uh-terA tube passed through the urethra into the bladder and left in place to drain urine into a bag.Full entry . The irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry must suit the energy; sterile water is often used, as above. A retrograde pyelogram may be added to check the upper tract.
Key steps:
- A full cystoscopy maps the bladder first.
- The tumor is shaved away in slices with the cutting loop; a very small one may just be taken with cup forceps.
- The chips are washed out with the Ellik evacuator or a Toomey syringe and caught for pathologypuh-THOL-uh-jeeThe study of disease and its causes and effects, or the disease changes found in a person or tissue.path/o disease-logy study ofFull entry .
- A final deep piece may be cut "cold," without current, and sent separately, to show whether the muscle is involved.
- Bleeding points are sealed with a Bugbee electrode, the instruments come out and a catheter drains the bladder.
Specimens: keep every chip. The tumor chips and the separate deep piece go in their own labeled containers, as the surgeon names them.
Medications: low-risk tumors that have not reached the muscle may later be treated by putting antineoplastican-tee-nee-oh-PLAS-tikA drug used to treat cancer by killing cancer cells or stopping them from growing and dividing.anti- againstneo- newplas growth, formation-tic relating toFull entry drugs, such as mitomycin C, into the bladder; high-risk ones by putting in BCGbee-see-JEE (said as letters)Bacille Calmette-Guérin: a live, weakened bacterium used as a tuberculosis vaccine and as a bladder cancer treatment.Full entry (bacille Calmette-Guérin), which strengthens the body's immune reaction to the cancer.
Wound class: II, because the urinary tract is entered; one textbook also allows Class I.
After surgery: bleeding, infection and injury to the urethra are the main risks. Bladder cancer often comes back in other parts of the bladder, even after the tumor is fully removed, and the stage of the tumor decides whether radiationray-dee-AY-shunEnergy that travels as waves or particles, such as X-rays, used to make images or treat cancer; also pain that spreads from its starting point.radi/o rays, radiation-ation processFull entry or chemotherapy follows.
Suprapubic cystostomy
What and why: a cystotomy is an opening into the bladder through a low abdominal incision; a cystostomy leaves a drainage tube in that opening, coming out above the pubisPYOO-bisThe front part of each hip bone, low in the pelvis; the two meet in the middle at the pubic symphysis.pub/o pubisFull entry . It drains the bladder without using the urethra, often in a poor-risk patient, as with long-standing urinary retentionYUR-ih-nair-ee rih-TEN-shunBeing unable to empty the bladder completely, or at all.Full entry or a neurogenic bladder. A bladder opened this way also lets the surgeon remove bladder stones (a suprapubic cystolithotomy).
Before surgery: supine, under general, spinal or local anesthesiaLOH-kul an-es-THEE-zhuhNumbing medicine applied to or injected into one small area, so a procedure there is not felt while the person stays awake.Full entry . Setup: a basic laparotomylap-uh-ROT-uh-meeSurgery that opens the abdomen through a large cut to reach the organs inside.lapar/o abdomen-tomy cutting intoFull entry set, a large Malecot or Pezzer catheter, Foley catheters of 22 to 30 Fr, and a drainage bag; a flexible cystoscopy is often part of the case.
Key steps:
- A vertical or Pfannenstiel incision; the rectusREK-tusLatin for straight; the name of several straight muscles, such as the rectus abdominis of the abdomen and the rectus femoris of the thigh.Full entry fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry is divided in the midlineMID-lineAn imaginary line down the center of the body; also, a type of IV catheter placed in a vein of the upper arm.Full entry .
- The bladder is filled with saline through a catheter, so it is easy to find, and its dome is freed.
- The bladder wall is held up with forceps or two tractionTRAK-shunA steady pulling force applied to a body part with weights, ropes and pulleys.Full entry sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry and opened; its contents are suctioningSUK-shun-ingRemoving mucus, saliva or other secretions from the mouth, nose or airway with a tube connected to a suction source.Full entry .
- A large Malecot or Pezzer catheter goes in, the bladder is closed snugly around it, and the tube is stitched to the skin so it cannot be pulled out. A drain may be left in front of the bladder.
A trocarTROH-karA sharp or bladed instrument inside a tube (cannula), used to pierce a body wall and leave the tube in place as a port.Full entry cystostomy does the same through a needle or trocar puncture, with a catheter passed through it, often under local anestheticLOH-kul an-es-THET-ikA drug that blocks feeling in one part of the body without making the person unconscious.Full entry .
Wound class: II.
Suburethral sling
What and why: in stress urinary incontinenceYOOR-ih-nair-ee in-KON-tih-nunsLeaking of urine that a person cannot control.Full entry , urine leaks when pressure in the abdomen rises, as with a cough or a sneeze. A sling is a strip of tissue or mesh placed under the urethra, which presses it closed at those moments; it is now the most widely used operation for stress incontinencein-KON-tih-nensLoss of control over the bladder or bowel, so urine or stool leaks out without the person meaning it to.in- notcontin/o to hold back-ence state ofFull entry in females and has largely replaced the older suspension operations. Chapter 33 teaches the other repairs of the pelvic floor.
- Pubovaginal sling: a strip of the patient's own rectus fascia, taken through a small Pfannenstiel incision, is placed at the bladder neck and its sutures tied above the fascia. It remains the gold standard, and concerns about synthetic mesh have renewed interest in it.
- Midurethral sling: a strip of polypropylene mesh tape in a plastic sleeve, carried on two large curved needles, is passed from a small vaginal incision behind the pubic bone and out above it (retropubic), or out through the obturator foramen (transobturator), and left without tension under the middle of the urethra. No anchors or stitches hold it.

Before surgery: lithotomy, with the abdomen and vagina prepped; local anesthetic with sedationsih-DAY-shunA calm, relaxed or sleepy state brought on by drugs, or the use of drugs to cause it.sed calm, settle-ation processFull entry is often enough for a midurethral sling. Setup: a weighted speculumSPEK-yoo-lumAn instrument used to open and hold open a body opening, such as the vagina, so the inside can be seen.Full entry and Allis clamps, the sling kit, a Foley with a rigid stylet, and a cystoscopy setup to check the bladder (a 70-degree lens for a pubovaginal sling).
Key steps (retropubic midurethral sling):
- The bladder is drained with a Foley, and local anesthetic is injected above the pubic bone and under the urethra.
- A small incision is made in the front wall of the vagina, close to the urethral opening, and the tissue under and beside the urethra is dissectdy-SEKT, or dih-SEKTTo cut apart or separate tissues carefully during surgery.Full entry free.
- With a rigid guide in the Foley to push the bladder neck aside, each needle is passed up behind the pubic bone and out through a tiny skin incision above it.
- Before each needle is pulled through, the surgeon does a cystoscopy to be sure it has not passed through the bladder.
- The tape is set loosely under the urethra, often with a small dilatorDY-lay-terAn instrument used to stretch or widen an opening, canal or passage in the body.Full entry between them; the patient may be asked to cough so the tension can be adjusted. The sleeves come off, the ends are cut at the skin, and the vaginal incision is closed.
Wound class: II, because the vagina is entered.
After surgery: the risks include a needle through the bladder, bleeding behind the pubic bone, infection and trouble emptying the bladder; a synthetic sling can erode into the urethra or vagina more often than the patient's own fascia.
Cystectomy with ileal conduit
What and why: a cystectomy removes the bladder, most often for a cancer that has grown into its muscle wall or for tumors that keep coming back despite treatment. In a radical cystectomy, the pelvic lymph nodelimf nohdA small, bean-shaped organ of the immune system that filters lymph fluid and holds white blood cells.Full entry come out too: in a male, with the prostatePROS-taytA walnut-sized gland below the bladder in males that surrounds the urethra and makes part of the fluid in semen.Full entry and seminal vesicleVES-ih-kulA small, raised blister on the skin filled with clear fluid, less than 1 cm across.Full entry ; in a female, with the urethra, uterus, cervix, tubes, ovaries and the front of the vagina (an anterior pelvic exenteration). The operation can be open, laparoscopiclap-uh-roh-SKOP-ikDone through a few small cuts in the abdomen with a thin camera and long instruments, instead of one large opening.lapar/o abdomen-scopic viewingFull entry or robotic, and a cystectomy with an ileumIL-ee-umThe last and longest part of the small intestine, which joins the large intestine.Full entry conduit is now most often done robotically. Without a bladder, the urine must be diverted.
Urinary diversion:
- Ileal conduit: the classic method. A short piece of ileum, still on its blood supply, becomes a passage: the ureterYOOR-uh-terOne of the two tubes that carry urine from the kidneys down to the bladder.Full entry drain into one end, and the other end comes out through the skin as a stomaSTOH-muhAn opening on the surface of the body made by surgery, such as the end of bowel brought out through the belly wall.stoma mouth, openingFull entry (a urostomy), where a bag collects the urine. The conduit is a passage, not a reservoirREZ-er-vwarA place where germs live and multiply, such as a person, animal, water or soil.Full entry : the urine runs straight through it into the bag.
- Continent reservoir or neobladder: a pouch sewn from bowel, either drained through a small stoma that the patient catheterizes, or joined to the urethra so the patient voids, in suitable patients.
Before surgery: the surgeon and an ostomyOS-tuh-meeA surgically made opening from an inside organ, such as the bowel or urinary tract, through the belly wall to the outside.-ostomy surgical openingFull entry (enterostomal) nurse mark the stoma site with the patient, usually above the belt line in the right lower abdomen; keep the mark from being scrubbed off during the prep. The patient is supine, or in low lithotomy for a female patient. Setup: a major laparotomy set with long instruments, a kidney set, intestinal clamps, GI staplers, sponge sticks and small dissecting sponges, clamp shods, vessel loops, clips, ureteral stentstentA small tube, often of metal mesh, placed inside a vessel or duct to hold it open.Full entry and a large self-retaining retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry such as a Bookwalter.
Key steps (open):
- A lower midline incision. The space in front of the bladder is opened, and the urachus, the cord from the bladder to the umbilicus, is clamped and divided.
- The bowel is moved aside and packed with moist laps behind the retractor blades.
- Each ureter is freed, looped with a vessel loop tagged with a hemostatHEE-moe-statA clamp with finger rings and a locking ratchet used in surgery to grasp and close off bleeding vessels.hem/o blood-stat stopping, standing stillFull entry , then tied and divided near the bladder; temporary stents divert the urine.
- The pelvic lymph nodes are removed, now or after the bladder; keep each packet separate and labeled exactly as the surgeon names it.
- The bladder's blood vessels are controlled with clips, staplers or a vessel sealer, and the bladder comes out in one piece with the prostate and seminal vesicles, or with the uterus and front of the vagina, whose cuff is then closed.
- The conduit: a 15 to 20 cm segment of ileum near the ileocecal valve is isolated on its mesentery between intestinal clamps, and the ileum is rejoined so the bowel works again. Bowel technique begins when the bowel is opened (chapter 32).
- The ureters are spatulated (split and opened out at the end) and sewn into the conduit with fine absorbable suture over stents; the free end of the conduit is brought out through a disk of skin at the marked site and everted into a spout.
- Drains are placed, the wound is closed, and a temporary pouch goes on the stoma.
Specimens: the bladder and its organs, lymph node packets, often a frozen section of the urethral edge.
Counts: as for any open abdomen (chapter 28), and every radiopaqueray-dee-oh-PAYKBlocking x-rays, so the material shows up white on an x-ray image.radi/o radiation, x-rayopaque not letting throughFull entry sponge packed into the pelvis to slow the oozing must come back out.
Wound class: II, because the urinary tract and the bowel are opened under control; gross spillage from the bowel makes it Class III. One textbook calls the bladder removal Class I and the bowel and ureter part Class II.
After surgery: this is a long, major operation in older patients who often have other diseases, with a high rate of complications, such as bleeding, infection, leaks where the bowel and the ureters were joined, and a narrowed stoma. An enhanced recovery (ERAS) plan may be used. The patient or a caregiver cares for the stoma for life.
16Urethral operations
- urethrayoo-REE-thruhThe tube that carries urine from the bladder out of the body.Full entry dilationdy-LAY-shunThe widening or opening up of a body part, such as the cervix during labor, the pupils or a blood vessel.dilat widen-ion processFull entry : a urethral strictureSTRIK-cherA narrowed section of a hollow body passage, such as the urethra, esophagus or bowel, that is tighter than normal.Full entry , a scarred narrowing from a birth defect, infection or injury, is stretched step by step with sounds or with filiforms and followers. Inspect the filiforms and followers for damage and weak spots, especially at the threaded ends, before you pass them. A small catheter left in for a few days can soften the stricture further. Females are dilated with short straight metal dilatorDY-lay-terAn instrument used to stretch or widen an opening, canal or passage in the body.Full entry or hollow McCarthy dilators.
- Internal urethrotomy: a scope with a blade (a urethrotome) cuts the scar under direct view, and a indwelling urinary catheterin-DWEL-ing YUR-ih-nair-ee KATH-uh-terA tube passed through the urethra into the bladder and left in place to drain urine into a bag.Full entry stays for 3 to 5 days.
- Meatotomy: an incision that widens a narrowed external meatusmee-AY-tusAn opening or passage in the body, such as the urinary opening or the ear canal.Full entry . In a male patient, a straight hemostatHEE-moe-statA clamp with finger rings and a locking ratchet used in surgery to grasp and close off bleeding vessels.hem/o blood-stat stopping, standing stillFull entry is placed on the underside of the meatus, the opening is cut along the frenulum, and the lining is sewn to the skin with fine absorbable sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry ; petrolatum gauze goes on. It is done supine in males and in lithotomylih-THOT-uh-meeA position lying on the back with the hips and knees bent and the legs raised and spread apart, often in stirrups.lith/o stone-tomy cutting intoFull entry in females, under local anestheticLOH-kul an-es-THET-ikA drug that blocks feeling in one part of the body without making the person unconscious.Full entry , with a plastic instrument set.
- Meatoplasty: a reconstruction that reshapes the meatus, done as part of a hypospadiashy-poh-SPAY-dee-usA birth defect in which the opening of the urethra is on the underside of the penis instead of at the tip.hypo- below-spadias a tear, an openingFull entry repair (below).
- Urethroplasty: a repair of a long or deep stricture with a graftGRAFTTissue or a man-made material moved into place in surgery to replace or repair a damaged part.Full entry or a flap, often in exaggerated lithotomy, with the anus isolated under a plastic drape.
- Wound class: II, because the urinary tract is entered.
Artificial urinary sphincter (AUS)
What and why: an implanted, fluid-filled device that closes the urethra, used as a last measure when other treatments for stress incontinencein-KON-tih-nensLoss of control over the bladder or bowel, so urine or stool leaks out without the person meaning it to.in- notcontin/o to hold back-ence state ofFull entry have failed. It has three parts: a cuff around the urethra, a pressure-regulating balloon reservoirREZ-er-vwarA place where germs live and multiply, such as a person, animal, water or soil.Full entry in the lower abdomen, and a pump in the scrotumSKROH-tumThe pouch of skin and muscle that holds the testicles.Full entry or labia. Squeezing the pump moves fluid out of the cuff so the patient can void; the cuff refills by itself in a minute or two.
Before surgery: modified lithotomy; a laparotomylap-uh-ROT-uh-meeSurgery that opens the abdomen through a large cut to reach the organs inside.lapar/o abdomen-tomy cutting intoFull entry set; the sphincterSFINGK-terA ring of muscle that tightens to close an opening or passage in the body and relaxes to open it.Full entry parts, with contrastKON-trastA dye or other substance given before an imaging test so body parts show up more clearly.Full entry or injectable saline to fill them and an antibiotic solution. Handle the device as an implant.
Key steps: through a perinealper-ih-NEE-ulHaving to do with the perineum, the area between the genitals and the anus.Full entry incision the surgeon frees the bulbous urethra and wraps the cuff around it; through a small suprapubic incision the reservoir goes under the rectusREK-tusLatin for straight; the name of several straight muscles, such as the rectus abdominis of the abdomen and the rectus femoris of the thigh.Full entry muscle; the pump is tunneled into the scrotum; the parts are connected and filled.
Wound class: I, because the urethra is wrapped, not opened.
After surgery: a reaction to the device, erosion of the urethra under the cuff and failure of the fluid system are the known problems.
17Prostate operations
Transurethral resection of the prostate (TURP)
What and why: a transurethral resection of the prostatetrans-yoo-REE-thrul rih-SEK-shun of the PROS-taytSurgery that removes part of the prostate gland with an instrument passed up through the urethra.trans- throughurethr/o urethra-al relating toresection cutting outFull entry removes the obstructing inner prostatePROS-taytA walnut-sized gland below the bladder in males that surrounds the urethra and makes part of the fluid in semen.Full entry through the urethrayoo-REE-thruhThe tube that carries urine from the bladder out of the body.Full entry , chip by chip, with a resectoscope, leaving the outer capsule. It treats the voiding problems of benign enlargement and can relieve a blockage from cancer. A monopolar TURP uses a nonelectrolyte fluid; a bipolarby-POH-lerHaving two poles or two opposite ends; most often used as a short form of bipolar disorder.bi- twopolar having polesFull entry TURP resects in saline, and for larger glands saline avoids TURP syndrome. Newer ways to treat the enlarged prostate include incising it instead of removing it and vaporizing it with a laser.
Before surgery: spinal anesthesiaan-us-THEE-zhuhLoss of feeling or sensation, often brought on by drugs so that surgery or a procedure can be done without pain.an- withoutesthesi/o feeling, sensation-ia conditionFull entry may be chosen, because an awake patient shows the first signs of TURP syndrome. lithotomylih-THOT-uh-meeA position lying on the back with the hips and knees bent and the legs raised and spread apart, often in stirrups.lith/o stone-tomy cutting intoFull entry , with the buttocks at the edge of the lower break and SCDs on; a prep of the lower abdomen, genitals and perineumpair-ih-NEE-umThe area of skin and muscle between the genitals and the anus.perine/o perineumFull entry ; lithotomy drapes with a fluid pouch and, if the surgeon wants one, a rectalREK-tulRelating to the rectum, the last part of the large intestine; also, given or measured through the rectum.rect/o rectum, straight-al relating toFull entry sheathSHEETHA covering that wraps around a structure; in procedures, a short hollow tube left in a blood vessel to pass catheters through.Full entry . Setup: the cystoscopy setup plus urethral sounds, a resectoscope (24 or 27 Fr sheath and obturatorOB-too-ray-terA smooth-tipped rod that fits inside a tube, such as a tracheostomy tube or cannula, to guide it in and then is taken out.Full entry , working elements, a foroblique and a backup telescope, cutting loops and a roller ball), an Ellik evacuator or Toomey syringe, a three-way indwelling urinary catheterin-DWEL-ing YUR-ih-nair-ee KATH-uh-terA tube passed through the urethra into the bladder and left in place to drain urine into a bag.Full entry of about 22 or 24 Fr with a 30-mL balloon, and the irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry and drainage system. Check the camera and the surgeon's choice of loops before the start, and keep the back table neat and in clear view.
Key steps:
- The urethra is dilated with sounds if needed, and a cystoscopy checks the bladder and the size of the obstruction.
- The resectoscope sheath goes in with its obturator; the resectoscope, with its telescope and loop, replaces the obturator, and the irrigation, light cord and active cord are connected.
- With the bladder filled, the surgeon notes where the ureterYOOR-uh-terOne of the two tubes that carry urine from the kidneys down to the bladder.Full entry openings are, then resects, usually starting with the middle lobe and moving to the lateral lobes, switching between cutting and coagulationkoh-ag-yuh-LAY-shunThe process by which blood changes from a liquid into a gel, forming a clot.coagul clot-ation processFull entry current.
- The chips are flushed from the bladder with the Ellik evacuator; collect every piece for pathologypuh-THOL-uh-jeeThe study of disease and its causes and effects, or the disease changes found in a person or tissue.path/o disease-logy study ofFull entry .
- Bleeding points are sealed. A large Foley goes in, its balloon is filled in the bladder, never in the empty prostate cavity, and it is pulled gently down against the bladder neck and taped to the leg to press on the prostate bed. continuous bladder irrigationkun-TIN-yoo-us BLAD-er ir-ih-GAY-shunA steady flow of sterile fluid run into the bladder and drained back out through a three-way catheter.Full entry may follow.
Specimens: the prostate chips, all of them, from the evacuator and the drape's screen.
Wound class: II; one textbook allows facility policy to call a TURP unclassified.
After surgery: the catheter may stay for several days so the bladder can be irrigated. Watch for TURP syndrome, bleeding, infection and, later, a urethral strictureSTRIK-cherA narrowed section of a hollow body passage, such as the urethra, esophagus or bowel, that is tighter than normal.Full entry .
Open simple prostatectomy
What and why: for a very large benign gland, the surgeon shells out (enucleates) the inner adenomaad-uh-NOH-muhA tumor of gland tissue that is not cancer.aden/o gland-oma tumorFull entry whole through a lower abdominal incision instead of chipping it away. It also suits a patient who has bladder stones or pouches (diverticula) to treat at the same time. In a suprapubic prostatectomy the surgeon reaches the gland through the opened bladder; in a retropubic one, through the front of the prostatic capsule, without opening the bladder.
Before surgery: supine, in slight Trendelenburg positiontren-DEL-en-burg puh-ZISH-unA position in which the client lies on the back with the bed tilted so the head is lower than the feet.Full entry , the legs slightly apart; a prep of the abdomen and genitals; a towel over the penis and scrotumSKROH-tumThe pouch of skin and muscle that holds the testicles.Full entry . Setup: a laparotomylap-uh-ROT-uh-meeSurgery that opens the abdomen through a large cut to reach the organs inside.lapar/o abdomen-tomy cutting intoFull entry set with bladder retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry , prostatic instruments and a self-retaining retractor, Foley catheters (a three-way for irrigation), a suprapubic tube, drains and syringes. A Foley is placed first.
Key steps (suprapubic):
- A lower midlineMID-lineAn imaginary line down the center of the body; also, a type of IV catheter placed in a vein of the upper arm.Full entry incision opens the space in front of the bladder (the space of Retzius); a retractor is padded with moist laps.
- The bladder is opened between tractionTRAK-shunA steady pulling force applied to a body part with weights, ropes and pulleys.Full entry sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry ; have suction ready.
- A bladder retractor holds the bladder open, and a dye may be given to show the ureteral openings. The surgeon cuts the lining around the adenoma and shells it out with a finger.
- Bleeding in the empty cavity is stopped with the electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry , suture ligatures and hemostatichee-moh-STAT-ikStopping bleeding; also, a product or agent used to stop bleeding.hem/o blood-stasis stopping, standing still-ic relating toFull entry .
- A three-way Foley goes through the urethra into the bladder, often with a suprapubic tube too, and the bladder is closed in two layers, irrigated to check for leaks, and drained.
Wound class: II.
Radical prostatectomy, open
For prostate cancerPROS-tayt KAN-serCancer that starts in the prostate, the gland below the bladder in males that helps make semen.Full entry still inside the gland, a radical prostatectomy removes the whole prostate, its capsule and the seminal vesicleVES-ih-kulA small, raised blister on the skin filled with clear fluid, less than 1 cm across.Full entry , and the bladder neck is joined to the urethra. The nerves for erection run in bundles beside the gland, and in a nerve-sparing operation the surgeon saves one or both; no heat is used near them. Pelvic lymph nodelimf nohdA small, bean-shaped organ of the immune system that filters lymph fluid and holds white blood cells.Full entry are usually removed for stagingSTAY-jingWorking out how large a cancer is and how far it has spread in the body.Full entry . Prostatectomy is now commonly done robotically (below), but know the open operations too.
- Retropubic: through a lower midline incision, staying outside the peritoneumpair-ih-toh-NEE-umThe thin membrane that lines the belly cavity and covers most of the organs inside it.peri- aroundton stretched-eum a structureFull entry . The dorsalDOR-sulHaving to do with the back of the body, or the top of the hand or foot.Full entry vein complex, a large cluster of veins in front of the prostate, can bleed heavily, so be ready for it. A urethral suture guide helps place the sutures that join the urethra to the bladder neck, and a 22 Fr Foley with a 30-mL balloon stays after.
- perinealper-ih-NEE-ulHaving to do with the perineum, the area between the genitals and the anus.Full entry : through an inverted U-shaped incision in the perineum, in exaggerated lithotomy, with a curved Lowsley retractor passed up the urethra into the bladder to push it down toward the perineum. It is rarely done today. The Foley stays 1 to 2 weeks while the joined urethra heals.
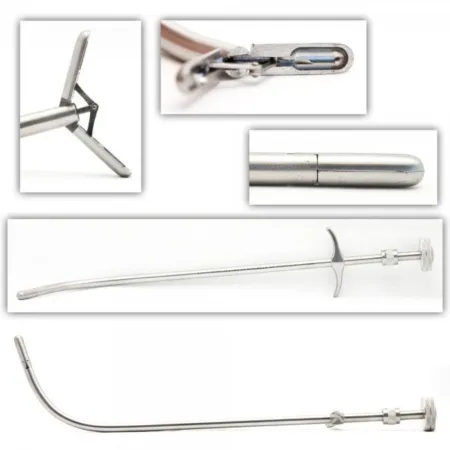
Wound class: II, because the urethra is cut.
Prostate seed implantation (brachytherapy)
What and why: radioactive seeds placed inside the prostate treat an early, slow-growing cancer from within. Each seed's radiationray-dee-AY-shunEnergy that travels as waves or particles, such as X-rays, used to make images or treat cancer; also pain that spreads from its starting point.radi/o rays, radiation-ation processFull entry reaches only about 5 mm, so the prostate gets a much higher dose than outside radiation could give, while nearby organs are spared. The seeds are iodineEYE-uh-dyneA mineral the thyroid gland uses to make thyroid hormone; it is also used to kill germs on the skin and in some contrast dyes.Full entry -125 or palladium-103. A team does it: the urologist, a radiation oncologist, a medical physicist or dosimetrist and the radiation safety staff, under federal and state rules for radioactive materials.
Before surgery: lithotomy, with the scrotum held up out of the way, under regional or general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry , often as an outpatient. A stepper on the table holds the transrectal ultrasound probe, which carries a template grid; the plan maps where every seed goes.


Key steps:
- A catheter drains the bladder and refills it with sterile water, which helps the ultrasound picture; it is then removed, so seeds are not placed against the urethra.
- The probe goes in under a sterile cover, and the plan's images are matched on the screen.
- Needles loaded with seeds are passed through the template's holes into the prostate, as the plan directs, the front ones first.
- A cystoscopy at the end finds any seed in the urethra or bladder, and a Foley stays for a day or two.
Radiation safety: handle the seeds only with forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry or tongs, never fingers, and account for every one. At the end, the radiation safety officer's team scans the staff, the instruments and the trash, drapes included, with a radiation detector. Chapter 22 teaches radiation safety.
Wound class: II, because the case enters the urinary tract with a catheter and a cystoscopy.
After surgery: the patient strains the urine and returns any seed that comes out, and for 6 to 8 weeks keeps about 15 feet from children and pregnant people. Seeds can slip into the bladder or drift to the lungs; cystitissis-TY-tisInflammation of the urinary bladder.cyst/o bladder, sac-itis inflammationFull entry , retention, a stricture, incontinencein-KON-tih-nensLoss of control over the bladder or bowel, so urine or stool leaks out without the person meaning it to.in- notcontin/o to hold back-ence state ofFull entry and erectile dysfunctionih-REK-tile dis-FUNK-shunRepeated trouble getting or keeping an erection firm enough for sex.dys- difficult, abnormalfunction workingFull entry can follow.
Prostate biopsy
A needle biopsy of the prostate, guided by transrectal ultrasound, takes cores of tissue for the diagnosis of cancer. It is usually done in the surgeon's office or as an outpatient, under local anestheticLOH-kul an-es-THET-ikA drug that blocks feeling in one part of the body without making the person unconscious.Full entry or sedationsih-DAY-shunA calm, relaxed or sleepy state brought on by drugs, or the use of drugs to cause it.sed calm, settle-ation processFull entry , after a cleansing enemaEN-uh-muhLiquid put into the rectum and lower bowel through the anus.Full entry and antibiotics, which lower the risk of infection; hematuriahee-muh-TOOR-ee-uhBlood in the urine, either seen by eye or found only by a test.hemat/o bloodur/o urine-ia conditionFull entry , stool or semen is common for a few days. A biopsy can also be taken through the perineum, which carries a lower risk of a serious infection (sepsisSEP-sisA severe whole-body response to an infection that damages the body's own organs.Full entry ).
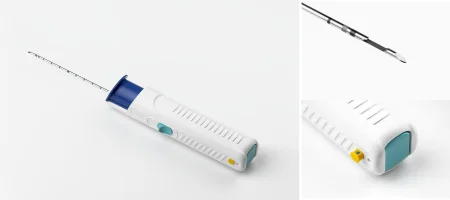
18Robotic prostatectomy with lymph node dissection
This is the Core Curriculum's model case for urology, so it is taught here from start to finish. Chapter 21 teaches the robot itself: its parts, draping, docking and an emergency undocking.
Pathophysiology
- The tumor: prostate cancerPROS-tayt KAN-serCancer that starts in the prostate, the gland below the bladder in males that helps make semen.Full entry is an adenocarcinoma, a malignant tumor of the gland tissue, which usually starts in the outer (peripheral) part of the gland. It is often slow-growing and gives no symptoms until late.
- Spread: to the lymph nodelimf nohdA small, bean-shaped organ of the immune system that filters lymph fluid and holds white blood cells.Full entry , to organs such as the adrenal glanduh-DREE-nul GLANDOne of two small glands that sit on top of the kidneys and make hormones such as cortisol, aldosterone and epinephrine.ad- toward, nearren/o kidney-al relating toFull entry , liver and lungs, and to bone, such as the pelvis, spine, ribs and femur. That is why the pelvic lymph nodes are removed with the prostatePROS-taytA walnut-sized gland below the bladder in males that surrounds the urethra and makes part of the fluid in semen.Full entry , and why the stage decides the outlook.
- Causes and risks: age, environmental factors, genes and hormone levels. African American and Jamaican males of African descent have the highest rate of prostate cancer in the world.
Grading and stagingSTAY-jingWorking out how large a cancer is and how far it has spread in the body.Full entry : the pathologist gives the two most common cell patterns a grade from 1 to 5 and adds them for the Gleason score. The Core Curriculum's scale runs from 2 to 10: 6 is low grade, 7 medium, and 8 to 10 high, and in practice 6 is the lowest score usually seen. The stage describes how far the cancer has gone: in the Core Curriculum's lettered system, A is small, cannot be felt and is still inside the gland; B can be felt but is still inside it; C has spread beyond the prostate; D has spread to distant sites. The TNMtee-en-em (said as letters)Tumor, Node, Metastasis: a system for describing how far a cancer has grown and spread.Full entry system (tumor, nodes, metastasismuh-TAS-tuh-sisThe spread of cancer cells from where the cancer started to other parts of the body.meta- change, beyondstasis standing, placeFull entry ) is the other one you will see.
pathologists now also report five Grade Groups (1 to 5) built from the Gleason score, which separates the two kinds of score 7 (3 + 4 and the higher-risk 4 + 3).
Diagnosis
A PSA blood test and a digital rectalREK-tulRelating to the rectum, the last part of the large intestine; also, given or measured through the rectum.rect/o rectum, straight-al relating toFull entry exam come first, and the PSA is drawn before the exam. An older blood markerMAR-kerSomething that can be measured, such as a substance in the blood, that shows a disease or body process is present.Full entry , prostatic acid phosphatase, is still listed in the Core Curriculum. magnetic resonance imagingmag-NET-ik REZ-uh-nunts IM-uh-jingAn imaging test that uses a strong magnet and radio waves to make detailed pictures of the inside of the body.Full entry and transrectal ultrasound show the gland, and a needle biopsy confirms the cancer. When the biopsy is positive, bone scans, computed tomographykum-PYOO-tid toh-MOG-ruh-feeAn imaging test that uses x-rays and a computer to make cross-section pictures of the inside of the body.tom/o cut, slice-graphy process of recordingFull entry and MRI look for spread.
Preparing the patient
- 6 to 8 weeks before: the patient starts Kegel exercisesKAY-gul EK-ser-syze-izExercises that strengthen the pelvic floor muscles by squeezing and relaxing them.Full entry (pelvic floor) exercises, which strengthen the urinary sphincterSFINGK-terA ring of muscle that tightens to close an opening or passage in the body and relaxes to open it.Full entry and may help with urine control after surgery, and has the final diagnostic exams.
- 1 week before: medicines are stopped as the surgeon directs.
- 2 days before: no alcohol.
- The day before: a bowel prep, and nothing by mouth as directed.
- anesthesiaan-us-THEE-zhuhLoss of feeling or sensation, often brought on by drugs so that surgery or a procedure can be done without pain.an- withoutesthesi/o feeling, sensation-ia conditionFull entry and monitoring: general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry , with monitoring of the depth of anesthesia (BIS), exhaled carbon dioxideKAR-bun dy-OK-sideA gas made by the body's cells as waste, carried in the blood to the lungs and breathed out.Full entry (capnography), blood pressure, heart rate, saturationsach-uh-RAY-shunHow full something is; in nursing, usually the percentage of hemoglobin in the blood that is carrying oxygen.Full entry , breathing rate, temperature and urine output, and deep vein thrombosisDEEP VAYN throm-BOH-sisA blood clot in a deep vein, most often in the leg or pelvis.thromb/o clot-osis conditionFull entry prevention. Antibiotic and anticoagulantan-tee-koh-AG-yoo-luntA drug that slows the blood's ability to form clots.anti- againstcoagul/o clotting-ant an agent that doesFull entry prophylaxisproh-fuh-LAK-sisTreatment given to prevent a disease or problem, rather than to treat one that is already present.pro- beforephylax guardFull entry are standard.
Position: low lithotomylih-THOT-uh-meeA position lying on the back with the hips and knees bent and the legs raised and spread apart, often in stirrups.lith/o stone-tomy cutting intoFull entry in stirrups, with the hips flexed a little to keep the femoralFEM-er-ulRelating to the thigh or the femur, the thigh bone.Full entry and obturatorOB-too-ray-terA smooth-tipped rod that fits inside a tube, such as a tracheostomy tube or cannula, to guide it in and then is taken out.Full entry nerves from stretching, and both arms tucked at the sides in a neutral position, padded to protect the median and ulnar nerves. After the ports are in, the table goes into steep Trendelenburg positiontren-DEL-en-burg puh-ZISH-unA position in which the client lies on the back with the bed tilted so the head is lower than the feet.Full entry . To keep the patient from sliding, use an anti-skid pad or a vacuum positioner and padded safety straps, never shoulder braces. Once the robot is docked, the table must not be moved, or the fixed arms could injure the patient.
Prep and drape: the abdomen from mid-chest to mid-thigh, and the perineumpair-ih-NEE-umThe area of skin and muscle between the genitals and the anus.perine/o perineumFull entry . Folded towels square off the abdomen, then an under-buttocks sheet, leggings and a laparoscopiclap-uh-roh-SKOP-ikDone through a few small cuts in the abdomen with a thin camera and long instruments, instead of one large opening.lapar/o abdomen-scopic viewingFull entry drape. Then the time out.
The room, instruments and supplies
Equipment:
- Extra tables: a Mayo standMAY-oh standA small tray on an adjustable stand placed over or beside the patient during surgery to hold the instruments used most often.Full entry and a ring stand.
- Dedicated electrical circuits, an electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry generator, and an insufflationin-suh-FLAY-shunBlowing a gas into a body cavity, such as carbon dioxide into the abdomen during laparoscopic surgery.Full entry with its carbon dioxide supply.
- The patient cart, with four instrument arms and its safety locks.
- The surgeon console, which gives 3D high-definition vision, filters out tremorTREM-erShaking of a part of the body, such as the hands, in small rhythmic movements that the person cannot control.Full entry and controls the wristed instruments.
- The vision cart: the communication parts, the hub that powers and links the system, an HD monitor, the camera box and the light source.
- Positioning aids (armboards, a safety strap, stirrups) and suction.
Instruments: laparoscopic instruments; robotic instruments chosen by the surgeon, mainly bipolarby-POH-lerHaving two poles or two opposite ends; most often used as a short form of bipolar disorder.bi- twopolar having polesFull entry forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry , graspers such as the ProGrasp, and monopolar curved scissors, with a needle driver for the anastomosisuh-nas-tuh-MOH-sisA connection between two tube-shaped structures, such as two ends of bowel or two blood vessels, made by surgery or found naturally.Full entry ; 0-degree and 30-degree scopes with a scope warmer; a light cord. A genitourinaryjen-ih-toh-YOOR-ih-nair-eeRelating to the genital (reproductive) organs and the urinary organs together.genit/o reproductive organsurin/o urine-ary relating toFull entry (open) set is on hold in case the case must convert.




Supplies: a back table pack; #11 and #15 blades; light handle covers; skin prep; suction tubing; 10- and 30-mL syringes; drapes, gowns, gloves and sponges. Specialty supplies: drapes for the camera and robotic arms, endoscopicen-doh-SKOP-ikDone with an endoscope, a thin tube with a light and camera passed into the body.endo- within-scopic viewingFull entry dissectors, a indwelling urinary catheterin-DWEL-ing YUR-ih-nair-ee KATH-uh-terA tube passed through the urethra into the bladder and left in place to drain urine into a bag.Full entry , a specimen retrieval pouch, a Veress needle, a vessel sealer, and sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry for the anastomosis and for closing the abdomen.

The operation
The Core Curriculum's sequence starts from behind, at the seminal vesicleVES-ih-kulA small, raised blister on the skin filled with clear fluid, less than 1 cm across.Full entry ; some surgeons start in front, in the space between the pubisPYOO-bisThe front part of each hip bone, low in the pelvis; the two meet in the middle at the pubic symphysis.pub/o pubisFull entry and the bladder (the space of Retzius), and the order of steps changes with them.
- You cover each arm of the patient cart with its sterile drape.
- A 24 Fr Foley goes in to keep the bladder empty. Keep it within reach on the field, on a Mayo or prep stand, because it will be moved during the case.
- The skin near the umbilicus is incised with a #11 or #15 blade, the abdominal wall is lifted by hand, the Veress needle goes in and the abdomen is inflated.
- The first port, 12 mm, goes in, and the 30-degree scope looks around.
- Under the camera, 8 mm robotic ports are placed on each side of the rectusREK-tusLatin for straight; the name of several straight muscles, such as the rectus abdominis of the abdomen and the rectus femoris of the thigh.Full entry muscles, at about the level of the umbilicus, a 10 mm assistant port low on the patient's right, just above the anterior superior iliacIL-ee-akHaving to do with the ilium, the large, wing-shaped upper part of the hip bone.Full entry spine, for retractionrih-TRAK-shunA drawing back or pulling in of tissue; in breathing, the skin sinking in between, below or above the ribs with each breath.Full entry and passing sutures, and a 5 mm port below the umbilicus for suction and irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry . Then the table goes into Trendelenburg. The Core Curriculum's outline puts the assistant port just below the spine.
- A nonsterile team member helps drive the patient cart to the table, where it is docked and locked. The arms are attached to the ports, and the robotic instruments go in, usually bipolar forceps, a grasper and a dissecting instrument.
- The surgeon breaks scrub and moves to the console. You stay at the field: you change instruments in the arms, reload clips, load sutures and pass them in through the assistant port, run the suction, move the Foley when asked and deal with equipment problems.
- The 30-degree scope is swapped for the 0-degree scope. The bowel is lifted up out of the pelvis to show the rectum.
- The peritoneumpair-ih-toh-NEE-umThe thin membrane that lines the belly cavity and covers most of the organs inside it.peri- aroundton stretched-eum a structureFull entry is opened in the midlineMID-lineAn imaginary line down the center of the body; also, a type of IV catheter placed in a vein of the upper arm.Full entry , and the vas deferens and seminal vesicles are found. Each vas is divided, the ureterYOOR-uh-terOne of the two tubes that carry urine from the kidneys down to the bladder.Full entry are identified, and the seminal vesicles are freed and lifted up with the vas. The surgeon stays in the midline, because the ureters enter the bladder at the sides.
- The space between the prostate and the rectum is opened down to the tip (apex) of the prostate.
- Lymph node dissectiondy-SEK-shunA tear in the inner layer of an artery wall that lets blood split the layers apart; also, the cutting apart of tissue in surgery.Full entry : the surgeon frees the lymph nodes from beside the external iliac vein and the side wall of the pelvis with blunt dissection and cautery, clips them to stop lymphLIMFThe clear fluid that flows through the lymphatic vessels and carries white blood cells.Full entry from leaking, and works around the obturator nerve without harming it. Each packet is passed off to you; keep the right and left nodes apart and labeled exactly as the surgeon names them. The Core Curriculum places the node dissection here, when the surgeon finds a reason for it; another reference takes the nodes after the prostate is free.
- The umbilical ligaments are divided, and the bladder falls away from the front of the abdominal wall.
- The prostate is pulled aside, and the endopelvic fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry beside it is opened down to the urethrayoo-REE-thruhThe tube that carries urine from the bladder out of the body.Full entry .
- You load a suture and pass it in through a port, and the surgeon secures the dorsalDOR-sulHaving to do with the back of the body, or the top of the hand or foot.Full entry venous complex, the large cluster of veins over the front of the prostate, with a figure-of-eight stitch.
- With upward tractionTRAK-shunA steady pulling force applied to a body part with weights, ropes and pulleys.Full entry on the prostate, the surgeon opens the front of the bladder neck until the Foley shows. You pull gently on the catheter, which lifts the prostate, while the back of the bladder neck is cut and freed all the way around.
- The pediclePED-ih-kulA narrow stem or stalk that attaches a structure, such as a tumor or a skin flap, to the body.Full entry at the sides of the prostate are clipped and divided close to the prostate, out to the puboprostatic ligaments. The nerve bundles, which control erection, are protected, and in a nerve-sparing operation no heat is used near them.
- The dorsal venous complex is divided, and the urethra is cut just beyond the apex of the prostate, front wall first, then the back wall with the rectourethralis muscle. The prostate is now free.
- A specimen retrieval pouch goes in through a port; once the prostate is inside, its string is brought out through a port and held with a hemostatHEE-moe-statA clamp with finger rings and a locking ratchet used in surgery to grasp and close off bleeding vessels.hem/o blood-stat stopping, standing stillFull entry .
- The bladder neck is sewn to the stump of the urethra with a running 2-0 or 3-0 absorbable stitch: the vesicourethral (urethrovesical) anastomosis.
- A Foley is passed through the urethra and across the anastomosis into the bladder, before the last stitch is tied or once the anastomosis is done.
- You fill the bladder with 200 mL of saline through the catheter, so the surgeon can check the anastomosis for leaks; have more suture ready in case one needs a stitch. The Core Curriculum's outline and one textbook do this the other way round: they test first, then replace the Foley with a new one.
- The robot is undocked, the surgeon scrubs back in, and the specimen pouch comes out through a port site that is made a little larger.
- The gas is let out as the ports come out, and the incisions are closed, the fascia at the larger ports and then the skin.
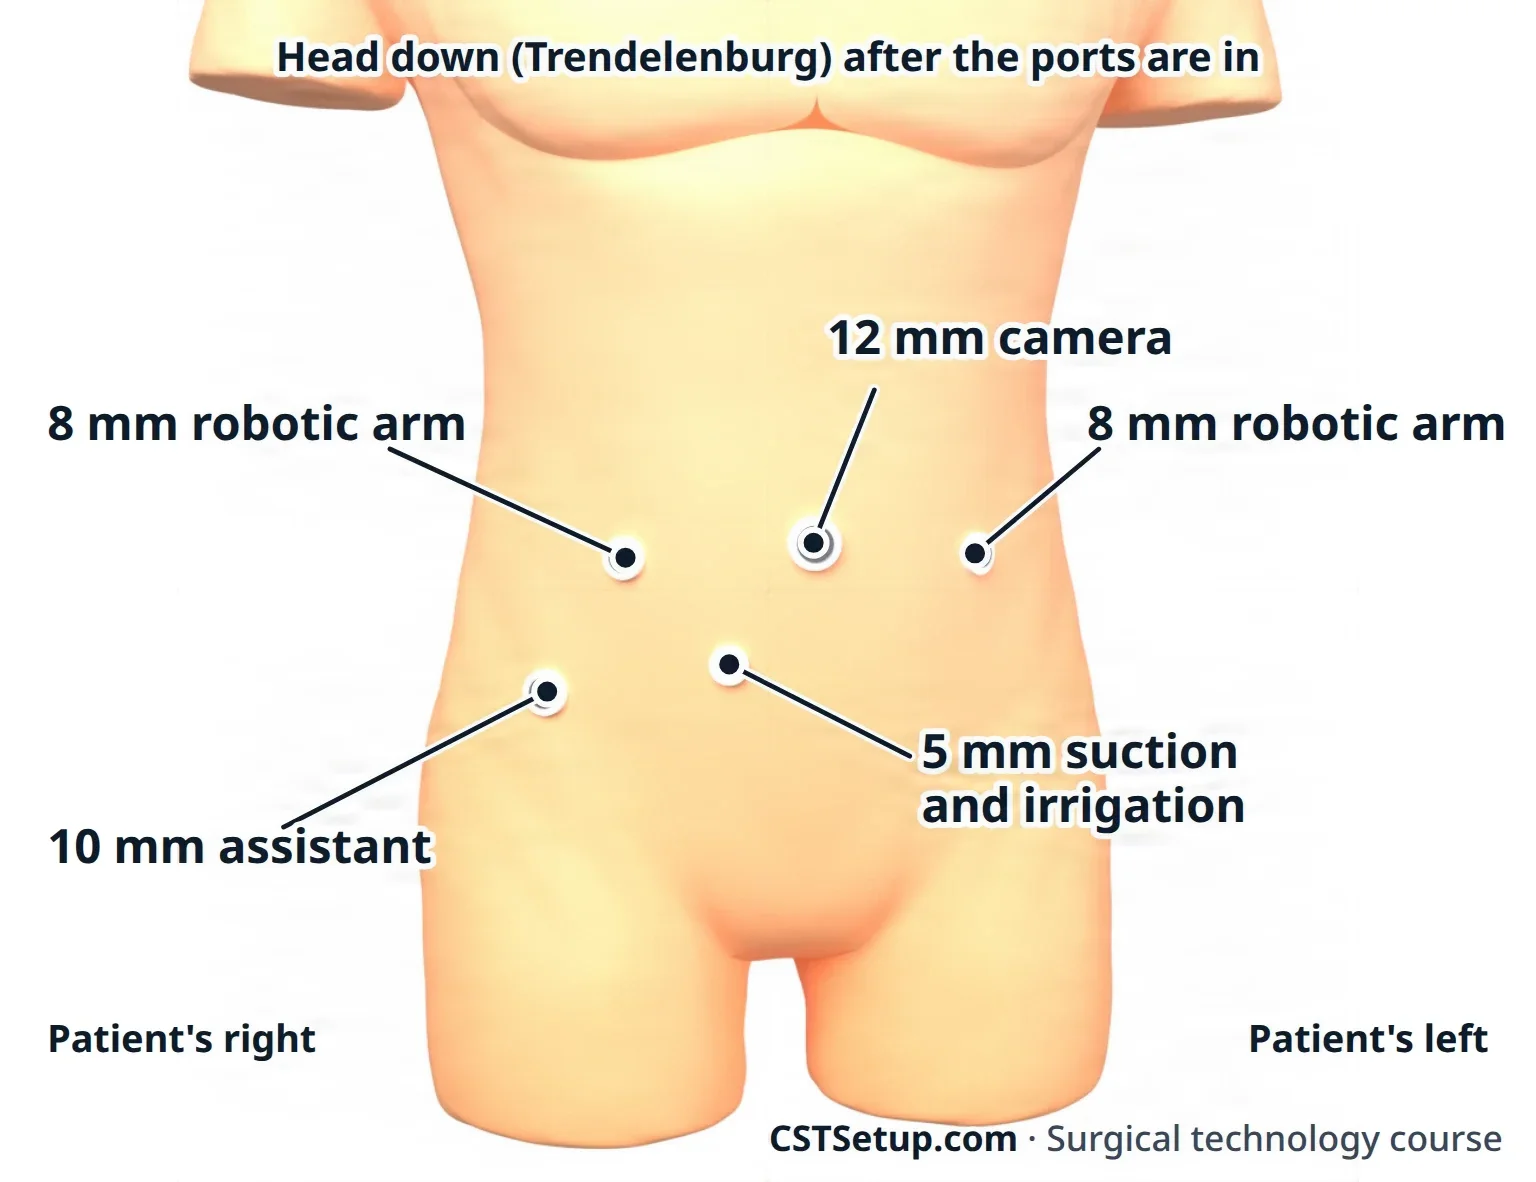
when the surgeon is at the console, you are the hands at the patient. Know which instrument is in which arm, keep the Foley ready to pull, and be ready to undock and open fast if the patient bleeds.
Catheters and drains: the Foley, which stays about a week while the anastomosis heals, and a closed wound drain, which may come out through one of the port sites.
Specimens: the lymph nodes and the prostate, each labeled. The prostate's margins tell the surgeon whether all the cancer came out.
Dressings: skin closure strips or adhesive bandages over the port sites.
Counts: initial, when closure of the cavity begins, and at subcutaneoussub-kyoo-TAY-nee-usUnder the skin; in the fatty layer between the skin and the muscle.sub- undercutane/o skin-ous relating toFull entry and skin closure. Count every needle and item passed in through a port.
Wound class: II, because the urethra is cut; III if the bowel is injured. The Core Curriculum's outline also lists Class I, and one textbook calls the case Class I.
After surgery: the patient goes to PACU. The outlook depends on whether the cancer was still in the prostate or had reached the lymph nodes or distant tissues. Complications include a leak or breakdown of the anastomosis, bleeding, DVT, wound infection, urinary incontinenceYOOR-ih-nair-ee in-KON-tih-nunsLeaking of urine that a person cannot control.Full entry , erectile dysfunctionih-REK-tile dis-FUNK-shunRepeated trouble getting or keeping an erection firm enough for sex.dys- difficult, abnormalfunction workingFull entry and death. Compared with the open operation, the robotic one means less blood loss and pain, a shorter stay and a faster recovery.
19Penile operations
These cases use a minor plastic set with fine instruments and fine sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry . Allis and Babcock clamps grip the genital tissues well. Use local anestheticLOH-kul an-es-THET-ikA drug that blocks feeling in one part of the body without making the person unconscious.Full entry with epinephrineep-ih-NEF-rinA hormone and drug, also called adrenaline, that raises heart rate and blood pressure and opens the airways.Full entry with great care, if at all, on the penis.
Circumcision
What and why: a circumcisionsur-kum-SIZH-unSurgery to remove the foreskin, the skin that covers the tip of the penis.Full entry removes the foreskin (prepuce). In an adult it treats phimosis, a tight foreskin that will not pull back over the glans; paraphimosis, a foreskin that has been pulled back and cannot return; balanoposthitis, an inflamed glans and foreskin; and the scarring of repeated infection. It is also done for hygiene and for cultural and religious reasons, often in newborns; respect the family's religious practices.
Before surgery: supine; local anesthetic with sedationsih-DAY-shunA calm, relaxed or sleepy state brought on by drugs, or the use of drugs to cause it.sed calm, settle-ation processFull entry or general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry ; a genital prep and a small fenestrated sheet. Setup: a minor plastic set, a needlepoint electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry or bipolarby-POH-lerHaving two poles or two opposite ends; most often used as a short form of bipolar disorder.bi- twopolar having polesFull entry , fine absorbable sutures and petrolatum gauze. Infants are restrained on a special board, and a clamp device or a plastic ring is used; their pain is real and is treated with a nerve block or numbing cream.
Key steps:
- The line of the coronal ridge is marked.
- hemostatHEE-moe-statA clamp with finger rings and a locking ratchet used in surgery to grasp and close off bleeding vessels.hem/o blood-stat stopping, standing stillFull entry on the edge of the foreskin hold it while it is cut lengthwise on the top (dorsalDOR-sulHaving to do with the back of the body, or the top of the hand or foot.Full entry ) side, then around its whole circumference; or two circular cuts are made, one on the shaft skin and one near the glans, and the cuff between them is removed.
- Bleeders are sealed with low-power cautery or tied.
- The skin edge is sewn to the cuff behind the glans with fine absorbable stitches, and petrolatum gauze goes on. A penile block with bupivacainebyoo-PIV-uh-kaynA long-acting local anesthetic used to numb an area, block nerves, or give epidural and spinal anesthesia.Full entry eases the pain afterward.
Wound class: no tract is opened, so it meets Class I by the CDC definitions; one textbook lists it as Class II. Follow your facility's policy.
After surgery: cold packs ease swelling; an erection can tear the stitches in an adult.
Penile implant
What and why: a penile prosthesispros-THEE-sisAn artificial body part that replaces one that is missing or does not work, such as an artificial leg, joint, eye or heart valve.Full entry treats erectile dysfunctionih-REK-tile dis-FUNK-shunRepeated trouble getting or keeping an erection firm enough for sex.dys- difficult, abnormalfunction workingFull entry from a physical cause, such as diabetes, vascular or nerve disease, pelvic surgery or injury. A malleable (semirigid) device is a pair of bendable rods. An inflatable device has cylinders in the two corpora cavernosa, a saline reservoirREZ-er-vwarA place where germs live and multiply, such as a person, animal, water or soil.Full entry under the abdominal muscles near the bladder, and a pump in the scrotumSKROH-tumThe pouch of skin and muscle that holds the testicles.Full entry .
Before surgery: supine or lithotomylih-THOT-uh-meeA position lying on the back with the hips and knees bent and the legs raised and spread apart, often in stirrups.lith/o stone-tomy cutting intoFull entry ; a indwelling urinary catheterin-DWEL-ing YUR-ih-nair-ee KATH-uh-terA tube passed through the urethra into the bladder and left in place to drain urine into a bag.Full entry (often 14 or 16 Fr) to mark the urethrayoo-REE-thruhThe tube that carries urine from the bladder out of the body.Full entry . Infection is the great danger of any implant, so traffic in the room is kept to a minimum. Set the implant on its own small table or Mayo covered with plastic, never touching paper or cloth that sheds lint, and open it only when the surgeon has chosen the size. Setup: a minor set with fine instruments, Hegar dilatorDY-lay-terAn instrument used to stretch or widen an opening, canal or passage in the body.Full entry , a measuring tool, the Furlow inserter and Keith needles, the connector tools, a self-retaining ring retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry , and antibiotic irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry . An implant coated with antibiotics is only dipped in saline, never soaked.

Key steps (inflatable, through the scrotum):
- A small incision where the penis meets the scrotum, held open with the ring retractor and its hooks.
- Each corpus cavernosum is opened between stay sutures and widened with Hegar dilators, and its length is measured.
- The cylinders, primed with saline, are pulled into place with the Furlow inserter, which carries a tractionTRAK-shunA steady pulling force applied to a body part with weights, ropes and pulleys.Full entry suture on a Keith needle out through the glans.
- With the bladder empty, the reservoir goes into a pocket behind the abdominal wall, in front of the bladder, and is filled with saline.
- The pump goes into the scrotum, the tubing is cut and connected, and the device is tested. The incision is closed in layers.
Wound class: I, because no tract is opened.
After surgery: the device may be left partly inflated for a day to limit bleeding. The Foley comes out after about a day.
Penectomy
What and why: a partial or total amputationam-pyoo-TAY-shunThe removal of all or part of a limb or other body part, by surgery or by injury.Full entry of the penis for cancer. Because it changes the patient's body and life so much, surgeons choose the smallest operation that will remove the cancer with a margin, often about 2 cm. A partial penectomy, which needs at least 3 cm of healthy shaft, can leave enough length for the patient to urinate standing; otherwise a total penectomy brings the urethra out through the perineumpair-ih-NEE-umThe area of skin and muscle between the genitals and the anus.perine/o perineumFull entry .
Before surgery: supine or lithotomy; the lesionLEE-zhunAn area of tissue that has been damaged or has changed from normal, such as a sore, wound, lump or spot.Full entry is wrapped and covered so cancer cells are not spread and it stays out of the sterile fieldSTAIR-ul feeldAn area set up with sterile drapes and supplies, kept free of all germs, for a sterile procedure.Full entry . A Penrose drain around the base of the penis works as a tourniquet. Setup: a minor set and a needlepoint ESU.
Key steps (partial): the skin is cut around the shaft down to Buck fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry ; the corpora are divided with the margin and closed with mattress sutures; the urethra is left a little longer, split, and sewn to the skin to make a new opening; a Foley stays for 3 to 5 days.
Wound class: II, because the urethra is divided.
20Scrotal and testicular operations
These cases are done supine with a genital prep, under local, regional or general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry , with a minor set. A scrotumSKROH-tumThe pouch of skin and muscle that holds the testicles.Full entry support or mesh briefs over fluffed gauze give gentle pressure afterward and limit swelling.
Hydrocelectomy
What and why: a hydrocele is fluid trapped in the tunica vaginalis, from infection, injury, a tumor or, in adults, peritoneal dialysispair-ih-toh-NEE-ul dy-AL-ih-sisA kind of dialysis that uses the lining of the abdomen as a filter, with fluid run in and out through a catheter.peritone/o peritoneum-al relating todia- through, apart-lysis loosening, separatingFull entry . A hydrocelectomy removes or turns inside out the swollen sac.
Key steps:
- A small incision in the stretched scrotal skin over the mass.
- The sac is freed and brought out, then opened; have suction ready for the fluid.
- The extra sac is cut away and its edges oversewn, or the sac is turned inside out around the testis and stitched behind it, so fluid cannot collect again.
- A small Penrose drain may come out through the bottom of the scrotum, and the incision is closed in layers.
Wound class: I.
A spermatocelectomy removes a spermatocele, a cyst on the head of the epididymisep-ih-DID-ih-misA coiled tube on the back of each testis where sperm mature and are stored.epi- upondidym testis (twin)Full entry , through the same incision, freeing it from the testis and cord.
Varicocelectomy
What and why: a varicocele is a tangle of swollen veins of the pampiniform plexusPLEK-susA network of nerves or blood vessels that branch and join together.Full entry around the cord, which can harm sperm production. It is more common on the left, because the left testicular vein drains into the left renal vein at a right angle and so meets more back pressure. The operation ties off the swollen veins, usually through an incision above or over the inguinalING-gwih-nulRelating to the groin, the fold where the thigh meets the lower abdomen.Full entry canal, sometimes under a microscope; the setup is like an inguinal herniaHER-nee-uhA bulge of an organ or tissue through a weak spot in the muscle or tissue wall that normally holds it in.Full entry repair.
Key steps: the surgeon frees the veins of the cord from the vas deferens, ties and cuts the swollen veins, may leave a drain and closes in layers.
Wound class: I.
Orchiectomy
What and why: an orchiectomy removes one or both testes. One testis is removed for cancer, a dead testis after torsion, injury or infection. Both are removed to stop testosteronetes-TOS-tuh-rohnThe main male sex hormone, made mostly in the testes and in small amounts by the ovaries and adrenal glands.test/o testis-sterone steroid hormoneFull entry in advanced prostate cancerPROS-tayt KAN-serCancer that starts in the prostate, the gland below the bladder in males that helps make semen.Full entry . Losing testosterone can bring tiredness, a lower sex drive and tender breasts, and references note that testosterone may be prescribed to prevent these, though not when lowering it is the point of the operation, as in prostate cancer.
- Simple orchiectomy, through the scrotum: the testis is brought out, the cord is divided into bundles that are each double-clamped, cut and tied, the vas is tied separately, and a drain may be left. Ask whether right and left go as separate specimens.
- Radical inguinal orchiectomy, for testicular cancer: through a groin incision over the inguinal canal, the surgeon frees the spermatic cord, clamps it and divides it at the internal ring, then delivers the testis up into the wound and removes it with its tunica vaginalis and cord. A drain may go in the empty side of the scrotum.
- Testicular prosthesispros-THEE-sisAn artificial body part that replaces one that is missing or does not work, such as an artificial leg, joint, eye or heart valve.Full entry : an implant can be placed for appearance, at the same time or later; it is measured and ordered ahead.
Wound class: I.
Orchiopexy and testicular torsion
What and why: an orchiopexy fixes a testis in the scrotum. Strictly, the word means fixing it to the scrotal wall; it also names the whole operation that brings down an cryptorchidismkrip-TOR-kih-diz-umA condition in which one or both testicles have not moved down into the scrotum.crypt/o hiddenorch/o testis-ism conditionFull entry (orchidopexy). An undescended testis left in the warmer abdomen or groin can lead to infertilityin-fer-TIL-ih-teeNot being able to become pregnant after a year of regular sex without birth control, or after six months for women over 35.Full entry and carries a higher risk of cancer, so it is brought down after the first year of life. It is often found with an inguinal hernia.
Testicular torsion: the testis twists on its cord and loses its blood supply; it can die in as little as 4 hours. A Doppler ultrasoundDOP-ler UL-truh-soundAn ultrasound that uses sound waves to hear or show blood flowing through vessels or the fetal heartbeat.Full entry confirms it, and surgery is done at once: the testis is untwisted and stitched in the scrotum, and the other testis is fixed too, because its support may be weak as well. A dead testis is removed.
Key steps (undescended testis):
- A groin incision, as for a hernia repair, opens the inguinal canal.
- The testis and its cord are freed up to the internal ring, and the hernia sac is tied off, which gives the cord more length.
- A small cut in the scrotum and a pocket between the skin and the dartos muscle (a subdartos pouch) receive the testis, which is passed through and anchored with a fine stitch.
- Both incisions are closed in layers.
Wound class: I.
Vasectomy and vasovasostomy
Vasectomy: a permanent form of birth control that removes a short piece of each vas deferens. It is often done in the office under local anestheticLOH-kul an-es-THET-ikA drug that blocks feeling in one part of the body without making the person unconscious.Full entry . The surgeon holds the vas against the scrotal skin, numbs it, and reaches it through one small midlineMID-lineAn imaginary line down the center of the body; also, a type of IV catheter placed in a vein of the upper arm.Full entry puncture or incision; a short segment, about 1.5 to 2 cm, is cut out, the ends are sealed with cautery, ties or clips, and the sheathSHEETHA covering that wraps around a structure; in procedures, a short hollow tube left in a blood vessel to pass catheters through.Full entry may be closed between them. The same is done on the other side. The patient must keep using birth control until a semen test shows no moving sperm.
Vasovasostomy: rejoining the cut ends of the vas, usually to restore fertility after a vasectomy, under a microscope with stitches as fine as 10-0. A segment of each end is trimmed until the openings are healthy, and fluid from the testicular end is checked on a glass slide for sperm. Set up the microscope and microsurgical instruments and sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry ; the patient wears a scrotal support for weeks and has sperm counts afterward.
Wound class: I, a clean case.
21Pediatric genitourinary surgery
Children's needs are taught in chapters 13 and 18. These are the urology operations done mainly in children.
Wilms tumor excision
What and why: Wilms tumorVILMZ TOO-merA cancer of the kidney that develops in young children.Full entry (nephroblastoma) is the most common kidney cancer of childhood, usually found between ages 2 and 5 as a painless lump in the abdomen; it can affectAF-ekt (stress on the first syllable)In mental health, the outward expression of a person's emotions, as seen in the face, voice and body language.Full entry one or both kidneys. The goal is to remove the kidney (a radical nephrectomy) without breaking the tumor, because cells spilled from it can seed new tumors.
Before surgery: supine with a small pad under the operative flank; an abdominal prep including the flank. Setup: a kidney set, a laparotomylap-uh-ROT-uh-meeSurgery that opens the abdomen through a large cut to reach the organs inside.lapar/o abdomen-tomy cutting intoFull entry set, Deaver retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry , a vascular set, vessel loops, a narrow Penrose drain, clamp shods, and hemostatichee-moh-STAT-ikStopping bleeding; also, a product or agent used to stop bleeding.hem/o blood-stasis stopping, standing still-ic relating toFull entry . Support the family: cancer surgery on a child is hard for everyone.
Key steps: an abdominal (subcostalsub-KOS-tulBelow the ribs.sub- belowcost/o rib-al relating toFull entry or lateral) incision, not a flank one; the surgeon looks for spread to the liver and other organs and feels the renal vein for a tumor clot; the colon is moved aside; the ureterYOOR-uh-terOne of the two tubes that carry urine from the kidneys down to the bladder.Full entry is looped and the renal artery and vein are tied; the kidney comes out whole.
Wound class: II, because the ureter is divided.
After surgery: the child needs lifelong follow-up, because the tumor can return years later.
Hypospadias and epispadias repair
What and why: in hypospadiashy-poh-SPAY-dee-usA birth defect in which the opening of the urethra is on the underside of the penis instead of at the tip.hypo- below-spadias a tear, an openingFull entry the urethrayoo-REE-thruhThe tube that carries urine from the bladder out of the body.Full entry opens on the underside of the penis, anywhere from the glans down to the scrotumSKROH-tumThe pouch of skin and muscle that holds the testicles.Full entry or perineumpair-ih-NEE-umThe area of skin and muscle between the genitals and the anus.perine/o perineumFull entry . The farther back it opens, the more the penis bends downward (chordee). In epispadiasep-ih-SPAY-dee-usA birth defect in which the urethra opens on the top side of the penis instead of at the tip, or in a female, too far forward.epi- upon, above-spadias an opening (from a Greek word for tearing)Full entry the urethra opens on the top of the penis; the severe forms come with incontinencein-KON-tih-nensLoss of control over the bladder or bowel, so urine or stool leaks out without the person meaning it to.in- notcontin/o to hold back-ence state ofFull entry and are part of the exstrophy complex below. The repair may include meatoplasty and glanuloplasty (reshaping the opening and the glans), straightening the penis, building a urethra (urethroplasty), and covering it with skin.
Before surgery: most patients are infants and toddlers, supine with the legs apart. Setup: a hypospadias tray of fine plastic and sometimes eye instruments, 4 to 8 Fr catheters and very fine sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry ; the surgeon often wears loupes. The surgeon may produce an artificial erection to see how much the penis bends; papaverine, injected into the erectile tissue, is one drug that causes one. A fine catheter stays for several days, under a soft foam dressing. An epispadias repair uses the same setup.
Key steps (MAGPI, for a meatusmee-AY-tusAn opening or passage in the body, such as the urinary opening or the ear canal.Full entry near the tip): the skin is cut around just below the glans and slid back; a bridge of tissue between the meatus and the groove of the glans is flattened and closed across; tractionTRAK-shunA steady pulling force applied to a body part with weights, ropes and pulleys.Full entry sutures hold the glans, whose edges are sewn together underneath; the skin is brought back over the shaft; a catheter goes in.
Wound class: II, because the urethra is opened; one textbook lists hypospadias and epispadias repair as Class I.
Bladder exstrophy
What and why: in exstrophy, a defect present at birth, the bladder lies open on the lower abdomen, its front wall missing, with epispadias, a short penis with an upward bend, rectusREK-tusLatin for straight; the name of several straight muscles, such as the rectus abdominis of the abdomen and the rectus femoris of the thigh.Full entry muscles and pubic bones spread apart, and the vagina and anus moved forward. Repair restores the lower urinary tract in stages. The bladder and abdomen are closed first, preferably at about 6 to 12 weeks of age, so the bladder is big enough to work toward control; one reference closes them in the first 24 to 48 hours of life. The epispadias is repaired at about 2 to 3 years, and urinary control is worked on at about 4 to 5 years.
Key steps (closure): the prep covers the whole body below the nipples, front and back, so the baby can be turned. Ureteral catheters go into each ureteral opening; the bladder and urethral plate are freed with their blood supply, closed in two layers and placed back in the pelvis, with a suprapubic tube for drainage. The pubic bones are drawn together with sutures, often after an orthopedicor-thuh-PEE-dikHaving to do with the bones, joints, muscles, ligaments and tendons, and the branch of medicine that treats them.orth/o straightped/o child (the field began with straightening children's bones)-ic relating toFull entry surgeon cuts the pelvic bones (an osteotomy), so an orthopedic set is added.
Wound class: II, because the urinary tract is opened.
Other children's cases
Children also have cystoscopy, with a small scope, for infections, bedwetting, urethral valves, reflux, stones and blockages; mild vesicoureteral refluxves-ih-koh-yoo-REE-ter-ul REE-fluksThe backward flow of urine from the bladder up into the ureters and toward the kidneys.vesic/o bladderureter/o ureter-al relating toreflux flowing backFull entry , urine flowing back up the ureter, may be treated by injecting a gel at the ureteral opening through the scope, and severe reflux by reimplanting the ureter.
22Gender confirmation surgery
What and why: a person who is transgender has a gender identityJEN-der eye-DEN-tih-teeA person's own inner sense of their gender, whether or not it matches the sex they were assigned at birth.Full entry that differs from the sex they were assigned at birth. Gender dysphoria is the distress that difference can cause. Gender confirmation (gender-affirming) surgery changes the body to match the person's gender identity. It is usually the last step of transition, after hormone therapy and living in the affirmed gender, which physicians may require for at least a year, and the standard of careSTAN-derd uv kairThe level of care that a reasonably careful nurse with the same training would give in the same situation.Full entry call for letters of support from mental health providers. Not every transgender person wants or has surgery. It is done in stages by a team that may include a plastic surgeon, a urologist, a gynecologist, an endocrinologist and mental health professionals.
Respectful care: ask the name and pronouns the patient uses, record them and pass them on to every caregiver, and use them. Protect the patient's privacy, for example by fully closing the curtains during an exam. Every patient has the right to be valued, respected and affirmed. A lack of affirming care is a root cause of the health gaps these patients face, and many meet barriers, cost above all, in getting care at all.
The Core Curriculum groups the operations as female to male and male to female; references also call them masculinizing (transmasculine) and feminizing (transfeminine) surgery.
- Phalloplasty: building a penis (a phallus) from a flap of skin and tissue from the forearm (a radial forearm flap) or the thigh (an anterolateral thigh flap), joined to blood vessels and nerves under a microscope. It may include lengthening the urethrayoo-REE-thruhThe tube that carries urine from the bladder out of the body.Full entry so the patient can urinate standing; one reference puts the chance of urethral problems, such as strictureSTRIK-cherA narrowed section of a hollow body passage, such as the urethra, esophagus or bowel, that is tighter than normal.Full entry , at about 40 percent. It is usually staged, and hair removal on the donor skin, which takes about 8 to 12 months, is finished first.
- Vaginectomy: removing the vagina, usually at the second stage of a phalloplasty, after a hysterectomyhis-tuh-REK-tuh-meeSurgery to remove the uterus.hyster/o uterus-ectomy surgical removalFull entry done as a separate operation.
- Testicular implants: after full healing, they may be placed in a new scrotumSKROH-tumThe pouch of skin and muscle that holds the testicles.Full entry built from the labia majora (scrotoplasty); like any testicular implant, they are measured and ordered ahead. A penile prosthesispros-THEE-sisAn artificial body part that replaces one that is missing or does not work, such as an artificial leg, joint, eye or heart valve.Full entry may be placed in a final stage.
- Vaginoplasty: creating a vagina. Penile inversionin-VER-zhunA turning inward or upside down; for the foot, turning the sole in toward the other foot.Full entry is the most common technique: the erectile tissue is taken apart, a space is opened between the prostatePROS-taytA walnut-sized gland below the bladder in males that surrounds the urethra and makes part of the fluid in semen.Full entry and the rectum, and the inverted penile skin, often with a scrotal skin graftGRAFTTissue or a man-made material moved into place in surgery to replace or repair a damaged part.Full entry , lines the new vagina over a dilatorDY-lay-terAn instrument used to stretch or widen an opening, canal or passage in the body.Full entry . Part of the glans becomes a sensitive clitorisKLIT-er-isA small, very sensitive organ at the top of the vulva, where the inner folds of skin meet.Full entry on its own nerve and blood supply, and the urethra is shortened so the stream points down when sitting. A bowel or peritonealper-ih-toh-NEE-ulHaving to do with the peritoneum, the thin lining of the belly cavity and the organs inside it.Full entry flap may be used when skin is short.
- Labiaplasty: shaping the labia from the genital skin; the foreskin, for example, becomes the clitoral hood and part of the labia minora.
- Penectomy: removing the penis, as part of vaginoplasty or alone.
Before surgery: patients stop smoking at least 4 weeks before and complete hair removal months ahead; a full-depth vaginoplasty needs daily dilationdy-LAY-shunThe widening or opening up of a body part, such as the cervix during labor, the pupils or a blood vessel.dilat widen-ion processFull entry afterward. Many cases are long and in lithotomylih-THOT-uh-meeA position lying on the back with the hips and knees bent and the legs raised and spread apart, often in stirrups.lith/o stone-tomy cutting intoFull entry , so pad and check the legs with special care.
Things to know: the prostate is not removed in a vaginoplasty, so the patient can still develop prostatitispros-tuh-TY-tisInflammation of the prostate gland.prostat/o prostate-itis inflammationFull entry , benign prostatic hyperplasiabee-NINE proh-STAT-ik hy-per-PLAY-zhuhA prostate gland that has grown larger than normal, from growth that is not cancer.hyper- more than normalplas growth or formation-ia conditionFull entry or prostate cancerPROS-tayt KAN-serCancer that starts in the prostate, the gland below the bladder in males that helps make semen.Full entry later. The space for the new vagina lies against the rectum and bladder, so injury to them is a known risk, and the surgeon may check the rectalREK-tulRelating to the rectum, the last part of the large intestine; also, given or measured through the rectum.rect/o rectum, straight-al relating toFull entry wall with a finger during the dissectiondy-SEK-shunA tear in the inner layer of an artery wall that lets blood split the layers apart; also, the cutting apart of tissue in surgery.Full entry .
Wound class: II, because the urethra and, in many cases, the vagina are opened; testicular implants placed on their own open no tract, Class I.
23Wound classes and care after GU surgery
Most of the chapter's wound classes follow one rule from chapter 11: an operation that enters the urinary tract under control is Class II, clean-contaminated. scrotumSKROH-tumThe pouch of skin and muscle that holds the testicles.Full entry , adrenaluh-DREE-nulHaving to do with the adrenal glands, the two small glands that sit on top of the kidneys.ad- nearren/o kidney-al relating toFull entry and implant operations that open no tract are Class I. Infected urine, an abscessAB-sesA closed pocket of pus in tissue, walled off by the body.Full entry or an infected stone means an infection already present, Class IV, and bowel spilling into the wound makes a case Class III.
After surgery, many urology patients leave the room with a urethrayoo-REE-thruhThe tube that carries urine from the bladder out of the body.Full entry catheter, a ureterYOOR-uh-terOne of the two tubes that carry urine from the kidneys down to the bladder.Full entry stentstentA small tube, often of metal mesh, placed inside a vessel or duct to hold it open.Full entry , a suprapubic tube, a nephrostomy tube or a wound drain. When several are in place, label each collection bag, and keep the tubing free of kinks and below the level of the bladder so each one keeps draining. Every tube is recorded: its type and size, where it goes in, and who placed it. Watch the urine for its amount and color: grossly bloody drainage can mean bleeding.
keep every drainage bag below the level of the bladder and every tube free of kinks, during the transfer and on the stretcher. Urine that cannot flow freely backs up, and urine that flows back from the bag raises the risk of a urinary tract infection.
What to take from this chapter
- Urology treats the urinary tract, the adrenal glands and the male genitals, through the urethra, through the skin, open, or with the laparoscope and the robot. Most cases go through a scope, and everything passed up the urethra must be sterile.
- Know the scopes by their parts: the cystoscope's sheath, obturator, telescope and bridge; the resectoscope's working element and loops; semirigid and flexible ureteroscopes; the nephroscope. On the French scale, 3 Fr is about 1 mm.
- Match the fluid to the energy: sterile water for a diagnostic cystoscopy, a retrograde pyelogram or a TURBT; glycine or sorbitol for a monopolar TURP; saline for bipolar, the holmium laser and most ureteroscopy. Never water for a TURP. Warm it to body temperature, track every bag and the deficit, and know the signs of TURP syndrome.
- Stents go in over a guidewire, with a safety wire beside it; a three-way Foley's large balloon sits in the bladder, never in the prostate cavity, and presses on the bleeding prostate bed. Stones go to the lab dry.
- A radical nephrectomy takes the kidney inside Gerota fascia with the adrenal gland, the pedicle tied first; a partial nephrectomy clamps the hilum for no more than about 30 minutes. A transplanted kidney goes into the iliac fossa, and the donor kidney is flushed cold at once to keep the warm ischemia time short.
- Keep every TURP and TURBT chip, every lymph node packet labeled by side, and every radioactive seed accounted for, handled with forceps. An ileal conduit is a passage, not a reservoir, and its stoma site is marked before the prep.
- For the robotic prostatectomy: low lithotomy and steep Trendelenburg on an anti-skid pad or vacuum positioner, never shoulder braces; the surgeon at the console and you at the patient; the vesicourethral anastomosis tested with 200 mL of saline; Class II.
- Testicular torsion is an emergency; an undescended testis goes into a subdartos pouch; implants are handled as little as possible and kept off lint. Gender confirmation surgery is done in stages by a team, and every patient is cared for with the name and pronouns they use.
Check yourself5 quick questions
Free for everyone. Pick an answer for each, then check them all at once.
In the ORWhere you'll use this
The chapter's whole question pool in sets of 10, with the answer explained after each one.
Part of the educators programThe chapter's words on spaced cards: the ones you miss come back sooner.
Part of the educators programGiven by your class's teacher. Each class draws its own 25 from the chapter's pool.
Part of the educators program
Suggest a fix
Something wrong, unclear or out of date in this chapter? Tell us and we will fix it for everyone. Your email is only used to reply.