Neurosurgery
Brain, spine and nerves: how the skull is opened and closed in layers, how the spine is freed and fused, how a trapped nerve is set loose, and the habits that protect tissue that cannot grow back.
1What neurosurgery covers
Neurosurgery operates on the brain, the spine and the peripheral nerves. To reach them the surgeon usually has to cut through or remove bone, so a neurosurgical setup carries soft tissue instruments and bone instruments side by side, and spine cases share many tools with orthopedicor-thuh-PEE-dikHaving to do with the bones, joints, muscles, ligaments and tendons, and the branch of medicine that treats them.orth/o straightped/o child (the field began with straightening children's bones)-ic relating toFull entry (chapter 39).
Nervous tissue, unlike most of the body, does not grow back after injury or disease, and the tissue of the brain and spinal cord is delicate, as are the instruments made to handle it. Neurosurgeons remove tumors, relieve pain, treat injuries and diseases that threaten life, and restore function that a disease has taken away.
The Core Curriculum sorts the cases into three groups: the peripheral nerves, the spine and the craniumKRAY-nee-umThe part of the skull that encloses and protects the brain.crani/o skullFull entry . Each group has open and minimally invasive approaches; the minimally invasive ones it names are endoscopicen-doh-SKOP-ikDone with an endoscope, a thin tube with a light and camera passed into the body.endo- within-scopic viewingFull entry , percutaneous (through the skin) and robot-assisted, and image-guided navigation is used both in the skull and on the spine. As in every specialty, any approach other than open counts as minimally invasive surgery (MIS), and cases that share instruments, positions and steps are taught together as co-related procedures. Neurologic surgery is one of the specialties in your clinical case count.
Neurosurgical patients are often very frightened. Before brain surgery a patient may fear not waking up, or losing sight, hearing, the ability to move or the ability to think. A patient who looks unaware, or even unconscious, may be fully aware of what is happening, so talk to the patient and explain it.
Other chapters hold the background this one builds on: the nervous system, the autonomic nervous systemaw-tuh-NOM-ik NUR-vus SIS-tumThe part of the nervous system that controls body functions without conscious thought, such as heart rate, breathing and digestion.auto- selfnom/o law, control-ic relating toFull entry included, and the cerebrospinal fluidser-uh-broh-SPY-nul FLOO-idThe clear, watery fluid that bathes and cushions the brain and spinal cord.cerebr/o brainspin spine-al relating toFull entry (CSF) in chapter 4; the vertebral columnVER-tuh-brul KOL-umThe spine: the column of small bones (vertebrae) that runs down the back and surrounds the spinal cord.vertebr joint, vertebra-al relating toFull entry in chapter 3; hemostatichee-moh-STAT-ikStopping bleeding; also, a product or agent used to stop bleeding.hem/o blood-stasis stopping, standing still-ic relating toFull entry , bone wax and cottonoids in chapter 29; the microscope in chapter 23; navigation and robots in chapter 21; fluoroscopyfloo-ROS-kuh-peeAn x-ray method that shows moving pictures of the inside of the body in real time.fluor/o glowing (from the fluorescent screen)-scopy looking, viewingFull entry and radiationray-dee-AY-shunEnergy that travels as waves or particles, such as X-rays, used to make images or treat cancer; also pain that spreads from its starting point.radi/o rays, radiation-ation processFull entry safety in chapter 22; positioning in chapter 31; and craniosynostosis in chapter 38. Each case below links to its setup card, which holds the full instrument list and every step; here you get the reasons, and the moments when the scrub matters most.
2Anatomy at the surgical field
From the scalp to the brain
A craniotomykray-nee-OT-uh-meeSurgery in which a piece of the skull is removed to reach the brain, and usually put back at the end.crani/o skull-tomy cutting intoFull entry passes through the same layers every time, and closes them in reverse. Chapter 4 teaches the meningesmuh-NIN-jeezThe three thin layers of tissue that cover and protect the brain and spinal cord.mening/o membraneFull entry themselves; here is what each layer means at the field.
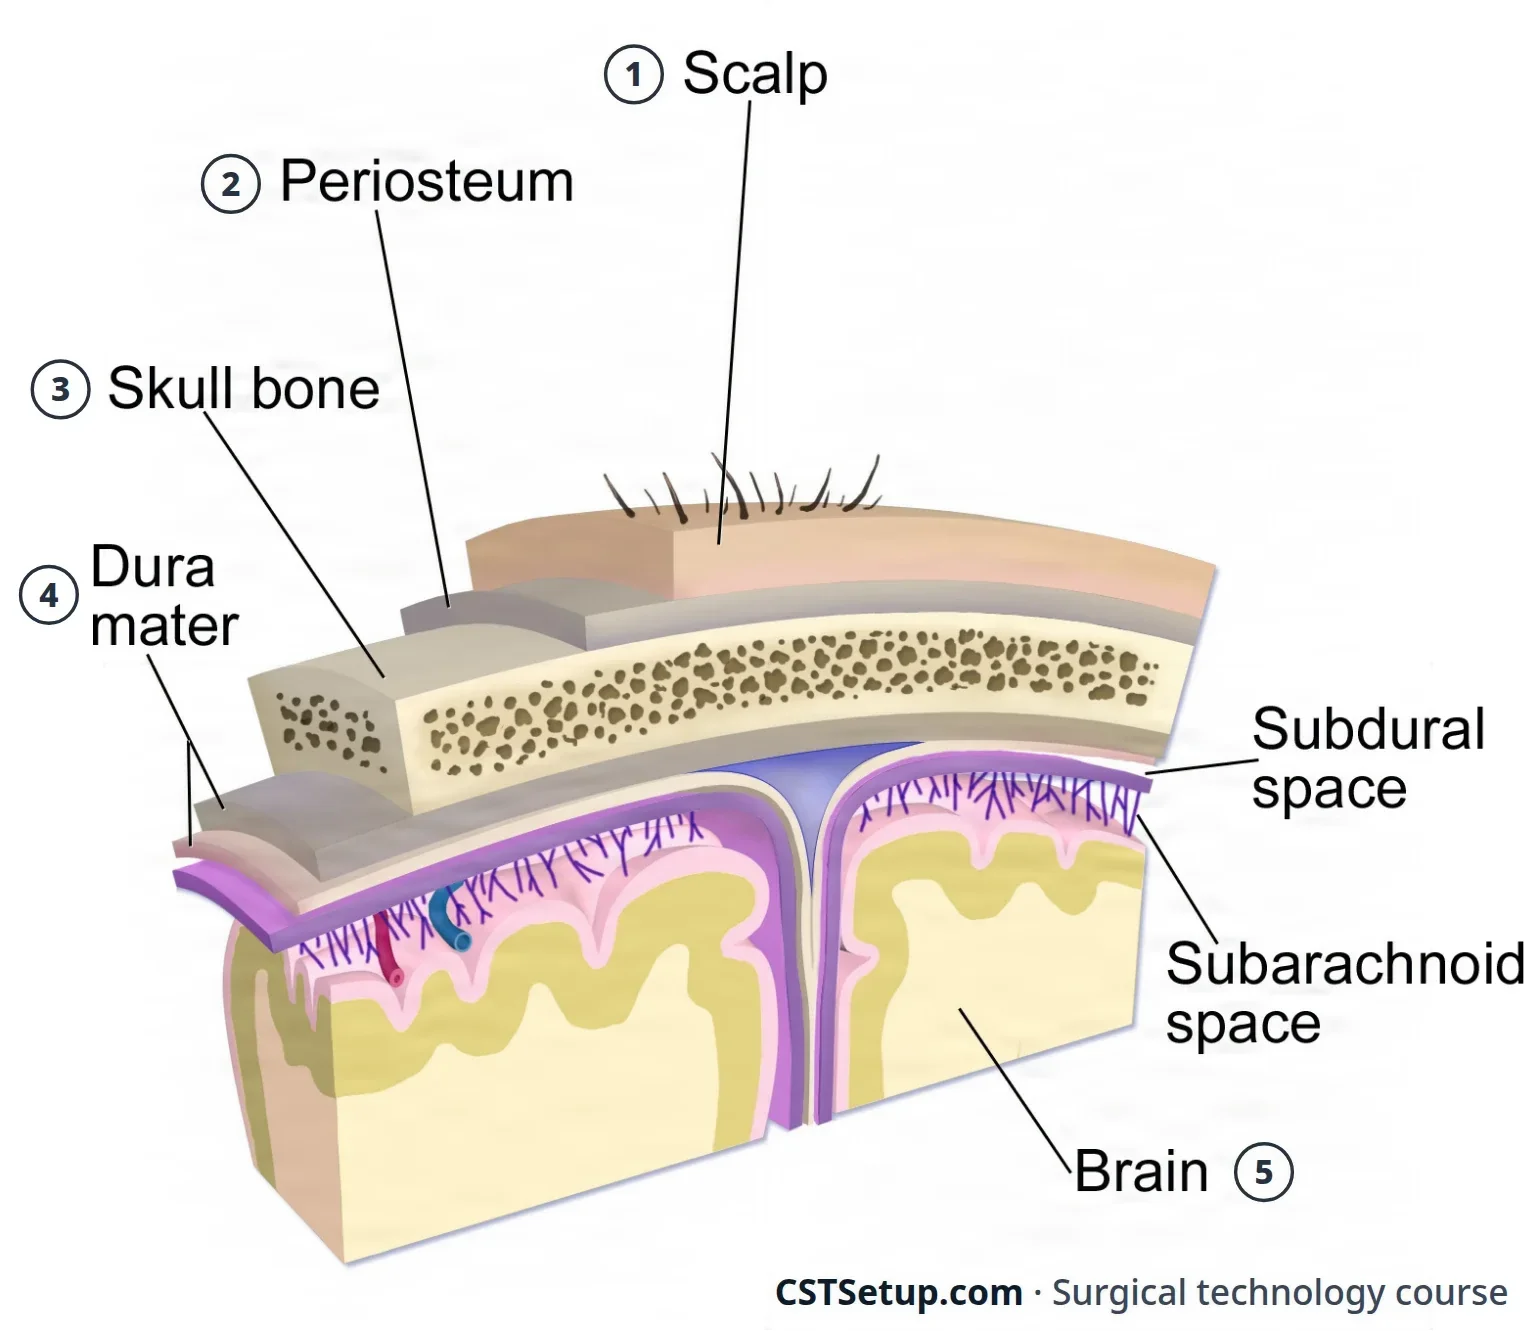
- Scalp: thick skin full of hair folliclehair FOL-ih-kulA small tube-shaped pocket in the skin from which a hair grows.Full entry , over a layer of tissue with a rich blood supply, then muscle and the galea, a tough fibrousFY-brusMade of or containing tough threads (fibers), especially of connective tissue.fibr/o fiber-ous full of, relating toFull entry sheet. The scalp bleeds freely when it is cut.
- Pericranium: the periosteum of the skull, lifted off the bone with a periosteal elevator.
- Skull: the bones chapter 3 names, joined at seams called sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry . Each bone has an outer and an inner table; a burr hole is through when the inner table is perforationper-fuh-RAY-shunA hole that goes all the way through the wall of an organ or tissue.per- throughforat bored (a hole)-ion processFull entry and the duraDOOR-uhThe tough outer layer of the membranes that cover the brain and spinal cord.Full entry shows.
- Dura mater: the tough, fibrous outer covering, whose folds and venous sinusSY-nusA hollow space in the body, most often one of the air-filled spaces in the skull bones around the nose.Full entry chapter 4 teaches. A sinus torn during surgery bleeds hard and can draw in air, a venous air embolismEM-buh-liz-umThe blocking of a blood vessel by a mass carried there in the blood (an embolus), such as a clot, fat or an air bubble.embol/o plug-ism conditionFull entry , so the surgeon frees the dura from the bone before cutting a bone flap.
- Arachnoid, pia and the brain: the delicate web of the arachnoid, the cerebrospinal fluidser-uh-broh-SPY-nul FLOO-idThe clear, watery fluid that bathes and cushions the brain and spinal cord.cerebr/o brainspin spine-al relating toFull entry beneath it in the subarachnoid spacesub-uh-RAK-noyd SPAYSThe space between two of the thin membranes that cover the brain and spinal cord, filled with cerebrospinal fluid.sub- belowarachn spider (the arachnoid layer looks like a web)-oid likeFull entry , and the pia on the surface of the brain.
The brain's blood supply
The internal carotidkuh-ROT-idHaving to do with the carotid arteries, the two large arteries on each side of the neck that carry blood to the head and brain.Full entry and vertebral arteries feed the circle of Willis, the ring of arteries under the brain that chapter 5 teaches. The anterior and middle cerebralsuh-REE-brul or SAIR-uh-brulHaving to do with the brain, especially the cerebrum, its largest part.cerebr/o brain, cerebrum-al relating toFull entry arteries come off the internal carotids; the posterior cerebral arteries come from the basilar artery.
The brain receives about a fifth of the heart's output and can store very little oxygen or glucose, so it cannot go long without blood. It holds its own blood flow steady as the blood pressure rises and falls, but that control usually fails when the mean arterial pressureMEEN ar-TEER-ee-ul PRESH-erThe average pressure in the arteries over one heartbeat, used as a measure of how well blood reaches the organs.Full entry drops below 60 mm Hg. aneurysmAN-yuh-riz-umA weak spot in the wall of an artery that bulges outward like a balloon.aneurysm a widening (Greek)Full entry form most often where these arteries branch.
The spine and the spinal cord
Chapter 3 teaches the vertebrae, and chapter 4 the cord, where it ends, the cauda equina below it and the meninges around it. A layer of fat separates the dura from the bone of the canal. The cord's arteries, the anterior spinal artery and the posterior spinal arteries, come from the vertebral arteries.
What lies in front of the spine matters as much as what lies behind it, because an instrument that goes too deep meets it:
- The neck: an anterior approach works in the plane between the carotid artery on the outside and the tracheaTRAY-kee-uhThe windpipe: the tube that carries air from the throat to the lungs.Full entry and esophagusih-SOF-uh-gusThe muscular tube that carries food and liquid from the throat to the stomach.esophag/o esophagusFull entry toward the midlineMID-lineAn imaginary line down the center of the body; also, a type of IV catheter placed in a vein of the upper arm.Full entry .
- The chest: the aortic arch sits at about T4, and below that the aorta descends along the left of the vertebral bodies to T12. The upper thoracicthuh-RAS-ikRelating to the chest, or to the middle part of the spine.thorac/o chest-ic relating toFull entry spine (T1 to T4) is reached from the right, away from the arch and the heart; the lower thoracic spine is reached from the left, because the aorta stands handling better than the vena cavaVEE-nuh KAY-vuhOne of the two large veins that return oxygen-poor blood from the body to the right atrium of the heart.Full entry .
- The lower back: the aorta and vena cava lie just in front of the lumbarLUM-barHaving to do with the lower back, the part of the spine between the ribs and the pelvis.Full entry vertebrae, which is why the surgeon takes care never to reach past the front of a disc.
Peripheral nerves
A nerve is a cable. Each axonAK-sonThe long, thin part of a nerve cell that carries electrical signals away from the cell body.Full entry is wrapped in endoneurium, the axons are bundled into fascicles wrapped in perineurium, and the whole nerve is wrapped in epineurium. Two nerves that chapter 4 traces are trapped often enough to need surgery: the median nerve, under the flexor retinaculum (transversetrans-VERSLying across something, at a right angle to its length.Full entry carpal ligament) at the wrist, and the ulnar nerve, in the cubital tunnel behind the elbow, the "funny bone". The ulnar nerve carries feeling from the little finger and half the ring finger, and drives most of the hand's small muscles.
3How the problem is found
The neurologic exam
The neurosurgeon's exam looks at gait, speech and mental statusMEN-tul STAT-usA person's state of mind at a given time: how alert they are, what they know and how they think, speak and behave.Full entry ; muscle tone, strength, reflexREE-fleksAn automatic body response to something that stimulates it, which happens without thought, such as the knee jerk.Full entry and flexibility; balance and coordination, which test the cerebellumser-uh-BEL-umThe part of the brain at the back, under the cerebrum, that coordinates movement, balance and posture.Full entry ; and the cranial nerveKRAY-nee-ul NERVOne of the 12 pairs of nerves that come straight from the brain and brainstem rather than the spinal cord.Full entry , along with most of the testing of sensation. Many neurologic problems cannot be seen, so the exam does the looking.
Before surgery the team records a baseline neurologic assessment, so changes after surgery can be measured against it: level of consciousnessLEV-ul uv KON-shus-nisHow awake, alert and aware of their surroundings a person is.Full entry and orientation, vision, the pupils and eye movements, strength and sensation in the limbs, and pain. The level of consciousness is scored on the Glasgow Coma ScaleGLAS-goh KOH-muh SKAYLA scoring tool that rates a person's level of consciousness by their eye opening, verbal response and movement, from 3 to 15.Full entry (chapter 13), and a muscle strength scale grades the limbs of a patient with a spinal cord injurySPY-nul KORD IN-juh-reeDamage to the spinal cord that disrupts signals between the brain and the body below the injury.Full entry or one having spine surgery.
Tests and scans
| Test | What it shows | When you meet it |
|---|---|---|
| computed tomographykum-PYOO-tid toh-MOG-ruh-feeAn imaging test that uses x-rays and a computer to make cross-section pictures of the inside of the body.tom/o cut, slice-graphy process of recordingFull entry | X-ray slices, with or without contrastKON-trastA dye or other substance given before an imaging test so body parts show up more clearly.Full entry | The first scan after a head injury and for bleeding inside the skull; 3D CTAsee-tee-ay (said as letters)Computed tomography angiography: a CT scan with IV contrast dye that shows blood vessels in detail.Full entry rebuilds the vessels from a contrast scan |
| magnetic resonance imagingmag-NET-ik REZ-uh-nunts IM-uh-jingAn imaging test that uses a strong magnet and radio waves to make detailed pictures of the inside of the body.Full entry | Detailed slices in three planes, with no ionizing radiationray-dee-AY-shunEnergy that travels as waves or particles, such as X-rays, used to make images or treat cancer; also pain that spreads from its starting point.radi/o rays, radiation-ation processFull entry | The best study for tumors, abscessAB-sesA closed pocket of pus in tissue, walled off by the body.Full entry , ligament injuries and disc herniationher-nee-AY-shunThe bulging or pushing of an organ or tissue through an opening or weak spot into a place where it does not belong.herni/o hernia, rupture-ation processFull entry ; some ORs scan during surgery |
| Functional MRI | The areas that light up while the patient speaks or moves | Maps speech and movement before surgery, so the surgeon can avoid them |
| Stereotactic CT or MRI | A scan with a head frame or fiducials in place | The coordinates for stereotactic surgery |
| angiographyan-jee-OG-ruh-feeAn imaging test that shows blood vessels by injecting a contrast dye and taking x-ray, CT or MRI pictures.angi/o vessel-graphy process of recordingFull entry , digital subtraction angiography, MR angiography | The vessels, filled with contrast or imaged by MRI | aneurysmAN-yuh-riz-umA weak spot in the wall of an artery that bulges outward like a balloon.aneurysm a widening (Greek)Full entry , arteriovenousar-teer-ee-oh-VEE-nusRelating to both arteries and veins, or joining an artery to a vein.arteri/o arteryven/o vein-ous relating toFull entry malformationmal-for-MAY-shunA body part or organ that formed in an abnormal way before birth.mal- badformation shapingFull entry and narrowed arteries; chapter 22 teaches angiography |
| Myelography | Contrast in the space around the spinal cord | The cord and nerve roots; largely replaced by MRI |
| Discography | Contrast injected into a disc while the patient reports the pain | Shows whether a disc is the source of back pain |
| Ultrasound | Sound-wave images | Blood flow in the neck vessels before surgery; cysts, tumors and the ventricleVEN-trih-kulOne of the two lower chambers of the heart, or one of the fluid-filled spaces inside the brain.Full entry during surgery |
| electroencephalogramih-lek-troh-en-SEF-uh-loh-gramA test that records the electrical activity of the brain through small sensors placed on the scalp.electr/o electricityencephal/o brain-gram recordFull entry | The brain's electrical activity | seizureSEE-zherA sudden burst of abnormal electrical activity in the brain that changes movement, feeling, behavior or awareness.Full entry , head injury and dementiadih-MEN-shuhA long-term, usually worsening decline in memory and thinking that is serious enough to affect daily life.de- away fromment mind-ia conditionFull entry ; during surgery, seizure foci and the brain's activity when a vessel is clamped |
| electromyographyih-lek-troh-my-OG-ruh-feeA test that records the electrical activity of muscles, usually through thin needles placed in the muscle.electr/o electricitymy/o muscle-graphy recordingFull entry and nerve conductionkun-DUK-shunThe passing of something, such as an electrical signal or heat, from one place to another through a material.Full entry | How fast motor nerves conduct, through needle electrodes in the muscle | Nerve damage from a herniated disc, spondylosis or a trapped nerve |
| Somatosensory evoked potentials (SSEPs) | Signals from a stimulated nerve up to the brain | Before surgery to judge nerve damage; during spine, carotidkuh-ROT-idHaving to do with the carotid arteries, the two large arteries on each side of the neck that carry blood to the head and brain.Full entry and aneurysm surgery to warn of injury |
| lumbar punctureLUM-bar PUNK-cherA procedure in which a needle is put between two bones in the lower back to take out spinal fluid or give medicine; a spinal tap.lumb/o lower backpuncture piercingFull entry | cerebrospinal fluidser-uh-broh-SPY-nul FLOO-idThe clear, watery fluid that bathes and cushions the brain and spinal cord.cerebr/o brainspin spine-al relating toFull entry pressure and a sample of the fluid | Infection, bleeding and hydrocephalushy-droh-SEF-uh-lusA buildup of too much cerebrospinal fluid inside the spaces (ventricles) of the brain.hydr/o watercephal/o head-us noun endingFull entry ; never done when a mass in the skull is suspected, because the sudden drop in pressure can make the brain herniate |
The patient's scans must be in the room, or loaded on the OR computer, before the case begins, because the surgeon uses them to find the problem, confirm the side and level, and plan the approach.
4Neurologic disease
Pressure inside the skull
The skull is a closed box (chapter 4). intracranial pressurein-truh-KRAY-nee-ul PRESH-erThe pressure inside the skull, made by the brain, the blood and the fluid around the brain.intra- insidecrani/o skull-al relating toFull entry (ICP) is the pressure that the brain tissue, the blood and the cerebrospinal fluidser-uh-broh-SPY-nul FLOO-idThe clear, watery fluid that bathes and cushions the brain and spinal cord.cerebr/o brainspin spine-al relating toFull entry exert inside it. A mass such as a tumor or a blood clot, cerebral edemaseh-REE-brul eh-DEE-muhSwelling of the brain caused by extra fluid in the brain tissue.cerebr/o brain-al relating toedema swellingFull entry (cerebral edema), more CSF made or less absorptionub-ZORP-shunThe taking in of a substance, such as a drug or a nutrient, into the bloodstream.Full entry , or blocked venous drainage all raise it, and increased intracranial pressurein-KREEST in-truh-KRAY-nee-ul PRESH-erPressure inside the skull that has risen above the normal range.Full entry that keeps climbing can push part of the brain out of its compartment, a herniationher-nee-AY-shunThe bulging or pushing of an organ or tissue through an opening or weak spot into a place where it does not belong.herni/o hernia, rupture-ation processFull entry . When the temporal lobeTEM-puh-rul LOHBThe part of each side of the brain, above the ear, that handles hearing, memory and understanding language.Full entry herniates, it presses on the third cranial nerveKRAY-nee-ul NERVOne of the 12 pairs of nerves that come straight from the brain and brainstem rather than the spinal cord.Full entry and the pupil on that side widens.
The team lowers the pressure in several ways. mannitolMAN-ih-tolAn osmotic diuretic, given by IV, that draws water out of tissues into the blood so the kidneys can remove it.Full entry , given into a vein, often with furosemidefyoo-ROH-suh-mideA loop diuretic: a drug that makes the kidneys remove more salt and water from the body.Full entry , draws water out of the tissues into the blood for the kidneys to remove. CSF can be drained through a ventricleVEN-trih-kulOne of the two lower chambers of the heart, or one of the fluid-filled spaces inside the brain.Full entry catheter or a lumbarLUM-barHaving to do with the lower back, the part of the spine between the ribs and the pelvis.Full entry drain. During surgery, the anesthesia provideran-us-THEE-zhuh pruh-VY-derThe licensed professional who gives anesthesia and watches over the client's breathing and vital functions during a procedure.Full entry may briefly hyperventilationhy-per-ven-tih-LAY-shunBreathing faster or deeper than the body needs, so too much carbon dioxide is breathed out.hyper- above, excessiveventilation moving air in and out of the lungsFull entry the patient to relax the brain. When swelling cannot be controlled, the surgeon may leave the bone flap out, a decompressive craniectomy, so the brain can swell outward.
Tumors
An intracranialin-truh-KRAY-nee-ulInside the skull.intra- withincrani/o skull-al relating toFull entry tumor is either primary, growing from the brain's own tissue or its coverings, or secondary, spread from a cancer elsewhere (a metastasismuh-TAS-tuh-sisThe spread of cancer cells from where the cancer started to other parts of the body.meta- change, beyondstasis standing, placeFull entry ). Primary brain tumorBRAYN TOO-merAn abnormal mass of cells growing in or on the brain, which may be cancerous or not.Full entry seldom spread outside the brain and spinal cord. The most common sign is a neurologic deficit that slowly worsens, often weakness; headache, seizureSEE-zherA sudden burst of abnormal electrical activity in the brain that changes movement, feeling, behavior or awareness.Full entry and loss of vision or hearing are also common, and a first seizure in an adult often means a tumor. Tumors are graded from I, slow-growing and benign, to IV, malignant, aggressive and quick to recurrencerih-KER-ensThe return of a disease or symptom after a period when it had gone away.re- againcur run-ence state ofFull entry .
| Tumor | What it is |
|---|---|
| Glioma | A tumor of the glial cells, the brain's supporting cells; the most common malignant brain tumor. A malignant glioma usually cannot be removed completely, so the surgeon takes as much as is safe. Oligodendrogliomas, of the cells that make myelinMY-uh-linThe fatty covering wrapped around many nerve fibers that protects them and speeds up their signals.myel/o marrow, the spinal cord (myelin was first seen as a marrow-like core of nerves)Full entry , and ependymomas, of the cells that line the ventricles, are gliomas too |
| Astrocytoma | The commonest glioma, grown from astrocytes, star-shaped glial cells. In children it usually forms in the cerebellumser-uh-BEL-umThe part of the brain at the back, under the cerebrum, that coordinates movement, balance and posture.Full entry , in adults in the cerebrumsuh-REE-brumThe largest part of the brain, made of two halves, that handles thinking, memory, language, sensation and voluntary movement.Full entry |
| Glioblastoma | A grade IV astrocytoma that grows fast, infiltrates the brain with finger-like extensions and can cross to the other hemisphere; surgery and radiationray-dee-AY-shunEnergy that travels as waves or particles, such as X-rays, used to make images or treat cancer; also pain that spreads from its starting point.radi/o rays, radiation-ation processFull entry help, but survival is poor |
| Medulloblastoma | A tumor of neural precursor cells, the immature cells that would have become neuronNOOR-onA nerve cell: a cell that carries electrical and chemical signals through the nervous system.neur/o nerveFull entry , in the cerebellum and fourth ventricle of young children; fast-growing, though it often responds to antineoplastican-tee-nee-oh-PLAS-tikA drug used to treat cancer by killing cancer cells or stopping them from growing and dividing.anti- againstneo- newplas growth, formation-tic relating toFull entry and radiation |
| Meningioma | Grows from arachnoid cells and attaches to the duraDOOR-uhThe tough outer layer of the membranes that cover the brain and spinal cord.Full entry ; the most common primary brain tumor, about a third of them, usually benign and slow. It can be very vascular and stick to a venous sinusSY-nusA hollow space in the body, most often one of the air-filled spaces in the skull bones around the nose.Full entry or a major artery |
| Vestibular schwannoma (acoustic neuroma) | A benign tumor of the Schwann cells of the balance part of cranial nerve VIII, inside the internal auditory canal; it causes hearing loss and ringing in one ear and can grow against the brain stemBRAYN STEMThe lowest part of the brain, which connects it to the spinal cord and controls breathing, heart rate and other automatic functions.Full entry |
| Pituitary adenomaad-uh-NOH-muhA tumor of gland tissue that is not cancer.aden/o gland-oma tumorFull entry | A tumor of the pituitary glandpih-TOO-ih-tair-ee glandA gland the size of a pea, hanging below the brain, whose hormones control many other glands.Full entry ; about 70 percent secretionsih-KREE-shunA substance a gland or cell makes and releases, such as mucus, saliva, sweat or a hormone.Full entry too much of a hormone. A microadenoma is under 1 cm, a macroadenoma larger, and a large one can press on the optic chiasm and take away part of the field of vision |
| Craniopharyngioma | A solid and cystic tumor near the pituitary stalk, often with diabetes insipidusdy-uh-BEE-teez in-SIP-ih-dusA disorder of antidiuretic hormone: the body makes too little of it, or the kidneys do not respond to it.Full entry and changes in the visual fields |
| Metastasis | About half of the brain tumors seen in practice, most often from lung or breast cancer or melanomamel-uh-NOH-muhA cancer that starts in melanocytes, the cells that give skin its color.melan/o black, dark-oma tumorFull entry |
The spine's most frequent tumors are metastases, and spinal tumors are named for where they sit: outside the dura (extradural), or inside it, either outside the cord (intradural extramedullary) or within it (intramedullary).
Treatment combines surgery, radiation (including stereotactic radiosurgery), chemotherapy, steroidSTAIR-oydA fat-based chemical built from cholesterol; the group includes hormones such as cortisol and estrogen, and many drugs.ster/o solid-oid likeFull entry to control swelling and drugs to prevent seizures.
Vascular disease
- aneurysmAN-yuh-riz-umA weak spot in the wall of an artery that bulges outward like a balloon.aneurysm a widening (Greek)Full entry : a weak spot in an artery wall that balloons out, most often at a branch point of the circle of Willis. When it ruptures, blood fills the subarachnoid spacesub-uh-RAK-noyd SPAYSThe space between two of the thin membranes that cover the brain and spinal cord, filled with cerebrospinal fluid.sub- belowarachn spider (the arachnoid layer looks like a web)-oid likeFull entry , a subarachnoid hemorrhagesub-uh-RAK-noyd HEM-er-ijBleeding into the fluid-filled space between the two inner layers of tissue that cover the brain.sub- underarachn/o spider (the web-like arachnoid layer)-oid likeFull entry , and the patient describes "the worst headache" of their life. The danger does not end there: the vessels can go into spasmSPAZ-umA sudden, involuntary tightening of a muscle or of the muscle in a hollow organ or tube.Full entry (vasospasm), with the greatest risk 4 to 10 days after the bleed, and the patient can develop ischemiais-KEE-mee-uhToo little blood flow to a part of the body, so the tissue does not get enough oxygen.isch- hold back-emia blood conditionFull entry , hydrocephalushy-droh-SEF-uh-lusA buildup of too much cerebrospinal fluid inside the spaces (ventricles) of the brain.hydr/o watercephal/o head-us noun endingFull entry , rising ICP, diabetes insipidus or the syndrome of inappropriate antidiuretic hormoneSIN-drohm of in-uh-PROH-pree-it an-tee-dy-yoo-RET-ik HOR-mohnA condition in which the body releases more antidiuretic hormone than it needs, so the kidneys hold on to too much water.Full entry (SIADH), and can bleed again. Even with modern surgery the death rate is as high as 40 percent.
- arteriovenousar-teer-ee-oh-VEE-nusRelating to both arteries and veins, or joining an artery to a vein.arteri/o arteryven/o vein-ous relating toFull entry malformationmal-for-MAY-shunA body part or organ that formed in an abnormal way before birth.mal- badformation shapingFull entry (AVM): a tangle of thin-walled vessels joining arteries straight to veins with no capillaryKAP-ih-lair-eeOne of the tiniest blood vessels, joining the smallest arteries to the smallest veins.Full entry between. It is usually congenitalkun-JEN-ih-tulPresent at birth.con- withgen birth, origin-al relating toFull entry , often found between the ages of 20 and 40, and causes bleeding and seizures as it steals blood from the brain around it; other kinds, such as cavernous malformations, can bleed too.
- Intracerebral hemorrhageHEM-uh-rijA large loss of blood from a blood vessel, inside the body or out of it.hem/o blood-rrhage bursting forthFull entry : bleeding into the brain itself, the cause of stroke in many patients with high blood pressure, most often deep in the basal gangliaBAY-sul GANG-glee-uhGroups of nerve cells deep inside the brain that help start, stop and smooth out movements.Full entry , the cerebellum or the brain stem. A patient who is getting worse needs emergency surgery to control the pressure.
- epidural anesthesiaep-ih-DOOR-ul an-us-THEE-zhuhPain relief or numbness from an anesthetic drug given through a thin catheter into the space just outside the covering of the spinal cord.epi- upon, overdur/o dura (the tough covering of the spinal cord)-al relating toFull entry hematomahee-muh-TOH-muhA collection of blood, often clotted, that has leaked out of the blood vessels into the tissue.hem/o blood (here as hemat-)-oma swelling or massFull entry : arterial bleeding between the skull and the dura, usually from a middle meningeal artery torn by a blow to the head or a skull fracture. It can kill quickly, sometimes after a period with no symptoms while it grows.
- subdural hematomasub-DOO-rul hee-muh-TOH-muhA collection of blood between the brain's tough outer covering (the dura) and the brain.sub- underdur dura-al relating tohemat/o blood-oma massFull entry : venous bleeding from torn bridging veins, between the dura and the arachnoid. It collects more slowly and is acute, subacute or chronic; from about 2 weeks after the injury, a membrane forms around the liquefying blood.
- Ischemia and infarctionin-FARK-shunDeath of an area of tissue (an infarct) because its blood supply has been cut off.Full entry : ischemia is a temporary shortage of blood flow; an infarct is tissue that has died because its blood supply stopped. In the brain, plaquePLAKA deposit that builds up on a surface in the body, such as a sticky film of bacteria on teeth or a fatty buildup in an artery wall.Full entry most often forms where the internal carotidkuh-ROT-idHaving to do with the carotid arteries, the two large arteries on each side of the neck that carry blood to the head and brain.Full entry artery divides. Carotid endarterectomy (chapter 40) treats plaque in the neck, and a clot can be dissolved or pulled out through a catheter (chapter 22).
Hydrocephalus
Hydrocephalus is too much CSF: the ventricles swell and the pressure inside the skull rises. It can be present at birth, or come from a narrowed cerebralsuh-REE-brul or SAIR-uh-brulHaving to do with the brain, especially the cerebrum, its largest part.cerebr/o brain, cerebrum-al relating toFull entry aqueduct, a tumor or cyst in the ventricles, a subarachnoid hemorrhage, a tumor of the posterior fossaFOS-uhA shallow hollow or dip in a bone or on the body's surface.Full entry , an injury, spina bifidaSPY-nuh BIF-ih-duhA birth defect in which the bones of the spine do not close completely around the spinal cord.spina spinebifida split in two (Latin)Full entry or a Chiari malformation. In obstructive (noncommunicating) hydrocephalus something blocks the flow, most often at the aqueduct; in communicating hydrocephalus the pathways are open but the fluid is not absorbed, as after meningitismen-in-JY-tisInflammation of the meninges, the membranes that cover the brain and spinal cord.mening/o meninges-itis inflammationFull entry or a subarachnoid hemorrhage. An infant's head grows large and the scalp veins stand out. Normal pressure hydrocephalus, in older adults, causes dementiadih-MEN-shuhA long-term, usually worsening decline in memory and thinking that is serious enough to affect daily life.de- away fromment mind-ia conditionFull entry , an unsteady walk and loss of bladder control, a combination worth knowing because a shuntSHUNTA passage that moves blood or other fluid from one place to another, either made by a surgeon or present in the body.Full entry can help.
Treatment removes a blocking lesionLEE-zhunAn area of tissue that has been damaged or has changed from normal, such as a sore, wound, lump or spot.Full entry , opens a new path for the fluid (an endoscopicen-doh-SKOP-ikDone with an endoscope, a thin tube with a light and camera passed into the body.endo- within-scopic viewingFull entry third ventriculostomy) or drains it with a shunt or, in an emergency, a temporary ventricular catheter, all taught below.
Infections
- Meningitis: inflammation of the coverings of the brain and spinal cord, usually from an infection; bacterial meningitis is an emergency, and a CSF leak after surgery opens a way in for the germs.
- encephalitisen-sef-uh-LY-tisInflammation of the brain tissue.encephal/o brain-itis inflammationFull entry : inflammation of the brain itself, most often from a virus.
- Brain abscessAB-sesA closed pocket of pus in tissue, walled off by the body.Full entry : a pocket of pus, from an infection elsewhere such as bacterial endocarditisen-doh-kar-DY-tisInflammation of the inner lining of the heart, most often on the heart valves.endo- insidecardi/o heart-itis inflammationFull entry , a penetrating wound or bone fragments driven into the brain. It needs surgical drainage when it is not caught early. Several lesions at once may be an infection rather than tumors, so the team takes precautionprih-KAW-shunA step taken ahead of time to prevent harm, such as the infection-control practices used with every client.Full entry against spreading an unknown germ, and a stereotactic biopsy makes the diagnosis.
- Spinal epidural abscess: from a bone infection of the spine, germs carried in the blood, or germs carried in by surgery, a lumbar punctureLUM-bar PUNK-cherA procedure in which a needle is put between two bones in the lower back to take out spinal fluid or give medicine; a spinal tap.lumb/o lower backpuncture piercingFull entry or an epidural injection. It causes back and nerve pain and weakness that can progress to paralysispuh-RAL-uh-sisLoss of the ability to move a part of the body, and sometimes loss of feeling in it.para- beside, abnormal-lysis looseningFull entry , and it is treated by surgical decompression and irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry and 4 to 8 weeks of IV antibiotics.
Creutzfeldt-Jakob disease, a prion disease of the brain, needs special handling of instruments, with single-use instruments when possible; chapters 10 and 27 teach it.
Disorders of function and development
- epilepsyEP-ih-lep-seeA long-term brain condition in which a person has repeated seizures that are not caused by another illness.Full entry : recurrent seizures, bursts of abnormal electrical activity in the brain. Surgery can map where the seizures start, with electrodes on or in the brain, and remove that area or place a stimulator (chapter 4 teaches the vagus nerveVAY-gus nervThe 10th cranial nerve, which runs from the brain stem to the chest and belly and slows the heart and helps digestion.Full entry stimulator).
- Parkinson diseasePAR-kin-sun dih-ZEEZA slowly worsening brain disease in which the nerve cells that help control movement die off.Full entry : a slowly worsening disease of movement, with stiffness, tremorTREM-erShaking of a part of the body, such as the hands, in small rhythmic movements that the person cannot control.Full entry , poor balance and slowness. For patients who still respond to levodopalee-voh-DOH-puhThe main drug for Parkinson disease, which the brain turns into dopamine.Full entry , deep brain stimulation is the main surgical treatment.
- cerebral palsySER-uh-brul PAWL-zeeA group of lifelong disorders of movement and posture caused by damage to the developing brain before, during or soon after birth.cerebr/o brain-al relating topalsy paralysisFull entry : a group of movement disorders caused by lesions or abnormal development of the brain early in its growth; the disorders do not progress, though they often change. A selective rhizotomy (below) can ease leg spasticityspas-TIS-ih-teeMuscle stiffness and tightness that resists stretching, more strongly the faster a limb is moved.Full entry that drugs do not control.
- Dementia: a progressive decline in mental function that cannot be reversed; normal pressure hydrocephalus is one cause that surgery can treat.
- Spina bifida: a birth defect in which part of the vertebral columnVER-tuh-brul KOL-umThe spine: the column of small bones (vertebrae) that runs down the back and surrounds the spinal cord.vertebr joint, vertebra-al relating toFull entry does not close, most often in the lumbar and sacralSAY-krulHaving to do with the sacrum, the triangle-shaped bone at the base of the spine between the hip bones.Full entry spine, one of the neural tubeNOOR-ul TOOBThe hollow structure in an early embryo that develops into the brain and spinal cord.neur/o nerve-al relating toFull entry defects. It ranges from spina bifida occulta, with no deficit, to a meningocele, a sac of meningesmuh-NIN-jeezThe three thin layers of tissue that cover and protect the brain and spinal cord.mening/o membraneFull entry and CSF, to a myelomeningocele, in which the cord and nerve roots push out in a sac, a failure of the neural tube to close early in development.
Trauma
traumatic brain injurytraw-MAT-ik brayn IN-juh-reeDamage to the brain caused by an outside force, such as a blow or jolt to the head or an object entering the skull.Full entry (TBI) causes about a third of all trauma deaths, most often from falls and vehicle crashes. The first injury cannot be undone, so the whole effort goes to preventing the second one, from bleeding, swelling and rising pressure. A blunt blow injures by impact and by shearing as the moving brain stops against the skull; in the United States, gunshot causes most penetrating brain injuries. About 10 percent of people with a severe head injury also have a spinal cord injurySPY-nul KORD IN-juh-reeDamage to the spinal cord that disrupts signals between the brain and the body below the injury.Full entry , so the spine is checked as well.
A depressed skull fracture is lifted back into place at surgery; an open fracture is irrigated well and closed against infection; a fracture of the base of the skull can leak CSF from the nose or ear.
In spinal injury, a broken vertebra is far more common than an injured cord, and the cervicalSER-vih-kulRelating to the neck, or to the cervix, the lower end of the uterus.cervic/o neck, cervix-al relating toFull entry spine accounts for about a third of the fractures. The primary injury is the damage done at the moment of trauma; the secondary injury follows from the body's response to trauma, including the lethal triadTRY-adA group of three things, such as three signs that occur together.Full entry (chapter 11), and from moving and handling the patient. A complete lesion takes away all movement and feeling below it, an incomplete one only some.
Spine and nerve disease
- Degenerative disc disease and herniation: the most common problem neurosurgeons treat. The annulus tears, the nucleus escapes into the canal and presses on a nerve root, causing radiculopathy, pain and weakness along that nerve, most often at L4 to L5 or L5 to S1. Steroids, pain medicine, rest and epidural steroid injections come first, and surgery when they fail.
- Spondylosis: wear of the discs with age; as they lose fluid and collapse, bone spurs (osteophytes) grow along the canal. When it presses on the cord, a myelopathy, walking and balance suffer.
- stenosisstuh-NOH-sisNarrowing of a passage or opening in the body, such as a blood vessel, heart valve or the spinal canal.sten/o narrow-osis conditionFull entry : narrowing of the spinal canal by degenerating discs, bone spurs and buckled ligaments, squeezing the cord or nerves.
- Spondylolisthesis: one vertebral body slipping forward on the one below.
- Compression fracture: a vertebral body crushed, most often by osteoporosisos-tee-oh-puh-ROH-sisA condition in which bones lose density and become thin, weak and easy to break.oste/o bonepor/o pore, small opening-osis abnormal conditionFull entry , sometimes by a tumor or infection; most occur where the thoracicthuh-RAS-ikRelating to the chest, or to the middle part of the spine.thorac/o chest-ic relating toFull entry spine meets the lumbar (T12 to L2).
- Carpal tunnel syndrome: the median nerve squeezed in the carpal tunnel, by a narrow tunnel, a wrist fracture, arthritis, thickened synovium, pregnancy, obesity or repeated vibration and movement. It causes numbness, tingling and pain in the fingers and weakness of the thumb muscles, and is most common between 30 and 60 and in women.
- Cubital tunnel syndrome: the ulnar nerve squeezed at the elbow, from injury, elbow fractures or dislocationdis-loh-KAY-shunAn injury in which the ends of bones that meet at a joint are forced out of their normal position.Full entry , or repeated bending at work or play. It causes numbness in the fourth and fifth fingers, hand weakness and, when severe, a claw hand.
- Nerve injury: a nerve cut or crushed, usually in the hand or forearm, often by tools or machinery.
An epidural hematoma is arterial and can kill fast; a subdural hematoma is venous and slower. A first seizure in an adult often means a tumor, and a lumbar puncture is never done when a mass in the skull is suspected.
5Planning the case
Neurosurgical cases need a great deal of equipment, chosen and checked before the patient arrives: the bed and its attachments, any C-arm, navigation, neuromonitoring and cell salvage, the blood productBLUD PROD-uktAny part of donated blood prepared for transfusion, such as red cells, plasma or platelets.Full entry ordered, and any special instruments and supplies. The microscope needs a clear path to the field, and cords are kept out of the traffic. For surgery on the head, the bed is often turned 90 or 180 degrees away from the anesthesiaan-us-THEE-zhuhLoss of feeling or sensation, often brought on by drugs so that surgery or a procedure can be done without pain.an- withoutesthesi/o feeling, sensation-ia conditionFull entry machine, so the surgical team can reach the head; the anesthesia provideran-us-THEE-zhuh pruh-VY-derThe licensed professional who gives anesthesia and watches over the client's breathing and vital functions during a procedure.Full entry needs breathing circuit tubing long enough for the turn.
Positions
The position follows the part of the brain or spine the surgeon must reach. Chapter 31 teaches each position and its padding, and chapter 23 the spine frames and headrests; here is what neurosurgery adds.
- Supine: the frontalFRUN-tulRelating to the front of the body, or to the forehead and the bone or brain area behind it.Full entry , parietalpuh-RY-uh-tulRelating to the wall of a body cavity; also names a lobe of the brain and two bones of the skull.pariet/o wall-al relating toFull entry and temporal lobeTEM-puh-rul LOHBThe part of each side of the brain, above the ear, that handles hearing, memory and understanding language.Full entry , the front of the neck and the front of the lumbarLUM-barHaving to do with the lower back, the part of the spine between the ribs and the pelvis.Full entry spine. For a temporal approach the head is turned so that side faces up, with the shoulder on that side raised a little.
- Lateral: one temporal or occipital lobeok-SIP-ih-tul LOBEThe part of the brain at the back of the head that takes in and makes sense of what the eyes see.Full entry , the cerebellopontine angle, the brain stemBRAYN STEMThe lowest part of the brain, which connects it to the spinal cord and controls breathing, heart rate and other automatic functions.Full entry and cerebellumser-uh-BEL-umThe part of the brain at the back, under the cerebrum, that coordinates movement, balance and posture.Full entry , the front of the thoracicthuh-RAS-ikRelating to the chest, or to the middle part of the spine.thorac/o chest-ic relating toFull entry and lumbar spine, and the placement of nerve stimulators and pumps; its park bench variation, with the face turned slightly toward the floor, makes a brachial plexusPLEK-susA network of nerves or blood vessels that branch and join together.Full entry stretch more likely.
- Prone: the back of the spine and the posterior fossaFOS-uhA shallow hollow or dip in a bone or on the body's surface.Full entry , the body on a spine frame or table such as a Wilson frame or a Jackson table.
- Sitting (Fowler): some craniotomykray-nee-OT-uh-meeSurgery in which a piece of the skull is removed to reach the brain, and usually put back at the end.crani/o skull-tomy cutting intoFull entry at the back of the head. The surgeon sees well and the patient bleeds less, but the blood pressure can fall, the neck can bend enough to kink the airway, and the pressure in the head's veins can drop below the air pressure in the room, so air can be sucked into an open vein, a venous air embolismEM-buh-liz-umThe blocking of a blood vessel by a mass carried there in the blood (an embolus), such as a clot, fat or an air bubble.embol/o plug-ism conditionFull entry . The anesthesia provider may place a central venous catheterSEN-trul VEE-nus KATH-uh-terAn IV catheter whose tip sits in a large vein near the heart, used for long-term drugs, fluids, nutrition or blood draws.Full entry and a precordial Doppler ultrasoundDOP-ler UL-truh-soundAn ultrasound that uses sound waves to hear or show blood flowing through vessels or the fetal heartbeat.Full entry to listen for air in the heart (chapter 13).

In cranialKRAY-nee-ulRelating to the skull, or toward the head end of the body.crani/o skull-al relating toFull entry surgery at least one arm is tucked at the side so an instrument table fits over the patient; in cervicalSER-vih-kulRelating to the neck, or to the cervix, the lower end of the uterus.cervic/o neck, cervix-al relating toFull entry spine surgery both are tucked, so the surgeon can work from either side of the bed; for thoracic and lumbar cases the arms rest on armboards at less than 90 degrees. sequential compression devicesih-KWEN-shul kum-PRESH-un dih-VYSInflatable leg sleeves that fill with air and squeeze the legs in turns to keep blood moving in the veins.Full entry go on before inductionin-DUK-shunThe starting of a process on purpose, such as bringing on labor or putting a client under anesthesia.Full entry , the eyes are covered, and the head is kept above the heart to reduce bleeding.
Holding the head
Chapters 23 and 31 teach the donut and horseshoe headrests, which support the head without fixing it; a donut is enough for a superficial clot or tumor. When the head must not move at all, the surgeon uses a skull clamp, often called by a brand name, Mayfield: three sterile pins grip the skull and the clamp locks to a base unit on the bed, which leaves the head, face and airway open to view.
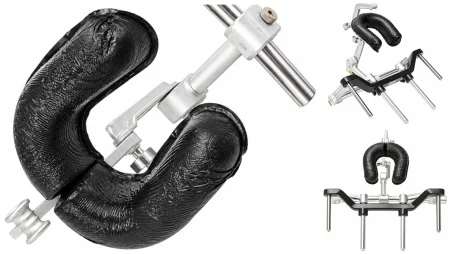


The clamp is placed after induction, and it is safe only if every step is right.
- The bed attachmentuh-TACH-mentThe deep emotional bond between an infant and a parent or caregiver.Full entry is mounted to the maker's instructions and checked before the patient is moved.
- Open the sterile pins onto a small sterile fieldSTAIR-ul feeldAn area set up with sterile drapes and supplies, kept free of all germs, for a sterile procedure.Full entry on a prep table; the surgeon covers their points with antibiotic or povidone-iodinePOH-vih-done EYE-uh-dineA brown antiseptic solution of iodine used to kill germs on the skin before procedures and on wounds.Full entry ointment.
- The surgeon places the clamp, two pins on the rocker arm and one on the other arm, keeping clear of the frontal sinusSY-nusA hollow space in the body, most often one of the air-filled spaces in the skull bones around the nose.Full entry , the temple, the eyes and the large vessels and nerves, and tightens it to the force the maker sets. The pins go only partway into the outer table of the skull.
- At least three people move the head: the anesthesia provider, who controls the airway; one person who holds the head in the clamp; and one who locks the clamp to the bed attachment. Every toothed joint must be fully engaged, and the person holding the head makes the final check that nothing moves.
- For a prone case the clamp goes on while the patient is still supine, the surgeon supports the head during the turn, and someone else locks it.
Pins are made in adult and child sizes, but the maker does not recommend them for children younger than 5. At the end of the case the same team takes the head out: the anesthesia provider holds the airway, one person holds the head and another releases the locks, and the surgeon confirms that all three pins are out; a bleeding pin site gets pressure or a stitch. Keep a firm hold on the head as it leaves the clamp, so it is never dropped.
Gardner-Wells tongs, fixed to the skull, hold the head in line or pull tractionTRAK-shunA steady pulling force applied to a body part with weights, ropes and pulleys.Full entry on the neck. A patient may arrive in a haloHAY-lohA ring shape: either a ring of light seen around lights, or a metal ring fixed to the skull to hold the neck still.Full entry , a ring fixed to the skull to hold an unstableun-STAY-bulDescribes a client whose condition is changing quickly or is hard to predict.Full entry neck; part of it must come off to reach the surgical site, so have the matching wrenches in the room.
never move a patient's body while the head is locked in a skull clamp. Release the head first, with the anesthesia provider controlling the airway.
Prep and drape
Hair is removed only on the surgeon's order (chapter 31), with clippers, outside the OR, and only as much as the incision needs; for some incisions a strip 1 to 2 cm wide is enough, and the rest of the hair is parted and held back with rubber bands or water-based gel. For the back of the neck, long hair is tied on top of the head and the nape is clipped up to about the level of the ears.
The surgeon marks the correct side of the head or the level of the spine, and the mark must show in the prepped field. A marking solution may be indigo carmine, gentian violet or brilliant green, but never methylene blue, which can inflame the brain and spinal cord. Keep prep solutions out of the eyes and ears. A bone or fat graftGRAFTTissue or a man-made material moved into place in surgery to replace or repair a damaged part.Full entry site, such as the iliacIL-ee-akHaving to do with the ilium, the large, wing-shaped upper part of the hip bone.Full entry crest or the abdomen, gets its own prep.
For a craniotomy, four or more towels square off the site, held with skin staples, nonperforating towel clips or silk sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry , and an adhesive drape keeps hair out of the incision. The craniotomy drape has a plastic pouch that hangs below the head to catch blood and irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry and drain them to suction. Have extra drapes, because the head is hard to cover well, and keep the drapes clear of any stereotactic frame. An overhead instrument table may go across the patient, its edge just below the chin, before draping; the craniotomy sheet goes over it and the instruments sit on top.

Room and equipment
A typical room has the overhead instrument table or two large Mayo standMAY-oh standA small tray on an adjustable stand placed over or beside the patient during surgery to hold the instruments used most often.Full entry and a large back table, sequential compression devices, a warming and cooling unit, one or two monopolar ESUs and a bipolarby-POH-lerHaving two poles or two opposite ends; most often used as a short form of bipolar disorder.bi- twopolar having polesFull entry unit, nitrogen to drive the air-powered tools, and usually two suctions; neurosurgeons usually wear loupes and may wear a headlight. Cell salvage is used in most spine surgery (chapter 12). Contamination or infection is not an absolute bar to it; the wound is first washed with antibiotic irrigation. Makers still advise against it with a malignant tumor; the surgeon and anesthesia provider decide, and a leukocyte filter is used in place of the usual one.
one reference still leaves cell salvage out whenever the patient has an infection or a cancer.
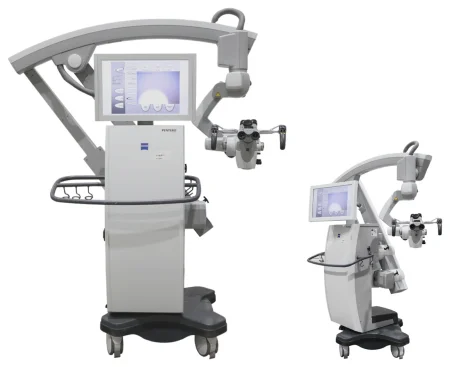
The microscope (chapter 23) magnifies about 6 to 40 times, against 2 or 3.5 times for loupes, with bright light down the line of sight. It also narrows the surgeon's view to a small circle, which changes your job:
- Know the procedure, the anatomy and every microinstrument by name, and watch the field on the video monitor so you can see what comes next.
- When the surgeon asks and holds out a hand, place the instrument in it the way it will be used, so the surgeon never looks away from the eyepieces.
- Keep the tips clean of blood and tissue, because the microscope magnifies the smallest speck.
- Microinstruments are bayonet shaped, so the surgeon's hand stays out of the line of sight, and they are fine, fragile and costly. Never hand over one that is bent, dulled or damaged; take it out of use for repair or replacement.

Neuromonitoring watches the nervous system during surgery: electroencephalogramih-lek-troh-en-SEF-uh-loh-gramA test that records the electrical activity of the brain through small sensors placed on the scalp.electr/o electricityencephal/o brain-gram recordFull entry over the brain, evoked potentials (SSEPs in spine surgery, hearing during an acoustic neuroma), and electromyographyih-lek-troh-my-OG-ruh-feeA test that records the electrical activity of muscles, usually through thin needles placed in the muscle.electr/o electricitymy/o muscle-graphy recordingFull entry to find nerves. A baseline is recorded before the incision. A significant change warns the team to change the position, move a retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry or an implant, or stop the resectionrih-SEK-shunSurgery to remove part of an organ or tissue.re- back, againsect to cut-ion processFull entry short. The anesthesia provider adjusts the drugs so the signals can be read.

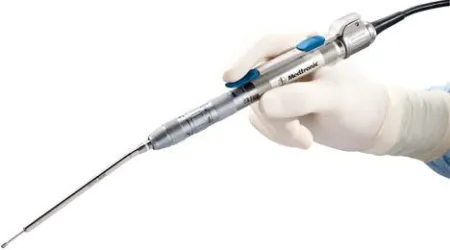
The ultrasonic aspirator breaks up tumor tissue with high-frequency vibration, washes it with saline from its tip and suctions it away, while sparing the nerves and vessels nearby. Its settings suit soft tumors or firm and calcified ones, and it is used when a lot of tissue must come out. Its disposable sleeve is one of the Core Curriculum's neurologic supplies.

Lasers and ultrasound: a carbon dioxideKAR-bun dy-OK-sideA gas made by the body's cells as waste, carried in the blood to the lungs and breathed out.Full entry laser removes small amounts of tissue precisely in tight places, and an Nd:YAG laser coagulationkoh-ag-yuh-LAY-shunThe process by which blood changes from a liquid into a gel, forming a clot.coagul clot-ation processFull entry the vessels around the target (chapter 20 teaches laser safety).
Power tools drill burr holes, cut bone flaps, thin bone, remove bone for a fusion and drill the holes for plates. They run on compressed nitrogen, a batteryBAT-uh-reeIn law, touching a person on purpose without their consent.Full entry or electricity. The craniotome drives a perforator bit for burr holes, in 12 mm and 7 mm sizes, with a clutch that stops the bit before it reaches the duraDOOR-uhThe tough outer layer of the membranes that cover the brain and spinal cord.Full entry ; changed to a saw blade with a dura guard (footplate), it cuts the bone flap.
- Keep every tool in the safety position except while it is in use.
- Irrigate the tip the whole time it runs, to keep heat off the tissue.
- Never rest a drill on the patient.
- Test every drill and saw before the case.

electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry (chapter 20): monopolar current is safe on the skin, galea, periosteum, muscle and bone, and is used freely to expose the back of the spine; the bipolar is safe on the dura and near nerves and vessels, with saline irrigation to keep its tips from sticking. Keep several bipolar forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry on the field and swap them as their tips coat with escharES-karThick, dry, dark dead tissue that covers part or all of a wound.Full entry .

Instrument sets
A craniotomy uses a minor set for the soft tissue and a basic craniotomy (neurological) set; spine cases use a laminectomy set or an anterior cervical set; peripheral nerve cases use a minor or plastic set; microinstruments and implant systems are added as needed.
- Bone: the Hudson brace and its bits, a Gigli saw with its handles and guide, rongeurron-ZHURA strong surgical instrument with sharp, cup-shaped jaws used to bite away small pieces of bone.Full entry (Kerrison, Leksell and others), pituitary rongeurs, curettekyoo-RETA surgical instrument with a small spoon- or loop-shaped tip used to scrape tissue.Full entry , gouges and osteotomes.
- Dissecting and elevating: Penfield dissectors, numbered 1 to 5, and periosteal elevators.
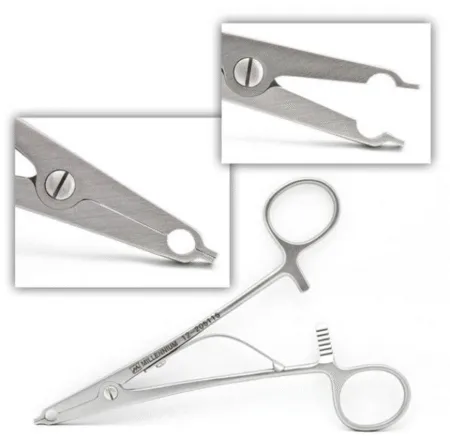
- Scalp: Raney clips and their applier or a scalp clip gun, and Dandy clamps.
- retractionrih-TRAK-shunA drawing back or pulling in of tissue; in breathing, the skin sinking in between, below or above the ribs with each breath.Full entry : self-retaining retractors for the scalp and muscles (Gelpi, Weitlaner, Adson-Beckman, cerebellar); a brain retractor system (such as the Leyla-Yasargil or Greenberg) that holds malleable brain spoons; and hand retractors, among them the Love and Scoville nerve root retractors.
- Dura and fine work: dura hooks, nerve hooks, dural separators, pituitary spoons, and bayonet, Cushing, Adson and Gerald forceps.
- Suction: Frazier or Adson tips in several sizes. Keep a 10 mL syringe of saline to flush a tip that clogs.
- Microsurgery: an arachnoid knife, bayonet microforceps, curettes, scissors, needle holders, dissectors and bipolar forceps.

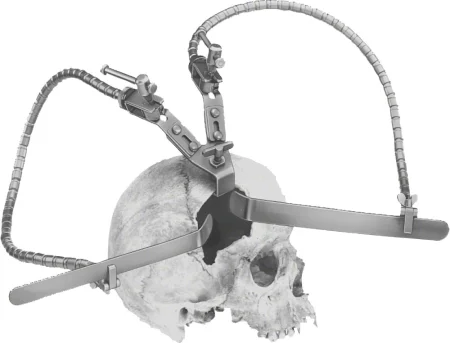
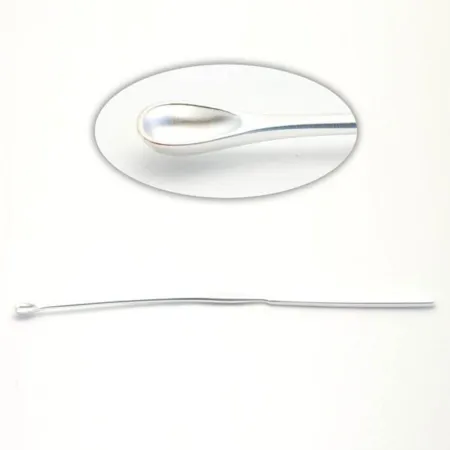
Implants: bone grafts, plates, screws, rods, clips, shuntSHUNTA passage that moves blood or other fluid from one place to another, either made by a surgeon or present in the body.Full entry , coils and antineoplastican-tee-nee-oh-PLAS-tikA drug used to treat cancer by killing cancer cells or stopping them from growing and dividing.anti- againstneo- newplas growth, formation-tic relating toFull entry wafers are all implants in neurosurgery. Handle each one with care, so it stays sterile and undamaged. When several go in, tell the circulator clearly where each one went, so the record shows every implant and its place; the FDA requires certain implants to be traceable (chapter 29).
Sponges and counts
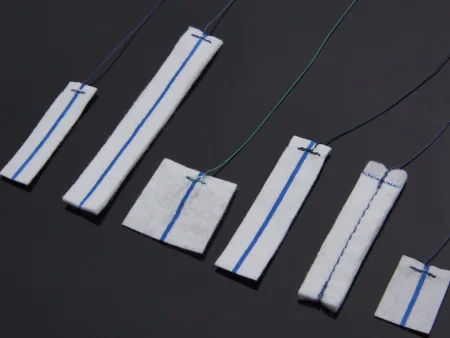
Gauze 4x4 sponges control bleeding until the skull or the spinal canal is opened. After that, the surgeon uses cottonoids (patties), the moist squares and strips of pressed cotton or rayon with X-ray detectable markerMAR-kerSomething that can be measured, such as a substance in the blood, that shows a disease or body process is present.Full entry and strings that chapter 29 teaches, because gauze is coarse and can tear the brain and spinal cord.
- Offer patties from a basin, a flat waterproof surface or a flat ribbon retractor. A moist patty laid on the brain protects it, and the surgeon suctions through a patty rather than straight onto neural tissue.
- Cotton balls with X-ray detectable strings can be packed gently into a bleeding tumor bed.
- Patties, cotton balls and scalp clips are all part of the count, and so are dura needles and the other small items. Take used patties off the field at once, onto an extra draped Mayo stand or small table where they can be counted, and check that each comes back whole, with its string.

Drugs and solutions
Label every drug and solution the moment it reaches the field (chapter 12). These are the ones you handle most in neurosurgery.
- hemostatichee-moh-STAT-ikStopping bleeding; also, a product or agent used to stop bleeding.hem/o blood-stasis stopping, standing still-ic relating toFull entry (chapter 29): thrombinTHROM-binAn enzyme in the blood that turns fibrinogen into fibrin, the threads that hold a blood clot together.thromb/o clot-in substanceFull entry , soaked into absorbable gelatin sponge or patties; oxidized cellulose; microfibrillar collagenKOL-uh-jenThe main structural protein of the body, which gives strength to skin, bones, tendons, ligaments and scar tissue.coll/a glue-gen producingFull entry . Cut the gelatin sponge and oxidized cellulose into the same sizes as the patties. The plant-based powder is not used in neurosurgery.
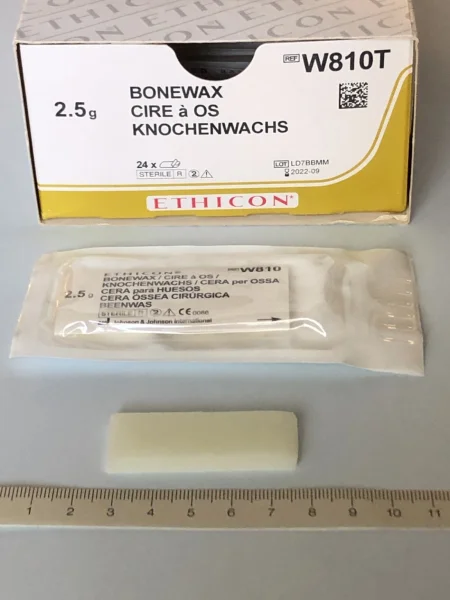
- Bone wax (chapter 29): kept ready for every cranial and spinal case; you can load a small ball of it on the tip of a #4 Penfield.
- Irrigation (chapter 29): warm saline, at body temperature (37°C) and no warmer, often with an antibiotic the surgeon chooses; a bulb or piston syringe, or a syringe with an angiocatheter tip for fine work under the microscope.
- Papaverine: on a patty over vessels to stop or prevent spasmSPAZ-umA sudden, involuntary tightening of a muscle or of the muscle in a hollow organ or tube.Full entry .
- local anestheticLOH-kul an-es-THET-ikA drug that blocks feeling in one part of the body without making the person unconscious.Full entry with epinephrineep-ih-NEF-rinA hormone and drug, also called adrenaline, that raises heart rate and blood pressure and opens the airways.Full entry : injected along the incision to numb it and to narrow the vessels, so the scalp bleeds less.
- Dural sealant and dural graft: a sealant or fibrin glue over the dural stitch line makes it watertight, and a graft, natural or synthetic, patches a gap.
- Chemotherapy wafers: after a malignant glioma is removed, the surgeon may line the cavity with dissolving wafers that release a chemotherapy drug, carmustine, straight into the surrounding brain. The Core Curriculum's supply list calls them radiationray-dee-AY-shunEnergy that travels as waves or particles, such as X-rays, used to make images or treat cancer; also pain that spreads from its starting point.radi/o rays, radiation-ation processFull entry wafers, but these wafers hold a drug, not a radioactive source. Radiation itself can be placed in or beside a tumor as small radioactive seeds, a technique called brachytherapybrak-ee-THAIR-uh-peeRadiation treatment in which a radioactive source is placed inside the body, in or right next to a tumor.brachy- short (a short distance)-therapy treatmentFull entry .
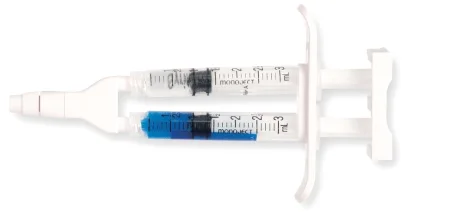

The anesthesia provider gives the prophylaxisproh-fuh-LAK-sisTreatment given to prevent a disease or problem, rather than to treat one that is already present.pro- beforephylax guardFull entry antibiotic within 60 minutes before the incision (within 2 hours for vancomycinvan-koh-MY-sinAn antibiotic, given by IV for serious gram-positive infections or by mouth for one bowel infection.Full entry ), and may give a steroidSTAIR-oydA fat-based chemical built from cholesterol; the group includes hormones such as cortisol and estrogen, and many drugs.ster/o solid-oid likeFull entry to limit swelling, a diureticdy-yoo-RET-ikA drug that makes the kidneys pass more water and salt out of the body as urine.dia- throughur/o urine-etic relating toFull entry such as mannitolMAN-ih-tolAn osmotic diuretic, given by IV, that draws water out of tissues into the blood so the kidneys can remove it.Full entry to relax the brain, and a drug to prevent seizureSEE-zherA sudden burst of abnormal electrical activity in the brain that changes movement, feeling, behavior or awareness.Full entry when the cortexKOR-teksThe outer layer of an organ, especially the folded gray outer layer of the brain.cortic/o cortex, outer layerFull entry will be handled. A urinary catheter is placed for a long case, heavy bleeding or diuretics. In spine surgery, vancomycin powder in the wound lowers the infection rate.
Drains, monitors and closing supplies
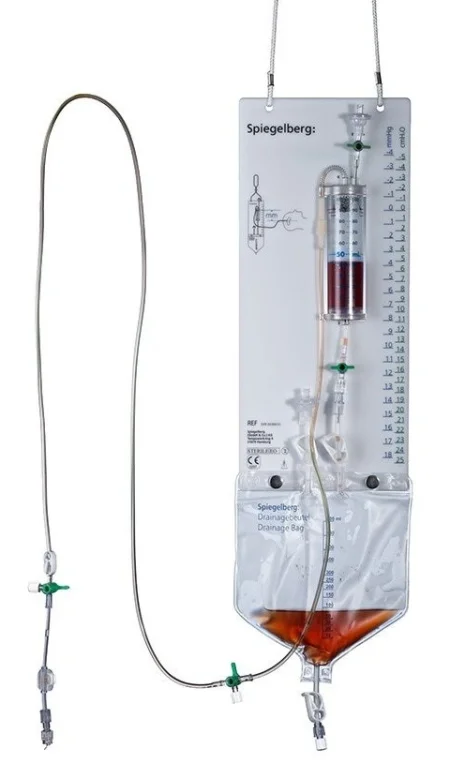
- Lumbar drain: a catheter in the subarachnoid spacesub-uh-RAK-noyd SPAYSThe space between two of the thin membranes that cover the brain and spinal cord, filled with cerebrospinal fluid.sub- belowarachn spider (the arachnoid layer looks like a web)-oid likeFull entry of the lower spine. Draining cerebrospinal fluidser-uh-broh-SPY-nul FLOO-idThe clear, watery fluid that bathes and cushions the brain and spinal cord.cerebr/o brainspin spine-al relating toFull entry relaxes the brain during aneurysmAN-yuh-riz-umA weak spot in the wall of an artery that bulges outward like a balloon.aneurysm a widening (Greek)Full entry and tumor surgery, and the drain also prevents or treats a CSF leak, which is most likely after posterior fossa and transsphenoidal operations. It is placed from a prepackaged kit on its own small sterile setup, and the anesthesia provider runs the stopcock.
- ventricleVEN-trih-kulOne of the two lower chambers of the heart, or one of the fluid-filled spaces inside the brain.Full entry catheter: placed through a burr hole into a ventricle, it drains CSF and is the most accurate way to measure intracranial pressurein-truh-KRAY-nee-ul PRESH-erThe pressure inside the skull, made by the brain, the blood and the fluid around the brain.intra- insidecrani/o skull-al relating toFull entry . A catheter with a pressure transducer in its tip is less invasive and less accurate and cannot drain. A disposable ICP kit holds what is needed to place a monitoring screw through a small drill hole.
- Both drains are a direct path into the central nervous systemSEN-trul NER-vus SIS-tumThe brain and the spinal cord together.centr/o center-al having to do withFull entry , so they are placed with strict aseptic technique, and their stopcocks and clamps must be set exactly as ordered: drain too much CSF and the brain can herniate.
- Wound drains: a closed suction drain, such as a Hemovac, may be brought out through a stab wound.
- Dressings: a spinal incision gets a nonadherent pad and gauze under tape. A head dressing is harder to keep in place: a nonadherent strip, gauze and fluffs, then rolled gauze wrapped around the head, which also presses on the wound to help prevent a hematomahee-muh-TOH-muhA collection of blood, often clotted, that has leaked out of the blood vessels into the tissue.hem/o blood (here as hemat-)-oma swelling or massFull entry .
Anesthesia
Most brain and spine surgery is done under general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry (peripheral nerve surgery below). Some operations need the patient awake for testing, as when electrodes are placed. When the neck is unstable or will not bend back, the breathing tube may be placed with the patient awake, guided by a fiberoptic scope. The anesthesia provider places enough IV access, often an arterial linear-TEER-ee-ul lineA thin catheter placed in an artery, often in the wrist, to measure blood pressure all the time and draw blood.Full entry , and sometimes a central line.
Most neurosurgery is long, so the anesthesia provider warms the gases and fluids and uses warm and forced-air blankets against the hypothermiahy-poh-THER-mee-uhA body temperature that has fallen below the normal range.hypo- belowtherm/o heat-ia conditionFull entry chapter 13 teaches; infants are especially at risk. Waking up should be smooth, without coughing or struggling, so the dressing often goes on before the reversal drugs are given, to avoid a surge in blood pressure.
6Operations on the brain and skull
Craniotomy: opening and closing
What and why: a craniotomykray-nee-OT-uh-meeSurgery in which a piece of the skull is removed to reach the brain, and usually put back at the end.crani/o skull-tomy cutting intoFull entry opens the skull by lifting out a piece of it, the bone flap, to reach the brain: to remove a tumor or a blood clot that a burr hole cannot reach, to stop bleeding, to clip or remove an abnormal vessel, to drain an abscessAB-sesA closed pocket of pus in tissue, walled off by the body.Full entry , or to take pressure off a cranial nerveKRAY-nee-ul NERVOne of the 12 pairs of nerves that come straight from the brain and brainstem rather than the spinal cord.Full entry . A burr hole, a single drilled hole, is the smallest opening into the skull. The opening and closing are the same in almost every brain operation; only the middle changes, so learn the pattern once.
The craniotomy is named for where it lies: frontalFRUN-tulRelating to the front of the body, or to the forehead and the bone or brain area behind it.Full entry , parietalpuh-RY-uh-tulRelating to the wall of a body cavity; also names a lobe of the brain and two bones of the skull.pariet/o wall-al relating toFull entry , temporal, occipitalok-SIP-ih-tulRelating to the back of the head.Full entry or a combination. A pterional craniotomy, centered where the frontal, parietal, temporal and sphenoid bones meet, opens wide access to the base of the skull and to lesionLEE-zhunAn area of tissue that has been damaged or has changed from normal, such as a sore, wound, lump or spot.Full entry beside the sylvian fissureFISH-erA narrow crack or split in the skin, a lining or an organ.Full entry ; a bifrontal craniotomy opens the front of the skull on both sides; a suboccipital opening reaches the posterior fossaFOS-uhA shallow hollow or dip in a bone or on the body's surface.Full entry . The bone flap may stay hinged on its muscle (an osteoplastic flap) or come out free. In a patient with a malignant tumor, who will have radiationray-dee-AY-shunEnergy that travels as waves or particles, such as X-rays, used to make images or treat cancer; also pain that spreads from its starting point.radi/o rays, radiation-ation processFull entry , steroidSTAIR-oydA fat-based chemical built from cholesterol; the group includes hormones such as cortisol and estrogen, and many drugs.ster/o solid-oid likeFull entry and antineoplastican-tee-nee-oh-PLAS-tikA drug used to treat cancer by killing cancer cells or stopping them from growing and dividing.anti- againstneo- newplas growth, formation-tic relating toFull entry , the surgeon avoids a scalp flap with a narrow base, because poor blood supply plus those treatments raise the risk of wound infection.
Before surgery: the patient is positioned, pinned, registered if navigation is used, prepped and draped as above, and the incision injected with a local anestheticLOH-kul an-es-THET-ikA drug that blocks feeling in one part of the body without making the person unconscious.Full entry and epinephrineep-ih-NEF-rinA hormone and drug, also called adrenaline, that raises heart rate and blood pressure and opens the airways.Full entry .
Opening:
- The surgeon and assistant press firmly with their fingers, over folded sponges, along both sides of the incision line, and the surgeon cuts through the skin and galea in short segments with a #10 or #20 blade.
- Raney clips go on the cut edges, through the full-thicknessful-THIK-nisGoing through every layer of the skin, or every layer of another tissue such as the wall of an organ.Full entry of the scalp and the drapes, to stop the bleeding. Reload the appliers fast as they come back, because scalp bleeding can be heavy. Dandy clamps, passed tips down, may hold the lower edge, with rubber bands around their handles.
- The galea and periosteum are cut with the electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry , with the smoke evacuated, and the scalp flap is turned back over a folded sponge or lap, held with hooks or towel clips and rubber bands, and covered with a moist sponge. The pericranium is lifted off the bone with a periosteal elevator.
- Burr holes are drilled with the perforator, or a burr on a high-speed drill, while you irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry the bit against the heat and keep suction beside the stream to clear the bone dust. When the inner table gives way and the duraDOOR-uhThe tough outer layer of the membranes that cover the brain and spinal cord.Full entry shows, bone wax or a patty stops the bleeding from the hole, a small curettekyoo-RETA surgical instrument with a small spoon- or loop-shaped tip used to scrape tissue.Full entry cleans its edge, and a Kerrison rongeurron-ZHURA strong surgical instrument with sharp, cup-shaped jaws used to bite away small pieces of bone.Full entry can widen it.
- The surgeon frees the dura from the underside of the bone with a #3 Penfield or a similar dural separator, so the saw cannot tear it.
- The craniotome, fitted with its footplate (dura guard), cuts from hole to hole while you irrigate. Occasionally the bone is cut by hand with a Gigli saw, a flexible wire saw passed between the holes on a guide.
- The flap is lifted off the dura with periosteal elevators, and the bleeding bone edges are waxed. Keep the bone flap on the back table, apart from everything else, in a basin of saline or antibiotic solution if the surgeon asks, and tell the circulator and any relief scrub where it is, so it is never thrown away.
- Dural bleeding is stopped with the bipolarby-POH-lerHaving two poles or two opposite ends; most often used as a short form of bipolar disorder.bi- twopolar having polesFull entry or with thrombinTHROM-binAn enzyme in the blood that turns fibrinogen into fibrin, the threads that hold a blood clot together.thromb/o clot-in substanceFull entry -soaked gelatin sponge and patties. Small holes may be drilled at the bone edge for dural tack-up sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry , which hold the dura up against the bone and prevent a blood clot forming over it after surgery.
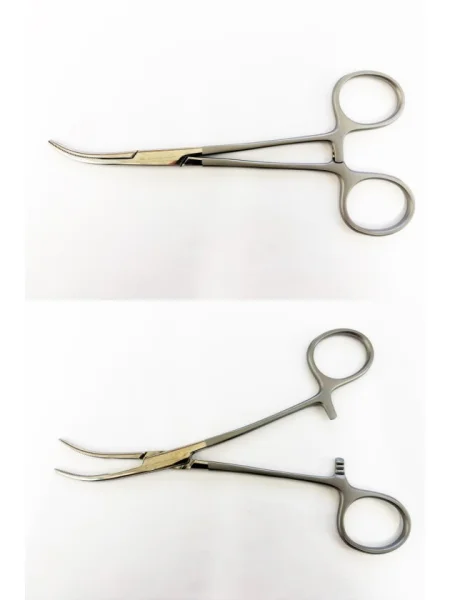
- The surgeon lifts the dura with a dura hook or a stitch, nicks it with a #15 or #11 blade, and opens it with Metzenbaum or dura scissors while a narrow moist patty, slid under the edge, protects the brain. tractionTRAK-shunA steady pulling force applied to a body part with weights, ropes and pulleys.Full entry sutures hold the edges back, tagged with mosquito clamps. Opened dura shrinks as it dries, so it is kept moist under wet nonadherent strips or patties.
- Moist brain spoons go in over patties, held by hand or locked to a self-retaining brain retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry . Wet each spoon before you pass it. The microscope may come in now.




Closing:
- The surgeon checks for bleeding with irrigation, the bipolar, oxidized cellulose and thrombin-soaked gelatin sponge. The anesthesia provideran-us-THEE-zhuh pruh-VY-derThe licensed professional who gives anesthesia and watches over the client's breathing and vital functions during a procedure.Full entry may hold pressure in the patient's airway (a Valsalva maneuverval-SAL-vuh muh-NOO-verBreathing out forcefully against a closed airway, as when bearing down or straining.Full entry ), which raises the pressure in the veins of the head and shows any bleeder that is still open.
- The brain is irrigated with body-temperature saline, often with an antibiotic. As wound closure begins, the closing count is done, and every patty and cotton ball must be accounted for (chapter 28).
- The dura is closed watertight with a running suture, often 4-0 braided nylon or silk, or 4-0 or 3-0 polypropylene or nylon, with a sealant or fibrin glue over the line; a gap is patched with muscle, pericranium, a dural substitute or pericardiumpair-ih-KAR-dee-umThe thin, two-layered sac that surrounds the heart.peri- aroundcardi/o heart-um a structureFull entry .
- The bone flap goes back and is fixed with titanium plates and screws, or with wire, mesh or clamps. While holes are drilled near the brain, a brain spoon or periosteal elevator between the bone and the dura protects it.
- The Raney clips come off and are counted, the galea is closed with interrupted absorbable sutures, often 2-0, and the skin with staples or 3-0 or 4-0 monofilament. A drain may come out through a stab wound.
- The head dressing goes on, and the pins come out before the patient wakes.
After surgery: the patient goes to the ICU or the PACU with monitoring lines, a urinary catheter and wound drains, any of which can be pulled out in the move, so take care moving the patient to the bed. The risks are wound infection, meningitismen-in-JY-tisInflammation of the meninges, the membranes that cover the brain and spinal cord.mening/o meninges-itis inflammationFull entry , a neurologic deficit, damage to vital structures, and a new clot in the subduralsub-DOOR-ulLocated beneath the dura, the tough outer membrane covering the brain and spinal cord.sub- underdur dura-al relating toFull entry or epidural anesthesiaep-ih-DOOR-ul an-us-THEE-zhuhPain relief or numbness from an anesthetic drug given through a thin catheter into the space just outside the covering of the spinal cord.epi- upon, overdur/o dura (the tough covering of the spinal cord)-al relating toFull entry space or inside the brain. The nurse compares the neurologic assessment after surgery with the baseline before it.
Wound class: I, clean, when no sinusSY-nusA hollow space in the body, most often one of the air-filled spaces in the skull bones around the nose.Full entry or other tract is entered.
Irrigate every drill and saw, keep bone wax ready for every bone edge, keep the dura moist, and guard the bone flap on the back table as if it were the patient's skull, because it is.
Craniectomy
In a craniectomy the bone is removed and not put back at the end. It may be a planned part of the operation, as in a suboccipital craniectomy for the posterior fossa, or it may be done for a tumor, a clot, an infected bone flap, craniosynostosis in an infant, or a severe head injury, when leaving the bone out lets the swollen brain expand and lowers the pressure. The bone can be kept for later: refrigerated or frozen in the bone bank, or stored in the patient's own body, under the skin of the abdomen or in a pocket under the scalp, and put back weeks or months later in a cranioplasty.
Wound class: I, or IV when it removes an infected bone flap.
Navigation at a craniotomy
Chapter 21 teaches navigation, its fiducials and their registration; in brain surgery its arm is fixed to the skull clamp, in a sterile sleeve, and must never be bumped. Once the dura is open, cerebrospinal fluidser-uh-broh-SPY-nul FLOO-idThe clear, watery fluid that bathes and cushions the brain and spinal cord.cerebr/o brainspin spine-al relating toFull entry drains and the brain shifts, most of all over the convexity and at the poles, so the scans taken before surgery no longer match; scans during surgery can update the map (ultrasound is cheap but often poor, computed tomographykum-PYOO-tid toh-MOG-ruh-feeAn imaging test that uses x-rays and a computer to make cross-section pictures of the inside of the body.tom/o cut, slice-graphy process of recordingFull entry better but slow and a radiation dose for the team, magnetic resonance imagingmag-NET-ik REZ-uh-nunts IM-uh-jingAn imaging test that uses a strong magnet and radio waves to make detailed pictures of the inside of the body.Full entry the best but costly and hard to fit into an OR), and at the base of the skull the map can be off by about 0.9 to 2.4 mm.
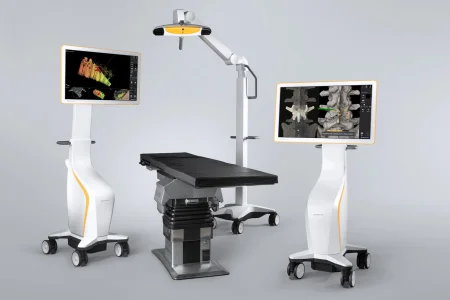
Tumor resection
What and why: the surgeon removes a brain tumorBRAYN TOO-merAn abnormal mass of cells growing in or on the brain, which may be cancerous or not.Full entry completely when it can be done safely, as for most meningiomas, or takes out as much as is safe when the tumor infiltrates the brain, as most malignant gliomas do.
Key steps (after the craniotomy opening):
- The surgeon dissectdy-SEKT, or dih-SEKTTo cut apart or separate tissues carefully during surgery.Full entry into the brain with the bipolar, microscissors and suction, under the microscope, guided by navigation or ultrasound.
- The tumor comes out with pituitary rongeurs, suction or the ultrasonic aspirator. Have the dissectors, bayonet and Gerald forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry and a full supply of moist patties and strips, with irrigating syringes kept full, within the surgeon's reach.
- Samples of the tumor go to pathologypuh-THOL-uh-jeeThe study of disease and its causes and effects, or the disease changes found in a person or tissue.path/o disease-logy study ofFull entry (chapter 29).
- The surgeon stops the bleeding in the tumor bed, lines it with oxidized cellulose and fills it with irrigation, and a Valsalva check confirms the bleeding has stopped; dissolving chemotherapy wafers may be placed.
- The dura and the rest of the wound are closed as above.
Some tumors need more. The fluid in a craniopharyngioma's cyst is very irritating and can inflame the meningesmuh-NIN-jeezThe three thin layers of tissue that cover and protect the brain and spinal cord.mening/o membraneFull entry , so many moist patties guard the brain around it. Where a meningioma was attached, the dura is coagulationkoh-ag-yuh-LAY-shunThe process by which blood changes from a liquid into a gel, forming a clot.coagul clot-ation processFull entry to prevent its return. A large or complicated tumor near the pituitary is reached by a frontal or frontotemporal craniotomy rather than through the nose; aneurysmAN-yuh-riz-umA weak spot in the wall of an artery that bulges outward like a balloon.aneurysm a widening (Greek)Full entry clips are kept ready for sudden bleeding from the large arteries nearby. An endoscopeEN-duh-skohpA thin tube with a light and a camera that is passed into the body to look inside an organ or cavity.endo- within-scope instrument for viewingFull entry can show tumor left behind, and a laser probe placed under MRI guidance can destroy a glioblastoma from the inside.
After surgery: as after any craniotomy.
Wound class: I.
Posterior fossa surgery
What and why: the posterior fossa holds the cerebellumser-uh-BEL-umThe part of the brain at the back, under the cerebrum, that coordinates movement, balance and posture.Full entry , the fourth ventricleVEN-trih-kulOne of the two lower chambers of the heart, or one of the fluid-filled spaces inside the brain.Full entry and the brain stemBRAYN STEMThe lowest part of the brain, which connects it to the spinal cord and controls breathing, heart rate and other automatic functions.Full entry , with the cranial nerves, and tumors, meningiomas and other lesions there are reached through a suboccipital craniectomy.
Before surgery: prone with the head of the bed raised, the head in pins, is the usual position; lateral and sitting positions are also used. The scrub works from a standing stool. A ventricular catheter may go in first through an occipital burr hole.
Key steps:
- The incision runs across the back of the head from one mastoid to the other, or down the midlineMID-lineAn imaginary line down the center of the body; also, a type of IV catheter placed in a vein of the upper arm.Full entry , and the neck muscles are freed from the bone and held with a self-retaining retractor.
- The surgeon drills one or more holes in the occipital bone and removes bone with the drill and rongeurs, such as a double-action, Kerrison or Leksell rongeur.
- Bleeding from bone and veins is controlled at every step, with bone wax, gelatin sponge and coagulation, because an open vein here can draw in air.
- The dura is opened over a protecting patty, the cisterna magna is opened and drained of CSF, and brain retractors go in over patties. Keep each retractor's handle dry, so it does not slip in the surgeon's hand, and its blade wet, so it does not tear the brain. These blades may rest near the centers that control breathing, so never bump them.
- The lesion comes out with long bayonet forceps, cup and pituitary forceps, suction and loop tips, with a nerve stimulator and evoked potentials guardingGAR-dingTightening of muscles, or protecting a body part with the hands or posture, to avoid pain when it is touched or moved.Full entry the cranial nerves and brain stem; after a Valsalva check for bleeding, the dura is closed and the defect may be covered with titanium mesh.
- The patient stays asleep until turned supine and the pins are out; as they come out, watch the scalp and the eyes.
Wound class: I.
Acoustic neuroma removal
What and why: a vestibular schwannoma (acoustic neuroma) grows in the internal auditory canal and into the angle between the cerebellum and the ponsPONZThe part of the brain stem between the midbrain and the medulla.Full entry . It is benign, but as it grows it can take away hearing and balance, press on the facial and other cranial nerves and the brain stem, and cause hydrocephalushy-droh-SEF-uh-lusA buildup of too much cerebrospinal fluid inside the spaces (ventricles) of the brain.hydr/o watercephal/o head-us noun endingFull entry . Surgery for these tumors is team work: a neurosurgeon works with an ear surgeon (a neurotologist) and other specialists, and the approach depends on the tumor's size and on whether the hearing can be saved.
- Retrosigmoid (suboccipital): a craniotomy behind the sigmoidSIG-moydShaped like the letter S; most often short for the sigmoid colon, the S-shaped last part of the colon before the rectum.Full entry sinus. It can save hearing, so it suits smaller tumors in patients who still hear well.
- Translabyrinthine: through the mastoid and the inner earIN-er EERThe deepest part of the ear, inside the skull bone, which holds the organs of hearing and balance.Full entry , for medium and large tumors; it destroys the hearing on that side but saves the facial nerveFAY-shul NERVThe seventh cranial nerve, which moves the muscles of the face and carries taste from the front of the tongue.Full entry best, and chapter 36 teaches it.
- Middle cranialKRAY-nee-ulRelating to the skull, or toward the head end of the body.crani/o skull-al relating toFull entry fossa: through a temporal craniotomy, for small tumors inside the canal in patients with useful hearing.
Key steps (middle fossa):
- The hair is clipped on that side, and the head, face and neck are prepped, usually with povidone-iodinePOH-vih-done EYE-uh-dineA brown antiseptic solution of iodine used to kill germs on the skin before procedures and on wounds.Full entry ; the eye on that side is lubricated and covered.
- Through an incision in front of the ear, the temporalis muscle is turned down or split, and a square of temporal bone about 5 cm across, over the root of the zygoma, is cut out and saved to go back at the end.
- Under the microscope, the dura is lifted off the floor of the middle fossa from back to front, so the facial nerve's ganglionGANG-glee-unA cluster of nerve cell bodies outside the brain and spinal cord; plural ganglia.Full entry is not hurt, with a Freer or House elevator, and a middle fossa retractor (such as a Fisch or House-Urban) holds the temporal lobeTEM-puh-rul LOHBThe part of each side of the brain, above the ear, that handles hearing, memory and understanding language.Full entry up.
- The surgeon drills down to the internal auditory canal, opens it and the dura, and frees the tumor from the facial nerve, with the facial nerve monitor running.
- The canal is sealed with fat from the abdomen or temporalis muscle, the bone square goes back, the muscle and incision are closed, and a pressure dressing goes on.
After surgery: a CSF leak, the reason the canal is sealed so carefully, and weakness of the facial nerve are the main risks to watch for.
Wound class: I; IV if the ear is actively infected.
Stereotactic surgery
What and why: stereotactic surgery (chapter 21 explains the word and its 3D map) reaches a precise target through a small opening by the least damaging path. It is used for biopsy of deep tumors, for draining a cyst or abscess, for placing catheters, for third ventriculostomy, and for placing electrodes to map seizureSEE-zherA sudden burst of abnormal electrical activity in the brain that changes movement, feeling, behavior or awareness.Full entry or to stimulate deep parts of the brain, as in Parkinson diseasePAR-kin-sun dih-ZEEZA slowly worsening brain disease in which the nerve cells that help control movement die off.Full entry , as well as to destroy small targets that cause movement disorders or intractable pain.
The two systems:
- Frame-based: the frame is fixed to the skull with pins under local anesthesiaLOH-kul an-es-THEE-zhuhNumbing medicine applied to or injected into one small area, so a procedure there is not felt while the person stays awake.Full entry on the day of surgery and stays on for the scans. Tell the radiology team and the anesthesia provider it is on, because it changes how they care for the patient.
- Frameless: fiducials on the scalp or set into the outer table of the skull take the place of the frame; frameless systems have largely overtaken frames since the early 2000s.
Key steps:
- The frame or fiducials go on and the patient is scanned; the computer plans the target and the path.
- In the OR, with the frame or fiducials still in place, the frame is fixed to the bed or registered, under local anesthesia with sedationsih-DAY-shunA calm, relaxed or sleepy state brought on by drugs, or the use of drugs to cause it.sed calm, settle-ation processFull entry or general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry .
- A burr hole is made, and the surgeon passes the needed tool to the target: a biopsy needle or cannulaKAN-yoo-luhA thin tube placed into the body or a body opening to deliver or remove fluid or air.Full entry , an electrode that coagulates or freezes tissue, or a stimulating lead.
- The frame or fiducials come off and the small wound is closed.
A stereotactic robot can hold the guide for placing seizure-mapping electrodes, deep brain stimulator leads and biopsy needles. Once the robot is locked to the head frame, neither the patient nor the bed may be moved. The tools include a power drill, trocarTROH-karA sharp or bladed instrument inside a tube (cannula), used to pierce a body wall and leave the tube in place as a port.Full entry , guidewires, a depth gauge and anchor bolts, and the electrode position is confirmed with imaging before a deep brain stimulator's batteryBAT-uh-reeIn law, touching a person on purpose without their consent.Full entry is placed.
Stereotactic systems differ from one maker to the next, so learn your facility's equipment, software and instruments before the case, through in-service training and by watching these procedures.
After surgery: as after a craniotomy, usually with a hospital stay of 2 to 3 days.
Radiosurgery uses the same 3D targeting to aim a high dose of radiation at a small target in the brain, such as a tumor, an AVM or the nerve in trigeminal neuralgia, while sparing the tissue around it.
Wound class: I.
Aneurysm repair
What and why: a ruptured aneurysm bleeds into the subarachnoid spacesub-uh-RAK-noyd SPAYSThe space between two of the thin membranes that cover the brain and spinal cord, filled with cerebrospinal fluid.sub- belowarachn spider (the arachnoid layer looks like a web)-oid likeFull entry , and the goal of surgery is to shut the aneurysm off from its parent artery while keeping blood flowing to the vessels around it. There are two ways: an interventional radiologist can fill the aneurysm with soft platinum coils through a catheter from the groin (chapter 22), which suits many small-necked aneurysms, or the surgeon can clip its neck through a craniotomy, the usual choice for a broad neck. Either way the treatment aims to prevent a second bleed, and a clipping is ideally done within 72 hours of the diagnosis. angiographyan-jee-OG-ruh-feeAn imaging test that shows blood vessels by injecting a contrast dye and taking x-ray, CT or MRI pictures.angi/o vessel-graphy process of recordingFull entry shows the exact size and position of the aneurysm.
Aneurysm clips: a clip has a body, a pivot and two blades, and the blades come straight, curved or angled to fit the anatomy. Most are spring loaded.
- Temporary clips open wider and close with less force. They shut off the parent artery for a short time, test where the permanent clip should sit, or control a giant aneurysm while clot is cleared from it. They are discarded after use.
- Permanent clips close with more force and stay in for life as an implant; record each one. Fenestrated clips have an opening in the blade so they can reach around a vessel, and Teflon-lined clips wrap all the way around a vessel to hold it.
- Have at least two appliers for every type of clip.
- Never squeeze a clip between your fingers or open and close it while you load it. Only the surgeon closes it, seated in the applier, just before placing it, because a clip that has been opened can be sprung, slip, and bleed or pinch another vessel or a nerve; a clip that has been opened is discarded.
Before surgery: the head is always held in a three-pin skull clamp. A lumbarLUM-barHaving to do with the lower back, the part of the spine between the ribs and the pelvis.Full entry drain may go in before positioning, on its own small sterile setup, so CSF can be let out to relax the brain. A carotidkuh-ROT-idHaving to do with the carotid arteries, the two large arteries on each side of the neck that carry blood to the head and brain.Full entry set stays ready, and occasionally the surgeon first exposes the carotid artery in the neck, as a separate step, so blood flow to the brain can be controlled if the aneurysm bleeds. The setup is a basic craniotomy set plus the aneurysm clips and appliers, microinstruments, papaverine and extra suction on the field; a blood salvage unit stands by.
Key steps:
- A frontal, pterional or bifrontal craniotomy is opened in the usual way.
- The surgeon splits the sylvian fissure with the bipolar to separate the frontal and temporal lobes, places brain spoons on a self-retaining retractor over moist patties, and finds the optic nerveOP-tik nervThe nerve that carries visual signals from the back of the eye to the brain; the second cranial nerve.Full entry and chiasm.
- The microscope comes in. The surgeon opens the arachnoid with microscissors, hooks, dissectors and a fine bipolar; the CSF that drains out relaxes the brain further.
- The parent arteries are freed so a temporary clip can go on if needed. Keep a temporary clip loaded on an applier at all times, ready for a rupture, and several suction tips on the field, because fine tips clog with blood.
- As the surgeon nears the aneurysm, the anesthesia provider may lower the blood pressure, so a rupture would be easier to control. The surgeon places a permanent clip across the neck, adding clips as needed, and the pressure is brought back up.
- The surgeon punctures the sac with a fine needle, such as a 30-gauge needle on a syringe, to check that no blood enters it, and may lay a patty soaked in papaverine on the arteries to prevent spasmSPAZ-umA sudden, involuntary tightening of a muscle or of the muscle in a hollow organ or tube.Full entry . A C-arm angiogram during surgery can confirm the result.
- The wound is closed as for any craniotomy, and the pins come out before the patient wakes.
If the aneurysm cannot be clipped, it can be wrapped or coated, with a piece of muscle or galea, a fast-setting plastic or another material the surgeon chooses.
if the aneurysm ruptures, the surgeon needs suction and moist patties at once, then the loaded temporary clip. Have all three in your hands before you are asked.
After surgery: intensive care for close watching of bleeding and pressure, then home after a few days if all goes well; vasospasm stays a danger in the days after the bleed (see Vascular disease).
Wound class: I.
AVM resection
What and why: an AVM can bleed again and again, and removing it completely, when possible, gives the best result. The care is shared: before surgery an interventional radiologist may block (embolize) the vessels feeding it, with coils, glue or tiny particles, to shrink it and make it bleed less, and after surgery may close vessels the surgeon could not reach. Radiosurgery is another option for some.
Key steps:
- A craniotomy is opened as for an aneurysm.
- Under the microscope the surgeon finds the feeding arteries away from the malformationmal-for-MAY-shunA body part or organ that formed in an abnormal way before birth.mal- badformation shapingFull entry , follows them in, and closes them with clips, the bipolar or ties; aneurysm clips go on the larger feeders.
- The AVM is dissected out with suction, bayonet forceps and a fine bipolar. At least one draining vein is kept open until every feeding artery is closed, and is taken last.
- The cavity is lined with strips of oxidized cellulose and gelatin sponge, and the wound is closed as for an aneurysm.
Watch the video monitor so you can swap the fine bipolar before its tips char and the surgeon has to look away.
Wound class: I.
Evacuating a hematoma
What and why: blood that collects above or below the dura after an injury presses on the brain, and the need to remove it is decided mostly by how fast the patient's neurologic state is getting worse. A chronic subdural hematomasub-DOO-rul hee-muh-TOH-muhA collection of blood between the brain's tough outer covering (the dura) and the brain.sub- underdur dura-al relating tohemat/o blood-oma massFull entry , its blood liquefied by then, can often be drained through burr holes; an acute subdural hematoma usually needs a craniotomy to remove the clot and stop the bleeding, and so does an epidural hematomahee-muh-TOH-muhA collection of blood, often clotted, that has leaked out of the blood vessels into the tissue.hem/o blood (here as hemat-)-oma swelling or massFull entry . A CT scan, the first study after a head injury, shows the clot.
Key steps (burr holes):
- The surgeon makes two or more short straight or small horseshoe incisions over the clot and drills two or more burr holes, widening them with a Kerrison rongeur.
- For a subdural hematoma, the dura is opened.
- The clot and fluid are removed, and bleeding is stopped with the ESU or clips.
- The space is washed through the holes with catheters or bulb syringes, with a great deal of irrigation, until the fluid runs clear.
- A drain may be left in the subdural or epidural space, and more burr holes are made if they are needed.
For an acute clot, the craniotomy follows the usual pattern; if the brain is swelling, the bone flap may be left out to give it room.
After surgery: as after any craniotomy, with each neurologic check compared with the baseline.
Wound class: I for a closed injury; an open, fresh traumatic wound is Class III.
Head and neck trauma
In trauma, damage control comes first: burr holes and a ventriculostomy, a catheter that drains CSF from a ventricle, to relieve the pressure. The definitive operation is a craniotomy to remove the blood and clots and stop the bleeding.
- The setup: a hospital that takes trauma keeps an emergency craniotomy cart ready, with linens, suction tubing, ESU supplies, hemostatichee-moh-STAT-ikStopping bleeding; also, a product or agent used to stop bleeding.hem/o blood-stasis stopping, standing still-ic relating toFull entry , scalp clips, sponges and the neurosurgical sets. When other injuries need surgery too, each gets its own setup (chapter 28), brought up in order or used by a second team at once.
- Positioning: the cervicalSER-vih-kulRelating to the neck, or to the cervix, the lower end of the uterus.cervic/o neck, cervix-al relating toFull entry spine is treated as injured until it is cleared. The patient arrives in a collar and is moved by logrollLOG-roleTo turn a client as one unit, keeping the head, neck, spine and hips in a straight line.Full entry on a lateral transfer device, with the spine kept neutral; the head is turned, the injured side up, only once the neck is cleared.
- Draping: the drapes must leave room for the other injuries, with a second procedure drape overlapping the craniotomy drape. A penetrating brain injury counts as contaminated, because the object was not sterile and it drags scalp and hair into the wound.
- A fracture over a venous sinus: when the bone over a sinus must be lifted, have everything ready for heavy bleeding and blood in the room. The head is kept above the heart and the table ready to move: raising the head lowers the pressure in the veins, and the bleeding with it, and lowering it raises the pressure to keep air from being drawn in. A catheter in the right atriumAY-tree-umOne of the two upper chambers of the heart, which receive blood coming back to the heart.atri/o atrium-um noun endingFull entry can draw out air if an embolismEM-buh-liz-umThe blocking of a blood vessel by a mass carried there in the blood (an embolus), such as a clot, fat or an air bubble.embol/o plug-ism conditionFull entry happens.
- A dirty wound: when the wound is badly contaminated or more than 24 hours old, the broken bone is not put back at once, and a cranioplasty follows later (see Cranioplasty).
The frontal sinus (handed here by chapter 37): when a fracture breaks through both walls of the frontal sinus, the back wall as well as the front, it is repaired from inside the skull through a bicoronal craniotomy, with the head in a three-pin holder and mannitolMAN-ih-tolAn osmotic diuretic, given by IV, that draws water out of tissues into the blood so the kidneys can remove it.Full entry and brief hyperventilationhy-per-ven-tih-LAY-shunBreathing faster or deeper than the body needs, so too much carbon dioxide is breathed out.hyper- above, excessiveventilation moving air in and out of the lungsFull entry to relax the brain. The surgeon strips out every bit of the sinus lining, so it cannot form a cyst later, removes the broken back wall so the sinus becomes part of the skull cavity (cranialization), plugs its openings into the nose with temporalis muscle glued in with fibrin sealant, repairs the dura, and lays a flap of pericranium, with its own blood supply, over the cranialized sinus. For a proven CSF leak or a torn dura there, a lumbar or ventricular drain stays in for 3 to 5 days.
Wound class (frontal sinus): II, because the sinus is entered; III when the fracture is a fresh open wound.
Spinal injury: stabilization devices put on at the scene stay on until there is clear proof that the spine is not injured. Emergency surgery is usually not done for a complete cord injury; an incomplete injury may benefit from removing bone fragments, foreign bodies or clots that press on the cord, and from stabilizing the spine with an implant system or a haloHAY-lohA ring shape: either a ring of light seen around lights, or a metal ring fixed to the skull to hold the neck still.Full entry brace, once the patient is stable. Decompression, stabilization and traction are the common operations.
Neck trauma (chapter 11): blunt, penetrating or near-hanging injuries can damage the airway, the larynxLAIR-inksThe voice box: the part of the airway in the neck, above the windpipe, that holds the vocal cords.laryng/o larynxFull entry and the major blood vessels. The neck is treated as broken and the airway secured first; the vessels are repaired with the vascular setup used in carotid surgery (chapter 40), and the airway, often with a tracheostomytray-kee-OS-tuh-meeA surgical opening through the front of the neck into the windpipe, usually holding a tube that the person breathes through.trache/o windpipe-stomy surgical openingFull entry (chapter 36).
Cranioplasty
What and why: a cranioplasty repairs a hole in the skull left by an injury, a malformation or an earlier operation, to protect the brain beneath, relieve headache and tenderness, and restore the shape of the head. A clean defect may be repaired at once; a contaminated one, after a bone flap infection or an open injury, is repaired later, after 1 to 2 months in one reference and 6 months in another. If the patient's own bone flap was kept, frozen or stored under the skin, it goes back with small plates and screws. Otherwise the defect is rebuilt with titanium mesh, methyl methacrylate bone cement, calcium phosphate, or a custom implant made from the patient's CT scan before surgery.
Key steps (methyl methacrylate):
- The old incision is reopened and the scalp lifted off the defect with great care, because there is no bone between the scalp and the brain.
- The surgeon trims the edges of the defect with rongeurs into a shallow saucer-like ledge, so the new plate cannot sink below the level of the skull. Keep the trimmed bone as a specimen, and have a sponge ready to clean the rongeur.
- The wound is irrigated with warm saline, often with an antibiotic.
- You mix the cement as its maker directs, in a closed vacuum mixing system, because it is flammable. While it is still a soft dough, put it in the sterile plastic bag from the kit and pass it.
- The surgeon molds the bagged dough over the defect, with an edge that overlaps the bone, then lifts it out to harden, because the setting cement gives off heat. Cool saline poured on it during this stage keeps the heat down. The references give from about 7 to 20 minutes for the cement to set, so have the fixation ready.
- The hardened plate is trimmed and its edges smoothed with a burr, then fixed into the defect with plates and screws, wire or sutures. The wound is irrigated and closed.
Change your gloves after handling uncured cement. Chapters 29 and 39 teach bone cement, its fumes and its effect on the patient.
After surgery: about a day of intensive care with hourly neurologic checks; infection, wound breakdown, bleeding and a sunken repair are the risks.
Wound class: I.
Craniosynostosis repair
Chapter 38 teaches craniosynostosis and its repair in full; here is the part neurosurgery adds, the work right on the dura. The superior sagittal sinus runs along the midline, under the line of the sagittal suture, so the fused bone is freed from the dura beneath it with great care. In a spring-assisted strip craniectomy for sagittal synostosis, a burr hole at each of two short incisions exposes the dura, the craniotome cuts toward each fontanelfon-tuh-NELA soft spot on a baby's head where the skull bones have not yet joined.Full entry , and a bone cutter and rongeur take out the fused strip in the midline; springs bent to fit on the back table go along the gap, and the removed bone, crushed into small pieces, goes back in as a graftGRAFTTissue or a man-made material moved into place in surgery to replace or repair a damaged part.Full entry .
a plain strip craniectomy without springs, removing the fused sagittal suture with the craniotome and rongeurs and lifting it off the dura with a Cobb elevator, is still taught in one reference; another notes that this was the operation used in the past.
Wound class: I.
Shunts and other operations for CSF
#### Ventriculoperitoneal shuntSHUNTA passage that moves blood or other fluid from one place to another, either made by a surgeon or present in the body.Full entry What and why: a shunt carries CSF from a ventricle to another part of the body where it can be absorptionub-ZORP-shunThe taking in of a substance, such as a drug or a nutrient, into the bloodstream.Full entry , usually the peritonealper-ih-toh-NEE-ulHaving to do with the peritoneum, the thin lining of the belly cavity and the organs inside it.Full entry cavity, and so lowers the pressure in the skull. It is the most common treatment for hydrocephalus in children and adults. When the abdomen cannot take it, because of infection or scarring, the catheter can end in the right atrium of the heart (a ventriculoatrial shunt), the pleural spacePLOOR-ul SPAYSThe thin space between the two layers of the pleura, the membrane that covers the lungs and lines the chest wall.Full entry , or another site, and a shunt can also run from the lumbar spine to the abdomen.
The shunt: a ventricular catheter, a reservoirREZ-er-vwarA place where germs live and multiply, such as a person, animal, water or soil.Full entry , a one-way valve and a peritoneal catheter; a single-piece system has fewer joints. The reservoir lets the team test the shunt, draw CSF, inject contrastKON-trastA dye or other substance given before an imaging test so body parts show up more clearly.Full entry or, sometimes, a drug. Valves open at set pressures or limit the flow, and a programmable valve can be reset after it is implanted, from outside the body, so no second operation is needed.

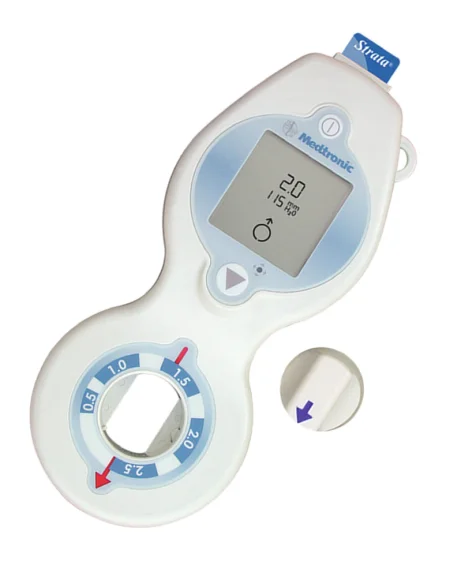
Handle the shunt as little as possible:
- Read the maker's instructions before the case.
- Keep it free of lint, dust, glove powder and blood, which can block it or cause a reaction, and never use a lubricant on it.
- Soak the parts in saline, or an antibiotic solution if the surgeon orders it, and prime the system with saline so no air is trapped in the valve.
- Check that the valve faces the right way, so the fluid flows from the ventricle toward the abdomen.
Before surgery: supine with a roll under the shoulder, the head turned to the other side on a ring headrest. Hair is removed at the burr hole site, behind the ear and down to the neck, and the prep runs from the head down the neck, chest and abdomen on that side. Towels square off the whole path from head to abdomen under an adhesive drape. Choose instruments and sutures sized for the patient, child or adult; an infant chills fast, so have warming ready. The setup adds a drill or perforator, a tunneling device, the shunt and a manometer.
Key steps: the order varies with the surgeon.
- A small upper abdominal incision is opened down to the peritoneumpair-ih-toh-NEE-umThe thin membrane that lines the belly cavity and covers most of the organs inside it.peri- aroundton stretched-eum a structureFull entry , which is lifted with two clamps and opened, then covered with a towel.
- A curved incision is made on the scalp, the bleeding is controlled and the periosteum cleared, and a burr hole of 1 to 2 cm is drilled; the dura and pia are coagulated and opened.
- Load the ventricular catheter on its stylet (introducer) as the dura is opened. The surgeon passes it into the lateral ventricle, sometimes guided by ultrasound, an endoscope or navigation, removes the stylet and watches for CSF. A little CSF may go to the lab. If no fluid comes, the catheter is pulled and passed again.
- A tunneling device makes a path under the skin from the scalp to the abdomen, through a neck incision if needed, staying away from the nipple and umbilicus, and the distal catheter is pulled through.
- The reservoir and valve are joined to the ventricular catheter and tied in place, and the surgeon tests the pump.
- When CSF dripDRIPA continuous IV infusion of fluid or a drug, given slowly over time by gravity or a pump.Full entry freely from the far end, the catheter goes into the peritoneal cavity, with enough extra length for a child to grow or an adult to move, and a purse-string suture holds it.
- The wounds are irrigated and closed, taking care that no needle punctures the tubing. Check that the shunt works before the patient leaves the room.

Ventriculoatrial shunt: the distal catheter is tunneled to a neck incision, where the internal or external jugular veinJUG-yuh-ler VAYNOne of the large veins on each side of the neck that carry blood from the head back toward the heart.Full entry is opened and the catheter passed down into the right atrium.
After surgery: a blocked catheter or valve is the most common problem, and it can happen at any time; a shunt can also drain too much or too little, causing anything from headache to a neurologic deficit. Children outgrow their shunts and need new ones. To revise a shunt, prep and drape the whole system, head to abdomen, because the surgeon may need to reach any part of it. An infected shunt may be brought out to drain externally until the infection clears.
Wound class: no tract is entered, so a shunt is Class I by the CDC's definitions. One reference lists a ventriculoperitoneal shunt as Class II.
#### External ventricular drain and intracranial pressurein-truh-KRAY-nee-ul PRESH-erThe pressure inside the skull, made by the brain, the blood and the fluid around the brain.intra- insidecrani/o skull-al relating toFull entry monitor A temporary catheter in a ventricle drains CSF to an external collecting system and measures the pressure, an invaluable aid in head injury with raised pressure; it can be placed at the bedside through a small twist drill hole, tunneled under the scalp and brought out through a separate stab wound.
Wound class: I.
#### endoscopicen-doh-SKOP-ikDone with an endoscope, a thin tube with a light and camera passed into the body.endo- within-scopic viewingFull entry third ventriculostomy What and why: in obstructive hydrocephalus, the surgeon can make a new opening in the floor of the third ventricle, so CSF drains out into the space beneath it and no shunt is needed. It may not suit an infant younger than 6 months or a patient who already has a shunt.
Before surgery: a rigid ventriculoscope (0, 6 and 30 degree lenses) in an operating sheathSHEETHA covering that wraps around a structure; in procedures, a short hollow tube left in a blood vessel to pass catheters through.Full entry with ports, or a flexible scope; graspers, cup forceps, scissors and bipolar instruments that pass through it; a small Fogarty balloon catheter; and warm lactated Ringer's solutionLAK-tay-tid RING-erz suh-LOO-shunAn isotonic IV fluid containing water, sodium, chloride, potassium, calcium and lactate.Full entry for irrigation, kept at body temperature and run slowly. Supine with the head raised about 30 degrees, which helps the veins drain, limits CSF loss and lowers the chance of air entering a vein.
Key steps:
- A burr hole is drilled over the right lateral ventricle and the dura is opened.
- The sheath goes into the lateral ventricle; it may be fixed to the drapes or held by a retractor arm so it cannot slip deeper. The irrigation tubing is attached and passed off the field.
- The scope passes through the foramen of Monro into the third ventricle, and the surgeon identifies the basilar artery under its floor.
- The floor is opened with a blunt instrument or wire and widened with the balloon to about 5 mm.
- The scope and sheath come out, gelatin sponge goes in the burr hole, a ventricular drain may be left, and the scalp is closed.

After surgery: fever, bleeding and short-term memory loss are the risks; a CT is done before discharge.
Wound class: I.
#### Myelomeningocele repair What and why: a myelomeningocele is the most serious form of spina bifidaSPY-nuh BIF-ih-duhA birth defect in which the bones of the spine do not close completely around the spinal cord.spina spinebifida split in two (Latin)Full entry (see Disorders above). The nerve tissue is abnormal, so even after repair the child has some weakness or loss of feeling below the level of the defect, and often a heart or urinary defect, hydrocephalus or a Chiari malformation as well. The repair closes the dura and the skin to protect the nerves: at once if the sac is leaking CSF, otherwise within 48 hours of birth, to prevent infection.
Before surgery: these children have many operations and often become sensitive to latexLAY-teksNatural rubber made from the sap of the rubber tree, used in some gloves, catheters and other medical supplies.Full entry , so follow your facility's latex-free protocol. The exposed nerve tissue loses heat fast, so all solutions are warm. Use small, fine instruments. The infant lies prone on small chest and hip rolls.
Key steps:
- If the sac is intact, the surgeon drains it with a 20-gauge needle and syringe and sends the fluid for culture.
- A #15 blade on a #3 handle cuts around the defect and the placode, the flat plate of nerve tissue. Have the bipolar and moist sponges, and moist patties, ready for bleeding.
- The surgeon frees the dura and closes it over the cord, often with 4-0 braided nylon, then closes the fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry over it.
- The wound is irrigated with warm saline, the muscle is closed, and the skin is brought together; a large defect may need a Z-plasty or a flap (chapter 38).
A shunt may be placed at the same operation if the hydrocephalus is severe, or later.
Wound class: no reference gives one, so it follows the CDC's definitions. A sac that is intact, or open but neither inflamed nor infected, enters no tract and is closed at once: Class I. A sac that has torn open is an open, fresh, accidental wound, and one that is inflamed or soiled before the repair (by stool, for example) is contaminated: Class III. A sac that is already infected, as cultures can show after a delayed repair, is Class IV.
Transsphenoidal hypophysectomy
What and why: the pituitary glandpih-TOO-ih-tair-ee glandA gland the size of a pea, hanging below the brain, whose hormones control many other glands.Full entry sits in the sella turcica, a hollow in the sphenoid bone, just below the optic chiasm and between the cavernous sinuses, which hold cranial nerves and the internal carotid arteries (chapter 9 describes the gland). A tumor there can take away the outer half of the field of vision in each eye, press on cranial nerves III to VI, make too much of a hormone, as in Cushing syndromeKUSH-ing SIN-drohmA condition caused by too much cortisol in the body over a long time.Full entry or acromegalyak-roh-MEG-uh-leeA rare hormone disorder in adults in which the body makes too much growth hormone.acr/o extremities (hands and feet)-megaly enlargementFull entry , or make too little. Most pituitary tumors are removed through the nose and the sphenoid sinus, which spares the brain, shortens recovery and leaves no visible scar; a very large or complex tumor needs a craniotomy instead.
Approaches: an endoscope passed through the nose, which needs no incision and no microscope; or the microscope, through the nostril with a bivalved speculumSPEK-yoo-lumAn instrument used to open and hold open a body opening, such as the vagina, so the inside can be seen.Full entry or through an incision in the gum under the upper lip. All give similar results. An ear, nose and throat surgeon often opens the way to the sphenoid. Navigation can guide either approach.
Before surgery: the head is held in a three-pin clamp, semi-sitting (beach chair), with the head turned to the right, toward the surgeon, who works from the patient's right side. The C-arm checks the position on the sella; mark the floor where its wheels stand, so it can go back to the same spot. The face is prepped and draped with towels and an adhesive drape across the bridge of the nose; use a prep safe for the face, never CHG (chapter 31), and references differ on whether the nose and mouth are prepped. A thigh or the abdomen is prepped and draped separately for a fat, muscle or fascia graft.
The nose cannot be made sterile, so this is a clean-contaminated case done with surgical asepsisSUR-jih-kul ay-SEP-sisPractices that keep an area or object completely free of microorganisms; also called sterile technique.a- withoutsepsis decay, infectionFull entry . Keep the graft instruments on their own setup, harvest the graft first, before the nose is entered, and keep the nasal instruments on a separate Mayo standMAY-oh standA small tray on an adjustable stand placed over or beside the patient during surgery to hold the instruments used most often.Full entry .
Medications and sponges: prepare a separate small table for the topical and injected drugs: nasal specula, cottonoids, syringes and 25-gauge needles. The circulator supplies the topical cocaine and the lidocaineLY-doh-kaynA local anesthetic that numbs an area, also given by IV to treat some fast, abnormal heart rhythms.Full entry with epinephrine, and the surgeon injects the lining of the nose and gum. Note every cottonoid placed in the nose so it comes out and is counted. A throat pack keeps blood out of the stomach: it is counted, its placement is announced, and its removal is confirmed before the breathing tube comes out. Some references do not count it with the sponges, so facility policy decides how it is recorded.
Key steps (microscope):
- The fat graft is taken from the abdomen (or muscle or fascia from the thigh) and kept moist in saline on the back table, and the graft wound is closed and covered with a towel.
- The lining of the nasal septumNAY-zul SEP-tumThe wall of cartilage and bone that divides the inside of the nose into right and left sides.nas/o nosesept/o dividing wallFull entry is lifted from the cartilageKAR-tih-lijFirm, smooth, rubbery tissue that cushions joints and gives shape to parts such as the ear, nose and windpipe.chondr/o cartilageFull entry , and a bivalved speculum goes in; part of the septumSEP-tumA wall of tissue that divides two spaces or cavities, such as the two sides of the heart or nose.sept/o wall, partitionFull entry and the front of the sphenoid sinus come out with a drill or rongeurs, and the bone is kept as a specimen. Drape the C-arm now, before the sphenoid is entered; the microscope may have been draped before the case began.
- The floor of the sella is opened with a punch or a small osteotome, which you may be asked to tap gently, and the dura is opened with a #11 blade.
- The tumor comes out in pieces with ring curettes, enucleators, microdissectors and suction, often with a frozen section early. Collect every piece. The anesthesia provider may raise the pressure in the head with a Valsalva maneuver to push the tumor down into view.
- Bleeding is controlled with patties soaked in epinephrine and gelatin sponge. The sella is packed with the fat or muscle graft to prevent a CSF leak, and its floor may be rebuilt with septal cartilage or a plate, with fibrin sealant if needed.
- The nose is packed, the patient is laid flat and the pins come out before waking.
After surgery: intensive care, watching for changes in neurologic state and for a CSF leak; a lumbar drain may be placed to treat one. Because the gland was handled, the patient may make too much or too little of its hormones, at once or weeks later, as in diabetes insipidusdy-uh-BEE-teez in-SIP-ih-dusA disorder of antidiuretic hormone: the body makes too little of it, or the kidneys do not respond to it.Full entry ; some patients need hormone replacement for life. Infection and meningitis are the other risks.
Wound class: II, clean-contaminated, because the nasal and sinus airway is entered.
Graft first, nose second, on separate setups. Count every cottonoid that goes into the nose, and confirm the throat pack is out before the breathing tube comes out.
7Operations on the spine
Spine surgery is done by neurosurgeons and by orthopedicor-thuh-PEE-dikHaving to do with the bones, joints, muscles, ligaments and tendons, and the branch of medicine that treats them.orth/o straightped/o child (the field began with straightening children's bones)-ic relating toFull entry surgeons; neurosurgeons do most of the cervicalSER-vih-kulRelating to the neck, or to the cervix, the lower end of the uterus.cervic/o neck, cervix-al relating toFull entry cases, and both operate on the lumbarLUM-barHaving to do with the lower back, the part of the spine between the ribs and the pelvis.Full entry spine. The Core Curriculum lists the approaches as minimally invasive, including robot-assisted; image-guided navigation; and open, from the front (anterior), the side (lateral) or the back (posterior). These points apply to every spine case:
- Turning the patient: for a prone case the patient is anesthetized and endotracheal intubationen-doh-TRAY-kee-ul in-too-BAY-shunPutting a breathing tube through the mouth or nose into the windpipe (trachea).endo- withintrache/o windpipe-al relating toFull entry on the stretcher, then turned as chapter 31 teaches.
- The right level: the surgeon marks the level, and an X-ray or fluoroscopyfloo-ROS-kuh-peeAn x-ray method that shows moving pictures of the inside of the body in real time.fluor/o glowing (from the fluorescent screen)-scopy looking, viewingFull entry shot with a needle or instrument on the spine confirms it, before the incision or once the bone is exposed; another image after the repair shows the work was done at the right level.
- Imaging: fluoroscopy lets the surgeon watch screws go in, so everyone wears lead (chapter 22). Navigation and the O-arm, now the standard image guidance in spine surgery, make screw placement more accurate and lower the patient's x-ray exposure, which matters most in children, and spine robots guide implants into place (chapter 21).
- Neuromonitoring: many spine cases are watched with SSEPs and electromyographyih-lek-troh-my-OG-ruh-feeA test that records the electrical activity of muscles, usually through thin needles placed in the muscle.electr/o electricitymy/o muscle-graphy recordingFull entry .
- Two Mayo standMAY-oh standA small tray on an adjustable stand placed over or beside the patient during surgery to hold the instruments used most often.Full entry : one for bone instruments, one for soft tissue.
- Bone and disc: wipe the rongeurron-ZHURA strong surgical instrument with sharp, cup-shaped jaws used to bite away small pieces of bone.Full entry tip clean with a moist 4x4 after every bite, as the surgeon presents it to you, because the surgeon cannot look away from the wound. Save the bone as a specimen or as graftGRAFTTissue or a man-made material moved into place in surgery to replace or repair a damaged part.Full entry for a fusion, and keep disc tissue apart from bone.
- Prep and drape: the area is prepped wide, around both sides of the back, squared off with towels and covered with an adhesive drape and a laparotomylap-uh-ROT-uh-meeSurgery that opens the abdomen through a large cut to reach the organs inside.lapar/o abdomen-tomy cutting intoFull entry sheet, or a thyroid sheet for the neck.
What the spine instruments do:
- Cobb elevator: a broad periosteal elevator that strips the muscles off the spinous processes and laminae.
- Leksell rongeur: a large double-action rongeur that takes big bites, such as the spinous process.
- Kerrison rongeur: a punch that bites thin bone and ligament off the edge of the canal, made up-biting and down-biting, often at a 40 degree angle, in several widths.
- Pituitary rongeur: pulls disc material out piece by piece.
- Nerve root retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry (Love, Scoville): hold the nerve root and duraDOOR-uhThe tough outer layer of the membranes that cover the brain and spinal cord.Full entry toward the midlineMID-lineAn imaginary line down the center of the body; also, a type of IV catheter placed in a vein of the upper arm.Full entry so the disc can be reached.
- Self-retaining retractors: the Beckman-Adson or Weitlaner first, then deeper ones such as the Meyerding or Taylor as the wound deepens.
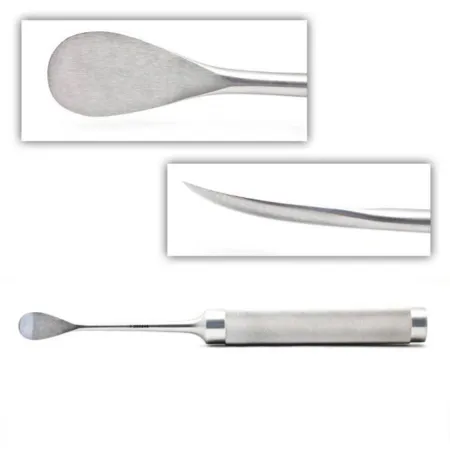
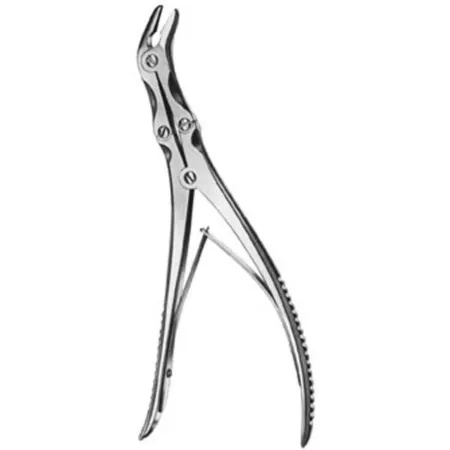
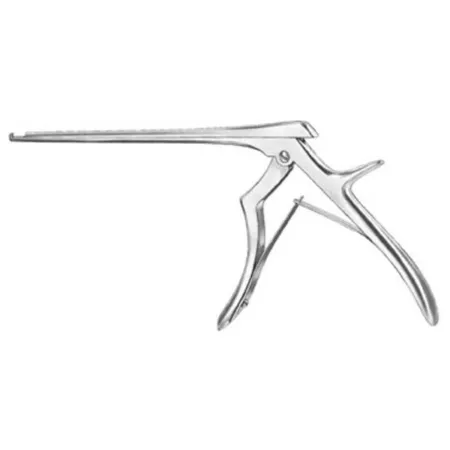
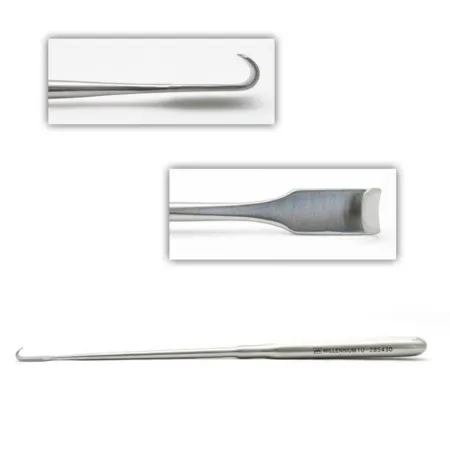

Laminectomy and discectomy
What and why: a laminectomy removes one or more laminae, the back of the vertebral arch, to open the spinal canal: for stenosisstuh-NOH-sisNarrowing of a passage or opening in the body, such as a blood vessel, heart valve or the spinal canal.sten/o narrow-osis conditionFull entry , a herniated disc, a fracture or dislocationdis-loh-KAY-shunAn injury in which the ends of bones that meet at a joint are forced out of their normal position.Full entry , a tumor, or to place a spinal cord stimulator. A hemilaminectomy takes one side; a laminotomy takes only a small window. A discectomy removes the part of the disc pressing on the nerve.
Before surgery: prone on a laminectomy frame or spinal table, or lateral for one side. A Wilson frame is set up as chapter 23 teaches. For L4 to L5 the prep runs from the lower edge of the shoulder blades to the lower edge of the buttocks and around both sides. The setup is a laminectomy set with the surgeon's retractor and an assortment of rongeurs, a bipolarby-POH-lerHaving two poles or two opposite ends; most often used as a short form of bipolar disorder.bi- twopolar having polesFull entry , bone wax and gelatin sponge, thrombinTHROM-binAn enzyme in the blood that turns fibrinogen into fibrin, the threads that hold a blood clot together.thromb/o clot-in substanceFull entry and oxidized cellulose.
Key steps (open lumbar):
- The surgeon may inject the incision with local anestheticLOH-kul an-es-THET-ikA drug that blocks feeling in one part of the body without making the person unconscious.Full entry and epinephrineep-ih-NEF-rinA hormone and drug, also called adrenaline, that raises heart rate and blood pressure and opens the airways.Full entry , makes a midline incision with a #20 or #10 blade and deepens it to the fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry .
- The back muscles are stripped off the spinous processes and laminae with a Cobb or other periosteal elevator, open 4x4s are packed along the bone to stop the bleeding and push the muscle aside, and self-retaining retractors go in.
- A spinal needle in the disc space and a fluoroscopy shot confirm the level.
- A large rongeur takes the spinous process and Kerrison rongeurs take the lamina, bite by bite; a drill may take part of the facet joint. Clean the tip after each bite and keep the bone.
- Patties now replace the 4x4s. The dura is loosened from the bone with a nerve hook or Freer elevator so it does not tear, and bone wax is ready for bleeding bone.
- The ligamentum flavum is cut with a #15 blade on a #7 handle and removed with Kerrison rongeurs, taking care of the epidural anesthesiaep-ih-DOOR-ul an-us-THEE-zhuhPain relief or numbness from an anesthetic drug given through a thin catheter into the space just outside the covering of the spinal cord.epi- upon, overdur/o dura (the tough covering of the spinal cord)-al relating toFull entry veins below it.
- The assistant holds the nerve root and dura toward the midline with a nerve root retractor while the surgeon removes the disc fragments with a pituitary rongeur and cleans the space with curettekyoo-RETA surgical instrument with a small spoon- or loop-shaped tip used to scrape tissue.Full entry . The disc goes to pathologypuh-THOL-uh-jeeThe study of disease and its causes and effects, or the disease changes found in a person or tissue.path/o disease-logy study ofFull entry in its own container, and the surgeon stays well inside the disc (Anatomy, above).
- The wound is irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry and the bleeding controlled with the bipolar. Every patty and sponge comes out, a drain may go in, and a long-acting local anesthetic may be injected; the back muscles are brought together with heavy absorbable sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry , the wound is closed in layers, and the skin with staples or nylon.
If the dura tears or must be opened, it is repaired, and the surgeon may keep the patient lying flat for 24 hours or longer while it heals. To remove a tumor inside the dura, the surgeon opens it with a hook and a #15 blade over a grooved director, holds the edges back with fine tractionTRAK-shunA steady pulling force applied to a body part with weights, ropes and pulleys.Full entry sutures and works under the microscope, with ultrasound to find the tumor; the dura is closed with braided nylon or PTFE suture.
After surgery: turn the patient back to supine with care. Infection, an unstableun-STAY-bulDescribes a client whose condition is changing quickly or is hard to predict.Full entry spine, nerve root damage, bleeding and a cerebrospinal fluidser-uh-broh-SPY-nul FLOO-idThe clear, watery fluid that bathes and cushions the brain and spinal cord.cerebr/o brainspin spine-al relating toFull entry leak are the risks. Before going home, the patient learns the warning signs: a fever of 101°F (38°C) or more, redness or drainage from the wound, a sudden severe headache, new weakness, or a change in bowel or bladder control. The patient avoids aspirin and anti-inflammatory drugs for some weeks, because they increase bleeding, and does not lift more than about 10 pounds or bend and twist at the waist until the surgeon allows it.
Wound class: I. A closed drain does not change the class by the CDC's definitions; one reference lists the case as Class II when a drain is placed.
Microdiscectomy and minimally invasive spine surgery
What and why: the same disc can be removed through a small tube, with less muscle cut, less pain and a shorter stay; most patients go home the same day and return to work in 4 to 6 weeks. The patient is told beforehand that the surgeon may need to change to an open incision, and the team is ready for it.
Before surgery: general, spinal or local anesthesiaLOH-kul an-es-THEE-zhuhNumbing medicine applied to or injected into one small area, so a procedure there is not felt while the person stays awake.Full entry with sedationsih-DAY-shunA calm, relaxed or sleepy state brought on by drugs, or the use of drugs to cause it.sed calm, settle-ation processFull entry ; prone on a radiolucent spinal table, frame or Andrews table; the C-arm and the microscope or an endoscopeEN-duh-skohpA thin tube with a light and a camera that is passed into the body to look inside an organ or cavity.endo- within-scope instrument for viewingFull entry .
Key steps:
- A spinal needle placed under the C-arm finds the level; a guidewire goes through it, and you hold the wire with a clamp while the needle comes out.
- Through a 1 to 1.5 cm incision, dilating tubes of rising size separate the muscle, and a tubular retractor slides over them, docks on the lamina and is locked to an arm fixed to the bed.
- The microscope or endoscope is brought in. A long electrode on the electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry clears the soft tissue, and a Kerrison rongeur, Leksell rongeur or long cutting burr removes a small window of lamina.
- A nerve root retractor holds the root, the epidural veins are coagulationkoh-ag-yuh-LAY-shunThe process by which blood changes from a liquid into a gel, forming a clot.coagul clot-ation processFull entry with the bipolar, and the disc is cut and its loose pieces removed with disc rongeurs.
- The space is irrigated with lactated Ringer's solutionLAK-tay-tid RING-erz suh-LOO-shunAn isotonic IV fluid containing water, sodium, chloride, potassium, calcium and lactate.Full entry , bleeding is controlled with the bipolar and gelatin sponge, the tube comes out, and the skin is closed with strips or skin glue.

Wound class: I.
Posterior cervical laminectomy
What and why: opens the back of the cervical spine to take pressure off the cord: for cervical stenosis, common in older adults, which can seriously injure the cord if it is not treated; for a tumor of the cord or the vertebrae; or after an injury, to remove bone fragments and fuse the spine.
Before surgery: a patient with severe spondylosis may need the breathing tube placed with a fiberoptic scope. The patient is anesthetized on the stretcher, turned prone with the head in a three-pin skull clamp, the arms tucked and the bed in slight reverse Trendelenburg positionree-VERS tren-DEL-un-burg puh-ZISH-unA position lying on the back on a bed or table that is tilted so the head is higher than the feet, with the body kept straight.Full entry to help the veins drain; neuromonitoring watches for change. If an autograft will be taken, the back of the iliacIL-ee-akHaving to do with the ilium, the large, wing-shaped upper part of the hip bone.Full entry crest is prepped too.
Key steps:
- A midline incision over the cervical spinous processes, a self-retaining retractor such as the Beckman-Adson, and the muscles stripped with Cobb or Key elevators; a clamp on a spinous process and an X-ray confirm the level.
- Bleeding is controlled with the bipolar, gelatin sponge and patties.
- A Leksell rongeur takes the spinous processes, Kerrison rongeurs and a drill with a small burr take the laminae, and the ligamentum flavum is removed; a disc can be removed as well.
- If the spine needs it, a fusion with instrumentation and bone graft follows.
- The wound is irrigated, often with antibiotic solution, and closed in layers, often with staples for the skin. A rigid cervical collar goes on before the patient wakes.
Wound class: I.
Spinal fusion
What and why: a fusion joins two or more vertebrae into one solid piece of bone, to stop painful or dangerous movement: after a decompression leaves the spine unstable, for a slipped vertebra (spondylolisthesis), for a degenerated disc, a deformity, a tumor or an injury. The Core Curriculum names two kinds, which are often combined: instrumented fusion, with screws, rods and plates holding the spine still while it heals, and interbody fusion, with bone or a cage packed with bone placed in the disc space. The graft may be the patient's own bone from the iliac crest, which hurts afterward, donor bone (allograft), demineralized bone matrix or another substitute, or the bone saved during the decompression. Chapter 39 teaches bone grafts and many of the tools spine fusion shares with orthopedics.
#### Anterior cervical discectomy and fusion (ACDF) What and why: removes one or more herniated or degenerated cervical discs and bone spurs from the front of the neck, then fuses the vertebrae. It treats pain in the neck, shoulders and arms, with numbness and weakness of the hands, from a disc, stenosis or spondylosis pressing on the cord or the nerve roots.
Before surgery: supine with a small roll under the shoulders to extend the neck slightly, the head turned a little away from the side of the approach, and the arms tucked. Gardner-Wells tongs may apply traction. If an iliac crest graft will be taken, a small bean bag or gel roll lifts that hip. A patient whose neck is unstable may be intubated awake; neuromonitoring is common. Both the neck and the hip are marked, injected with lidocaineLY-doh-kaynA local anesthetic that numbs an area, also given by IV to treat some fast, abnormal heart rhythms.Full entry and epinephrine, prepped and draped.
Key steps:
- The graft (if autograft): through an incision over the iliac crest, at least 3 cm behind the anterior superior iliac spine, the crest is stripped of periosteum and a graft is cut with an osteotome and mallet, an oscillating saw or a dowel cutter, then soaked in antibiotic solution. The bleeding bone is sealed, and the graft wound is counted and closed, or packed until the end in case more bone is needed, and covered with a towel.
- The neck: a transversetrans-VERSLying across something, at a right angle to its length.Full entry incision in a skin crease over the level, through the platysma. The surgeon works along the inner edge of the sternocleidomastoid, with a finger opening the plane between the carotidkuh-ROT-idHaving to do with the carotid arteries, the two large arteries on each side of the neck that carry blood to the head and brain.Full entry artery on the outside and the tracheaTRAY-kee-uhThe windpipe: the tube that carries air from the throat to the lungs.Full entry and esophagusih-SOF-uh-gusThe muscular tube that carries food and liquid from the throat to the stomach.esophag/o esophagusFull entry toward the midline, and a small self-retaining retractor holds it.
- The long neck muscles are peeled off the front of the spine with periosteal elevators or peanuts, with the bipolar for bleeding. A spinal needle in the disc and a lateral X-ray confirm the level.
- A self-retaining cervical retractor, such as the Cloward or Caspar, goes in with its blades under the long neck muscles, guardingGAR-dingTightening of muscles, or protecting a body part with the hands or posture, to avoid pain when it is touched or moved.Full entry the carotid artery and esophagus.
- The disc is cut with a #15 or #11 blade on a #7 handle and removed with pituitary rongeurs and curettes, while a vertebral spreader opens the space. Wipe each bite off the tip with a moist 4x4 and keep the disc as a specimen.
- A burr and Kerrison rongeurs remove the last disc and bone spurs, the posterior longitudinal ligament may be removed, and a nerve hook checks that the nerve roots and dural sac are free.
- A depth gauge and calipers measure the space. While the graft is shaped with small rongeurs, cover the neck wound with a moist 4x4 and a towel, and save every spare bit of bone. The graft is tapped into place with a tamp or impactor and a mallet.
- A small plate is screwed to the vertebrae above and below; irrigate the burr while the pilot holes are drilled. Fluoroscopy confirms the graft, plate and screws.
- The wound is irrigated, a drain may go in, the platysma is closed with absorbable suture and the skin with a buried stitch or staples. A rigid cervical collar goes on before the patient wakes.
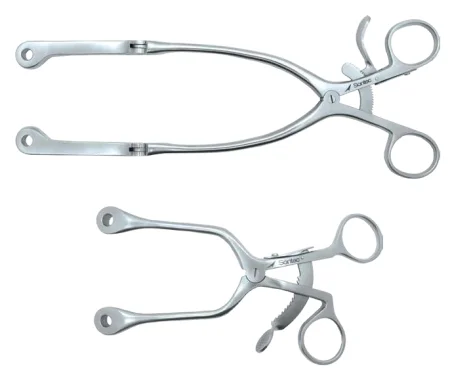
in the Cloward technique, the surgeon drills a round hole across the disc space with the Cloward drill and its guard, cuts a matching bone dowel from the iliac crest with a dowel cutter, and taps the dowel into the hole.
A cervical disc arthroplastyAR-throh-plas-teeSurgery to repair or replace a joint, most often the hip or knee.arthr/o joint-plasty surgical repairFull entry replaces the removed disc with an artificial one instead of a fusion. Its indications are much the same as for an ACDF, and keeping motion at that level may protect the discs next to it from wearing out.
A herniated cervical disc can also be removed through an endoscope, with the foramen enlarged, through a cannulaKAN-yoo-luhA thin tube placed into the body or a body opening to deliver or remove fluid or air.Full entry placed under fluoroscopy, with EMG monitoring, and the tiny wound is closed with strips.
After surgery: when the patient moves to the stretcher, keep the head in line with the body so an ACDF graft cannot shift, and keep the back table and Mayo sterile until the patient has left the room. Wound infection and nerve root damage are the risks to know; the hospital stay is about 3 to 5 days.
Wound class: I.
#### Posterior lumbar fusion What and why: a posterior lumbar interbody fusion (PLIF) removes the lamina and the diseased disc from the back, places cages packed with bone graft in the disc space to hold its height and let the bone grow through, and usually adds pediclePED-ih-kulA narrow stem or stalk that attaches a structure, such as a tumor or a skin flap, to the body.Full entry screws and rods. Pedicle screws pass through the pedicles, the bony bridges between the laminae and the vertebral bodies, and hold the spine still while the fusion heals.
Before surgery: prone on a laminectomy frame or spinal table, as for a laminectomy; if an iliac crest graft is taken first, the patient may start supine for the graft and then be turned. Have the laminectomy set, the fusion instruments and implant system, a high-speed drill with cutting burrs, the cage system and bone graft, and hemostatichee-moh-STAT-ikStopping bleeding; also, a product or agent used to stop bleeding.hem/o blood-stasis stopping, standing still-ic relating toFull entry including bone wax and fibrin sealant.
Key steps:
- The exposure and laminectomy are done as above, and the facet joints may be removed with the drill.
- The disc is removed, and the disc space is opened with a distractor under fluoroscopy; cage sizers find the right size.
- The cages, hollow titanium cylinders, are packed with graft and placed in the disc space with an introducer.
- For each pedicle screw, a burr opens the bone at the entry point, a Penfield dissector or probe finds the entrance, a probe follows the path down the pedicle, the hole is tapped, and the screw goes in.
- Bone graft is laid along the sides of the spine, and rods or plates, bent to the spine's normal curve, are locked onto the screws. The foramina are checked to be sure the nerves are free.
- After a final fluoroscopy check the wound is irrigated, a suction drain may be placed, and it is closed in layers.


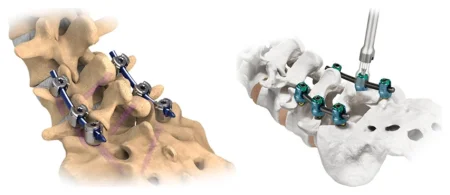
Spinal instruments and a rod system correct scoliosisskoh-lee-OH-sisA sideways curve of the spine.scoli/o crooked, curved-osis abnormal conditionFull entry , a sideways curve most often operated on in adolescence: rods bent to the right shape are seated in hooks and screws along the curve and turned to straighten it, and bone graft is laid along the bone. Expect blood loss and keep an accurate record of it.
Harrington rods, held only at their ends by hooks under the laminae, with a cast or brace afterward; newer systems fix the spine more firmly.
Wound class: I.
#### Anterior and lateral lumbar fusion Anterior lumbar interbody fusion (ALIF) reaches the front of the lumbar spine through the abdomen, so the disc can be removed and the space filled without cutting the back muscles. The usual route stays behind the peritoneumpair-ih-toh-NEE-umThe thin membrane that lines the belly cavity and covers most of the organs inside it.peri- aroundton stretched-eum a structureFull entry (retroperitoneal); going through the peritonealper-ih-toh-NEE-ulHaving to do with the peritoneum, the thin lining of the belly cavity and the organs inside it.Full entry cavity is kept for special cases, such as earlier retroperitoneal surgery. At L5 to S1 the great vessels lie right on the disc: the left common iliac vessels are moved aside, and the middle sacralSAY-krulHaving to do with the sacrum, the triangle-shaped bone at the base of the spine between the hip bones.Full entry vessels are divided. Electrosurgery is kept to a minimum there, because the superior hypogastric nerve plexusPLEK-susA network of nerves or blood vessels that branch and join together.Full entry lies in front of the disc, and damage to it can cause retrograde ejaculationih-jak-yuh-LAY-shunThe release of semen from the penis, usually at orgasm.Full entry in men; bleeding is controlled with finger and sponge pressure, or the bipolar. An X-ray with a spinal needle in the disc confirms the level, because L5 can be mistaken for the sacrumSAY-krumThe large, triangle-shaped bone at the base of the spine, between the two hip bones.sacr/o sacrumFull entry .
A lateral approach reaches the lumbar discs through the psoas muscle from the side:
- The patient lies on the right side on a radiolucent table, positioned so a true lateral image can be taken, held with tape and a bean bag, with the table bent to open the space between the ribs and the iliac crest.
- A markerMAR-kerSomething that can be measured, such as a substance in the blood, that shows a disease or body process is present.Full entry and fluoroscopy find the middle of the disc, and the surgeon enters the space behind the peritoneum through a short incision, by finger.
- dilatorDY-lay-terAn instrument used to stretch or widen an opening, canal or passage in the body.Full entry pass through the psoas to the disc, with EMG stimulation warning when a nerve of the lumbar plexus is close; a retractor then holds the path open, and its position is checked on both views before the disc is removed.
The nerves are most at risk at L4 to L5, and an injured L4 root or an irritated nerve to the skin of the thigh are the complications to know.
Wound class: I.
#### thoracicthuh-RAS-ikRelating to the chest, or to the middle part of the spine.thorac/o chest-ic relating toFull entry corpectomy What and why: a corpectomy removes one or more vertebral bodies and their discs, for a fracture pressing on the cord, a tumor, a herniated disc that has moved, or an infection of the bone or disc, and rebuilds the column.
Before surgery: lateral on a bean bag, or on a Jackson table when fluoroscopy is needed, because the bean bag gets in the way of the images. A double-lumenLOO-menThe open space inside a tube, such as a blood vessel, the intestine or a catheter.Full entry breathing tube lets the anesthesia provideran-us-THEE-zhuh pruh-VY-derThe licensed professional who gives anesthesia and watches over the client's breathing and vital functions during a procedure.Full entry deflate the lung on that side. A thoracic or trauma surgeon often makes the exposure.
Key steps:
- The level is marked under fluoroscopy, and a thoracotomythor-uh-KOT-uh-meeA surgical cut through the chest wall to reach the lungs, heart or other organs in the chest.thorac/o chest-tomy cutting intoFull entry is made over the rib two levels above the diseased vertebra; the rib is removed with a rib cutter and kept moist for graft.
- The lung is deflated, a rib spreader goes in, and the pleuralPLOOR-ulHaving to do with the pleura, the thin two-layer membrane that covers the lungs and lines the chest wall.pleur/o pleura-al relating toFull entry is opened. The segmental vessels are tied with 2-0 silk or clipped and divided.
- The discs come out with pituitary rongeurs and curettes, and the vertebral body with Kerrison rongeurs, osteotomes and a high-speed drill. Save the bone, moist, for graft.
- The gap is filled with a cage packed with bone, or an iliac crest graft, and plates and screws, drilled and tapped into the bone, may hold it.
- A chest tubechest toobA tube placed through the chest wall into the space around the lung to drain air, blood or fluid.Full entry goes in, the ribs are brought together with a rib approximator, and the wound is closed in layers.
A posterior fusion may follow in the same session: the patient is turned prone and prepped and draped again.
Wound class: I, or IV when it is done for an infection. One reference lists the thoracic approach as Class II; by the CDC's definitions no tract is entered.
Kyphoplasty and vertebroplasty
What and why: both treat a painful compression fracture of a vertebral body, usually from osteoporosisos-tee-oh-puh-ROH-sisA condition in which bones lose density and become thin, weak and easy to break.oste/o bonepor/o pore, small opening-osis abnormal conditionFull entry , sometimes from a tumor, by injecting bone cement (polymethyl methacrylate) through a needle into the vertebra to support it, at the level confirmed on fluoroscopy. They are for a fracture that still hurts after nonoperative care and that magnetic resonance imagingmag-NET-ik REZ-uh-nunts IM-uh-jingAn imaging test that uses a strong magnet and radio waves to make detailed pictures of the inside of the body.Full entry shows is still active. Kyphoplasty first inflates a balloon in the bone to make a cavity, which can restore some height and lets the cement go in at lower pressure, so less leaks out, a safety advantage over vertebroplasty. These cases are done by interventional radiologists, pain physicians and spine surgeons, in the IR suite (chapter 22) or the OR.
Before surgery: a radiolucent table, one C-arm swung between front and side views or two C-arms, lead for the staff, the kit with its bone access needles and stylets, bone biopsy needles, the balloon system and the cement mixing and delivery system. The patient is under general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry or monitored sedation, prone and well padded, with the spine extended over the fracture; the antibiotic is given beforehand. The C-arm is set up for a true front view of the vertebra and its position noted so it can be found again, and the pedicles are marked on the skin before the prep.
Key steps:
- Through a small stab incision, the bone needle is docked on the outer edge of the pedicle and tapped in with a mallet, with fluoroscopy at each step. On the front view the tip must stay outside the inner edge of the pedicle until it reaches the vertebral body: a tip inside that edge is in the spinal canal and must be moved at once.
- The needle is advanced into the body, and a drill or curette deepens the path.
- Kyphoplasty only: the balloon tamp goes in and is inflated with contrastKON-trastA dye or other substance given before an imaging test so body parts show up more clearly.Full entry , slowly, under fluoroscopy and a pressure gauge, until the height is restored, the maker's limit is reached or the balloon nears the edge of the bone; it is then deflated and removed, leaving a cavity.
- The cement is mixed to a paste and injected through the cannula in small amounts under live fluoroscopy. The surgeon stops at once if cement nears the edge of the vertebral body.
- The cannula stays until the cement hardens; then the needle comes out and a small dressing goes on.

After surgery: cement can leak out of the vertebra, more often in vertebroplasty. Into a vein it can travel to the lungs; backward into the canal it can press on the cord or nerves and need emergency open surgery. A misplaced needle can injure a nerve root or the cord, and the vertebrae next to the treated one can fracture later.
Wound class: I.
Spinal cord stimulator
What and why: a spinal cord stimulator treats long-lasting pain of the trunk and limbs that nothing else has relieved. Leads in the epidural space send small electrical pulses that the patient feels as tingling, which masks the pain; the aim is less pain, less medicine and a better life. A trial comes first: a temporary lead connected to an external generator for about 3 to 7 days, and only a patient whose pain improves by at least half goes on to a permanent implant. A thoracic lead treats back and leg pain, a cervical lead arm pain.
Before surgery: the product representative, the stimulator system and fluoroscopy must be in the room, with a bed the C-arm can work around. The position depends on where the batteryBAT-uh-reeIn law, touching a person on purpose without their consent.Full entry (the implanted pulse generator) will go: prone for the buttock, lateral for the abdomen or when the patient will be woken to test the lead. The prep covers everything from the lead site to the battery site.
Key steps (paddle lead through a laminectomy):
- A midline incision at the planned level, the muscles stripped off the spinous process and lamina, and a self-retaining retractor placed.
- A laminectomy with punches and rongeurs, and the lead slipped into the epidural space.
- The lead is tested with the programmer, either by waking the patient to say where they feel the tingling or with EMG under general anesthesia, and its position is checked with fluoroscopy; then it is anchored with 2-0 nonabsorbable suture.
- A pocket is made under the skin of the buttock or abdomen, the lead is tunneled to it, and the battery is attached, with the extra wire coiled beneath it, and stitched in place.
- Both wounds are irrigated and closed, an abdominal binder goes over the battery site, and an X-ray confirms the lead position.
Record every part as an implant. Depending on the type of lead, a trial or permanent lead can also be placed percutaneously, through the skin, without a laminectomy. An intrathecal pump, a co-related procedure, places a catheter in the CSF through a needle in the lower back and tunnels it to a refillable pump in the abdomen, which delivers a drug such as baclofenBAK-loh-fenA muscle relaxant that eases muscle stiffness and spasms from nerve conditions such as multiple sclerosis and spinal cord injury.Full entry for spasticityspas-TIS-ih-teeMuscle stiffness and tightness that resists stretching, more strongly the faster a limb is moved.Full entry or morphineMOR-feenA strong opioid drug used to relieve moderate to severe pain.Full entry for pain.
After surgery: one of the most frequent problems is a lead that moves out of place, which is why the lead and the battery are anchored; a life-threatening infection is rare.
Wound class: I.
Rhizotomy
A rhizotomy cuts nerve roots or fibers to stop pain or spasticity: a facet rhizotomy destroys the small sensory nerveSEN-suh-ree NURVA nerve that carries signals about touch, pain, temperature, position and the other senses toward the brain and spinal cord.Full entry to a worn facet joint with the bipolar, through dilators placed under fluoroscopy, and a selective dorsalDOR-sulHaving to do with the back of the body, or the top of the hand or foot.Full entry rhizotomy, mostly for children with cerebral palsySER-uh-brul PAWL-zeeA group of lifelong disorders of movement and posture caused by damage to the developing brain before, during or soon after birth.cerebr/o brain-al relating topalsy paralysisFull entry , cuts the sensory rootlets that EMG testing picks out through a laminectomy, with the motor roots protected under a rubber pad.
Wound class: I.
8Operations on the peripheral nerves
Neurosurgeons, plastic surgeons, hand surgeons and orthopedicor-thuh-PEE-dikHaving to do with the bones, joints, muscles, ligaments and tendons, and the branch of medicine that treats them.orth/o straightped/o child (the field began with straightening children's bones)-ic relating toFull entry surgeons all operate on the peripheral nerves. Hand and arm cases are done at an arm table, with the surgeon seated, so have sitting stools ready, and a pneumatic tourniquet is used often (chapters 23 and 31 teach the tourniquet unit and the cuff). A minor or plastic set is the base. The anesthesiaan-us-THEE-zhuhLoss of feeling or sensation, often brought on by drugs so that surgery or a procedure can be done without pain.an- withoutesthesi/o feeling, sensation-ia conditionFull entry is local, a regional block such as an IV regional (Bier) block, or general. epinephrineep-ih-NEF-rinA hormone and drug, also called adrenaline, that raises heart rate and blood pressure and opens the airways.Full entry in the local anestheticLOH-kul an-es-THET-ikA drug that blocks feeling in one part of the body without making the person unconscious.Full entry is used with extreme caution, and as little as possible, where the blood supply is limited: the fingers, toes, tip of the nose and penis (chapter 13). Some references say it is not used in the fingers, or is contraindicationkon-truh-in-dih-KAY-shunA reason not to give a drug or do a treatment, because in that person it could cause harm.contra- againstindication a reason to useFull entry there.
many carpal tunnel releases are now done wide awake, under local anesthesiaLOH-kul an-es-THEE-zhuhNumbing medicine applied to or injected into one small area, so a procedure there is not felt while the person stays awake.Full entry with no tourniquet (WALANT): about 20 mL of 1% lidocaineLY-doh-kaynA local anesthetic that numbs an area, also given by IV to treat some fast, abnormal heart rhythms.Full entry with 1:100,000 epinephrine, buffered with bicarbonateby-KAR-buh-naytA base in the blood that balances acid; the kidneys control it, and its level is measured on blood gas and chemistry tests.Full entry , numbs the hand and keeps it dry. Large studies have not borne out the fear that epinephrine in the hand kills tissue, and phentolamine can reverse it if needed.
Carpal tunnel release
What and why: the surgeon divides the transversetrans-VERSLying across something, at a right angle to its length.Full entry carpal ligament, the roof of the carpal tunnel, to free the median nerve. It can be done open or through an endoscopeEN-duh-skohpA thin tube with a light and a camera that is passed into the body to look inside an organ or cavity.endo- within-scope instrument for viewingFull entry , whose advantage is one or two small incisions instead of a longer cut across the palm, and the symptoms usually go away once the nerve is free. It is an outpatient operation, and the patient goes home within hours.
Before surgery: supine with the arm out on a hand table; the tourniquet goes on the forearm or upper arm, and an Esmarch bandage empties the arm of blood before it is inflated. The arm is prepped all the way around, a stockinette may go over the hand, the hand is drawn through an extremity sheet, and a three-quarter sheet covers the hand table. The setup is a hand set; the endoscopicen-doh-SKOP-ikDone with an endoscope, a thin tube with a light and camera passed into the body.endo- within-scopic viewingFull entry operation adds its own scope system, and a rolled towel holds the wrist extended about 15 to 20 degrees.
Key steps (open):
- A curved or straight incision in the palm, parallel to the crease at the base of the thumb, carried to the wrist crease, with a #15 blade.
- Blunt dissectiondy-SEK-shunA tear in the inner layer of an artery wall that lets blood split the layers apart; also, the cutting apart of tissue in surgery.Full entry with small Metzenbaum scissors exposes the fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry ; small Weitlaner retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry , skin hooks or sharp Senn retractors hold the edges.
- The surgeon cuts the transverse carpal ligament with the #15 blade and lengthens the cut with tenotomy scissors, guardingGAR-dingTightening of muscles, or protecting a body part with the hands or posture, to avoid pain when it is touched or moved.Full entry the median nerve, then passes a small curved clamp along the cut to check that every attachmentuh-TACH-mentThe deep emotional bond between an infant and a parent or caregiver.Full entry is released. A tenosynovectomy may follow.
- The wound is irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry , the tourniquet is let down and bleeding is stopped with the bipolarby-POH-lerHaving two poles or two opposite ends; most often used as a short form of bipolar disorder.bi- twopolar having polesFull entry ; the surgeon may inject bupivacainebyoo-PIV-uh-kaynA long-acting local anesthetic used to numb an area, block nerves, or give epidural and spinal anesthesia.Full entry for pain.
- The skin is closed with an absorbable buried stitch or interrupted nylon, and the hand is wrapped in a bulky dressing of fluffed gauze, with a splint.
Key steps (endoscopic):
- A transverse incision in a wrist crease, between the flexor carpi ulnaris and palmaris longus tendons, down to the forearm fascia, which is opened.
- The tissue on the little-finger side is held aside, the wrist is extended over the towel, and the synovium is lifted off the underside of the ligament.
- A hamate finder and a dilatorDY-lay-terAn instrument used to stretch or widen an opening, canal or passage in the body.Full entry make a path for the scope, and the surgeon divides the ligament from inside, then releases the forearm fascia over the nerve; the details follow the maker's instructions for the system.
- The wound is irrigated and closed with a 4-0 nylon skin stitch.

After surgery: an elastic bandage over the bulky dressing works as a splint. Problems are rare; damage to the median nerve and wound infection are the ones to know.
Wound class: I.
Ulnar nerve release or transposition
What and why: the ulnar nerve can be squeezed where it passes behind the elbow. The surgeon either releases it where it is, by cutting the tight band of tissue (the ligament of Osborne) over it, or frees it and moves it to the front of the medial epicondyle, a transposition, under a sling of fascia that keeps it from slipping back into the tunnel.
Before surgery: supine, the arm on an arm table, held up over the patient or laid across the body, as the surgeon prefers; a tourniquet on the upper arm, inflated after the arm is emptied of blood. Local anesthesia or a Bier block may be used. Have moist umbilical tape, vessel loops or a Penrose drain to loop around the nerve, and be ready to help if the bone needs reshaping.
Key steps (transposition):
- The surgeon makes an incision over the nerve at the medial epicondyle and frees the nerve with Metzenbaum scissors, then passes a moist tape or vessel loop around it to handle it gently.
- The nerve is freed from above the elbow to below it, and the muscle and fascia where it enters and leaves may be slit so it cannot kink.
- A flap of fascia is raised over the medial epicondyle, and the nerve is moved from its groove behind the epicondyle to the front of it, under the flap.
- The flap is stitched loosely, often with 2-0 absorbable sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry , so it protects the nerve without squeezing it. The tourniquet is let down and bleeding is controlled.
- The wound is irrigated, closed in layers and dressed, and a splint or cast goes on.
After surgery: most patients' pain is fully relieved; nerve injury, infection and blood clots are the risks.
Wound class: I.
Peripheral nerve repair
A cut nerve is repaired as an emergency, because delay worsens the result. The patient lies supine with the arm on a hand table and a tourniquet on the arm; a badly damaged limb is cleaned and debridementdih-BREED-muntThe removal of dead, damaged or infected tissue from a wound so it can heal.Full entry first. Under the microscope, the surgeon frees the nerve ends, holds them together with two fine tractionTRAK-shunA steady pulling force applied to a body part with weights, ropes and pulleys.Full entry sutures, and trims them in 1 mm slices on a moist wooden tongue blade or a silicone block until clean fibers show. The repair joins either the outer sheathSHEETHA covering that wraps around a structure; in procedures, a short hollow tube left in a blood vessel to pass catheters through.Full entry (epineurium), with fine nylon such as 6-0 or 7-0 through each quarter of the nerve, or each bundle of fibers, with even finer nylon such as 10-0. Keep the nerve moist with frequent irrigation of balanced salt solution. A gap the ends cannot bridge is filled with a nerve graftGRAFTTissue or a man-made material moved into place in surgery to replace or repair a damaged part.Full entry from elsewhere in the body or a collagenKOL-uh-jenThe main structural protein of the body, which gives strength to skin, bones, tendons, ligaments and scar tissue.coll/a glue-gen producingFull entry nerve conduit, soaked in saline as its maker directs before it is sewn in. The limb is splinted until the nerve heals.
Wound class: a fresh accidental wound is Class III.
9Wound classes in neurosurgery
Most neurosurgery enters no tract, so it is clean. The class changes when the operation goes through the nose or a sinusSY-nusA hollow space in the body, most often one of the air-filled spaces in the skull bones around the nose.Full entry , when it treats a fresh injury, or when infection is already there (chapter 11 teaches the classes).
| Class | Neurosurgical examples |
|---|---|
| I, clean | Every cranialKRAY-nee-ulRelating to the skull, or toward the head end of the body.crani/o skull-al relating toFull entry , cerebrospinal fluidser-uh-broh-SPY-nul FLOO-idThe clear, watery fluid that bathes and cushions the brain and spinal cord.cerebr/o brainspin spine-al relating toFull entry , stereotactic, spine, stimulator and nerve release case that enters no tract and treats no infection |
| II, clean-contaminated | Transsphenoidal surgery, and any approach that opens the nose, a sinus or the mouth, such as a frontalFRUN-tulRelating to the front of the body, or to the forehead and the bone or brain area behind it.Full entry sinus repair |
| III, contaminated | A fresh open injury: a penetrating brain wound, an open skull fracture, a freshly cut nerve |
| IV, dirty | Infection already present: a brain or spinal abscessAB-sesA closed pocket of pus in tissue, walled off by the body.Full entry , an infected shuntSHUNTA passage that moves blood or other fluid from one place to another, either made by a surgeon or present in the body.Full entry or bone flap, an infected disc or vertebra, or an old wound with dead tissue |
10After neurosurgery
Moving the patient: lines, drains and the urinary catheter are easy to pull out in the move, a patient who had spine surgery is logrollLOG-roleTo turn a client as one unit, keeping the head, neck, spine and hips in a straight line.Full entry with the spine in line, and a cervicalSER-vih-kulRelating to the neck, or to the cervix, the lower end of the uterus.cervic/o neck, cervix-al relating toFull entry collar or brace goes on before the patient wakes.
Complications to watch for are the ones each operation above names: a cerebrospinal fluidser-uh-broh-SPY-nul FLOO-idThe clear, watery fluid that bathes and cushions the brain and spinal cord.cerebr/o brainspin spine-al relating toFull entry leak, most likely after posterior fossaFOS-uhA shallow hollow or dip in a bone or on the body's surface.Full entry and transsphenoidal surgery; bleeding and a new clot; infection and meningitismen-in-JY-tisInflammation of the meninges, the membranes that cover the brain and spinal cord.mening/o meninges-itis inflammationFull entry ; a new neurologic deficit, found against the baseline; seizureSEE-zherA sudden burst of abnormal electrical activity in the brain that changes movement, feeling, behavior or awareness.Full entry ; vasospasm after a subarachnoid hemorrhagesub-uh-RAK-noyd HEM-er-ijBleeding into the fluid-filled space between the two inner layers of tissue that cover the brain.sub- underarachn/o spider (the web-like arachnoid layer)-oid likeFull entry ; hormone changes such as diabetes insipidusdy-uh-BEE-teez in-SIP-ih-dusA disorder of antidiuretic hormone: the body makes too little of it, or the kidneys do not respond to it.Full entry after pituitary surgery; shuntSHUNTA passage that moves blood or other fluid from one place to another, either made by a surgeon or present in the body.Full entry failure; venous air embolismEM-buh-liz-umThe blocking of a blood vessel by a mass carried there in the blood (an embolus), such as a clot, fat or an air bubble.embol/o plug-ism conditionFull entry ; and positioning injuries from long cases (chapter 31).
Recovery: neurosurgery patients may live with changes in vision, hearing, swallowing, speech, movement, feeling or thinking. Therapists and rehabilitation help them recover, and the patient and family learn to watch for warning signs: a change in mental state or behavior, growing weakness, seizures, more pain or signs of infection, as well as how to use a cervical collar or brace and care for the wound.
What to take from this chapter
- Neurosurgery works on the brain, the spine and the peripheral nerves; nervous tissue does not grow back, and the brain and cord are delicate, so they are handled gently, often under magnification. A patient who seems unaware may be fully aware of what is happening: talk to them.
- A skull clamp holds the head with three pins. At least three people move a pinned head, every lock is checked, the body is never moved while the head is locked, and all three pins are confirmed out at the end.
- The craniotomy pattern: Raney clips on the scalp (and in the count), burr holes with an irrigated perforator, the dura freed with a Penfield, the flap cut with the craniotome's footplate and guarded on the back table, the dura opened over a patty and kept moist, then a watertight dural closure, plates, galea and skin.
- Inside the skull and the spinal canal, moist patties replace gauze. They protect the brain under the suction, and every patty and cotton ball comes back whole with its string and is counted; bone wax is ready for every bone edge.
- In aneurysm surgery a temporary clip stays loaded at all times, clips are never squeezed by hand and an opened clip is discarded, there are two appliers for each type, and a rupture calls for suction and patties at once.
- A shunt is handled as little as possible, kept free of lint and lubricant, primed with no air and placed with its valve facing the right way. Through the nose, the graft is taken first on its own setup, nasal patties and the throat pack are counted, and the case is Class II.
- On the spine, the level is confirmed by imaging, rongeur tips are wiped clean at every bite, bone is saved and disc kept apart, and the surgeon stays inside the disc because the great vessels lie in front. In kyphoplasty, the cement goes in a little at a time under live fluoroscopy, because cement that leaks out can reach the lungs or the spinal canal.
- Carpal tunnel release divides the transverse carpal ligament; an ulnar transposition moves the nerve in front of the elbow under a fascial sling. Most neurosurgery is Class I; the nose, a sinus, a fresh injury or an infection changes the class.
Check yourself5 quick questions
Free for everyone. Pick an answer for each, then check them all at once.
In the ORWhere you'll use this
The chapter's whole question pool in sets of 10, with the answer explained after each one.
Part of the educators programThe chapter's words on spaced cards: the ones you miss come back sooner.
Part of the educators programGiven by your class's teacher. Each class draws its own 25 from the chapter's pool.
Part of the educators program
Suggest a fix
Something wrong, unclear or out of date in this chapter? Tell us and we will fix it for everyone. Your email is only used to reply.