Asepsis and sterile technique
The rules that keep a surgical wound free of germs, and the habit of mind that makes you follow them when nobody is watching.
1Why it matters
Every incision opens a door into the body. Past the skin there is little to stop germs except the patient's own defenses, and surgery has already weakened those. An infection at the incision can mean another operation, a week or more back in the hospital, or a patient who never fully recovers.
A surgical site infection is one of the most common infections patients pick up in a hospital. Many of these infections can be prevented, and the surgical technologistSUR-jih-kul tek-NOL-uh-jistA member of the operating room team who prepares the sterile field and instruments and hands them to the surgeon.Full entry is the one person on the team whose whole job, from opening the first pack to the final count, centers on keeping the field free of germs. That makes this the most important chapter in the course.
asepsisay-SEP-sisThe state of being free of germs that cause disease, and the practices used to keep things that way.a- withoutsep- decay or infection-sis conditionFull entry means freedom from the germs that cause disease. surgical asepsisSUR-jih-kul ay-SEP-sisPractices that keep an area or object completely free of microorganisms; also called sterile technique.a- withoutsepsis decay, infectionFull entry is the set of rules that gets you there: how you open, set up, move, pass instruments and fix mistakes. This chapter gives you the rules and the reasons behind them, because a rule you understand is a rule you keep under pressure.
The rules are the same for every patient. Age, background, diagnosis and the size of the operation never change them. A small hand operation gets the same care as a heart operation.
2The words of asepsis
asepsisay-SEP-sisThe state of being free of germs that cause disease, and the practices used to keep things that way.a- withoutsep- decay or infection-sis conditionFull entry has its own vocabulary, and the cert exam uses all of it. Here it is in plain words.
Germs and infection
- pathogenPATH-uh-jenA germ, such as a bacterium, virus, fungus or parasite, that can cause disease.path/o disease-gen something that producesFull entry : a germ that can cause disease.
- Infection: pathogens that get into body tissue, multiply and cause harm.
- sepsisSEP-sisA severe whole-body response to an infection that damages the body's own organs.Full entry : a life-threatening reaction of the whole body to an infection.
- sporeSPORA tough, resting form that some bacteria and fungi make, able to survive heat, drying and many cleaning products.Full entry : a tough, resting form of some bacteria that survives heat, drying and many chemicals. Kill the spores and every other germ is dead too. (Prions, which are not living germs, need special processing.)
- Resident flora: germs living deep in the skin and hair folliclehair FOL-ih-kulA small tube-shaped pocket in the skin from which a hair grows.Full entry . A scrub reduces them but cannot remove them.
- transientTRAN-zee-entLasting only a short time and then going away.Full entry flora: germs picked up on the skin's surface from what we touch. Washing removes most of them.
- healthcare-associated infectionHELTH-kair uh-SOH-see-ay-tid in-FEK-shunAn infection a client gets while receiving health care that was not present or incubating when care began.Full entry (HAI): an infection picked up while receiving care, once called hospital-acquired or nosocomial.
- Surgical site infection (SSIes-es-EYE (said as letters)An abbreviation that can mean surgical site infection or sliding scale insulin.Full entry ): an infection of the incision, or of the organ or space operated on, within 30 days of surgery, or, for a deep or organ or space infection, up to 90 days after some operations such as a joint replacement.
How germs travel
- mode of transmissionmohd uv trans-MISH-unThe way a germ travels from where it lives to a new person.Full entry : the route a germ takes to a new host.
- dropletDROP-litA drop of moisture sprayed from the nose or mouth when a person coughs, sneezes or talks, which can carry germs a short way.Full entry : moisture from the nose or mouth, sent out by talking, coughing or sneezing. Droplets fall within a short distance.
- Airborne contamination: germs riding on dust, lint and shed skin cells that float in the air and settle onto open sterile items or into the wound.
- Fomite: an object that carries germs from one place to another, like a door handle or a phone.
- Vector: a living carrier, such as a mosquito, that brings germs to a new host.
- Cross-contamination: germs passed from one person, object or place to another.
Removing and killing germs
- Bioburden: how many germs, and how much soil such as blood, are on an item before it is cleaned or sterilizationstair-uh-luh-ZAY-shunA process that destroys all microorganisms, including spores, on an item; also a permanent birth control procedure.Full entry .
- decontaminationdee-kun-tam-ih-NAY-shunRemoving or destroying germs, chemicals or radioactive material from a person, surface or object to make it safe.de- removecontamination being made uncleanFull entry : cleaning and disinfectiondis-in-FEK-shunCleaning a surface or object with chemicals or heat to kill most germs, though not always all bacterial spores.Full entry a used item so it is safe to handle.
- Antiseptic: a chemical that reduces germs on skin, used for the scrub and the patient's skin prep.
- disinfectantdis-in-FEK-tuntA chemical used on objects and surfaces to kill most germs.Full entry : a chemical that kills most germs on objects and surfaces, usually not spores. It is too harsh for skin.
- Bactericidal kills bacteria. Bacteriostatic stops them multiplying without killing them.
- A fungicide kills fungi, a virucide kills viruses, and a sporicidalspor-ih-SY-dulAble to kill bacterial spores, the tough resting forms of some bacteria.Full entry agent kills spores.
- Sterilization: a process that kills all microorganisms, spores included.
- Terminal disinfection: the final disinfection that makes used items safe to handle. The end-of-day clean of an OR is called terminal cleaning.
Sterile and contaminated
- Sterile: free of all living microorganisms, spores included.
- Contamination: germs, or the likely presence of germs, on something that should be sterile. A sterile item that touches anything non-sterile is contaminated.
- sterile fieldSTAIR-ul feeldAn area set up with sterile drapes and supplies, kept free of all germs, for a sterile procedure.Full entry : the area around the patient prepared with sterile drapes, holding only sterile items and people.
- surgical asepsisSUR-jih-kul ay-SEP-sisPractices that keep an area or object completely free of microorganisms; also called sterile technique.a- withoutsepsis decay, infectionFull entry : the practices that keep the sterile field and sterile items free of germs.
- Strike-through: fluid soaking through a drape, gown or wrapper, carrying germs from the non-sterile side to the sterile side. A puncture does the same.
- Wicking: liquid creeping through a porous material, the way oil climbs a lamp wick. It is how strike-through happens.
- Event-related sterilitysteh-RIL-ih-teeThe state of being completely free of living germs, including spores; also, being unable to have children.Full entry : a package stays sterile until something happens to it, rather than until a date passes.
- Surgically clean: cleaned and disinfected, but not sterile.
- Surgical conscience: the habit of admitting and fixing a break in sterile technique, even when nobody else saw it.
3Sterile, clean and surgically clean
Sterile has no degrees. An item is sterile or it is not. There is no "almost sterile" and no "sterile enough." If you cannot say for certain that an item is sterile, treat it as non-sterile.
asepsisay-SEP-sisThe state of being free of germs that cause disease, and the practices used to keep things that way.a- withoutsep- decay or infection-sis conditionFull entry is the absence of the germs that cause disease. Sterile goes further: no living microorganisms at all, harmful or harmless. Everything that enters the wound or sits on the field has to be sterile.
Most of the room is surgically clean instead: cleaned and disinfectiondis-in-FEK-shunCleaning a surface or object with chemicals or heat to kill most germs, though not always all bacterial spores.Full entry , but never sterilizationstair-uh-luh-ZAY-shunA process that destroys all microorganisms, including spores, on an item; also a permanent birth control procedure.Full entry . The floor, the OR bed, the lights and the furniture are safe to work around, but they never touch a sterile item. Skin is never sterile either. The scrub and the skin prep cut its germs a great deal but never to zero, so gloves, gowns and drapes still go over it.
Event-related sterility
Most sterile packages carry no "use by" date. A package stays sterile until an event spoils it:
- moisture, from a wet surface, a spill or condensation
- a tear, hole or puncture in the wrapper
- a broken seal, or a package that has been opened
- rough or repeated handling that wears the wrapper thin
- a fall to the floor, depending on the wrapper
A few commercial items, such as some sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry , medicines and solutions, still carry an expiration date because the product itself breaks down over time. Those dates still count.
4Where germs come from
Germs reach a wound from two directions.
From the patient (endogenous sources). The patient's own skin, nose, mouth and bowel carry germs that are harmless where they live and dangerous inside a wound. Most surgical site infections start with these germs. That is why the skin is prepped before the incision, why drapes wall off the incision, and why instruments that touch the bowel are kept apart from the rest.
From outside the patient (exogenous sources). These are the people in the room and the environment. People are the biggest outside source in any OR. We shed skin cells and hair all day long, and we breathe out dropletDROP-litA drop of moisture sprayed from the nose or mouth when a person coughs, sneezes or talks, which can carry germs a short way.Full entry every time we talk. The room adds dust, lint and moving air, and equipment and supplies add whatever is on their surfaces.
How germs travel in the OR
- Touch. A glove touches something it should not.
- The air. Skin cells, lint and dust settle onto an open field. Every opening of the door, every extra person and every shake of a drape stirs up more.
- Droplets. Talking and coughing send them toward the field. Masks catch most, and quiet catches the rest.
- Objects. A phone or a chart is a fomite that carries germs into the room and onto hands.
- Moisture. Fluid that soaks through a drape, towel or wrapper carries germs from the non-sterile side. This is strike-through.
So the doors stay closed, which keeps the room's air pressure above the hallway's and pushes air out instead of in. Traffic and talking stay low, the field is set up farthest from the door, and nothing crosses it that does not belong there.
You cannot make a person sterile. The scrub, gown and gloves keep the germs you carry on your side of a barrier. That is why the rules are about barriers, distance and movement.
5The sterile field
A sterile fieldSTAIR-ul feeldAn area set up with sterile drapes and supplies, kept free of all germs, for a sterile procedure.Full entry is made for every operation: the draped patient, the back table, the Mayo standMAY-oh standA small tray on an adjustable stand placed over or beside the patient during surgery to hold the instruments used most often.Full entry , the ring stand and everything on them. AST groups the rules of asepsisay-SEP-sisThe state of being free of germs that cause disease, and the practices used to keep things that way.a- withoutsep- decay or infection-sis conditionFull entry under a few principles. The first is that a sterile field is created for each procedure. These rules keep it sterile.


- Only sterile items go on the field. Anything placed on the field, or moved around inside it, must be sterile.
- Check every item before it is opened. The scrub and the circulator check it together: the package is whole, dry and sealed, its chemical indicator shows it went through sterilizationstair-uh-luh-ZAY-shunA process that destroys all microorganisms, including spores, on an item; also a permanent birth control procedure.Full entry , and any expiration date has not passed. If anything is wrong, it does not go on.
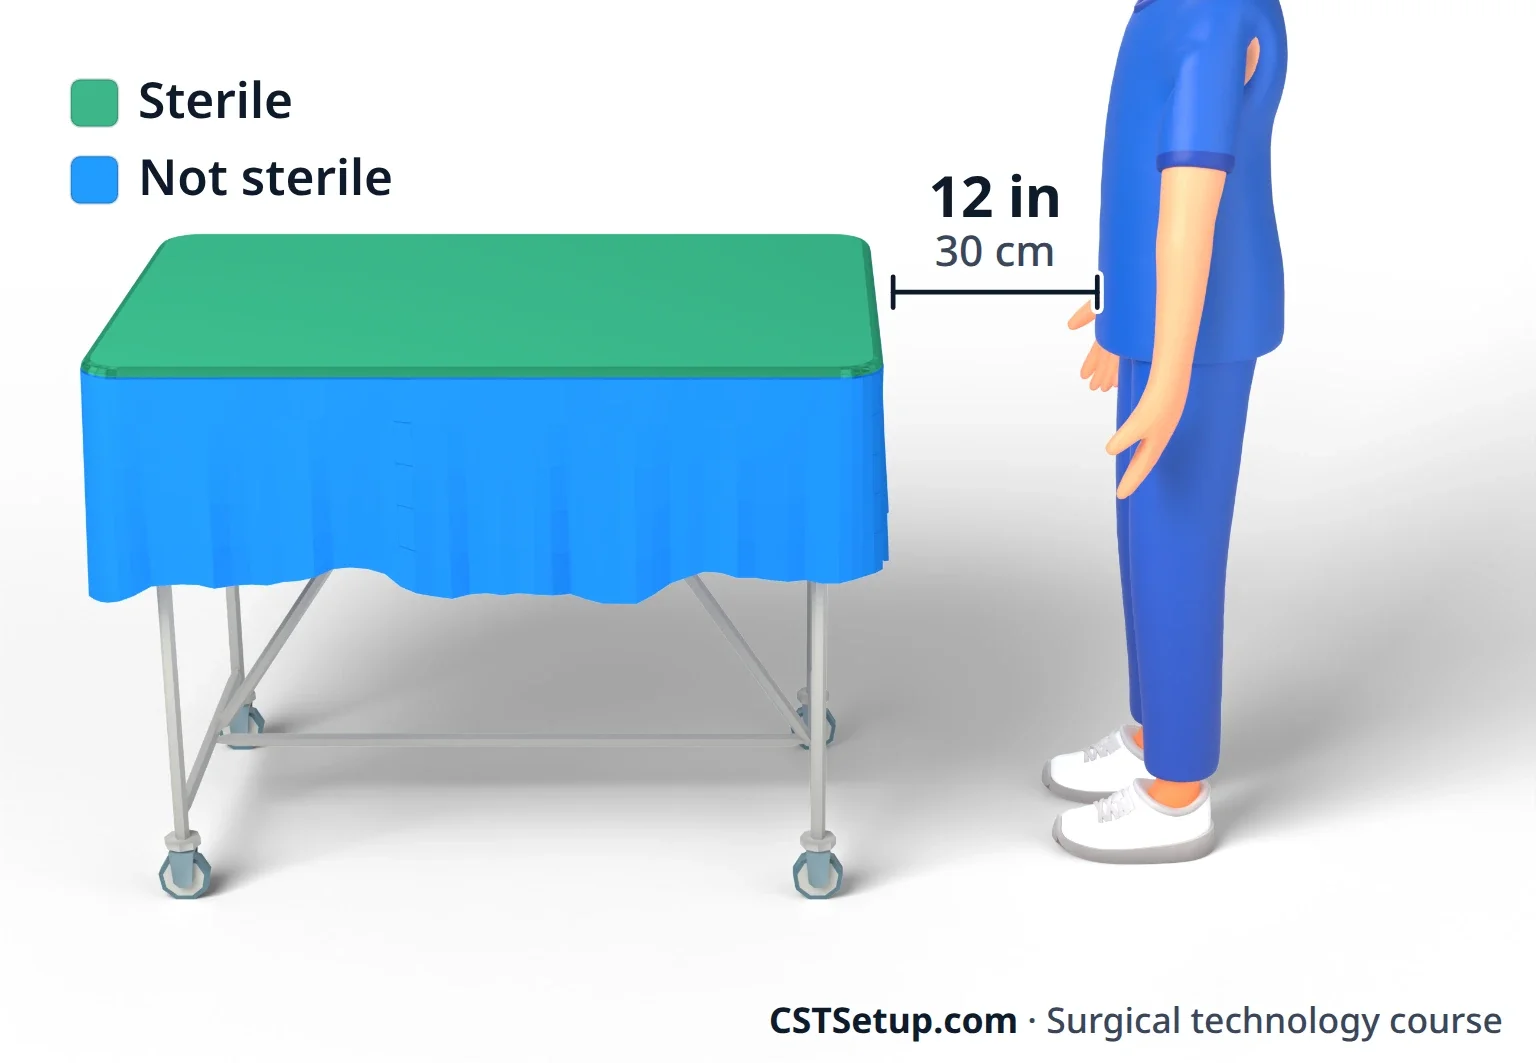
- A draped table is sterile only on top. Anything that hangs or falls below the tabletop is no longer sterile, and it never comes back up. A drape is never shifted once it is placed, because shifting drags its non-sterile part up onto the field.
- The edges of a wrapper or container are not sterile. Open the far flap of a wrapper away from you first and the near flap toward you last, and let the contents be lifted out or dropped onto the field without touching the edges.
- Open as close to the time of use as you can. The longer a field sits open, the more dust and skin cells settle on it.
- Watch the field all the time. A field nobody is watching cannot be trusted and is treated as contaminated. A scrub who has set up a field stays with it, even through a delay.
- A barrier that fluid soaks through, or that tears, is contaminated. That is strike-through. Most of today's disposable drapes and back table covers are impervious (check the label), so blood or irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry sitting on top of them does not soak through: suction or sponge it up as you go. A towel or cloth wrapper that gets wet, or a pack that is wet inside, is contaminated.
- Solutions are poured, never recapped. Once a bottle of sterile solution or medicine is opened, it is poured once and the rest is thrown away. A recapped bottle is not sterile.
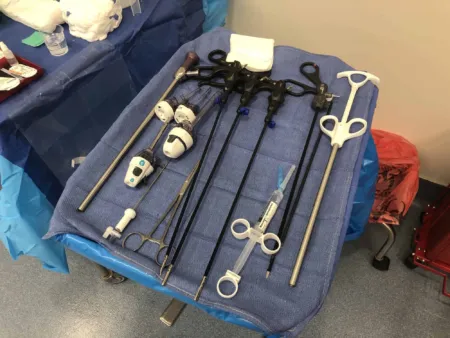
The Mayo stand
The Mayo stand cover is a sterile sleeve, closed at one end, that encloses the stand's tray, and the stand moves over the patient only after the patient is draped. So AST counts the underside of a draped Mayo stand as sterile too. Cords and tubing under it stay sterile as long as their ends were passed off the field correctly before the stand moved in.
Stand at a set-up field and call each spot sterile or not.
This lab runs in the browser with JavaScript on.
This browser could not start the 3D room. Everything the lab practices is in the chapter.
6Opening and delivering sterile items
Non-sterile team members, usually the circulator and the scrub before scrubbing in, open the sterile items. The scrub, once gowned and gloved, sets them up. Before anything is opened, the furniture is in place, the surfaces are clean and dry, and everyone near open supplies wears a mask.
A routine order
A set order means fewer moves and nothing forgotten:
- The back table pack
- The basin set
- Small wrapped items, such as towels
- Peel packs, including sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry
- Instrument sets
The scrub's own gown and gloves are opened on a separate surface, such as the Mayo standMAY-oh standA small tray on an adjustable stand placed over or beside the patient during surgery to hold the instruments used most often.Full entry , never on the back table. That keeps dripDRIPA continuous IV infusion of fluid or a drug, given slowly over time by gravity or a pump.Full entry off the field and keeps the scrub from reaching across it.
The back table pack
Most back table packs are made and sterilizationstair-uh-luh-ZAY-shunA process that destroys all microorganisms, including spores, on an item; also a permanent birth control procedure.Full entry by a manufacturer and arrive in a clear plastic dust cover. The circulator checks it (the cover whole and sealed, the pack dry, its indicator changed, the label in date), tears the dust cover open and slides the pack out onto the middle of the back table, long side along the table, as the diagram printed on the pack shows. The pack's outer wrapper is the back table cover. Open it in the order its diagram shows; most open lengthwise first. Hands under the cuff, unfold the cover toward one end of the table, then the other, so it runs the full length. Then grasp the fold nearest you and open it toward you, letting it fall over the edge. Never reach across the open pack: step around to the other side of the table and open that fold toward you the same way. Once open, the cover is never shifted.
Check it, take it out of its dust cover, and open it without ever reaching over the field.
This lab runs in the browser with JavaScript on.
This browser could not start the 3D room. Everything the lab practices is in the chapter.
Wrapped packs
Instrument sets and small items wrapped in your hospital's sterile processing department are usually wrapped envelope style (some large packs and trays are square-folded) and sealed with chemical indicator tape. A pack wrapped envelope style has four flaps. Open the flap farthest away first, then the two sides, then the near flap last, toward you. In that order a non-sterile arm never passes over the open inside. On a table, walk around the pack rather than reach across it.
When a small pack is held in the hand, the opener gathers each flap into that hand so the wrapper covers it, then offers the item to the scrub or drops it gently onto the field. The outer inch of any opened wrapper counts as non-sterile, and sterile items never sit in it.
Peel packs
A peel pack is peeled apart along its seal, never torn. The inside edge of the seal is the line between sterile and non-sterile, and the contents must never slide out over it. Either hold the pack open for the scrub to lift the item straight out, or flip the item onto the field with a quick, controlled pull. Stand close enough that it lands on the field, but never reach over it.
Heavy, sharp and rigid items
- Heavy or bulky items are opened on their own table, or handed straight to the scrub. Flipped onto the field, they can punch through the table cover.
- Blades and other sharps are handed straight to the scrub or opened where they can be seen. They never go onto an instrument tray, where they can hide.
- A rigid container is checked before it is opened: its plastic tamper-evident locks unbroken (on many containers they are the external indicator too, and change color in the sterilizerSTAIR-uh-ly-zerA machine that kills all germs, including spores, on instruments and supplies.Full entry ; others carry an indicator card in the card holder) and its card naming the right set. The opener breaks the locks and lifts the lid straight up, about 12 inches, toward themselves and away, then turns it over and checks its filters against the light: in place, dry, no holes or tears. The scrub, gowned, reads the internal indicators in the basket without touching anything, then lifts the basket straight up without touching the container's edges and holds it while the circulator checks the filters in the bottom of the container and looks for moisture. Only then does the basket go on the back table.
Inside the set
Chemical indicators show that a package went through a sterilizer. They cannot prove the contents are sterile, but a wrong color proves a problem. Every tray of a set needs its own internal indicator. A set is treated as non-sterile if:
- its internal indicator has not changed correctly
- any instrument in it is clamped shut, because steam cannot reach the closed surfaces
- it is wet inside, or a filter is torn or out of place
- it holds hair, bone, tissue or other debris
A non-sterile set is passed off for reprocessingree-PROS-es-ingThe steps that make a used reusable medical device safe to use on the next patient.Full entry , and the scrub changes gloves.
Dropped packages
What happens when a sterile package hits the floor depends on its wrapper.
- A package in a woven cloth wrapper is contaminated. The fall pushes air and dust in through the fabric.
- A package in an impervious wrapper, one that fluid cannot pass through, may be opened and used right away if it is whole and the spot where it landed was dry. It never goes back on the shelf.
Facilities set their own policy on dropped items, so learn yours.
To see a whole sterile fieldSTAIR-ul feeldAn area set up with sterile drapes and supplies, kept free of all germs, for a sterile procedure.Full entry laid out for one operation, open the setup below.
7Pouring solutions
Saline, water and medicines reach the field through a few strict steps.
- The circulator shows the label to the scrub, and both read it: what the solution is, its strength and its expiration date.
- The scrub sets the basin or medicine cup at the edge of the back table, or holds it out, so the circulator never reaches over the field.
- The circulator takes off the cap without touching the bottle's lip, and holds only the lip over the basin.
- The circulator pours slowly and steadily, close enough to avoid splashing but never touching the basin or cup. A splash pools on the table cover and has to be sponged up; a splash on a towel soaks through it.
- The bottle is poured once. It is never recapped, never poured from again, and never saved for later or for another patient. Whatever is left is thrown away.
- The scrub labels every cup, basin and syringe on the field as soon as it is filled, even when only one medicine is on the field.
Medicines in vials reach the field through a sterile transfer device, such as a vial spike. A stopper is never pulled out to pour, unless the vial is made to be poured that way.
Why so strict? Once the cap comes off, nobody can prove the lip stays sterile. Drops that ran down the outside of the bottle can run back over the lip on a second pour and carry germs into the basin.
8Sterile people
The second principle of asepsisay-SEP-sisThe state of being free of germs that cause disease, and the practices used to keep things that way.a- withoutsep- decay or infection-sis conditionFull entry is that sterile team members are properly dressed before they step up to the field. Once you are scrubbed, gowned and gloved, parts of you are sterile and parts are not. Knowing which is which is most of surgical asepsisSUR-jih-kul ay-SEP-sisPractices that keep an area or object completely free of microorganisms; also called sterile technique.a- withoutsepsis decay, infectionFull entry .
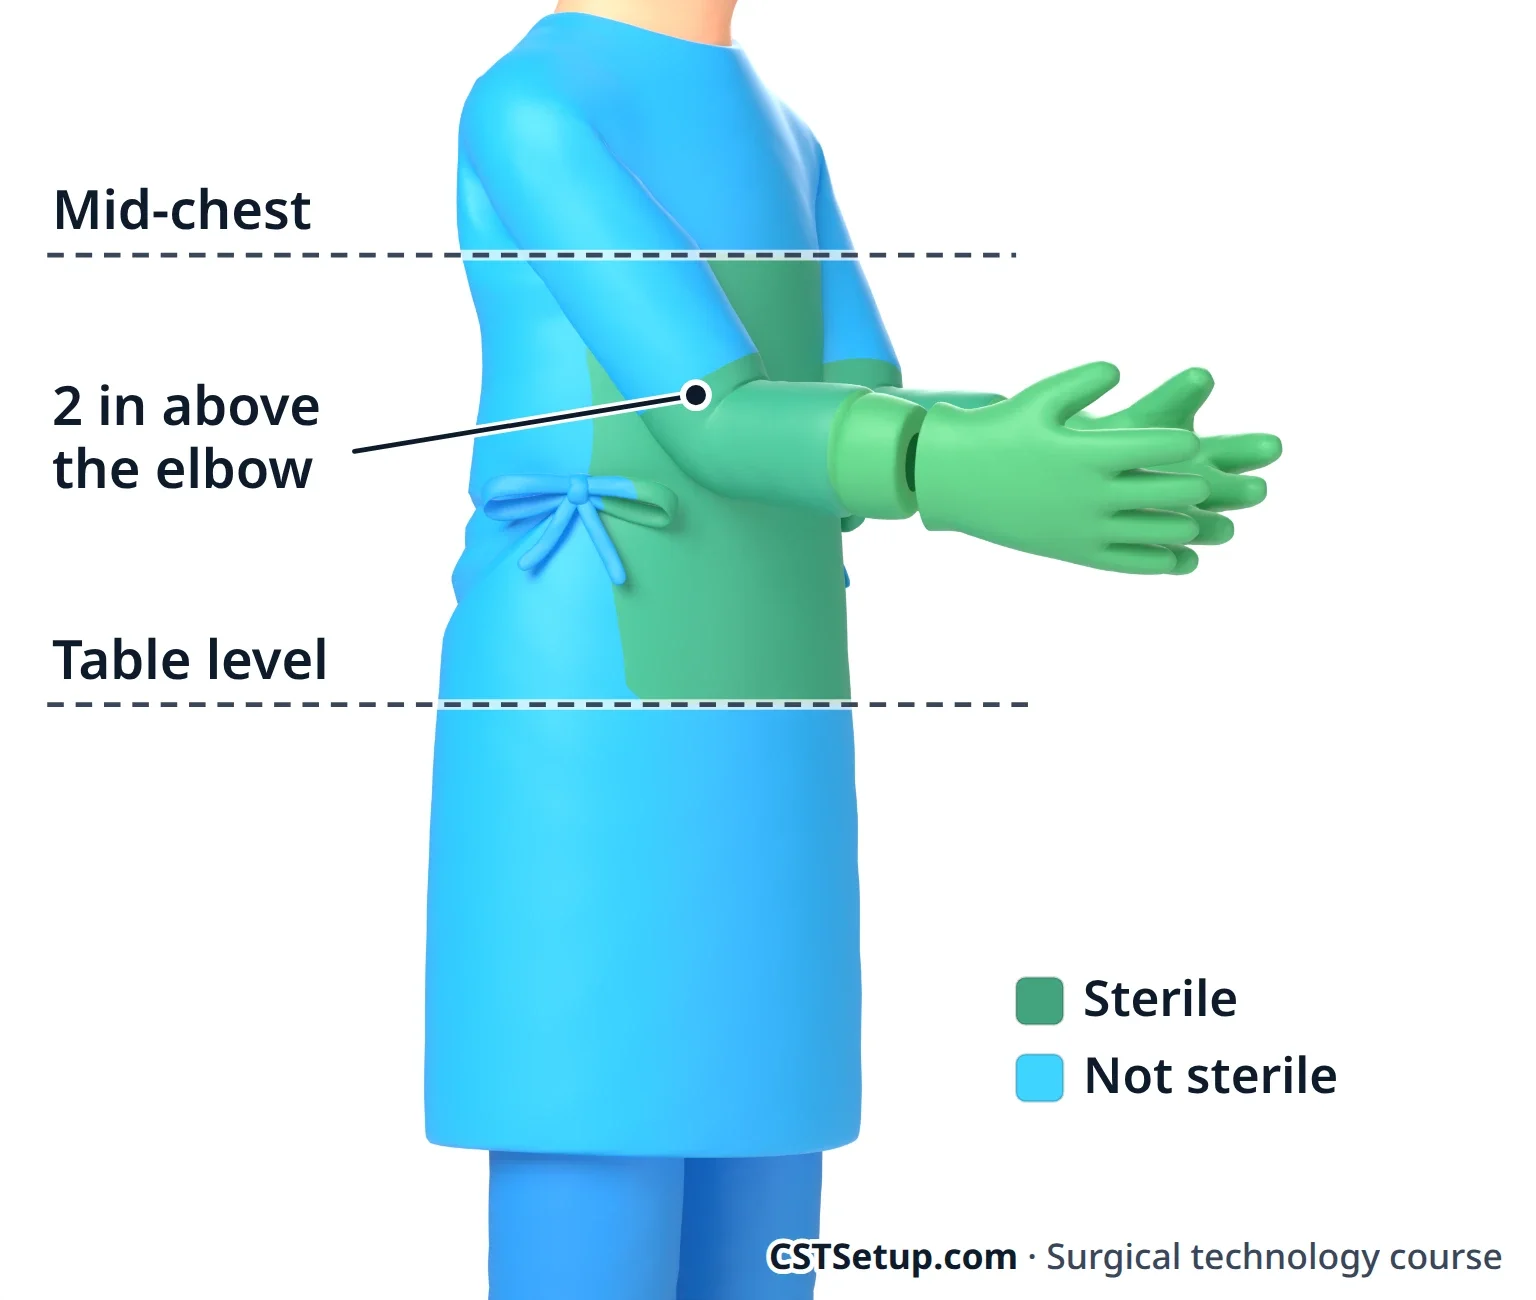
- Sterile: the front of the gown from mid-chest to the level of the sterile fieldSTAIR-ul feeldAn area set up with sterile drapes and supplies, kept free of all germs, for a sterile procedure.Full entry , and the sleeves from the cuff to 2 inches above the elbow, all the way around.
- Not sterile: the back (even once it is tied), the neckline, the shoulders, the underarms, and anything below the table.
- Keep gloved hands in front of you, between your waist and your chest. Never fold your arms with your hands in your underarms, and never let your hands drop to your sides.
The rule underneath all of this is simple: sterile touches sterile, non-sterile touches non-sterile. The scrub never reaches for the light switch. The circulator never reaches onto the field.
Gowning and gloving yourself
- Dry your hands and arms with the sterile towel, holding it away from your scrub suit. Wet skin under a gown invites strike-through.
- Lift the gown by its inside, just below the neckline, step back, and let it unfold. It is folded inside out, so the side you touch is the side that faces you.
- Slide your arms into the sleeves, but stop before your hands pass the cuff seam. The circulator pulls the gown onto your shoulders and ties the back.
- Glove using the closed method, below.
- Turn the gown last. The circulator holds the tab on the wraparound tie and walks behind you while you stand still. You pull the sterile tie free and fasten it at your side. Until then, stay at least 12 inches from anything sterile and keep facing the field.
Closed and open gloving
In closed gloving, your hands stay inside the sleeves until they are inside the gloves, so bare skin never touches the outside of a glove. AST recommends it for anyone gloving themselves to join the sterile team.
Open gloving is for non-sterile people doing a sterile task without a gown, such as placing a urinary catheter or doing a skin prep. The bare hand touches only the inside of the folded glove cuff, and the gloved hand only the outside of the other glove.
Once your hand has passed through the gown's knitted cuff, the cuff counts as contaminated, so it stays covered by the glove all case. That is also why closed gloving partway through a case needs a fresh gown.
AST recommends two pairs of gloves for every operation, with a colored inner pair so a hole in the outer glove shows.
Gowning and gloving others
- Hand the person a towel first, if they did a wet scrub.
- Hold the gown by its outside, gloved hands tucked under the folds at the shoulders, while they slide their arms in. Their hands stay inside the cuffs, and the circulator ties the back.
- Hold each glove open with your fingers under its cuff, palm toward them, thumbs out of the way. They push their hand in while you pull the glove cuff over the gown cuff, then let it go without a snap.
Changing a contaminated glove
The circulator, in non-sterile gloveSTAIR-ul gluvA glove that has been sterilized and packed so it can touch a sterile field or an open body area without bringing in germs.Full entry , pulls the contaminated glove off by its outside without dragging the gown cuff down. A sterile teammate then gloves you the way you glove the surgeon. If nobody sterile can help, change gown and gloves and glove closed. Open gloving is the last resort.
9Moving around the field
The third principle of asepsisay-SEP-sisThe state of being free of germs that cause disease, and the practices used to keep things that way.a- withoutsep- decay or infection-sis conditionFull entry is that movement in and around the sterile fieldSTAIR-ul feeldAn area set up with sterile drapes and supplies, kept free of all germs, for a sterile procedure.Full entry must never put it at risk.
- Non-sterile people never reach across, lean over or touch the sterile field, and they keep at least 12 inches from sterile people, tables and the draped patient.
- Non-sterile people face the sterile field as they pass it, and they never walk between two sterile areas, such as the back table and the OR table.
- Sterile people never reach across or lean over anything non-sterile, and they stay close to the field.
- Sterile tables stand at least 12 inches from walls, doors and anything else that is not sterile.
- Two sterile people pass each other face to face or back to back, never one facing the other's back.
- Keep talking and movement to a minimum. Both stir up air and dropletDROP-litA drop of moisture sprayed from the nose or mouth when a person coughs, sneezes or talks, which can carry germs a short way.Full entry .
- Sit down only if the whole operation is done sitting. Put any standing platform in place before you step up to the field, and stay at one height. Changing height can bring a part of the gown that was below the table up to the field.
- When you must come close to something non-sterile, such as when you drape the patient or gown a teammate, fold the drape or gown into a cuff over your gloves first, so your hands stay protected.
10When something goes wrong
Breaks in surgical asepsisSUR-jih-kul ay-SEP-sisPractices that keep an area or object completely free of microorganisms; also called sterile technique.a- withoutsepsis decay, infectionFull entry are common. What matters is what happens next. Fix a break the moment you see it, unless stopping would harm the patient; then fix it as soon as it is safe.
There are three ways to deal with a break:
- Remove it. A clamp that falls below the table, a glove with a hole, a set with a bad indicator, a bottle someone recapped: take it out of use. Remove anything it touched too, and change the gloves of anyone who handled it. Anything below the table edge is the circulator's to pick up, never the scrub's.
- Isolate and cover it. When something cannot be removed, such as a towel or drape that fluid has soaked through, or a hole in a drape over the patient, cover it with a new impervious drape, or replace the drape if your facility's policy says so. Fluid sitting on top of an impervious drape is not a break: suction or sponge it up.
- Acknowledge and report it. Say what happened to the people it affects: the circulator, who opens the replacement, and the surgeon whenever it reaches what they are using or the patient. A serious break may also need a written report under your facility's policy. The standards are plain: every break is reported.
Common breaks and their fixes
- A glove touches anything non-sterile: change the glove.
- A sleeve brushes something non-sterile: add a sterile sleeve cover or change the gown, as your facility prefers.
- An instrument falls below the table: leave it for the circulator, who keeps it in the room until the final count, and ask for another.
- Fluid soaks through a towel or drape: cover the area with an impervious drape.
- Fluid pools on an impervious drape, as it does all through an arthroscopy: suction it up and keep going.
When sterility is in doubt
Sometimes you do not know. Did the circulator's sleeve touch the corner of the table? Did the cord hang below the table before you picked it up? The answer is the same every time: if you are not sure an item is sterile, treat it as contaminated. asepsisay-SEP-sisThe state of being free of germs that cause disease, and the practices used to keep things that way.a- withoutsep- decay or infection-sis conditionFull entry aims to keep germs to an irreducible minimum, as few as people can possibly manage, and doubtful items have no place in that.
If you are not sure whether something is still sterile, treat it as contaminated and replace it. A replaced instrument costs a minute. An infection costs the patient far more.
Three things go wrong at the back table, each with its own fix.
This lab runs in the browser with JavaScript on.
This browser could not start the 3D room. Everything the lab practices is in the chapter.
11Surgical conscience
Surgical conscience is the habit of admitting a break in surgical asepsisSUR-jih-kul ay-SEP-sisPractices that keep an area or object completely free of microorganisms; also called sterile technique.a- withoutsepsis decay, infectionFull entry and fixing it, even when nobody else saw it happen. It is what makes every rule in this chapter work, because the field is only as sterile as the most honest person at the table.
Saying "I contaminated my glove" in a quiet room takes nerve, especially as a student. Every experienced surgeon and scrub has said it many times. Teams trust the person who speaks up, and they stop trusting the one who hides.
Surgical conscience works in both directions. When someone points out your break, fix it without arguing, even if you are not sure they are right. When you see someone else's break, say so plainly and calmly, whoever it is: "Your glove touched the light. Here is a new one." Talk about the item, not the person, and then work out the fix together. The surgeon decides on serious breaks, but everyone at the table protects the patient.
What to take from this chapter
- Asepsis is the goal; sterile technique is how you reach it. The rules are the same for every patient.
- Sterile means free of all life, spores included, and it has no degrees. A package stays sterile until an event, such as moisture or a tear, spoils it.
- Most germs that infect a wound come from the patient. Outside the patient, people are the biggest source. Barriers, distance and calm movement control them.
- Only the top of a draped table is sterile, and the edges of any wrapper are not.
- Check every item before it is opened, deliver it without reaching over the field, and pour each bottle once. Soaked through means contaminated.
- A gown is sterile in front from mid-chest to table level, and on the sleeves from cuff to 2 inches above the elbow. Glove yourself closed; open gloving is for sterile tasks without a gown.
- Non-sterile people keep 12 inches away; sterile people pass face to face or back to back.
- Every break is removed, covered or reported. When in doubt, replace it.
Check yourself5 quick questions
Free for everyone. Pick an answer for each, then check them all at once.
In the ORWhere you'll use this
Setups to see it in
The chapter's instruments
The chapter's whole question pool in sets of 10, with the answer explained after each one.
Coming soonThe chapter's words and instruments on spaced cards: the ones you miss come back sooner.
Coming soonGiven by your class's teacher. Each class draws its own 25 from the chapter's pool.
Coming soon
Suggest a fix
Something wrong, unclear or out of date in this chapter? Tell us and we will fix it for everyone. Your email is only used to reply.