General surgery
Gallbladders, appendixes, hernias, bowel, breast and thyroid: the core cases of general surgery, the anatomy under your instruments, and how to stay one step ahead of the surgeon.
1What general surgery covers
General surgery treats the abdominal wall and the organs inside the abdomen, the breast, the thyroid and parathyroid glandpair-uh-THY-royd glandOne of four small glands behind the thyroid that control the amount of calcium in the blood.para- besidethyr/o thyroid gland-oid likeFull entry , and the rectum and anus. General surgeons also remove lumps from the skin and the tissue just beneath it, such as lipomas and cysts. More and more surgeons now focus on one area, such as weight-loss, breast or bowel surgery.
General surgery carries the largest case requirement of any specialty. Students in an accredited program complete at least 30 general surgery cases, and 20 of them must be in the first scrub role.
The good news is that general surgery repeats itself. The same steps open and close almost every abdominal case, and the same rules for counts, specimens and contamination apply each time. Cases that share instruments, supplies, positions and steps are taught together as co-related procedures: a small bowel resectionrih-SEK-shunSurgery to remove part of an organ or tissue.re- back, againsect to cut-ion processFull entry , for example, is done much like a colon resection. Any approach other than open, whether laparoscopiclap-uh-roh-SKOP-ikDone through a few small cuts in the abdomen with a thin camera and long instruments, instead of one large opening.lapar/o abdomen-scopic viewingFull entry , robotic or endoscopicen-doh-SKOP-ikDone with an endoscope, a thin tube with a light and camera passed into the body.endo- within-scopic viewingFull entry , counts as minimally invasive surgery (MIS). Learn the pattern once, and each new procedure is mostly a new middle. Each case links to its full setup card, with the instrument list and every step; here you get the reasons, and the moments when the scrub matters most.
2Anatomy that matters
The abdominal wall
The abdominal wall reaches from the diaphragmDY-uh-framThe dome-shaped sheet of muscle under the lungs that is the main muscle of breathing; also the flat side of a stethoscope.Full entry down to the pubisPYOO-bisThe front part of each hip bone, low in the pelvis; the two meet in the middle at the pubic symphysis.pub/o pubisFull entry and shields the organs inside, the visceralVIS-er-ulHaving to do with the internal organs, especially those in the chest and belly.viscer/o internal organs-al relating toFull entry . Every abdominal case passes through the same layers, from outside in:
- Skin
- subcutaneoussub-kyoo-TAY-nee-usUnder the skin; in the fatty layer between the skin and the muscle.sub- undercutane/o skin-ous relating toFull entry fat, anywhere from a quarter inch to more than 8 inches thick. It holds two sheets of superficial fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry : the fatty Camper fascia and, deeper, the Scarpa fascia.
- Fascia, the tough sheets over the muscles. Near the midlineMID-lineAn imaginary line down the center of the body; also, a type of IV catheter placed in a vein of the upper arm.Full entry it forms the rectusREK-tusLatin for straight; the name of several straight muscles, such as the rectus abdominis of the abdomen and the rectus femoris of the thigh.Full entry sheathSHEETHA covering that wraps around a structure; in procedures, a short hollow tube left in a blood vessel to pass catheters through.Full entry , which encloses each rectus muscle.
- Muscle: the two rectus abdominis muscles in front, and the external oblique, internal oblique and transversus abdominis at the sides
- Transversalis fascia and preperitoneal fat
- peritoneumpair-ih-toh-NEE-umThe thin membrane that lines the belly cavity and covers most of the organs inside it.peri- aroundton stretched-eum a structureFull entry , the serousSEER-usThin, watery and clear to pale yellow, like the fluid part of blood.Full entry membrane lining the cavity
The two rectus muscles run from the pubis up to the fifth, sixth and seventh rib cartilageKAR-tih-lijFirm, smooth, rubbery tissue that cushions joints and gives shape to parts such as the ear, nose and windpipe.chondr/o cartilageFull entry . Above the arcuate line, about a third of the way down from the umbilicus to the pubis, the rectus sheath covers each muscle front and back. Below that line there is no posterior sheath, only the transversalis fascia behind the muscle.
In the midline, the sheaths from both sides fuse into the linea alba, a band of connective tissuekuh-NEK-tiv TISH-ooBody tissue that supports, binds together and protects other tissues and organs.Full entry with almost no blood vessels. It is the strongest layer of the midline, and a closure holds only as well as this fascia holds. A midline incision goes through it without cutting muscle, which makes it fast and nearly bloodless.
The peritoneum lines the wall and folds over the organs. It makes a slippery fluid that lets the organs slide over each other. The mesentery is a fan-shaped double fold of it that anchors the small intestine (and parts of the colon) to the back wall and carries their blood vessels, nerves and lymphLIMFThe clear fluid that flows through the lymphatic vessels and carries white blood cells.Full entry vessels. The greater omentum is an apron of fatty peritoneum that hangs from the stomach over the intestines. The kidneys, the pancreasPAN-kree-usA long, flat gland behind the stomach that makes digestive enzymes and the hormones insulin and glucagon.pan- allcreas fleshFull entry , most of the duodenumdoo-uh-DEE-numThe first, short part of the small intestine, just after the stomach.Full entry , parts of the colon and the rectum sit wholly or partly behind the peritoneum, in the retroperitoneum. adhesionad-HEE-zhunA band of scar tissue that joins two surfaces inside the body that are normally separate.ad- towardhes stick-ion conditionFull entry are strands of scar tissue that form between these surfaces after inflammation or infection; freeing them is called lysis of adhesions.
The abdomen is mapped two ways. Four quadrants: right upper, left upper, right lower and left lower. Nine regions, made by two vertical and two horizontal lines: the right and left hypochondriac, epigastric, right and left flank, umbilical, right and left groin (inguinalING-gwih-nulRelating to the groin, the fold where the thigh meets the lower abdomen.Full entry or iliacIL-ee-akHaving to do with the ilium, the large, wing-shaped upper part of the hip bone.Full entry ) and pubic regions. The liver and gallbladder sit in the right upper quadrant, the stomach, pancreas and spleenspleenAn organ in the upper left abdomen that filters the blood and helps fight infection.splen/o spleenFull entry mostly in the left upper, and the appendixuh-PEN-diksA small, finger-shaped pouch attached to the first part of the large intestine, in the lower right abdomen.Full entry in the right lower.
The GI tract
The gastrointestinal (GI) tract is one long tube: esophagusih-SOF-uh-gusThe muscular tube that carries food and liquid from the throat to the stomach.esophag/o esophagusFull entry , stomach, small intestine (duodenum, jejunumjeh-JOO-numThe second of the three sections of the small intestine; it follows the duodenum and leads into the ileum.jejun/o jejunum (from the Latin for empty)Full entry and ileumIL-ee-umThe last and longest part of the small intestine, which joins the large intestine.Full entry ), then the large intestine. References give its length as about 6 to 7.6 meters; after death, once its muscle tone is lost, it measures longer. The ileum ends at the cecum, a blind pouch where the appendix hangs as a narrow blind-ended tube. The colon then runs ascending, transversetrans-VERSLying across something, at a right angle to its length.Full entry , descending and sigmoidSIG-moydShaped like the letter S; most often short for the sigmoid colon, the S-shaped last part of the colon before the rectum.Full entry to the rectum and anal canal.
Its wall has four layers: the mucosamyoo-KOH-suhThe moist lining of body passages that open to the outside, such as the mouth, nose, gut and bladder.Full entry (the lining), the submucosa (dense connective tissue that binds the lining to the muscle), the muscle layer, and the serosa (the outer covering). The space inside is the lumenLOO-menThe open space inside a tube, such as a blood vessel, the intestine or a catheter.Full entry . Bacteria live throughout the bowel, most of all in the colon, which is why opening the bowel changes how you handle instruments.
Blood reaches the bowel through the mesentery. The celiac trunk branches to the stomach, liver and spleen; the cystic artery to the gallbladder comes off this tree. The superior mesenteric artery feeds the small intestine, the pancreas and most of the large intestine, including the right colon and the transverse colon. The inferior mesenteric artery feeds the rest: the descending and sigmoid colon and the rectum. When a piece of bowel comes out, its mesentery is divided along with it. Lymph from the bowel drains to nodes beside the mesentery, so in cancer operations that part of the mesentery and its nodes come out with the bowel.
The rectum, the last 10 to 12.5 cm of the bowel, ends at the anal canal. There two sphincterSFINGK-terA ring of muscle that tightens to close an opening or passage in the body and relaxes to open it.Full entry hold stool in: the internal sphincter, smooth musclesmooth MUS-ulMuscle that works without conscious control and lines hollow organs such as the stomach, intestines, bladder, airways and blood vessels.Full entry that works without conscious control, and the external sphincter, skeletal muscleSKEL-uh-tul MUS-ulMuscle attached to bones that a person moves by choice, such as the muscles of the arms and legs.Full entry the patient controls. In the anal canal, the pectinate (dentate) line marks where the gut lining meets skin. Above the line the lining has visceral nerves, which sense little pain; below it, skin nerves feel pain sharply.
Liver, gallbladder and biliary tree
The liver fills most of the right upper quadrant and part of the left. It has right and left lobes and eight segments, each with its own blood supply. Blood comes in through the hepatichih-PAT-ikRelating to the liver.hepat/o liver-ic relating toFull entry artery and through the portal vein, which carries blood from the stomach, intestines, spleen and pancreas, and leaves through the hepatic veins into the inferior vena cavain-FEER-ee-er VEE-nuh KAY-vuhThe large vein that carries blood from the lower body back to the right atrium of the heart.inferior lowervena veincava hollowFull entry . The liver is very vascular, and a tear can bleed hard.
The liver makes bilebileA yellow-green fluid made by the liver and stored in the gallbladder that helps digest fats.chol/e bileFull entry , which leaves through the right and left hepatic ducts. These join to form the common hepatic duct. The gallbladder, tucked under the right lobe, stores and concentrates bile and connects through the cystic duct. Where the cystic duct joins the common hepatic duct, the tube becomes the common bile ductKOM-un BILE DUKTThe tube that carries bile from the liver and gallbladder into the small intestine.Full entry . It meets the pancreatic duct and empties into the duodenum at the ampulla of Vater, where the sphincter of Oddi controls the flow.
The gallbladder has a fundusFUN-dusThe rounded top or base of a hollow organ, most often the top of the uterus.Full entry (the rounded end), a body, an infundibulum and a neck that narrows into the cystic duct. Its cystic artery most often branches from the right hepatic artery. The Calot triangle is bordered by the cystic duct, the common hepatic duct and the cystic artery. Surgeons clear the closely related hepatocystic triangle, which has the underside of the liver as its upper border and holds the cystic artery and duct. This small area matters most in a gallbladder operation, because the common bile duct lies right beside it and can be mistaken for the cystic duct.
Gallstones (cholelithiasiskoh-lee-lih-THY-uh-sisStones in the gallbladder.chol/e bilelith/o stone-iasis conditionFull entry ) form mainly from cholesterol, from bile pigment, or from a mix of both; cholesterol stones are the most common. A stone stuck in the cystic duct inflames the gallbladder (cholecystitiskoh-luh-sis-TY-tisInflammation of the gallbladder.chol/e bilecyst/o sac, bladder-itis inflammationFull entry ). A stone in the common bile duct blocks bile and causes jaundiceJAWN-disYellow color of the skin, the whites of the eyes and other tissues from too much bilirubin in the blood.Full entry , and a stone that reaches the ampulla can cause pancreatitispan-kree-uh-TY-tisInflammation of the pancreas, which may come on suddenly (acute) or last for years (chronic).pancreat/o pancreas-itis inflammationFull entry .
Pancreas and spleen
The pancreas lies behind the stomach, its head in the C-shaped curve of the duodenum and its tail reaching toward the spleen. Its duct carries digestive enzymeEN-zimeA protein that speeds up a chemical reaction in the body without being used up.Full entry to the duodenum. Its islets release hormones straight into the blood: beta cellBAY-tuh SELA cell in the pancreas that makes and releases insulin.Full entry make insulinIN-suh-linA hormone made by the pancreas that lets the body's cells take in glucose, also made as a medicine.Full entry and alpha cells make glucagonGLOO-kuh-gonA hormone made by the pancreas that raises blood sugar; also given as a drug for severe low blood sugar.Full entry .
The spleen sits in the left upper quadrant under the diaphragm, behind the stomach and sheltered by the 10th to 12th ribs. It filters old red blood cells and germs from the blood and stores blood. It is soft and very vascular, so it is easily injured in vehicle crashes and sports accidents. Most people live well without a spleen, but they fight certain bacteria less well, so splenectomy patients are vaccinated, ideally before surgery.
Breast
The breast lies on the pectoralis major muscle, from the second to the sixth rib, with a tail of tissue (the tail of Spence) reaching toward the axilla. It is made of about 15 to 20 lobes of glands, which drain through ducts to the nipple.
Most of the breast's lymph drains to the axillary lymph nodelimf nohdA small, bean-shaped organ of the immune system that filters lymph fluid and holds white blood cells.Full entry , so they are where surgeons look for spread of cancer. The axillary nodes are grouped by the pectoralis minor muscle: level I lateral to it, level II behind it, and level III medial to it.
Two axillary nerves must be spared. The long thoracicthuh-RAS-ikRelating to the chest, or to the middle part of the spine.thorac/o chest-ic relating toFull entry nerve supplies the serratus anterior; injury leaves a "winged" shoulder blade. The thoracodorsal nerve supplies the latissimus dorsi; injury weakens the arm when it pulls back, pulls in toward the body or turns.
Thyroid and parathyroids
The thyroid is a very vascular gland in the front of the neck. Its two lobes sit beside the tracheaTRAY-kee-uhThe windpipe: the tube that carries air from the throat to the lungs.Full entry , joined by the isthmus across the second to fourth tracheal rings. It makes two thyroid hormoneTHY-royd HOR-mohnA hormone made by the thyroid gland that controls how fast the body uses energy.Full entry , T4 (thyroxine) and T3tee-THREETriiodothyronine: the more active of the two main thyroid hormones, or the blood test that measures it.Full entry (triiodothyronine), and calcitoninkal-sih-TOH-ninA hormone made by the thyroid gland that lowers blood calcium; a lab-made form is used as a drug.Full entry . The strap muscles cover it, and the platysma lies just under the skin.
Two structures make thyroid surgery delicate, and harm to them causes its most typical complications:
- The recurrent larynxLAIR-inksThe voice box: the part of the airway in the neck, above the windpipe, that holds the vocal cords.laryng/o larynxFull entry nerve, a branch of the vagus nerveVAY-gus nervThe 10th cranial nerve, which runs from the brain stem to the chest and belly and slows the heart and helps digestion.Full entry , runs up in the groove between the trachea and esophagus, behind the thyroid, and moves the vocal cords. Injury on one side causes hoarseness; injury on both sides can block the airway.
- The parathyroid glandpair-uh-THY-royd glandOne of four small glands behind the thyroid that control the amount of calcium in the blood.para- besidethyr/o thyroid gland-oid likeFull entry , usually four, are tiny glands about 3 mm across on the back of the thyroid lobes, two near the upper poles and two near the lower. They are yellowish to brown. They make parathyroid hormonepar-uh-THY-royd HOR-mohnA hormone from the parathyroid glands in the neck that raises the calcium level in the blood.para- besidethyr/o thyroid-oid resemblingFull entry , which controls blood calcium. If they are removed or lose their blood supply, calcium drops, causing numbness and tingling, then twitching and spasmSPAZ-umA sudden, involuntary tightening of a muscle or of the muscle in a hollow organ or tube.Full entry .
3Incisions, position, prep and drape
Incisions
Abdominal incisions are named for where they lie. The right one gives enough room for the job, can be made longer if needed, and closes securely.
- midlineMID-lineAn imaginary line down the center of the body; also, a type of IV catheter placed in a vein of the upper arm.Full entry (upper or lower): through the linea alba, curving around the umbilicus. Fast, with excellent exposure to any part of the abdomen and easy to extend; the standard incision for exploratory laparotomylap-uh-ROT-uh-meeSurgery that opens the abdomen through a large cut to reach the organs inside.lapar/o abdomen-tomy cutting intoFull entry .
- Paramedian: vertical, about 2 to 5 cm to one side of the midline, through the rectusREK-tusLatin for straight; the name of several straight muscles, such as the rectus abdominis of the abdomen and the rectus femoris of the thigh.Full entry sheathSHEETHA covering that wraps around a structure; in procedures, a short hollow tube left in a blood vessel to pass catheters through.Full entry with the rectus muscle moved aside.
- subcostalsub-KOS-tulBelow the ribs.sub- belowcost/o rib-al relating toFull entry (Kocher): along the lower ribs; the right side for the gallbladder, bilebileA yellow-green fluid made by the liver and stored in the gallbladder that helps digest fats.chol/e bileFull entry tree and pancreasPAN-kree-usA long, flat gland behind the stomach that makes digestive enzymes and the hormones insulin and glucagon.pan- allcreas fleshFull entry , the left for the spleenspleenAn organ in the upper left abdomen that filters the blood and helps fight infection.splen/o spleenFull entry . It hurts more after surgery. Right and left subcostal incisions joined in the midline make a chevron.
- McBurney: a short oblique cut in the right lower abdomen, about a third of the way from the anterior superior iliacIL-ee-akHaving to do with the ilium, the large, wing-shaped upper part of the hip bone.Full entry spine to the umbilicus, that splits the muscles along their fibers. It gives limited exposure and is used for open appendectomyap-en-DEK-tuh-meeSurgery to remove the appendix.append appendix-ectomy surgical removalFull entry . Its transversetrans-VERSLying across something, at a right angle to its length.Full entry version is the Rocky-Davis.
- inguinalING-gwih-nulRelating to the groin, the fold where the thigh meets the lower abdomen.Full entry : oblique, just above and parallel to the inguinal ligament, for groin herniaHER-nee-uhA bulge of an organ or tissue through a weak spot in the muscle or tissue wall that normally holds it in.Full entry .
- Pfannenstiel: low transverse, about 3 to 5 cm above the pubisPYOO-bisThe front part of each hip bone, low in the pelvis; the two meet in the middle at the pubic symphysis.pub/o pubisFull entry in a skin fold; strong, with good exposure of the pelvis.
- Thoracoabdominal: from the abdomen across the costal margin into the chest, with the patient tilted onto one side, for the esophagusih-SOF-uh-gusThe muscular tube that carries food and liquid from the throat to the stomach.esophag/o esophagusFull entry , upper stomach and other upper abdominal organs.
- Port sites: small incisions, usually 1 to 2 cm, for laparoscopiclap-uh-roh-SKOP-ikDone through a few small cuts in the abdomen with a thin camera and long instruments, instead of one large opening.lapar/o abdomen-scopic viewingFull entry cannulaKAN-yoo-luhA thin tube placed into the body or a body opening to deliver or remove fluid or air.Full entry , most often one at the umbilicus for the scope.
Five cases on one abdomen. Tap where the surgeon cuts, and see the incision.
This lab runs in the browser with JavaScript on.
This browser could not start the 3D room. Everything the lab practices is in the chapter.
Position
Most cases are supine. Each arm rests on a well-padded armboard at less than 90 degrees, or, when the case requires it, is tucked at the side. The table then tilts so gravity moves the organs away from the target: head up (reverse Trendelenburg positionree-VERS tren-DEL-un-burg puh-ZISH-unA position lying on the back on a bed or table that is tilted so the head is higher than the feet, with the body kept straight.Full entry ) for the gallbladder, stomach and thyroid, often with the target side tilted up; head down (Trendelenburg positiontren-DEL-en-burg puh-ZISH-unA position in which the client lies on the back with the bed tilted so the head is lower than the feet.Full entry ) for the appendixuh-PEN-diksA small, finger-shaped pouch attached to the first part of the large intestine, in the lower right abdomen.Full entry , groin hernias and pelvis. A laparoscopic splenectomy is often done with the patient turned partly onto the right side. Cases that need the perineumpair-ih-NEE-umThe area of skin and muscle between the genitals and the anus.perine/o perineumFull entry , such as a low rectalREK-tulRelating to the rectum, the last part of the large intestine; also, given or measured through the rectum.rect/o rectum, straight-al relating toFull entry resectionrih-SEK-shunSurgery to remove part of an organ or tissue.re- back, againsect to cut-ion processFull entry , use lithotomylih-THOT-uh-meeA position lying on the back with the hips and knees bent and the legs raised and spread apart, often in stirrups.lith/o stone-tomy cutting intoFull entry . Anorectal cases use prone jackknife, lithotomy or a lateral position. The safety strap goes 2 inches above the knees, and when the head is up a padded footboard stops the patient sliding down the table. Before a steep tilt, an anti-skid pad or vacuum positioner keeps the patient from sliding.
Four cases. Tilt the table so the bowel falls away from the target, then look inside.
This lab runs in the browser with JavaScript on.
This browser could not start the 3D room. Everything the lab practices is in the chapter.
Prep and drape
- Abdomen: from the nipple line to mid-thigh and down both sides to the table. Clean the umbilicus first, with cotton-tipped applicators.
- Groin: the lower abdomen, the groin and the upper thighs, with the genitals when the surgeon needs them. The groin and genitals, being heavily contaminated, are prepped last.
- Breast: for a biopsy, the affected breast and the skin around it, with the axilla for a lesionLEE-zhunAn area of tissue that has been damaged or has changed from normal, such as a sore, wound, lump or spot.Full entry in the upper outer breast. For a mastectomyma-STEK-tuh-meeSurgery to remove all or part of a breast.mast/o breast-ectomy surgical removalFull entry , from just above the collarbone down to the umbilicus, and across from the opposite nipple to the table on the operative side, with the axilla and sometimes the upper arm; the arm is draped free in a stockinette. Prep gently over a suspected cancer or a localization wire.
- Neck: from the chin to the nipples, including the sides of the neck and the shoulders.
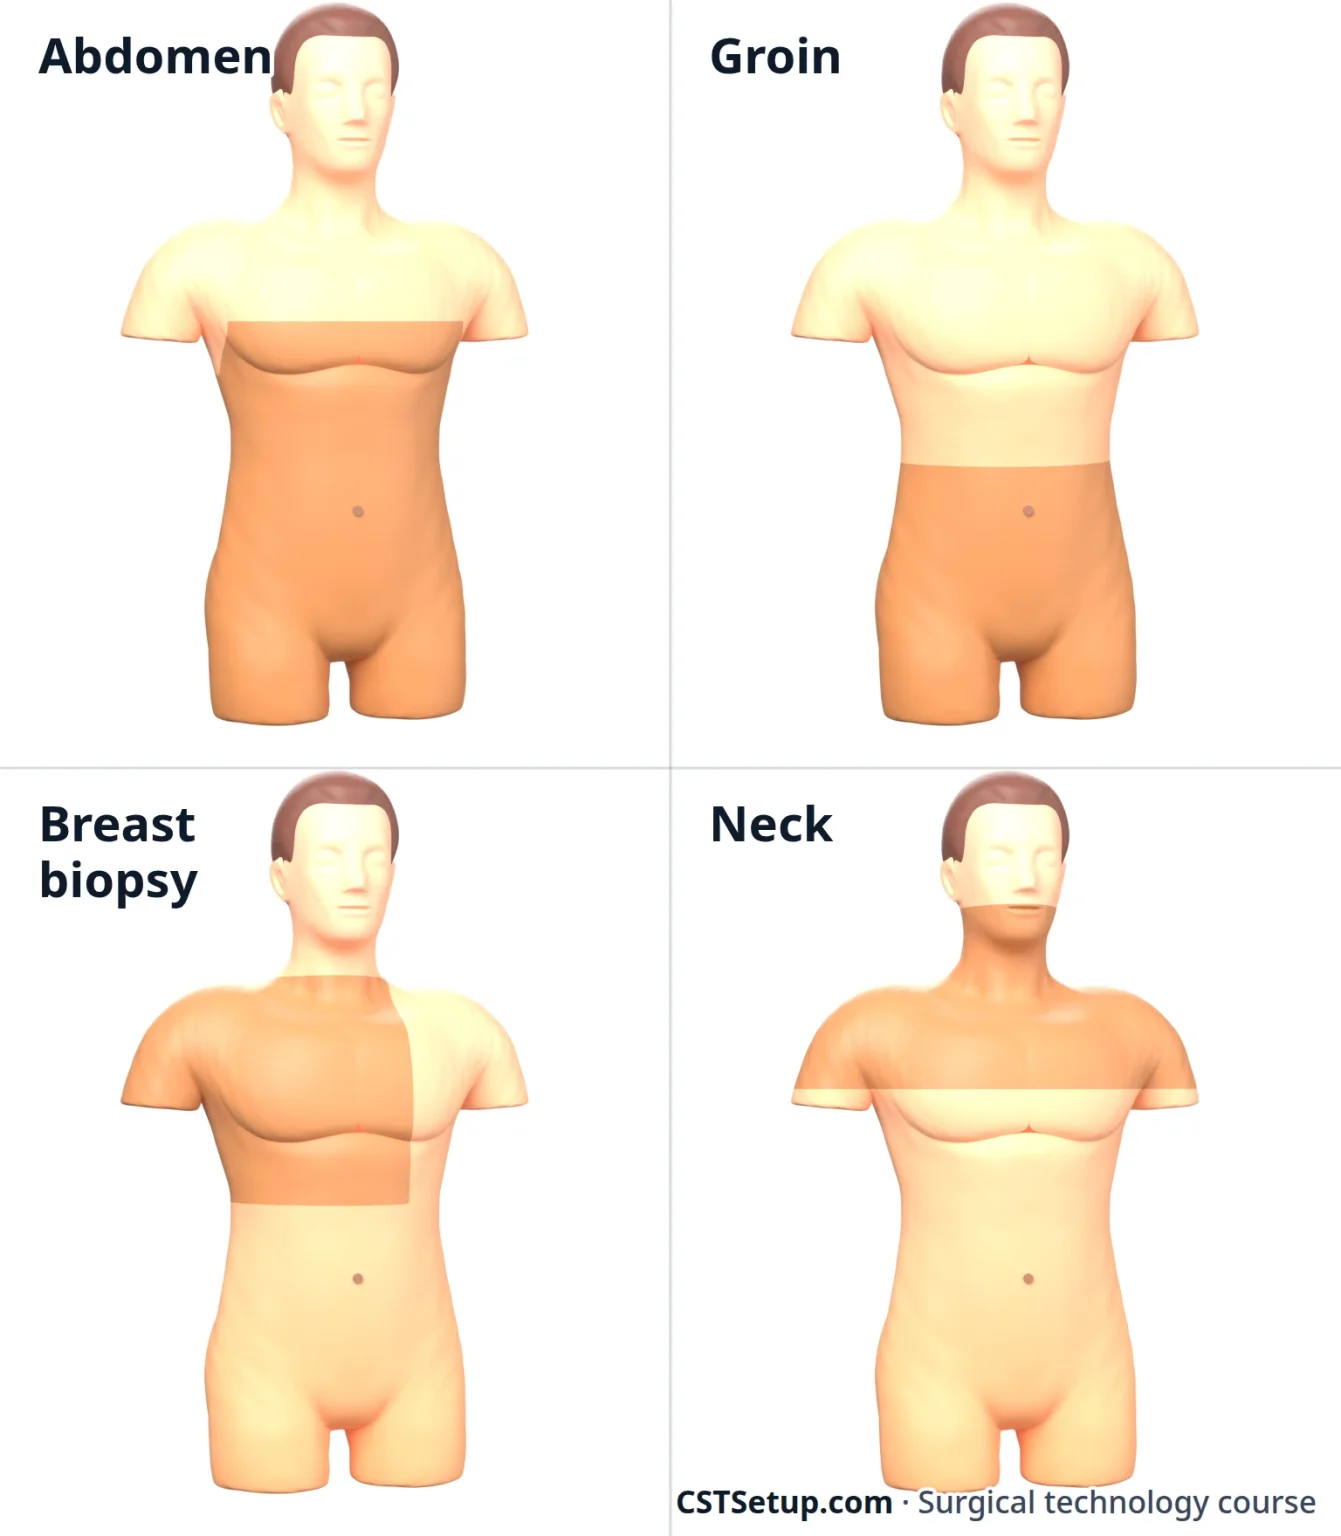
Draping usually begins with four towels to square off the site, then a fenestrated sheet: a laparotomy sheet for the abdomen and groin, a sheet with the arm draped free for a mastectomy, and a thyroid sheet, with its small transverse opening, for the neck.
4Trays and instruments
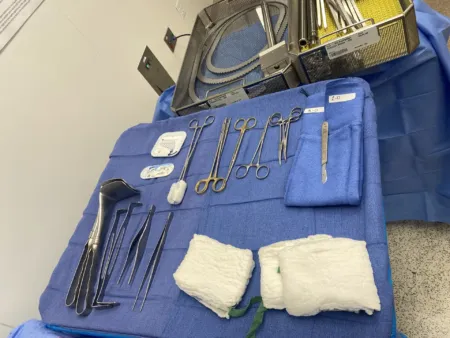
- Minor tray: short instruments for small, shallow cases such as breast biopsies, sentinel node biopsies and anorectal cases, with small retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry such as the Senn, rakes and Weitlaner, fine hemostatHEE-moe-statA clamp with finger rings and a locking ratchet used in surgery to grasp and close off bleeding vessels.hem/o blood-stat stopping, standing stillFull entry , Allis clamps, scissors, forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry and needle holders. Open herniaHER-nee-uhA bulge of an organ or tissue through a weak spot in the muscle or tissue wall that normally holds it in.Full entry repairs often use a laparotomylap-uh-ROT-uh-meeSurgery that opens the abdomen through a large cut to reach the organs inside.lapar/o abdomen-tomy cutting intoFull entry set instead.
- Major laparotomy tray: the base for every open abdomen. It holds Metzenbaum and Mayo scissors, tissue forceps, hemostats, Pean, Kocher, Allis, Babcock and right-angle clamps, needle holders and towel clips, with Deaver, Richardson, Harrington, Army-Navy and malleable (ribbon) retractors. A self-retaining retractor such as the Balfour or Bookwalter is added.
- Add-ons: long instruments for deep or large patients; a GI tray with intestinal clamps; a bilebileA yellow-green fluid made by the liver and stored in the gallbladder that helps digest fats.chol/e bileFull entry tray with gall duct dilatorDY-lay-terAn instrument used to stretch or widen an opening, canal or passage in the body.Full entry and stone forceps; a thyroid tray; a rectalREK-tulRelating to the rectum, the last part of the large intestine; also, given or measured through the rectum.rect/o rectum, straight-al relating toFull entry tray with anal retractors and speculumSPEK-yoo-lumAn instrument used to open and hold open a body opening, such as the vagina, so the inside can be seen.Full entry .
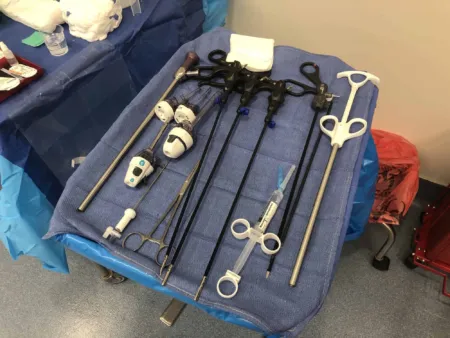
- laparoscopylap-uh-ROS-kuh-peeSurgery or an exam done through small cuts in the belly, using a thin, lighted tube with a camera.lapar/o abdomen-scopy looking with an instrumentFull entry tray: Veress needle, trocarTROH-karA sharp or bladed instrument inside a tube (cannula), used to pierce a body wall and leave the tube in place as a port.Full entry and cannulaKAN-yoo-luhA thin tube placed into the body or a body opening to deliver or remove fluid or air.Full entry , scopes, camera and light cord, graspers, a Maryland dissector, scissors, a hook electrode, a suction-irrigator and clip appliers, with a needle holder when suturing is planned.
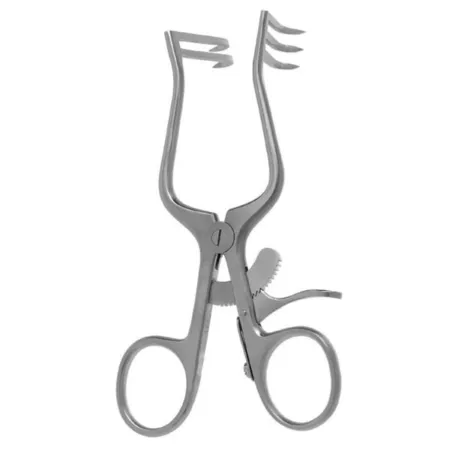

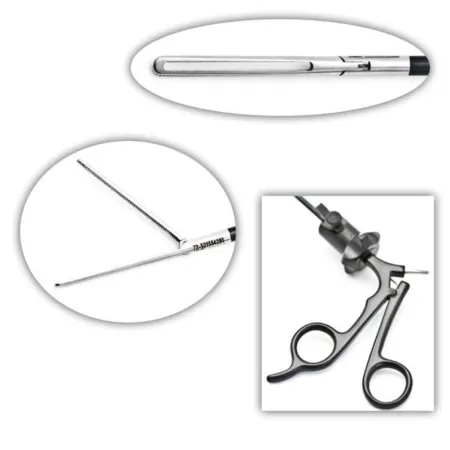

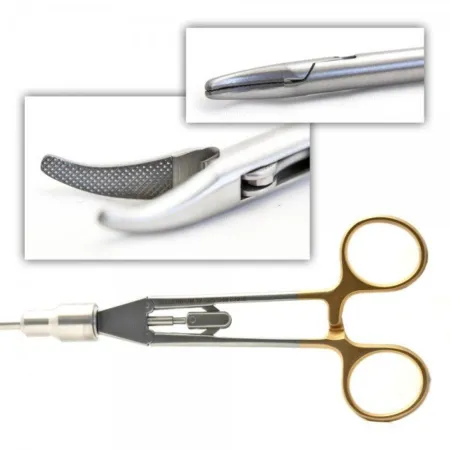
What the common instruments do:
- Kocher: large interlocking teeth at the tip grip tough, slippery tissue such as fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry and muscle.
- Allis: rows of fine teeth hold dense tissue that is being removed, such as breast or thyroid tissue, or bowel during a resectionrih-SEK-shunSurgery to remove part of an organ or tissue.re- back, againsect to cut-ion processFull entry .
- Babcock: rounded, smooth, open jaws lift and encircle delicate tissue such as bowel and the appendixuh-PEN-diksA small, finger-shaped pouch attached to the first part of the large intestine, in the lower right abdomen.Full entry without crushing it.
- Right angle: reaches behind a vessel or duct so a tie or vessel loop can pass around it.
- Kelly and Pean: the clamps used in pairs to clamp tissue that will be cut and then tied or sealed.
- Doyen: an intestinal clamp with smooth jaws for clamping bowel during a resection; noncrushing intestinal clamps leave a small gap so they do not crush the wall. Some have soft rubber shods slipped over the jaws for a snug seal on the tissue.
- Balfour and Bookwalter: self-retaining abdominal retractors. The Bookwalter mounts on the table, with blades that lock onto its frame.
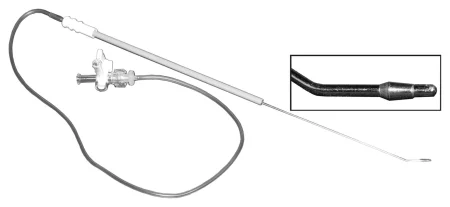
- Poole suction: an inner tube inside an outer sheathSHEETHA covering that wraps around a structure; in procedures, a short hollow tube left in a blood vessel to pass catheters through.Full entry with many holes, so a cavity full of fluid empties without strong suction on delicate tissue. With the sheath off, the inner tube works as a plain tip.



Before the peritoneumpair-ih-toh-NEE-umThe thin membrane that lines the belly cavity and covers most of the organs inside it.peri- aroundton stretched-eum a structureFull entry is opened, any 4x4 sponge not mounted on an instrument comes off the field; from then on, moist lap sponges are used, because a small sponge is easily lost in a deep wound. Keep peanuts and other small dissecting sponges mounted on a clamp, and keep warm saline ready for the laps and for irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry .
5Energy and staplers
Energy devices
General surgery leans on energy devices to cut and seal; chapter 20 teaches how they work and how to use them safely.
- Monopolar electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry : cuts and coagulationkoh-ag-yuh-LAY-shunThe process by which blood changes from a liquid into a gel, forming a clot.coagul clot-ation processFull entry , with the current passing through the patient to a return electrode pad that carries it back to the generator. The laparoscopiclap-uh-roh-SKOP-ikDone through a few small cuts in the abdomen with a thin camera and long instruments, instead of one large opening.lapar/o abdomen-scopic viewingFull entry hook is monopolar. Keep the pencil in its holster when not in use.
- bipolarby-POH-lerHaving two poles or two opposite ends; most often used as a short form of bipolar disorder.bi- twopolar having polesFull entry : current flows only between the two tips, so it focuses on the tissue between them.
- Ultrasonic shears (such as Harmonic): a blade vibrates about 55,000 times a second, cutting and coagulating with frictionFRIK-shunThe rubbing of one surface against another, such as skin against bed sheets.Full entry heat and no current through the patient, so no return pad is needed. The blade stays hot longer than an ESU tip, so hold it away from tissue while it cools and rest it on a moist towel between uses.
- Vessel sealers (such as LigaSure): squeeze tissue and pass controlled bipolar current to seal vessels up to about 7 mm, then cut the seal. With ultrasonic shears and staplers, they have replaced many clamp, cut and tie steps.

All of these make surgical smoke, so a smoke evacuator is used. Check every laparoscopic energy instrument for breaks in its insulation before you pass it.
Staplers
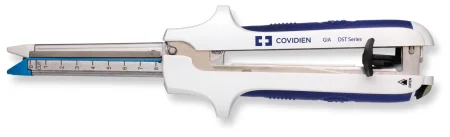
- Linear cutter (GIA): lays two double-staggered rows of staples and cuts between them. It divides bowel with both ends sealed and makes side-to-side joins.
- Linear (TA): lays rows of staples with no cut, to close an end or an opening; the surgeon trims the extra tissue.
- Circular (EEA): joins two hollow structures end to end, often in colorectal surgery. The anvil goes in one end and the body in the other; firing lays a ring of staples and a circular blade cuts away the extra tissue.
- Laparoscopic staplers: linear cutters made to work through a laparoscopic port, often 12 mm.
Staple cartridges (reloads) are color coded by staple size, to match thin or thick tissue. Follow the maker's instructions and read each package so the right size goes in. After a circular stapler fires, the surgeon checks both "donuts" of tissue: each must be a complete ring. Every part of the stapler, and the anvil, must be accounted for.
6Open and laparoscopic approach
Open surgery (laparotomylap-uh-ROT-uh-meeSurgery that opens the abdomen through a large cut to reach the organs inside.lapar/o abdomen-tomy cutting intoFull entry ) gives a full view and lets the surgeon explore by hand, at the cost of a large incision, more tissue injury and a longer recovery. Minimally invasive surgery works through small ports while the team watches a monitor. Most gallbladders and appendixes, most inguinalING-gwih-nulRelating to the groin, the fold where the thigh meets the lower abdomen.Full entry herniaHER-nee-uhA bulge of an organ or tissue through a weak spot in the muscle or tissue wall that normally holds it in.Full entry and much colon surgery are now done this way; at least 70 percent of general surgery procedures use minimally invasive methods. Open surgery stays the choice for some emergencies, such as a patient bleeding after trauma, and for patients whose condition rules out laparoscopylap-uh-ROS-kuh-peeSurgery or an exam done through small cuts in the belly, using a thin, lighted tube with a camera.lapar/o abdomen-scopy looking with an instrumentFull entry .
Getting in
The abdomen is inflated with carbon dioxideKAR-bun dy-OK-sideA gas made by the body's cells as waste, carried in the blood to the lungs and breathed out.Full entry (insufflationin-suh-FLAY-shunBlowing a gas into a body cavity, such as carbon dioxide into the abdomen during laparoscopic surgery.Full entry ), making a pneumoperitoneum. The gas lifts the wall off the organs, which gives room to see and to place the trocarTROH-karA sharp or bladed instrument inside a tube (cannula), used to pierce a body wall and leave the tube in place as a port.Full entry . Carbon dioxide is used because it is nonflammable, nontoxic and quickly absorptionub-ZORP-shunThe taking in of a substance, such as a drug or a nutrient, into the bloodstream.Full entry . In adults the pressure is usually held at 12 to 15 mm Hg, with the insufflator set to stop at 15.
Entry is made one of three ways:
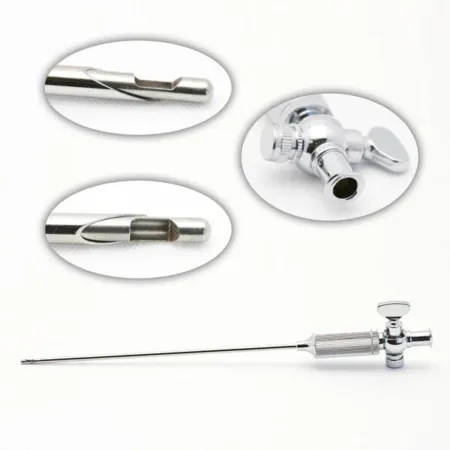
- Veress needle: a hollow needle with a spring-loaded blunt stylet that springs forward once the tip enters the cavity, shielding the organs. Test the spring before you pass it by pressing lightly on the tip. The surgeon lifts the wall by hand or with towel clamps, nicks the skin with a #11 blade and passes the needle. A saline drop test from a 10 mL syringe confirms the position: the saline is drawn in on its own. The gas tubing is then attached, and once the abdomen is inflated the needle is swapped for a trocar and cannulaKAN-yoo-luhA thin tube placed into the body or a body opening to deliver or remove fluid or air.Full entry .
- Open (Hasson): a short incision down to the fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry , which is opened, with a stay sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry placed at each end. The peritoneumpair-ih-toh-NEE-umThe thin membrane that lines the belly cavity and covers most of the organs inside it.peri- aroundton stretched-eum a structureFull entry is opened under direct view, and the blunt Hasson cannula goes in and is tied to the stay sutures. It suits patients with old scars or likely adhesionad-HEE-zhunA band of scar tissue that joins two surfaces inside the body that are normally separate.ad- towardhes stick-ion conditionFull entry near the umbilicus.
- Optical trocar: a bladeless trocar with the scope inside it, so the surgeon watches each layer as it passes, without inflating first.
The trocar is the pointed or blunt rod that makes the path. The cannula is the hollow tube around it, which stays in place as the port, sealed so the gas stays in.

The scrub's laparoscopy jobs
Secure the camera cord, light cord, insufflation tubing and energy cords to the drapes with nonpenetrating clamps, and pass their ends off the field to be connected. White balance the camera if your system does not do it on its own, and keep the scope in warm water or use anti-fog, because a cold lens fogs inside the warm abdomen; dry the lens before you hand it back. You may be asked to run the camera.
Count every sharp and countable item that goes into the abdomen, including needles passed through a port. A missing item must be found, or an X-ray taken, before the wound is closed. The fascia at the larger ports (10 mm, and in some references anything over 8 mm) is closed to prevent a hernia at the port site.
The gas has risks. Too much pressure can force carbon dioxide into the blood and lower breathing and cardiac outputKAR-dee-ak OWT-putThe amount of blood the heart pumps out in one minute.Full entry , and carbon dioxide absorbed from the abdomen can raise the patient's blood level of it. The gas and the irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry fluids add to the risk of hypothermiahy-poh-THER-mee-uhA body temperature that has fallen below the normal range.hypo- belowtherm/o heat-ia conditionFull entry . Leftover gas can irritate nerves and cause shoulder pain after surgery.
Robotic surgery and conversion
In robotic surgery the surgeon sits at a console away from the field, and the robot's arms hold the scope and instruments. The scrub, with the circulator, drapes the arms; places, changes and removes the instruments in the arms; and knows how to move the system away quickly in an emergency such as sudden bleeding.
Any minimally invasive case can turn open because of bleeding, an injury or anatomy the surgeon cannot see clearly. Keep a laparotomy set in the room, move quickly when the surgeon says "open", free the cords and tubing from the drapes and clear them away, and count everything you add.
7Flexible endoscopy
endoscopyen-DOS-kuh-peeA procedure that uses a thin, flexible tube with a light and camera to look inside the body.endo- within-scopy looking with an instrumentFull entry passes a flexible scope through a natural opening, such as the mouth or the anus, to look inside. With imaging (computed tomographykum-PYOO-tid toh-MOG-ruh-feeAn imaging test that uses x-rays and a computer to make cross-section pictures of the inside of the body.tom/o cut, slice-graphy process of recordingFull entry , magnetic resonance imagingmag-NET-ik REZ-uh-nunts IM-uh-jingAn imaging test that uses a strong magnet and radio waves to make detailed pictures of the inside of the body.Full entry , ultrasound and contrastKON-trastA dye or other substance given before an imaging test so body parts show up more clearly.Full entry studies under fluoroscopyfloo-ROS-kuh-peeAn x-ray method that shows moving pictures of the inside of the body in real time.fluor/o glowing (from the fluorescent screen)-scopy looking, viewingFull entry ), blood tests and the physical exam, it is one of the main ways GI disease is confirmed. The doctor sees the lining, takes biopsies to confirm or rule out cancer, and treats small problems through the scope, often before an open or laparoscopiclap-uh-roh-SKOP-ikDone through a few small cuts in the abdomen with a thin camera and long instruments, instead of one large opening.lapar/o abdomen-scopic viewingFull entry operation. A stand-alone endoscopy usually happens in an outpatient endoscopy unit or a room near the OR. Chapter 21 teaches the scopes themselves, and chapter 27 how they are cleaned.
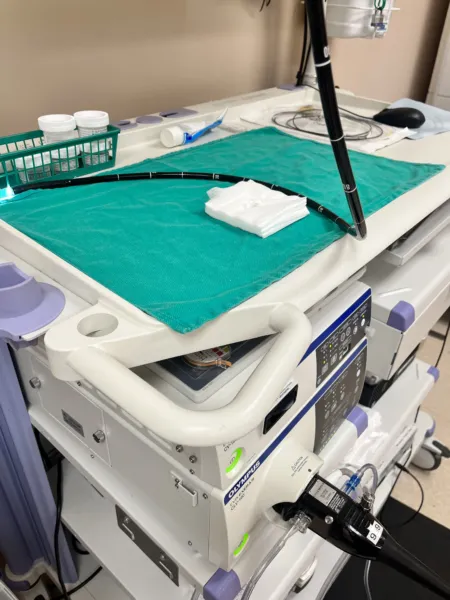
Setup: a flexible video endoscopeEN-duh-skohpA thin tube with a light and a camera that is passed into the body to look inside an organ or cavity.endo- within-scope instrument for viewingFull entry with its light source and video processor, a monitor, suction, irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry , an air source, an electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry and a camera to record the findings, plus saline containers for biopsies and water-soluble lubricant. Knobs and buttons on the handle bend the tip up, down and to each side and work the air, water and suction. Accessories pass down the working channel: biopsy forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry , brushes for cell samples, snares, retrieval nets, injection needles and dilating balloons, with clips, bands and probes to stop bleeding. The scope gets high-level disinfectiondis-in-FEK-shunCleaning a surface or object with chemicals or heat to kill most germs, though not always all bacterial spores.Full entry between patients, but an accessory that pierces the lining must be sterile. Check that the scope, the imaging system and the recording devices work before the procedure.
Medications and monitoring: most patients receive moderate sedationMOD-er-it seh-DAY-shunA drug-induced state of relaxed, lowered awareness in which the client still responds to voice or light touch and breathes on their own.Full entry through an IV, so their airway, vital signs, saturationsach-uh-RAY-shunHow full something is; in nursing, usually the percentage of hemoglobin in the blood that is carrying oxygen.Full entry and level of consciousnessLEV-ul uv KON-shus-nisHow awake, alert and aware of their surroundings a person is.Full entry are watched from start to finish. For an EGDee-jee-DEE (said as letters)Esophagogastroduodenoscopy: a test using a flexible scope through the mouth to look at the esophagus, stomach and start of the small intestine.esophag/o esophagusgastr/o stomachduoden/o duodenum-scopy looking, viewingFull entry the throat is numbed with a topical spray such as benzocaine.
Your role: pass the biopsy instruments and help thread them into the channel. As a biopsy forceps comes out, keep hold of its tip so the tissue is not lost, free the specimen with a hypodermic needle or by swishing the tip in the specimen cup, and get it into its labeled container at once. Keep the irrigation reservoirREZ-er-vwarA place where germs live and multiply, such as a person, animal, water or soil.Full entry full. AST's position is that a CSTsee-es-tee (said as letters)Certified Surgical Technologist, a credential for surgical technologists; in maternity care, contraction stress test.Full entry , directed by the surgeon and within state law and facility policy, may advance, hold and steer rigid and flexible scopes, a colonoscope or duodenoscope included.
EGD, esophagoscopy and ERCP
What and why: an esophagogastroduodenoscopy (EGD) examines the esophagusih-SOF-uh-gusThe muscular tube that carries food and liquid from the throat to the stomach.esophag/o esophagusFull entry , the stomach and the first part of the duodenumdoo-uh-DEE-numThe first, short part of the small intestine, just after the stomach.Full entry . Reasons include upper GI bleeding, difficult or painful swallowing, heartburn, pain or vomiting that will not settle, reflux, a swallowed caustic substance, and follow-up of conditions such as Barrett esophagusBAIR-it ih-SOF-uh-gusA change in the lining of the lower esophagus in which its normal cells are replaced by cells like those lining the intestine.Full entry . Through the scope the doctor can take biopsies, remove polypPOL-ipA growth that sticks out from the lining of a hollow organ, such as the colon, nose or uterus.Full entry , inject or band bleeding varicesVAIR-ih-seezSwollen, twisted veins, most often in the lower esophagus or the stomach, or in the legs.Full entry , place a enteral feeding tubeEN-ter-ul FEE-ding toobA tube placed into the stomach or small intestine to give liquid food, water and drugs to a person who cannot eat enough by mouth.Full entry (PEGPEG, or pee-ee-JEE (said as letters)An abbreviation that can mean a feeding tube placed through the belly into the stomach, or the laxative polyethylene glycol.Full entry , below) or a stentstentA small tube, often of metal mesh, placed inside a vessel or duct to hold it open.Full entry across a narrowing, and stretch a strictureSTRIK-cherA narrowed section of a hollow body passage, such as the urethra, esophagus or bowel, that is tighter than normal.Full entry with esophageal dilatorDY-lay-terAn instrument used to stretch or widen an opening, canal or passage in the body.Full entry such as the Maloney, Savary or balloon types. Graduated dilators can also be slid over a guidewire under fluoroscopy.
Position and steps: an IV is started, the throat is sprayed and sedationsih-DAY-shunA calm, relaxed or sleepy state brought on by drugs, or the use of drugs to cause it.sed calm, settle-ation processFull entry is given, with the patient in the left lateral position and the neck bent forward. A bite block keeps the patient from biting the scope, and lubricant goes on its tip. The scope is advanced into the duodenum, then drawn back slowly while the lining is studied, with biopsies and treatment along the way. If varices are to be injected, you prepare the sclerosing agent.
Esophagoscopy looks mainly at the esophagus. A rigid esophagoscope can be used, flared at its far end because the esophagus collapses around it, but often the flexible gastroscope does the job as part of an EGD. A rigid setup holds a set of esophagoscopes, light carriers, biopsy forceps and bougies; you insert the light carrier, attach the light cord and lubricate the scope. It helps diagnose cancer, diverticula, hiatal herniaHER-nee-uhA bulge of an organ or tissue through a weak spot in the muscle or tissue wall that normally holds it in.Full entry , strictures and varices, and treats by removing a swallowed object or passing a bougie to widen a narrowed esophagus.
endoscopic retrograde cholangiopancreatographyen-doh-SKOP-ik RET-roh-grade koh-lan-jee-oh-pan-kree-uh-TOG-ruh-feeA procedure that uses a scope passed through the mouth, with dye and X-rays, to see and treat the bile and pancreatic ducts.endo- within-scopic viewingretrograde moving backwardcholangi/o bile ductpancreat/o pancreas-graphy making a pictureFull entry (endoscopic retrograde cholangiopancreatography) uses a duodenoscope, which reaches through the stomach into the duodenum. Dye is injected through the papilla of Vater under fluoroscopy to outline the bilebileA yellow-green fluid made by the liver and stored in the gallbladder that helps digest fats.chol/e bileFull entry and pancreasPAN-kree-usA long, flat gland behind the stomach that makes digestive enzymes and the hormones insulin and glucagon.pan- allcreas fleshFull entry ducts. It helps find the cause of a blocked bile ductbyle duktOne of the tubes that carry bile from the liver and gallbladder to the small intestine.Full entry , allows biopsy, and lets the doctor cut the sphincterSFINGK-terA ring of muscle that tightens to close an opening or passage in the body and relaxes to open it.Full entry (a sphincterotomy) to pull out duct stones or place a stent. Duodenoscopes are hard to clean: outbreaks of drug-resistant bacteria have been traced to ones that were not fully reprocessingree-PROS-es-ingThe steps that make a used reusable medical device safe to use on the next patient.Full entry .
After: fluids are offered only once the gag reflexREE-fleksAn automatic body response to something that stimulates it, which happens without thought, such as the knee jerk.Full entry returns, and the patient is watched until the sedation wears off.

Colonoscopy and sigmoidoscopy
What and why: colonoscopykoh-luh-NOS-kuh-peeAn exam of the inside of the large intestine with a long, flexible tube that has a camera on its end.col/o colon-scopy looking with an instrumentFull entry examines the colon from the rectum to the ileocecal valve. It screens for cancer, finds the source of bleeding or inflammation, removes polyps and takes biopsies. Adults at average risk now start routine screening at age 45. A lesionLEE-zhunAn area of tissue that has been damaged or has changed from normal, such as a sore, wound, lump or spot.Full entry that will need surgery is often tattooed so the surgeon can find it later. Sigmoidoscopy examines only the rectum and the sigmoidSIG-moydShaped like the letter S; most often short for the sigmoid colon, the S-shaped last part of the colon before the rectum.Full entry colon.
Preparation and position: the patient limits food and takes a bowel-cleansing prep beforehand. For colonoscopy the patient lies on the left side with the knees bent, under warm blankets, with only the lower back and buttocks uncovered and a small drape over the pelvis. The doctor may ask for the patient to be turned, or for gentle pressure on the abdomen, to help the scope along. Sigmoidoscopy is done prone or in lithotomylih-THOT-uh-meeA position lying on the back with the hips and knees bent and the legs raised and spread apart, often in stirrups.lith/o stone-tomy cutting intoFull entry , and a cooperative patient can have a flexible sigmoidoscopy without sedation.
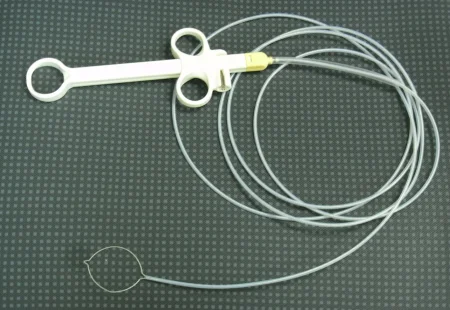
Steps: the lubricated scope is advanced to the cecum, then withdrawn slowly while the lining is inspected and photographed. Air pumped into the colon can cramp, so reassure the patient. Polyps come off with a wire snare, and cup or brush biopsy forceps take tissue.
After: watch for bleeding, pain, signs of a perforationper-fuh-RAY-shunA hole that goes all the way through the wall of an organ or tissue.per- throughforat bored (a hole)-ion processFull entry and reactions to the medicines. Perforation, bleeding, breathing trouble, chest pain and reactions to the anesthetican-us-THET-ikA drug that causes loss of feeling, with or without loss of consciousness.an- withoutesthesi/o feeling, sensation-ic relating toFull entry are the rare serious complications of any endoscopy.
Wound class (all flexible endoscopy): no incision is made. The tract is entered through its own opening under control, and the references class an endoscopy of a tract, such as a cystoscopy or a hysteroscopy, as Class II, clean-contaminated.

8Exploratory laparotomy and bowel technique
An exploratory laparotomylap-uh-ROT-uh-meeSurgery that opens the abdomen through a large cut to reach the organs inside.lapar/o abdomen-tomy cutting intoFull entry opens the abdomen to find and treat a problem when less invasive tests have not made the diagnosis, as after trauma or with a blockage, a perforationper-fuh-RAY-shunA hole that goes all the way through the wall of an organ or tissue.per- throughforat bored (a hole)-ion processFull entry or bleeding. Its opening and closing steps are the same for every open abdominal case.
Position: supine, arms on armboards. Prep and drape: the full abdomen; towels and a laparotomy sheet. Setup: a major laparotomy tray, long instruments, a self-retaining retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry , plenty of lap sponges, Yankauer and Poole suction, warm irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry and culture tubes. Intestinal clamps, staplers, vascular clamps, hemostatichee-moh-STAT-ikStopping bleeding; also, a product or agent used to stop bleeding.hem/o blood-stasis stopping, standing still-ic relating toFull entry and a bowel bag (a plastic bag that keeps bowel lifted out of the abdomen from drying) are opened or kept on hold.
An open abdomen loses heat fast. A forced-air warmer, irrigation kept in a solution warmer and keeping the patient covered before and after surgery protect against hypothermiahy-poh-THER-mee-uhA body temperature that has fallen below the normal range.hypo- belowtherm/o heat-ia conditionFull entry , and sequential compression devicesih-KWEN-shul kum-PRESH-un dih-VYSInflatable leg sleeves that fill with air and squeeze the legs in turns to keep blood moving in the veins.Full entry help prevent deep vein thrombosisDEEP VAYN throm-BOH-sisA blood clot in a deep vein, most often in the leg or pelvis.thromb/o clot-osis conditionFull entry .
Opening: the same steps begin every open abdominal case.
- The surgeon cuts the skin with the skin knife (a #20 or #10 blade); the knife goes into a basin and leaves the field once the skin is open. The electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry then goes through the fat, and bleeders are coagulationkoh-ag-yuh-LAY-shunThe process by which blood changes from a liquid into a gel, forming a clot.coagul clot-ation processFull entry or clamped.
- The fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry is opened with the deep knife (a #10 blade) or the ESU, and the opening is extended with the ESU or curved Mayo scissors. Off the midlineMID-lineAn imaginary line down the center of the body; also, a type of IV catheter placed in a vein of the upper arm.Full entry , the muscle is split or held aside. Have small Richardson or Army-Navy retractors ready.
- Before the peritoneumpair-ih-toh-NEE-umThe thin membrane that lines the belly cavity and covers most of the organs inside it.peri- aroundton stretched-eum a structureFull entry is opened, loose 4x4 sponges leave the field. The peritoneum is lifted with hemostatHEE-moe-statA clamp with finger rings and a locking ratchet used in surgery to grasp and close off bleeding vessels.hem/o blood-stat stopping, standing stillFull entry or smooth forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry , nicked with the deep knife or Metzenbaum scissors while the bowel is held away, and opened wider with scissors or the ESU. Cultures may be taken now. From here on, moist laps only.
- The surgeon explores the abdomen, often with a large Richardson retractor. If the table is tilted, keep the Mayo clear of the patient. Pass moist laps to protect the wound edges, then the self-retaining retractor, and more laps to pack the bowel away from the problem.
For heavy bleeding the area is packed first to slow it; then come suction, clamps, ties or clips and hemostatic agents.
In a badly injured, unstableun-STAY-bulDescribes a client whose condition is changing quickly or is hard to predict.Full entry patient, the surgeon may do damage control surgery: stop the bleeding and the contamination as fast as possible, without trying to rebuild anything, so the patient can go to the ICU to be warmed and resuscitationrih-sus-ih-TAY-shunEmergency treatment to restore breathing, heartbeat or blood circulation.Full entry . Have at least eight moist laps, two suctions and the ESU ready at the incision. All four quadrants are packed (note how many laps go into each), bleeding and bowel spillage are controlled, and the abdomen is irrigated, counted and left open, usually for at least 24 hours. It is covered with layers of plastic drape and drains, a sterile plastic bag sewn to the edges (a Bogota bag) or a wound vacuum system, and closed in stages at later operations. An abdomen left open also guards against abdominal compartment syndromekum-PART-ment SIN-drohmA buildup of pressure inside a closed group of muscles that cuts off their blood supply.Full entry : swelling from the injury and from the resuscitation fluids pushes the pressure inside a closed abdomen past what the blood vessels can bear, so tissue dies from lack of blood flow and breathing can be blocked. The treatment is to open the abdomen at once.
Closing: the same steps end every open abdominal case.
- The surgeon irrigates with fresh warm saline, which you suction out with the Poole, and checks for bleeding.
- All packs and instruments come out of the abdomen and the closing count begins; it must be complete before the peritoneum is closed.
- The peritoneum may be closed as its own layer, closed together with the fascia, or not closed at all; closing it separately adds no strength. The fascia, the layer that matters, is closed with strong sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry , often running. The fat may be closed with fine absorbable suture, and the skin with staples or a buried stitch.
- Retention sutures, heavy sutures through every layer threaded through tubing bolsters or bridges, are seldom used now; they may be placed for a patient at high risk of the wound splitting open.
A visceralVIS-er-ulHaving to do with the internal organs, especially those in the chest and belly.viscer/o internal organs-al relating toFull entry retainer may lie over the bowel while the fascia is closed: a flexible, radiopaqueray-dee-oh-PAYKBlocking x-rays, so the material shows up white on an x-ray image.radi/o radiation, x-rayopaque not letting throughFull entry pad that keeps the needle from catching bowel, with a ring that stays outside the body until the pad is pulled out.
In a contaminated or dirty wound, the skin may be left open and packed and closed later.
Specimens: whatever is removed. Cultures go to the lab right away in their own tubes.
Counts: before the incision, when closure of the peritoneum begins, when closure of the fascia begins, when skin closure begins, whenever items are added, and when the scrub or circulator changes.
Dressing: a dry dressing with an ABD pad, or wound vacuum-assisted closurewoond VAK-yoom uh-SIS-tid KLOH-zhurA wound treatment that uses a sealed dressing connected to a suction pump to draw fluid out and help the wound heal.Full entry over the closed incision or over an open abdomen.
Bowel technique
Once the GI tract is open, germs from its lumenLOO-menThe open space inside a tube, such as a blood vessel, the intestine or a catheter.Full entry contaminate whatever touches it, and in a cancer operation, tumor cells can be shed and seed healthy tissue. Bowel technique, also called isolation technique, keeps both away from the clean wound.
- It begins when the GI tract is opened and ends when it is closed. The team says aloud that the bowel is being opened.
- Before the bowel is opened, towels or a plastic wound protector go around the incision to catch spillage.
- Everything that touches the open bowel is dirty: instruments, sponges, suction tip, ESU tip, staplers, gloves and gowns. It stays in one dirty area, such as a second Mayo or a basin, apart from the clean Mayo and back table. The specimen goes into its own dirty basin for the circulator.
- Do not handle the clean setup while the bowel is open. If you need a clean item, pick it up with a sponge stick kept in a small basin for that job, touching only its rings.
- When the bowel is closed, the dirty items, the towels or wound protector, the suction tip, the ESU pencil and the light handles go to the dirty area. The dirty Mayo moves away but stays where you can still count from it. The wound is irrigated, the counts begin, and the change to a clean closure is announced.
- The team changes gloves, and often gowns too. One sterile member stays at the field while the others change, then changes last. New drapes or towels go over the old ones, with new light handles, a new suction tip and ESU pencil, clean sponges and clean instruments for the closure.
AST's 2017 bowel technique guideline has every sterile team member change both gown and gloves, with the scrub changing first and then gowning and gloving the others.
There are two ways to set up for it:
- Single setup: one set of instruments for the whole case. Before the bowel is opened, what the resectionrih-SEK-shunSurgery to remove part of an organ or tissue.re- back, againsect to cut-ion processFull entry needs goes to the Mayo; the back table stays sterile but untouched. Afterward the dirty items leave the field in a basin, the team changes gloves, the wound is redraped, and the Mayo is covered with sterile towels before the closing items come from the back table. A wet Mayo gets an impervious cover so moisture cannot carry germs through.
- Double setup: one setup for the operation through the bowel closure and specimen removal, and a second, covered setup, prepared before the case begins, for the closure. The closing setup may be a minor laparotomy tray.
Either way, a wound protector or towels guard the wound before the resection, and the wound is irrigated before the change to a clean closure.
Wound classes (taught in full in chapter 11) rate how contaminated a wound is, and so how likely it is to become infected:
- Class I (clean): no inflammation, and the respiratory, GI, genital and urinary tracts are not entered.
- Class II (clean-contaminated): one of those tracts is entered under control, without unusual contamination. Surgery of the bilebileA yellow-green fluid made by the liver and stored in the gallbladder that helps digest fats.chol/e bileFull entry tract and the appendixuh-PEN-diksA small, finger-shaped pouch attached to the first part of the large intestine, in the lower right abdomen.Full entry belongs here.
- Class III (contaminated): gross spillage from the GI tract, a major break in surgical asepsisSUR-jih-kul ay-SEP-sisPractices that keep an area or object completely free of microorganisms; also called sterile technique.a- withoutsepsis decay, infectionFull entry , acute inflammation without pus, or a fresh traumatic wound.
- Class IV (dirty): an infection already present, a perforated organ, or an old traumatic wound with dead tissue.
The bowel is about to be opened. Set up the dirty side, sort what touches it, and close out clean.
This lab runs in the browser with JavaScript on.
This browser could not start the 3D room. Everything the lab practices is in the chapter.
9Gallbladder and appendix
Laparoscopic cholecystectomy
What and why: a cholecystectomykoh-luh-sis-TEK-tuh-meeSurgery to remove the gallbladder.chol/e bilecyst/o sac, bladder-ectomy surgical removalFull entry removes the gallbladder, most often for painful gallstones, cholecystitiskoh-luh-sis-TY-tisInflammation of the gallbladder.chol/e bilecyst/o sac, bladder-itis inflammationFull entry or gallstone pancreatitispan-kree-uh-TY-tisInflammation of the pancreas, which may come on suddenly (acute) or last for years (chronic).pancreat/o pancreas-itis inflammationFull entry ; a calcified gallbladder is another reason. A stone that blocks the flow concentrates the bilebileA yellow-green fluid made by the liver and stored in the gallbladder that helps digest fats.chol/e bileFull entry behind it and raises the bilirubinbil-ih-ROO-binA yellow pigment made when old red blood cells break down, which the liver clears into bile.Full entry in the blood, causing jaundiceJAWN-disYellow color of the skin, the whites of the eyes and other tissues from too much bilirubin in the blood.Full entry . An inflamed gallbladder can rupture and spill bile, which causes biliary peritonitispair-ih-tuh-NY-tisInflammation of the peritoneum, the thin membrane that lines the inside of the belly and covers the organs there.peritone/o peritoneum-itis inflammationFull entry . High cholesterol and a high BMI make gallstones more likely. laparoscopylap-uh-ROS-kuh-peeSurgery or an exam done through small cuts in the belly, using a thin, lighted tube with a camera.lapar/o abdomen-scopy looking with an instrumentFull entry is the standard approach.
Diagnosis: ultrasound, computed tomographykum-PYOO-tid toh-MOG-ruh-feeAn imaging test that uses x-rays and a computer to make cross-section pictures of the inside of the body.tom/o cut, slice-graphy process of recordingFull entry , an abdominal X-ray or endoscopic retrograde cholangiopancreatographyen-doh-SKOP-ik RET-roh-grade koh-lan-jee-oh-pan-kree-uh-TOG-ruh-feeA procedure that uses a scope passed through the mouth, with dye and X-rays, to see and treat the bile and pancreatic ducts.endo- within-scopic viewingretrograde moving backwardcholangi/o bile ductpancreat/o pancreas-graphy making a pictureFull entry , with blood work such as a CBC with differential and electrolytes. In ERCP, a flexible scope reaches the duodenumdoo-uh-DEE-numThe first, short part of the small intestine, just after the stomach.Full entry and dye goes into the ducts through the ampulla of Vater. Stones stuck in the common bile ductKOM-un BILE DUKTThe tube that carries bile from the liver and gallbladder into the small intestine.Full entry are often cleared by ERCP before surgery.
anesthesiaan-us-THEE-zhuhLoss of feeling or sensation, often brought on by drugs so that surgery or a procedure can be done without pain.an- withoutesthesi/o feeling, sensation-ia conditionFull entry and position: general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry ; supine, arms on armboards. After the scope is in, the table goes into reverse Trendelenburg positionree-VERS tren-DEL-un-burg puh-ZISH-unA position lying on the back on a bed or table that is tilted so the head is higher than the feet, with the body kept straight.Full entry and tilts to the left, which raises the right side and lets the bowel fall away. A nasogastric tubenay-zoh-GAS-trik toobA thin, flexible tube passed through the nose and down the esophagus into the stomach.nas/o nosegastr/o stomach-ic having to do withFull entry empties the stomach, and a urinary catheter may be placed. Monitoring includes depth of anesthesia (BIS), capnography (carbon dioxideKAR-bun dy-OK-sideA gas made by the body's cells as waste, carried in the blood to the lungs and breathed out.Full entry monitoring), blood pressure, heart rate, saturationsach-uh-RAY-shunHow full something is; in nursing, usually the percentage of hemoglobin in the blood that is carrying oxygen.Full entry , breathing rate, temperature and urine output, and deep vein thrombosisDEEP VAYN throm-BOH-sisA blood clot in a deep vein, most often in the leg or pelvis.thromb/o clot-osis conditionFull entry prevention is used.
Prep and drape: the abdomen; folded towels and a fenestrated laparotomylap-uh-ROT-uh-meeSurgery that opens the abdomen through a large cut to reach the organs inside.lapar/o abdomen-tomy cutting intoFull entry drape.
Room: camera unit, light source, insufflationin-suh-FLAY-shunBlowing a gas into a body cavity, such as carbon dioxide into the abdomen during laparoscopic surgery.Full entry and carbon dioxide, electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry , video monitors, suction, a pressure bag for the irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry saline, positioning aids (armboards, a footboard, a head support and a safety strap) and a table that X-rays can pass through. On hold: a C-arm, lead aprons and a smoke evacuator.
Setup: a laparoscopy tray with a 5 or 10 mm scope, 0 or 30 degrees (the 30-degree scope helps view the gallbladder high in the abdomen); trocarTROH-karA sharp or bladed instrument inside a tube (cannula), used to pierce a body wall and leave the tube in place as a port.Full entry , two 10 mm and two 5 mm, with a Hasson cannulaKAN-yoo-luhA thin tube placed into the body or a body opening to deliver or remove fluid or air.Full entry if needed; a Veress needle and 10 mL syringe; a #11 blade; graspers, a Maryland dissector, hook or spatula cautery, scissors, a needle aspirator, ultrasonic shears, a clip applier, a suction-irrigator, a specimen bag, anti-fog and a scope warmer. On hold: cholangiogram supplies, gallbladder and common bile duct instruments, a choledochoscope and stone basket, and a major laparotomy tray with long instruments and a self-retaining retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry in case the case converts.
Medications: contrastKON-trastA dye or other substance given before an imaging test so body parts show up more clearly.Full entry and injectable saline for a cholangiogram, IV saline for irrigation, a local anestheticLOH-kul an-es-THET-ikA drug that blocks feeling in one part of the body without making the person unconscious.Full entry for the port sites, and topical hemostatichee-moh-STAT-ikStopping bleeding; also, a product or agent used to stop bleeding.hem/o blood-stasis stopping, standing still-ic relating toFull entry .
Key steps:
- A #11 blade incision at the umbilicus. The Veress needle goes in, its position is checked with the 10 mL syringe, and the abdomen is inflated. The needle is swapped for a 10 mm trocar and cannula, and the scope goes in. Hasson or optical entry are the other ways in.
- The other trocars go in under view: 10 mm below the xiphoid, and two 5 mm ports below the right ribs, at the midclavicular line and the anterior axillary line.
- A grasper on the fundusFUN-dusThe rounded top or base of a hollow organ, most often the top of the uterus.Full entry pushes the gallbladder up toward the patient's head; a second grasper pulls the infundibulum out to the side, opening the hepatocystic triangle. The gallbladder may be punctured with the needle aspirator to draw off bile.
- The surgeon clears the triangle with the hook, scissors and a grasper or dissector until the critical view of safety: the triangle cleared of fat and fibrousFY-brusMade of or containing tough threads (fibers), especially of connective tissue.fibr/o fiber-ous full of, relating toFull entry tissue, the lower third of the gallbladder lifted off the liver, and only two structures, the cystic duct and the cystic artery, entering the gallbladder. Nothing is clipped or cut before this.
- If a cholangiogram is planned (below), it is done now, before the cystic duct is divided: a clip goes on the gallbladder end of the cystic duct, and the duct is opened just below it for the catheter.
- Clips go on the cystic duct and the cystic artery, commonly two on the side that stays and one on the gallbladder side, and each is cut between them. Keep the clip applier loaded.
- The gallbladder is peeled off the liver bed with the hook or spatula, placed in a retrieval bag and removed, usually through the umbilical port.
- The liver bed and abdomen are irrigated and checked for bleeding, and the gas is let out. The fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry at the 10 mm sites is closed with absorbable sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry , and the skin with an absorbable buried stitch.
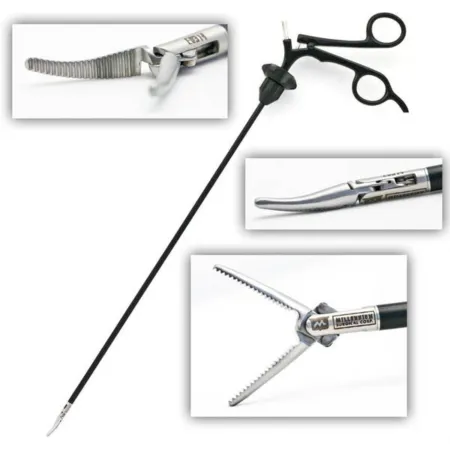

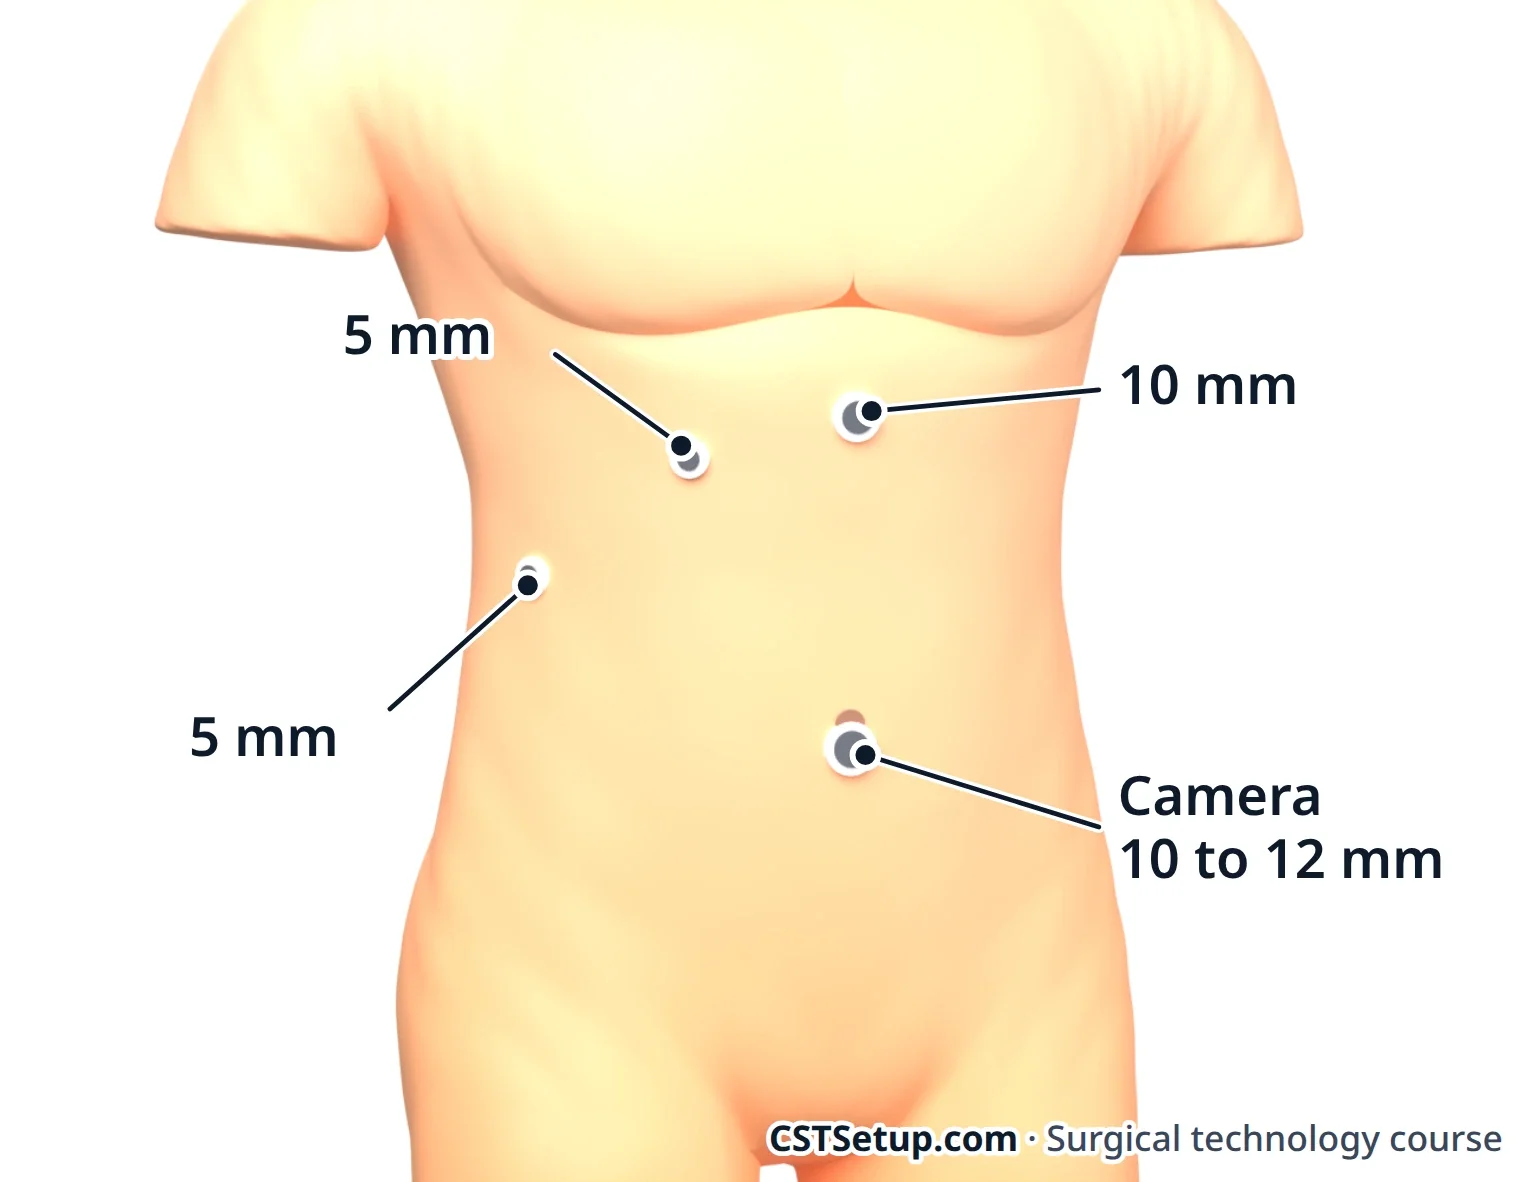
Some surgeons remove the gallbladder robotically, with results like the laparoscopiclap-uh-roh-SKOP-ikDone through a few small cuts in the abdomen with a thin camera and long instruments, instead of one large opening.lapar/o abdomen-scopic viewingFull entry operation.
Cholangiogram: an X-ray of the bile ductbyle duktOne of the tubes that carry bile from the liver and gallbladder to the small intestine.Full entry filled with contrast. It shows stones and the shape of the ducts. Some surgeons do one in every case, and others when the anatomy is unclear or a duct stone is suspected.
The surgeon clips the cystic duct and makes a small cut in it. The catheter comes in through a small puncture in the right upper abdomen, is threaded into the duct and is held with a clip or clamp. Saline goes in first to check its position, then the contrast.
Your setup: the catheter, a stopcock and IV tubing, and two labeled syringes (often 20 mL), one of saline and one of contrast diluted as the surgeon orders. Remove every air bubble from the syringes, tubing and catheter, because a bubble looks like a stone on the image.
Before the X-ray, radiopaqueray-dee-oh-PAYKBlocking x-rays, so the material shows up white on an x-ray image.radi/o radiation, x-rayopaque not letting throughFull entry sponges and extra instruments come out of the field, and a sterile drape covers it for the C-arm. Everyone wears a lead apron, stands behind a shield or leaves the room. If stones show, the surgeon may explore the common bile duct: the cystic duct is dilated, a choledochoscope goes in, and a basket or balloon catheter pulls the stones out. Keep the stones dry: they go to the lab with no saline, and never in a preservative, which can dissolve or change them.
Specimen: the gallbladder and any stones. Receive it in a basin so bile does not spill on the field.
Counts: initial, at fascia closure and at skin closure.
Drains and catheters: a urinary catheter; for a duct exploration, a Fogarty catheter, with a T-tube and drainage bag ready.
Dressing: a nonadherent pad with 2x2 gauze or a clear film, or skin glue or strips.
After surgery: the patient goes to PACU, and most go home the same day. Laparoscopy may be ruled out by suspected gallbladder cancer, cirrhosissih-ROH-sisLong-term scarring of the liver, in which scar tissue replaces healthy tissue and keeps the liver from working normally.cirrh/o orange-yellow-osis abnormal conditionFull entry with high portal pressure, peritonitis throughout the abdomen, septic shockSEP-tik shokThe most severe stage of sepsis, in which the circulation fails and blood pressure stays low even after IV fluids.sept/o infection-ic relating toFull entry , late pregnancy, or a heart or lung problem that cannot tolerate the gas. Advanced age and liver cirrhosis can also weigh against gallbladder surgery, and gallstones that cause no symptoms are usually left alone.
Complications: injury to the bile duct or nearby organs, bleeding, an ongoing bile leak, bile or stones spilled into the abdomen, and surgical site infection. The worst is injury to the common bile duct, usually from mistaking it for the cystic duct. That is why the surgeon slows down to reach the critical view of safety, and why a quiet, ready scrub matters most at that moment.
Wound class: II, because the biliary tract is entered; III if bile spills or the gallbladder is acutely inflamed without pus; IV if infection, such as pus, is already present. The Core Curriculum's outline and one surgical technology textbook list an uncomplicated case as Class I, and Class II only when a cholangiogram is done.
Open cholecystectomy
What and why: the open operation treats the same disease. It is chosen when laparoscopy is ruled out, as with suspected gallbladder cancer, late pregnancy, cirrhosis with high portal pressure, peritonitis throughout the abdomen, septic shock, scarring from earlier surgery or a heart or lung problem that cannot tolerate the gas, and it follows a conversion when the surgeon cannot identify every structure through the scope. Since laparoscopy became the standard, open experience has fallen sharply. The large incision means more tissue injury and a longer recovery.
Position, prep and drape: supine, in reverse Trendelenburg; the abdomen is prepped and draped for a laparotomy. The patient has general anesthesia, may get an NG tube, and may receive a prophylaxisproh-fuh-LAK-sisTreatment given to prevent a disease or problem, rather than to treat one that is already present.pro- beforephylax guardFull entry antibiotic. If a cholangiogram is likely, the bed must let the C-arm in, and the team wears radiationray-dee-AY-shunEnergy that travels as waves or particles, such as X-rays, used to make images or treat cancer; also pain that spreads from its starting point.radi/o rays, radiation-ation processFull entry protection.
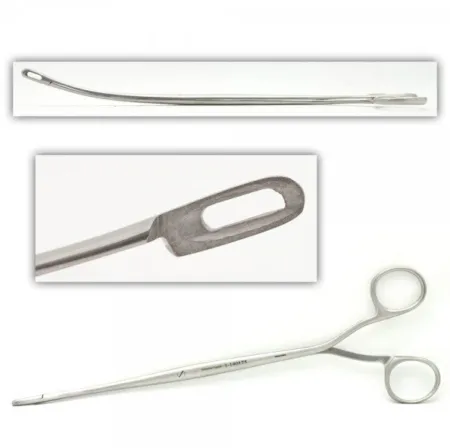
Setup: a laparotomy set and a gallbladder set, with an ultrasonic scalpel, bipolarby-POH-lerHaving two poles or two opposite ends; most often used as a short form of bipolar disorder.bi- twopolar having polesFull entry and monopolar ESU, clips and an applier, Potts scissors and a #11 blade. On hold: long instruments, cholangiogram supplies, the C-arm and its drape, a T-tube and drainage bag, and lead aprons. Gall duct instruments include Bakes dilatorDY-lay-terAn instrument used to stretch or widen an opening, canal or passage in the body.Full entry , gall duct and stone forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry , duct probes and stone scoops.
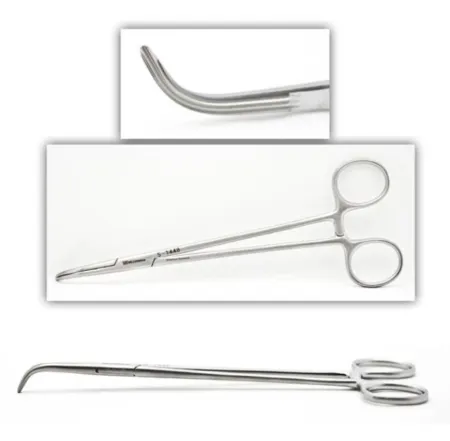
Keep right-angle clamps ready throughout, to reach under and around the ducts and vessels.
Medications: a long-acting local anesthetic may be injected along a subcostalsub-KOS-tulBelow the ribs.sub- belowcost/o rib-al relating toFull entry incision to ease pain afterward. The cholangiogram uses saline and diluted contrast, set up as above.
Key steps:
- An upper midlineMID-lineAn imaginary line down the center of the body; also, a type of IV catheter placed in a vein of the upper arm.Full entry or right subcostal incision. The subcostal one shows the biliary tree better but hurts more afterward, because the muscle is cut along the rib edge.
- A Deaver or Harrington retractor lifts the liver, and moist laps pack the nearby organs away. A swollen gallbladder may be emptied with a trocar on suction, and the hole closed with a clamp.
- A clamp on the body of the gallbladder gives tractionTRAK-shunA steady pulling force applied to a body part with weights, ropes and pulleys.Full entry . The surgeon opens the peritoneumpair-ih-toh-NEE-umThe thin membrane that lines the belly cavity and covers most of the organs inside it.peri- aroundton stretched-eum a structureFull entry over the Calot triangle and dissectdy-SEKT, or dih-SEKTTo cut apart or separate tissues carefully during surgery.Full entry with scissors, peanuts on holders and right angles.
- The cystic artery is tied twice or clipped and divided, and the cystic duct is dissected down to where it joins the common hepatichih-PAT-ikRelating to the liver.hepat/o liver-ic relating toFull entry duct.
- A cholangiogram may be done through the cystic duct, with the catheter placed under direct view.
- The gallbladder is freed from the liver bed. Receive it in a basin along with any clamps still on it, so bile stays off the field.
- The liver bed may be sewn, drains leave through a separate stab wound, and the wound is closed in layers.
Common bile duct exploration: when stones sit in the duct, two fine traction sutures lift its wall and the surgeon opens it lengthwise between them. Stones come out with stone forceps, scoops, irrigation or a balloon catheter, or with a choledochoscope and basket. The duct may be closed over a T-tube, whose long arm leaves through the wound to a drainage bag. Duct exploration during surgery is far less common now, because endoscopicen-doh-SKOP-ikDone with an endoscope, a thin tube with a light and camera passed into the body.endo- within-scopic viewingFull entry procedures before surgery remove most duct stones.
Specimen, counts and dressing: the gallbladder and any stones; counts as for a laparotomy. A bulky abdominal dressing, with each drain sewn to the skin and covered.
Wound class: II, because the biliary tract is entered.
After surgery: the complications are those of the laparoscopic operation, led by injury to the bile duct, bleeding, a bile leak and infection.
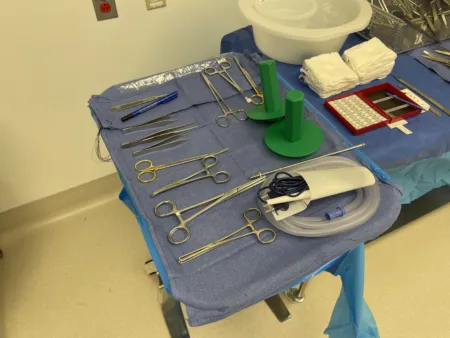
Appendectomy, open and laparoscopic
What and why: appendicitisuh-pen-dih-SY-tisInflammation of the appendix, the small pouch that hangs from the start of the large intestine.append/o appendix-itis inflammationFull entry usually starts when the inside of the appendixuh-PEN-diksA small, finger-shaped pouch attached to the first part of the large intestine, in the lower right abdomen.Full entry is blocked. Pressure builds, the wall swells and loses blood flow, bacteria spread, and the appendix can turn gangreneGANG-greenThe death of body tissue because its blood supply has been lost or because of severe infection.Full entry and burst, causing peritonitis. Most appendectomies are laparoscopic.
Laparoscopic: supine, in slight Trendelenburg positiontren-DEL-en-burg puh-ZISH-unA position in which the client lies on the back with the bed tilted so the head is lower than the feet.Full entry with the right side of the table slightly raised. The camera port goes at the umbilicus, with working ports elsewhere, often one in the right upper quadrant and one low in the midline above the pubisPYOO-bisThe front part of each hip bone, low in the pelvis; the two meet in the middle at the pubic symphysis.pub/o pubisFull entry . The surgeon finds the cecum and follows it to the appendix base, then makes a window in the mesoappendix, which carries the appendix's artery. It is divided with an energy device or a stapler with a vascular load; then the base is stapled or closed with pre-tied loops. The appendix leaves in a retrieval bag, and free fluid is cultured if there are signs of infection. A perforationper-fuh-RAY-shunA hole that goes all the way through the wall of an organ or tissue.per- throughforat bored (a hole)-ion processFull entry appendix or peritonitis may call for open surgery.
Open: a McBurney or Rocky-Davis incision; the muscles are split and held with small retractors. The surgeon lifts the appendix with a Babcock, divides and ties the mesoappendix, crushes and ties the base, and cuts the appendix off. Some surgeons bury the stump with a purse-string stitch in the cecum. The knife, clamps and anything that touched the cut end go into a basin with the specimen: bowel technique on a small scale. The team then changes gloves (and often gowns), and the wound is closed with clean instruments.
Prep and drape: the abdomen; towels and a laparotomy sheet. Medications: in an open appendectomyap-en-DEK-tuh-meeSurgery to remove the appendix.append appendix-ectomy surgical removalFull entry , antibiotic irrigation, mixed in a small basin on the back table, may be used, especially when the wound is contaminated. Specimen: the appendix, and a culture of any pus or fluid. Counts: initial and closing. Dressing: strips or glue on the ports; a dry dressing on an open wound. After a rupture, the skin may be left open and packed.
Wound class: II if the appendix is not perforated, III if inflamed without pus, IV if there is pus or it has burst. Some references class a ruptured appendix as III.
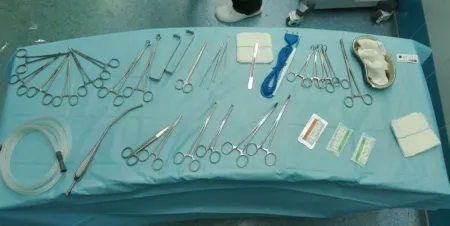
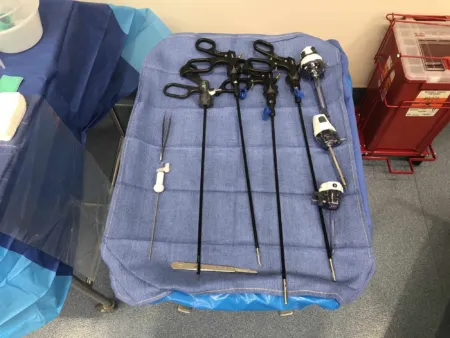
10Hernia repair
A herniaHER-nee-uhA bulge of an organ or tissue through a weak spot in the muscle or tissue wall that normally holds it in.Full entry is tissue, such as fat or bowel, bulging through a weak spot or opening in the wall that should hold it in. It is reducible if it slips back, incarcerated if it is stuck, and strangulated if its blood supply is cut off, which is a surgical emergency because the trapped tissue can die. The weakness may be present from birth or follow an earlier operation or an injury. A hiatal hernia, in which part of the stomach slides up through the diaphragmDY-uh-framThe dome-shaped sheet of muscle under the lungs that is the main muscle of breathing; also the flat side of a stethoscope.Full entry , is taught with the stomach operations below.
Herniorrhaphy and hernioplasty both mean hernia repair. A repair either sews the patient's own tissue together or adds mesh. Mesh bridges the weak area without tension and becomes filled with scar tissue, so many repairs use it. Synthetic mesh is a permanent implant: confirm its type and size with the surgeon before you open it, and know that its maker's details go into the patient's record. Mesh comes in sheets or patches, cut to overlap the edges of the defect, and is held with tacks, staples or sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry . Hernia sutures are soft and pliable, such as polyester or synthetic absorbable, with fine absorbable suture on the delicate sac. Most simple repairs are outpatient cases, and the patient goes home the same day.
Inguinal hernia
The inguinalING-gwih-nulRelating to the groin, the fold where the thigh meets the lower abdomen.Full entry canal is a tunnel about 4 cm long, just above the inguinal ligament. It runs from the deep ring to the superficial ring and carries the spermatic cord in males and the round ligament in females.
- Indirect: enters the deep ring and follows the cord, lateral to the inferior epigastric vessels. It may be present from birth and can reach the scrotumSKROH-tumThe pouch of skin and muscle that holds the testicles.Full entry or labia. It is the most common hernia.
- Direct: pushes through the back wall (floor) of the canal in the Hesselbach triangle, medial to the inferior epigastric vessels. The triangle is bordered by those vessels, the edge of the rectusREK-tusLatin for straight; the name of several straight muscles, such as the rectus abdominis of the abdomen and the rectus femoris of the thigh.Full entry muscle and the inguinal ligament. It comes with age and straining, such as heavy lifting.
- femoralFEM-er-ulRelating to the thigh or the femur, the thigh bone.Full entry : passes below the inguinal ligament, just medial to the femoral vein. It is more common in women than in men, and far more likely than an inguinal hernia to become incarcerated or strangulated.
Open mesh repair (Lichtenstein): supine; groin prep; towels and a laparotomylap-uh-ROT-uh-meeSurgery that opens the abdomen through a large cut to reach the organs inside.lapar/o abdomen-tomy cutting intoFull entry sheet. It may be done under general, spinal or local anesthesiaLOH-kul an-es-THEE-zhuhNumbing medicine applied to or injected into one small area, so a procedure there is not felt while the person stays awake.Full entry . Setup: a laparotomy set, a Penrose drain, mesh and local anestheticLOH-kul an-es-THET-ikA drug that blocks feeling in one part of the body without making the person unconscious.Full entry . It is the most common open mesh repair. Steps:
- An oblique groin incision through the fat and Scarpa fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry to the external oblique aponeurosis.
- The aponeurosis is opened along its fibers while the ilioinguinal and iliohypogastric nerves are found and protected.
- The cord is freed and looped with a Penrose drain, dipped in saline first and held with a clamp, for gentle tractionTRAK-shunA steady pulling force applied to a body part with weights, ropes and pulleys.Full entry .
- An indirect sac is freed from the cord, then pushed back, or opened, emptied, tied off and cut away.
- Mesh is trimmed to lie flat on the floor of the canal, slit for the cord, and sewn to the inguinal ligament below and the internal oblique and rectus sheathSHEETHA covering that wraps around a structure; in procedures, a short hollow tube left in a blood vessel to pass catheters through.Full entry above.
- The layers are closed.

laparoscopiclap-uh-roh-SKOP-ikDone through a few small cuts in the abdomen with a thin camera and long instruments, instead of one large opening.lapar/o abdomen-scopic viewingFull entry and robotic repair: the mesh goes behind the abdominal wall, in the preperitoneal space, covering the direct, indirect and femoral openings at once. In a TAPP repair the surgeon enters the abdomen, opens a flap of peritoneumpair-ih-toh-NEE-umThe thin membrane that lines the belly cavity and covers most of the organs inside it.peri- aroundton stretched-eum a structureFull entry over the groin, places the mesh and closes the flap. In a TEP repair the surgeon stays outside the peritoneum, opening the space with a balloon dissector. The mesh is held with tacks, sutures or glue, and some surgeons leave it unfixed. The patient lies supine with arms tucked, in 20 to 30 degrees of Trendelenburg positiontren-DEL-en-burg puh-ZISH-unA position in which the client lies on the back with the bed tilted so the head is lower than the feet.Full entry , with the bladder empty. Most robotic inguinal repairs use the TAPP approach, with an anti-skid pad under the patient for the steep tilt. Laparoscopic repairs mean less pain and a quicker return to activity, though they recurrencerih-KER-ensThe return of a disease or symptom after a period when it had gone away.re- againcur run-ence state ofFull entry somewhat more often than open repairs.
Specimen: the sac, if removed. Counts: initial and closing, with the Penrose counted as a miscellaneous item. Dressing: strips, glue or a small flat dressing. Wound class: I.
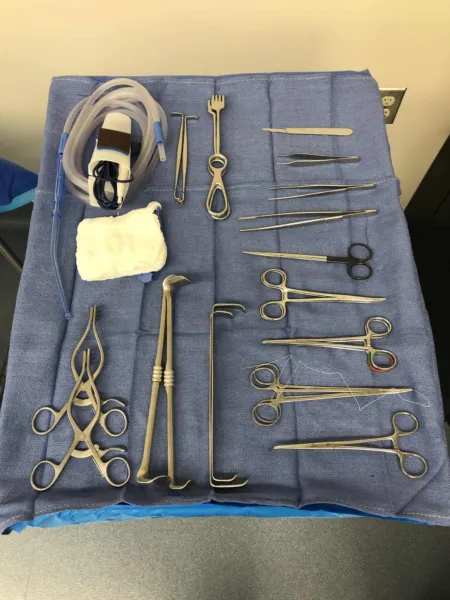
Femoral hernia
What and why: a femoral hernia comes through the femoral canal, below the inguinal ligament. The canal is the smallest, innermost compartment of the femoral sheath, bordered by the femoral vein on its outer side, the lacunar ligament on its inner side, the inguinal ligament in front and the pectineal ligament behind. The weak spot is the transversalis fascia below the inguinal ligament. About 5 percent of groin hernias are femoral; they are more common in women than in men and less common in children. Because they are far more likely than inguinal hernias to become incarcerated or strangulated, repair is always advised.
Approach, position, prep and drape: any inguinal method works: an open tissue or mesh repair, or a laparoscopic or robotic repair whose mesh covers the femoral opening along with the inguinal ones. The open repair goes through the same groin incision as an inguinal repair, so position, prep, drape and anesthesiaan-us-THEE-zhuhLoss of feeling or sensation, often brought on by drugs so that surgery or a procedure can be done without pain.an- withoutesthesi/o feeling, sensation-ia conditionFull entry match it, and a urinary catheter may be placed to keep the bladder empty.
Setup: the inguinal setup of a laparotomy set, a Penrose drain, mesh and local anesthetic, with a shaped 3-D mesh or a plug.
Key steps (open mesh repair): through an inguinal incision, the surgeon frees the femoral sac and pushes it back into the abdomen. A shaped piece of mesh is fitted over the femoral canal and sewn to the Cooper ligament, and the rest is laid along the floor of the inguinal canal, as in a Lichtenstein repair, and anchored with sutures. A mesh plug is another option.
Wound class: I when no bowel is opened. A strangulated hernia is an emergency, because the trapped tissue loses its blood supply and dies. If trapped bowel has died, a bowel resectionBOW-ul ree-SEK-shunSurgery to remove a section of the small or large intestine.Full entry follows, with bowel technique, and the case becomes at least Class II.
After surgery: the risks are those of an inguinal repair: recurrence, nerve injury and infection.
Umbilical and ventral hernia
An umbilical hernia comes through the umbilical ring in the linea alba. Most in young children close on their own by age 2; in adults they are more common with a high BMI, and their small necks make incarceration more likely. A ventralVEN-trulOn or toward the front, belly side of the body.ventr/o belly, front-al relating toFull entry hernia is a weakness in the front abdominal wall, and an incisional hernia forms at an old surgical incision.
Umbilical repair: supine. A curved incision just above or below the navel (or inside it) keeps the navel with the skin flap. The sac is freed from the back of the navel skin and pushed back. The fascial defect is closed with sutures, or bridged with a mesh plug or patch for a larger hole. The skin is closed with a buried stitch, and a small flat dressing goes on.
Open ventral or incisional repair: a wide prep; a laparotomy set. The surgeon lifts the old scar with Allis clamps and cuts it away (keep it as a specimen), removes old stitches, frees adhesionad-HEE-zhunA band of scar tissue that joins two surfaces inside the body that are normally separate.ad- towardhes stick-ion conditionFull entry and finds the fascia edges. Mesh is sewn or tacked across the defect. Mesh can lie on top of the fascia (onlay) or beneath the muscles (sublay): behind the rectus muscle, in the preperitoneal space, or inside the abdomen on the peritoneum (intraperitoneal). Behind the muscle or in the preperitoneal space carries the lowest risk of recurrence and infection. Large repairs may need suction drains.
In laparoscopic or robotic repairs, mesh inside the abdomen has a coated side that faces the bowel to prevent adhesions. It is fixed with sutures brought through the wall with a suture passer and with tacks.
Specimen: the sac or scar. Counts: initial, when closure of the peritoneum begins if it was opened, when closure of the fascia begins, and at skin closure. Wound class: I.
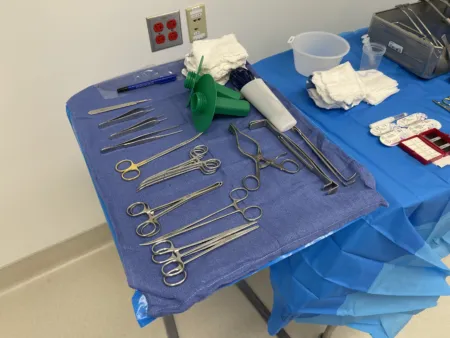
11Stomach and esophagus
The esophagusih-SOF-uh-gusThe muscular tube that carries food and liquid from the throat to the stomach.esophag/o esophagusFull entry , about 25 cm long in an adult, passes through the diaphragmDY-uh-framThe dome-shaped sheet of muscle under the lungs that is the main muscle of breathing; also the flat side of a stethoscope.Full entry to reach the stomach in the left upper abdomen. The stomach has three parts, the fundusFUN-dusThe rounded top or base of a hollow organ, most often the top of the uterus.Full entry at the top, the body and the antrum, with an opening at each end: the cardia, from the esophagus, and the pylorus, into the duodenumdoo-uh-DEE-numThe first, short part of the small intestine, just after the stomach.Full entry . The omentum hangs from its curves and has to be separated whenever part of the stomach is removed or reshaped. Chapter 7 has the full anatomy. These cases use a laparotomylap-uh-ROT-uh-meeSurgery that opens the abdomen through a large cut to reach the organs inside.lapar/o abdomen-tomy cutting intoFull entry or laparoscopylap-uh-ROS-kuh-peeSurgery or an exam done through small cuts in the belly, using a thin, lighted tube with a camera.lapar/o abdomen-scopy looking with an instrumentFull entry set with atraumatic GI clamps, long instruments for large patients, and staplers.
Hiatal hernia and Nissen fundoplication
What and why: the esophageal hiatus is the opening in the diaphragm for the esophagus, and a membrane normally anchors the junction of esophagus and stomach there. In a type I, or sliding, hiatal herniaHER-nee-uhA bulge of an organ or tissue through a weak spot in the muscle or tissue wall that normally holds it in.Full entry , the hiatus widens and the junction slides up into the chest, which often leads to gastroesophageal reflux diseasegas-troh-ih-sof-uh-JEE-ul REE-fluks dih-ZEEZA long-term condition in which stomach contents, including acid, flow back up into the esophagus.gastr/o stomachesophag/o esophagus-al relating toFull entry (GERD). Types II to IV, the paraesophageal hernias, have a true hernia sac: the fundus rolls up beside the esophagus, then the junction follows it, and finally other organs such as the colon or spleenspleenAn organ in the upper left abdomen that filters the blood and helps fight infection.splen/o spleenFull entry join them. A paraesophageal hernia can inflame the stomach lining (gastritisgas-TRY-tisInflammation of the lining of the stomach.gastr/o stomach-itis inflammationFull entry ) or ulcerate it, twist and strangulate the stomach, block its outlet or bleed.
In GERD the lower esophageal sphincterSFINGK-terA ring of muscle that tightens to close an opening or passage in the body and relaxes to open it.Full entry loses its tone and stomach acid washes up and erodes the lining, causing heartburn, regurgitationrih-gur-jih-TAY-shunA flowing backward: blood leaking back through a heart valve, or stomach contents coming back up into the mouth.Full entry , chest pain and trouble swallowing; over time it can lead to cancer. A fundoplication (fundus plus plication, a fold) wraps the top of the stomach around the lower esophagus so that it works as a valve. A Nissen wraps all the way around, 360 degrees; a Toupet wraps 270 degrees from behind, and a Dor 180 degrees in front. A hiatal hernia found at the same time is repaired in the same operation.
Diagnosis: EGDee-jee-DEE (said as letters)Esophagogastroduodenoscopy: a test using a flexible scope through the mouth to look at the esophagus, stomach and start of the small intestine.esophag/o esophagusgastr/o stomachduoden/o duodenum-scopy looking, viewingFull entry , a barium swallow, 24-hour pH monitoring and esophageal manometry. Changes in diet and weight and drugs such as antacidant-AS-idA drug that neutralizes stomach acid to relieve heartburn and indigestion.Full entry , histamineHIS-tuh-meenA chemical released by certain immune cells that widens blood vessels, makes them leaky and tightens airway muscles.hist/o tissue-amine a type of nitrogen-containing chemicalFull entry blockerBLOK-erA drug that stops a receptor or channel in the body from being activated, so the usual effect does not happen.Full entry and proton pump inhibitorPROH-ton pump in-HIB-ih-terA drug that strongly lowers the amount of acid the stomach makes.Full entry come first; surgery follows when they fail.
Position, prep and drape: supine, or in low lithotomylih-THOT-uh-meeA position lying on the back with the hips and knees bent and the legs raised and spread apart, often in stirrups.lith/o stone-tomy cutting intoFull entry with the surgeon between the legs, in reverse Trendelenburg positionree-VERS tren-DEL-un-burg puh-ZISH-unA position lying on the back on a bed or table that is tilted so the head is higher than the feet, with the body kept straight.Full entry of about 20 degrees. The prep runs from the nipple line to the pubisPYOO-bisThe front part of each hip bone, low in the pelvis; the two meet in the middle at the pubic symphysis.pub/o pubisFull entry . An nasogastric tubenay-zoh-GAS-trik toobA thin, flexible tube passed through the nose and down the esophagus into the stomach.nas/o nosegastr/o stomach-ic having to do withFull entry is placed if the stomach needs emptying, and a urinary catheter often is.
Setup: a laparoscopy set with a 30-degree scope, two 10 mm and two 5 mm trocarTROH-karA sharp or bladed instrument inside a tube (cannula), used to pierce a body wall and leave the tube in place as a port.Full entry , a fan liver retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry , Babcock graspers, clip appliers, ultrasonic shears, a laparoscopiclap-uh-roh-SKOP-ikDone through a few small cuts in the abdomen with a thin camera and long instruments, instead of one large opening.lapar/o abdomen-scopic viewingFull entry needle holder and knot pusher, nonabsorbable sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry and a Penrose drain. Extra-long instruments and an extra 10 mm trocar are added for an obese patient, and a laparotomy set stays ready in case the case converts.

Esophageal dilatorDY-lay-terAn instrument used to stretch or widen an opening, canal or passage in the body.Full entry : the anesthesia provideran-us-THEE-zhuh pruh-VY-derThe licensed professional who gives anesthesia and watches over the client's breathing and vital functions during a procedure.Full entry passes bougie or Maloney dilators, 32 F to 60 F, down the esophagus during the case, so they are laid out in order of size on a nonsterile table with water-soluble lubricant; they are never passed from the sterile fieldSTAIR-ul feeldAn area set up with sterile drapes and supplies, kept free of all germs, for a sterile procedure.Full entry . Dilators carry expiration dates, so check them ahead of time.

Key steps:
- The ports go in, and a fan retractor lifts the left lobe of the liver to show the hiatus.
- A Babcock on the fundus pulls the stomach down. The surgeon finds the crura, the two muscular pillars of the hiatus, opens a window behind the esophagus and loops a Penrose drain around it for tractionTRAK-shunA steady pulling force applied to a body part with weights, ropes and pulleys.Full entry .
- The fundus is freed by dividing the short gastric vessels with clips or ultrasonic shears.
- For a paraesophageal hernia, the sac is reduced and cut away, and the stomach is drawn back into the abdomen along with at least 2.5 to 3 cm of the lower esophagus.
- The anesthesia provider passes a large dilator, 56 F to 60 F, in step with the surgeon, who holds the stomach at an angle that lets it pass without a perforationper-fuh-RAY-shunA hole that goes all the way through the wall of an organ or tissue.per- throughforat bored (a hole)-ion processFull entry . The crura are sewn together behind the esophagus while the dilator acts as a stentstentA small tube, often of metal mesh, placed inside a vessel or duct to hold it open.Full entry , so the closure is not too tight; a very large defect may be reinforceree-in-FORSTo repeat and support teaching or care that has already been started, so the client remembers and follows it.Full entry with biologic mesh.
- The fundus is passed behind the esophagus, wrapped around it and sewn to itself over the dilator. The dilator then comes out, and an NG tube may take its place.
- Bleeding is checked, the ports come out and the incisions are closed.
Wound class: I, because the GI tract is not opened.
After surgery: most patients go home the same day. Complications include a hole in the esophagus or stomach, injury to the pleuralPLOOR-ulHaving to do with the pleura, the thin two-layer membrane that covers the lungs and lines the chest wall.pleur/o pleura-al relating toFull entry , trouble swallowing, death of the wrap, pneumonianoo-MOHN-yuhAn infection of one or both lungs in which the air sacs fill with fluid or pus.pneum/o lung, air-ia conditionFull entry , bleeding, infection and symptoms that do not improve.
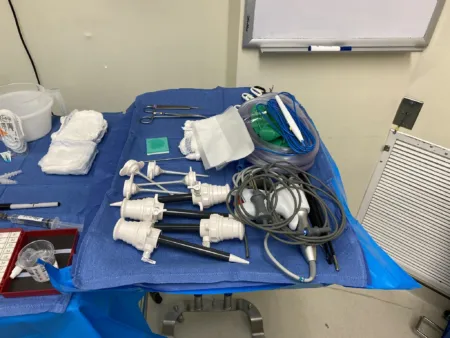
Gastrectomy and gastrostomy
What and why: a gastrectomy removes part or all of the stomach. A partial (distal) gastrectomy treats stomach cancer and ulcerUL-serAn open sore where the skin or the lining of an organ has broken down.Full entry disease that bleeds, perforates or blocks the outlet; such ulcers are commonly caused by H. pylori bacteria and long-term use of anti-inflammatory drugs (nonsteroidal anti-inflammatory drugnon-STAIR-oy-dul an-tee-in-FLAM-uh-tor-ee DRUGA drug that relieves pain, fever and inflammation and is not a steroid, such as ibuprofen or naproxen.non- notanti- againstinflamm/o inflammationFull entry ). A Billroth I joins the remaining stomach to the duodenum (a gastroduodenostomy); a Billroth II closes the end of the duodenum and joins the stomach to the jejunumjeh-JOO-numThe second of the three sections of the small intestine; it follows the duodenum and leads into the ileum.jejun/o jejunum (from the Latin for empty)Full entry (a gastrojejunostomy). The Billroth II is chosen when the disease reaches above the antrum or the duodenum is scarred. A total gastrectomy, for cancer or for bleeding nothing else will stop, is rebuilt with a Roux-en-Y loop of jejunum joined to the esophagus. A gastrectomy may add a vagotomy (cutting the vagus nerveVAY-gus nervThe 10th cranial nerve, which runs from the brain stem to the chest and belly and slows the heart and helps digestion.Full entry ) or a lymph nodelimf nohdA small, bean-shaped organ of the immune system that filters lymph fluid and holds white blood cells.Full entry dissectiondy-SEK-shunA tear in the inner layer of an artery wall that lets blood split the layers apart; also, the cutting apart of tissue in surgery.Full entry , and it is now nearly always done laparoscopically or robotically, with open surgery kept for some cases.
Diagnosis: a full endoscopyen-DOS-kuh-peeA procedure that uses a thin, flexible tube with a light and camera to look inside the body.endo- within-scopy looking with an instrumentFull entry with endoscopicen-doh-SKOP-ikDone with an endoscope, a thin tube with a light and camera passed into the body.endo- within-scopic viewingFull entry ultrasound sizes up the disease before surgery, and biopsy confirms or rules out cancer.
Position, prep and drape: supine or in low lithotomy; an upper midlineMID-lineAn imaginary line down the center of the body; also, a type of IV catheter placed in a vein of the upper arm.Full entry incision for open surgery; an abdominal prep and a laparotomy drape. An NG tube and a urinary catheter are placed, with steps to prevent deep vein thrombosisDEEP VAYN throm-BOH-sisA blood clot in a deep vein, most often in the leg or pelvis.thromb/o clot-osis conditionFull entry , hypothermiahy-poh-THER-mee-uhA body temperature that has fallen below the normal range.hypo- belowtherm/o heat-ia conditionFull entry and pressure injuryPRESH-er IN-juh-reeDamage to the skin and the tissue beneath it from pressure, or pressure with shear, usually over a bony area or under a device.Full entry .
Setup: a laparotomy set with GI instruments, long instruments, a self-retaining retractor, clip appliers and a fine right angle, plus linear cutting and circular staplers in several sizes, vessel loops and a drain. Have plenty of hemostatHEE-moe-statA clamp with finger rings and a locking ratchet used in surgery to grasp and close off bleeding vessels.hem/o blood-stat stopping, standing stillFull entry (Mayo, Crile or Kelly), clips and ties, and suture ligatures for the large gastric vessels.
Key steps:
- The surgeon explores the abdomen and sets the lines of resectionrih-SEK-shunSurgery to remove part of an organ or tissue.re- back, againsect to cut-ion processFull entry .
- The omentum is freed from both curves of the stomach between clamps or with an energy device, and the large vessels are clipped. Label any lymph nodes removed now at once and pass them off.
- Intestinal clamps (Kocher or Allen type) go across the duodenum for a Billroth I or the jejunum for a Billroth II. The bowel is cut between them, the stump is stapled or sewn shut, and the stomach is divided.
- The anastomosisuh-nas-tuh-MOH-sisA connection between two tube-shaped structures, such as two ends of bowel or two blood vessels, made by surgery or found naturally.Full entry , the new join between stomach and bowel, is stapled with GIA and TA staplers or sewn in two layers. Bowel technique is followed, and a second setup for the closure helps. The team changes gloves (and often gowns) and closes with clean instruments.
- A gastric tube may be brought out through the abdominal wall, drains are placed, and the abdomen is closed and covered with a flat dressing and an ABD pad.
Wound class: II.
After surgery: complications include bleeding, infection and a failed anastomosis, and diet is the patient's biggest adjustment.
Gastrostomy: a surgical opening from the stomach to the skin, used to feed the patient or to drain and decompress the stomach. Common reasons are tumors of the throat, larynxLAIR-inksThe voice box: the part of the airway in the neck, above the windpipe, that holds the vocal cords.laryng/o larynxFull entry , esophagus or upper stomach and narrowing of the esophagus. It can be made open, endoscopically through the skin or laparoscopically, and it may be added to a gastrectomy.
- Open (Stamm) gastrostomy: supine, prepped from mid-chest to mid-thigh, with a minor set. Through an upper midline incision the surgeon lifts the stomach with a Babcock, makes a small hole and inserts a 20 to 26 French indwelling urinary catheterin-DWEL-ing YUR-ih-nair-ee KATH-uh-terA tube passed through the urethra into the bladder and left in place to drain urine into a bag.Full entry , Malecot or Pezzer catheter, held by two purse-string sutures. The tube leaves through a stab wound in the left upper abdomen, and the stomach is sewn to the abdominal wall. Have several tubes ready but open none until the surgeon chooses, and keep suction ready in case stomach contents spill.
- Percutaneous endoscopic gastrostomy (PEGPEG, or pee-ee-JEE (said as letters)An abbreviation that can mean a feeding tube placed through the belly into the stomach, or the laxative polyethylene glycol.Full entry ): a enteral feeding tubeEN-ter-ul FEE-ding toobA tube placed into the stomach or small intestine to give liquid food, water and drugs to a person who cannot eat enough by mouth.Full entry placed through the skin into the stomach under endoscopic view, for a patient who cannot eat but whose GI tract works. A prepackaged kit holds a #11 blade, a trocar needle, a long suture or guidewire, the tube and a skin disk, and a gastroscopy setup with a snare is needed too. The patient is supine, the abdomen is prepped and antibiotics are given before the start. In the pull method, the scope inflates the stomach and its light shines through the abdominal wall, showing that nothing lies between stomach and skin; after local anestheticLOH-kul an-es-THET-ikA drug that blocks feeling in one part of the body without making the person unconscious.Full entry and a stab wound, a needle enters the stomach, and a suture or wire passed through it is caught in the snare and drawn out of the mouth with the scope. The tube is attached to it and pulled down the esophagus until it comes out through the stab wound; the scope goes back in to check its position, and a skin disk secures it.
- Wound class and complications: Class II, because the stomach is opened; bleeding, infection, skin erosion and leaking are the main risks.

Weight-loss surgery
What and why: bariatric (weight-loss) surgery treats obesity, which is defined by the body mass index (BMI). Morbid obesity means a BMI of 40 or more, with the person at least 100 pounds (45 kg) over ideal weight despite serious attempts to lose it. Patients usually qualify with a BMI of 40 or more, or 35 or more with a related disease such as type 2 diabetestipe too dy-uh-BEE-teezA form of diabetes in which the body does not respond well to insulin and does not make enough of it to keep blood glucose normal.Full entry , high blood pressure, high blood fats or sleep apneasleep AP-nee-uhA sleep disorder in which breathing stops and starts again and again during sleep.Full entry . They are screened for commitment, freedom from alcohol and tobacco and psychological readiness, and usually must try other weight-loss measures first. Restrictive operations make the stomach smaller; malabsorptive ones bypass part of the small bowel; some do both.
Positioning and equipment safety: these patients often have diabetes, heart and lung disease, sleep apnea and a difficult airway, so expect the anesthesia provider to need extra help with endotracheal intubationen-doh-TRAY-kee-ul in-too-BAY-shunPutting a breathing tube through the mouth or nose into the windpipe (trachea).endo- withintrache/o windpipe-al relating toFull entry . Check that the bed is rated for the patient's weight in the position it will be used in, with extensions fitted correctly and well padded. An anti-skid pad or vacuum positioner keeps the patient from sliding during a steep tilt; add padded safety straps, pressure-reducing devices and compression devices that fit. Plan the transfer: a bariatric gurney and table, slide sheets or a lift, and enough people to protect the patient and the staff. Have extra-large blood pressure cuffs, extra-long trocars and long instruments.
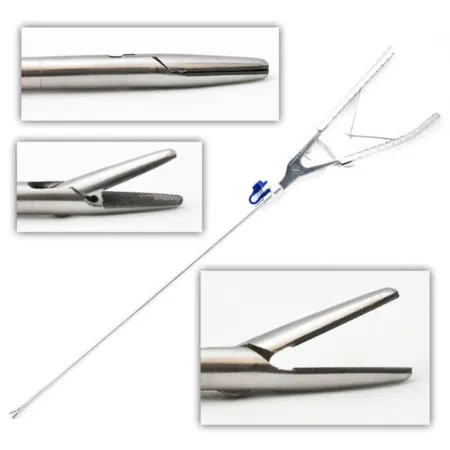
Medications: heparinHEP-uh-rinAn anticoagulant drug, given by injection or IV, that keeps blood clots from forming or growing.Full entry is given under the skin before surgery, along with compression boots, because the risk of DVT is high. Methylene blue may be instilled to test a new connection for leaks.
Adjustable gastric band: a silicone band with an inflatable inner balloon goes around the top of the stomach to make a small pouch; its tubing runs to a port under the skin, where saline is added or removed to tighten or loosen it. The operation is called a band gastroplasty; it causes no malabsorption and can be reversed. The patient lies in low lithotomy with the surgeon between the legs, secured for reverse Trendelenburg, often on a beanbag positioner. You test the band for leaks and flush it with saline, leave 5 mL in the band and tubing, clamp the tubing, and dip the band in saline before passing it. The surgeon tunnels it behind the stomach and locks it once the anesthesia provider has placed a balloon-tipped gastric tube at the junction of the esophagus and stomach; the stomach is then folded over the band and tacked with nonabsorbable sutures, and the port is sewn to the fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry . The band is filled about 4 weeks later and adjusted under fluoroscopyfloo-ROS-kuh-peeAn x-ray method that shows moving pictures of the inside of the body in real time.fluor/o glowing (from the fluorescent screen)-scopy looking, viewingFull entry several times in the first year. Erosion, slipping, port infection and a disconnected tube are typical problems.
Sleeve gastrectomy: staplers reduce the stomach by 70 to 90 percent, and the removed part comes out through a port and goes to pathologypuh-THOL-uh-jeeThe study of disease and its causes and effects, or the disease changes found in a person or tissue.path/o disease-logy study ofFull entry as facility policy requires. Both parts are checked for a complete separation with no defects before closing. Leaks, a narrowed outlet and bleeding from the staple line, the short gastric vessels or the spleen are the main risks.
Roux-en-Y gastric bypass: it bypasses most of the stomach. A small pouch, usually under 30 mL, is stapled off the top of the stomach and joined to a divided limb of jejunum (the Roux limb), and the other cut end of the jejunum is joined farther down so the stomach's secretionsih-KREE-shunA substance a gland or cell makes and releases, such as mucus, saliva, sweat or a hormone.Full entry still reach the intestine. The patient is supine or in low lithotomy with leggings. The setup adds extra-long laparoscopic instruments, a flexible or fan liver retractor, a 30-degree scope, 12 mm ports, an optical trocar or Veress needle, and endoscopic linear staplers. In order: five ports above the umbilicus plus one for the liver retractor; the jejunum divided about 40 cm past the ligament of Treitz; the pouch stapled and sized with a 32 French bougie or a balloon passed by the anesthesia provider; the Roux limb joined to the pouch with staplers, sutures or a circular stapler and tested with methylene blue; and the gaps in the mesentery closed. Weight comes off faster than with a band. The risks include bleeding, leaks, pulmonary embolismPUL-muh-nair-ee EM-buh-liz-umA blockage of an artery in the lungs, usually by a blood clot that has traveled there from elsewhere in the body.pulmon/o lung-ary relating toembol/o plug-ism conditionFull entry , pneumonia, infection, bowel obstructionBOW-ul ub-STRUK-shunA partial or complete blockage that stops food, fluid and gas from moving through the small or large bowel.Full entry , internal or incisional hernia, ulcers at the new connection, gallstones, dumping syndrome and vitamin deficiency.

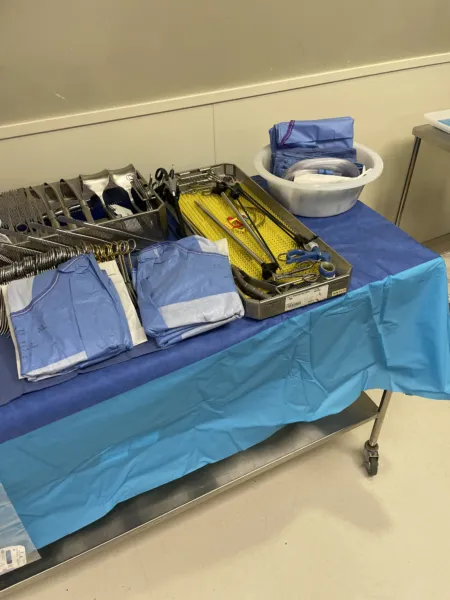
Wound class: II for the bypass and the sleeve, because the stomach is opened; I for a band, which does not open it.
After surgery: reverse Trendelenburg helps the patient breathe, most patients without breathing problems can be extubated in the OR or PACU, and walking early helps prevent clots. Obese patients run higher risks of wound infection, wound separation, pulmonary embolism, breathing failure and anastomotic leaks.
12Bowel resection and anastomosis
A bowel resectionBOW-ul ree-SEK-shunSurgery to remove a section of the small or large intestine.Full entry removes diseased intestine: cancer, polypPOL-ipA growth that sticks out from the lining of a hollow organ, such as the colon, nose or uterus.Full entry , diverticulitisdy-ver-tik-yuh-LY-tisInflammation or infection of one or more small pouches that bulge out from the wall of the colon.diverticul/o a small pouch-itis inflammationFull entry , Crohn diseasekrohn dih-ZEEZA long-term inflammatory bowel disease that can affect any part of the digestive tract, through the full thickness of its wall.Full entry or ulcerative colitisUL-ser-uh-tiv koh-LY-tisA long-term inflammatory bowel disease that affects the inner lining of the colon and rectum.ulcer sorecol/o colon-itis inflammationFull entry , a blockage, a twist of the bowel (volvulus), an injury, or bowel that has lost its blood supply. The ends are joined (an anastomosisuh-nas-tuh-MOH-sisA connection between two tube-shaped structures, such as two ends of bowel or two blood vessels, made by surgery or found naturally.Full entry ), or one end is brought to the skin as a stomaSTOH-muhAn opening on the surface of the body made by surgery, such as the end of bowel brought out through the belly wall.stoma mouth, openingFull entry when joining them is not safe. The model case is the open right hemicolectomy. It removes the end of the ileumIL-ee-umThe last and longest part of the small intestine, which joins the large intestine.Full entry , the cecum, the ascending colon and part of the transversetrans-VERSLying across something, at a right angle to its length.Full entry colon, for disease of the cecum, ascending colon or hepatichih-PAT-ikRelating to the liver.hepat/o liver-ic relating toFull entry flexure. The same steps apply to other bowel resections, open or minimally invasive.
Open right hemicolectomy
pathologypuh-THOL-uh-jeeThe study of disease and its causes and effects, or the disease changes found in a person or tissue.path/o disease-logy study ofFull entry : the reasons include inflammatory disease (Crohn disease, diverticulitis, ulcerative colitis); a blockage from fecal impaction, intussusceptionin-tuh-suh-SEP-shunA condition in which one part of the intestine slides into the part next to it, like a telescope.intus withinsuscept to take upFull entry , an adhesionad-HEE-zhunA band of scar tissue that joins two surfaces inside the body that are normally separate.ad- towardhes stick-ion conditionFull entry band, a tumor or a volvulus; polyps; pseudomembranous enterocolitis; blunt or penetrating trauma; and vascular disease, such as an arteriovenousar-teer-ee-oh-VEE-nusRelating to both arteries and veins, or joining an artery to a vein.arteri/o arteryven/o vein-ous relating toFull entry malformationmal-for-MAY-shunA body part or organ that formed in an abnormal way before birth.mal- badformation shapingFull entry , ischemiais-KEE-mee-uhToo little blood flow to a part of the body, so the tissue does not get enough oxygen.isch- hold back-emia blood conditionFull entry colitiskoh-LY-tisInflammation of the colon, the large intestine.col/o colon-itis inflammationFull entry or a blocked vessel. Polyps may be benign or malignant, and they grow on a stalk (pedunculated) or sit on the wall with no stalk (sessile); the types include polypoid and villous adenomaad-uh-NOH-muhA tumor of gland tissue that is not cancer.aden/o gland-oma tumorFull entry , mucousMYOO-kusRelating to mucus or making mucus, as in mucous membrane.Full entry polyps, pseudopolyps and familial polyposis. Coexisting conditions to note include coronary artery diseaseKOR-uh-nair-ee AR-tuh-ree dih-ZEEZNarrowing of the arteries that supply blood to the heart muscle, most often from fatty plaque buildup.Full entry , high cholesterol, high blood pressure and smoking.
Diagnosis: colonoscopykoh-luh-NOS-kuh-peeAn exam of the inside of the large intestine with a long, flexible tube that has a camera on its end.col/o colon-scopy looking with an instrumentFull entry , computed tomographykum-PYOO-tid toh-MOG-ruh-feeAn imaging test that uses x-rays and a computer to make cross-section pictures of the inside of the body.tom/o cut, slice-graphy process of recordingFull entry , a barium enemaEN-uh-muhLiquid put into the rectum and lower bowel through the anus.Full entry , a chest X-ray and an intravenous pyelogram (IVPeye-vee-PEE (said as letters)An abbreviation with more than one meaning, most often IV push or intravenous pyelogram.Full entry ), with blood tests such as the carcinoembryonic antigenkar-sin-oh-em-bree-ON-ik AN-tih-jenA protein measured in the blood as a tumor marker, mainly to follow colorectal cancer.Full entry tumor markerMAR-kerSomething that can be measured, such as a substance in the blood, that shows a disease or body process is present.Full entry , electrolytes and clottingKLOT-ingThe process by which blood thickens into a gel to plug a damaged vessel and stop bleeding; also called coagulation.Full entry times, and a test for hidden blood in the stool.
anesthesiaan-us-THEE-zhuhLoss of feeling or sensation, often brought on by drugs so that surgery or a procedure can be done without pain.an- withoutesthesi/o feeling, sensation-ia conditionFull entry and position: general anesthesiaJEN-er-ul an-es-THEE-zhuhDrug-induced loss of consciousness and feeling over the whole body, so a person feels nothing and is not aware during surgery.an- withoutesthesi/o feeling, sensation-ia conditionFull entry , and an epidural anesthesiaep-ih-DOOR-ul an-us-THEE-zhuhPain relief or numbness from an anesthetic drug given through a thin catheter into the space just outside the covering of the spinal cord.epi- upon, overdur/o dura (the tough covering of the spinal cord)-al relating toFull entry may be added for pain control; supine, arms on armboards, with a safety strap. Low lithotomylih-THOT-uh-meeA position lying on the back with the hips and knees bent and the legs raised and spread apart, often in stirrups.lith/o stone-tomy cutting intoFull entry is used when a circular stapler must pass through the anus. A nasogastric tubenay-zoh-GAS-trik toobA thin, flexible tube passed through the nose and down the esophagus into the stomach.nas/o nosegastr/o stomach-ic having to do withFull entry and a urinary catheter are usually placed. Monitoring covers depth of anesthesia (BIS), exhaled carbon dioxideKAR-bun dy-OK-sideA gas made by the body's cells as waste, carried in the blood to the lungs and breathed out.Full entry (capnography), blood pressure, heart rate, saturationsach-uh-RAY-shunHow full something is; in nursing, usually the percentage of hemoglobin in the blood that is carrying oxygen.Full entry , breathing, temperature and urine output, with steps to prevent deep vein thrombosisDEEP VAYN throm-BOH-sisA blood clot in a deep vein, most often in the leg or pelvis.thromb/o clot-osis conditionFull entry .
Prep and drape: the abdomen, with any stoma site marked before surgery, if possible with the patient standing; towels and a laparotomylap-uh-ROT-uh-meeSurgery that opens the abdomen through a large cut to reach the organs inside.lapar/o abdomen-tomy cutting intoFull entry sheet.
Setup: major laparotomy and GI trays, long instruments, a self-retaining retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry , an energy device (electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry , ultrasonic shears or vessel sealer), GIA and TA staplers with reloads, clips, Poole and Yankauer suction, a dirty setup, and a separate clean closing setup such as a minor laparotomy tray. Keep an extra Poole tip clean for the final irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry .
Key steps:
- The surgeon opens the abdomen through a midlineMID-lineAn imaginary line down the center of the body; also, a type of IV catheter placed in a vein of the upper arm.Full entry or paramedian incision, explores it and confirms the extent of the disease. A self-retaining retractor, padded with moist laps, holds the wound open.
- The colon is freed from the side wall while the surgeon protects the right ureterYOOR-uh-terOne of the two tubes that carry urine from the kidneys down to the bladder.Full entry and the duodenumdoo-uh-DEE-numThe first, short part of the small intestine, just after the stomach.Full entry . The surgeon runs the colon by hand to choose where to cut and where to join.
- The mesentery and its vessels are divided: clamp, cut and tie, a vessel sealer or a stapler. Pass clamps in pairs, with ties right behind.
- The bowel is divided, usually with a GIA stapler, or between clamps: noncrushing bowel clamps on the side that stays and crushing clamps on the specimen side. The specimen passes off the field, and bowel technique starts once a lumenLOO-menThe open space inside a tube, such as a blood vessel, the intestine or a catheter.Full entry is open.
- Anastomosis. Stapled: the stapled ends lie side by side, a corner of each is cut off, one fork of the GIA goes into each limb and fires, and the leftover opening is held with Allis clamps, closed with a TA stapler and the extra trimmed. Hand-sewn: two layers, an inner running absorbable stitch and an outer layer of interrupted stitches through the serosa. A count is done before the anastomosis is finished.
- The gap in the mesentery is closed and the abdomen irrigated with warm saline.
- Bowel technique ends: dirty items out, fresh gloves (and often gowns) and drapes, and closure with clean instruments.
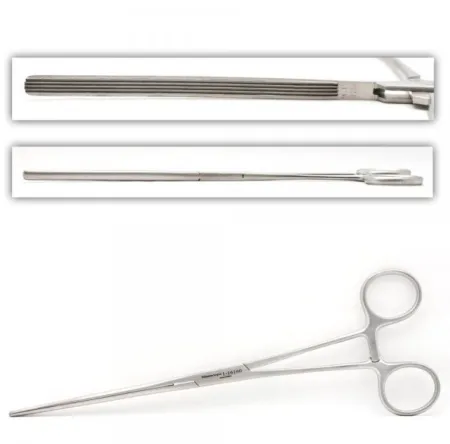
Specimen: the bowel segment, which may go for frozen section as well as permanent section. Counts: initial, at peritoneumpair-ih-toh-NEE-umThe thin membrane that lines the belly cavity and covers most of the organs inside it.peri- aroundton stretched-eum a structureFull entry closure and at subcutaneoussub-kyoo-TAY-nee-usUnder the skin; in the fatty layer between the skin and the muscle.sub- undercutane/o skin-ous relating toFull entry or skin closure, plus a count before the anastomosis is finished; anything added, including the clean closing setup, is counted. Drains: a urinary catheter, and sometimes a closed suction drain. Dressing: an ABD or island dressing with gauze, and the stoma appliance. Wound class: II with controlled spillage, III with uncontrolled spillage, IV with infection already present. After surgery: PACU or ICU. Complications include a leaking anastomosis, bleeding, DVT, bowel that loses its blood supply, wound infection, short bowel (short-gut) syndrome and death. The outlook depends on whether a cancer is still local or has spread to the mesentery or to distant tissues.
Small bowel resection
What and why: a small bowel resectionrih-SEK-shunSurgery to remove part of an organ or tissue.re- back, againsect to cut-ion processFull entry removes a diseased, blocked or dead segment of small intestine and joins the healthy ends. It is a co-related procedure, done much like a colon resection. The small intestine has three parts, the duodenum (20 to 25 cm), the jejunumjeh-JOO-numThe second of the three sections of the small intestine; it follows the duodenum and leads into the ileum.jejun/o jejunum (from the Latin for empty)Full entry (about 0.9 m) and the ileum (about 1.8 m), hung from the mesentery, which must be divided from any segment that comes out. Those are lengths in a living person, where muscle tone keeps the whole small intestine at about 3 m; without that tone, after death, it measures about twice as long. Some references give longer figures for the parts, a jejunum of about 2.7 m and an ileum of about 4 m. The usual reasons are obstruction, inflammatory disease such as Crohn disease, and cancer. A blockage may come from bowel trapped in a herniaHER-nee-uhA bulge of an organ or tissue through a weak spot in the muscle or tissue wall that normally holds it in.Full entry , a twist (volvulus), one segment telescoping into the next (intussusception, mostly in children) or bowel that stops moving after surgery (paralytic ileuspair-uh-LIT-ik IL-ee-usA stop in the normal movement of the intestines that happens without anything physically blocking them.paraly loosening, disabling-ic relating toFull entry ); left alone, it can lead to perforationper-fuh-RAY-shunA hole that goes all the way through the wall of an organ or tissue.per- throughforat bored (a hole)-ion processFull entry , dead bowel and peritonitispair-ih-tuh-NY-tisInflammation of the peritoneum, the thin membrane that lines the inside of the belly and covers the organs there.peritone/o peritoneum-itis inflammationFull entry . A Meckel diverticulum, a pouch on the lower ileum left over from before birth, is another reason: it can block and strangulate the bowel, become inflamed much like an appendixuh-PEN-diksA small, finger-shaped pouch attached to the first part of the large intestine, in the lower right abdomen.Full entry , or bleed.
Diagnosis: a GI contrastKON-trastA dye or other substance given before an imaging test so body parts show up more clearly.Full entry series, barium studies and CT.
Position, prep and drape: supine under general anesthesia, with an NG tube and a urinary catheter; a midline or paramedian incision; an abdominal prep and a laparotomy drape.
Setup: a major laparotomy set with intestinal instruments, vascular forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry , vessel loops, clips and GI linear staplers in several sizes, with a Penrose drain on hold and laparoscopiclap-uh-roh-SKOP-ikDone through a few small cuts in the abdomen with a thin camera and long instruments, instead of one large opening.lapar/o abdomen-scopic viewingFull entry equipment if the case is minimally invasive.
Medications: the prophylaxisproh-fuh-LAK-sisTreatment given to prevent a disease or problem, rather than to treat one that is already present.pro- beforephylax guardFull entry antibiotic is chosen for the germs of the small bowel; cephalosporinsef-uh-loh-SPOR-inA large group of antibiotics related to penicillin that kill bacteria by damaging their cell walls.Full entry are common for clean-contaminated cases.
Key steps: the surgeon opens and explores the abdomen, protects the wound edges with moist laps or a wound protector and places a self-retaining retractor. Small windows in the mesentery at each end of the diseased segment let a linear stapler fire across the bowel. The segment is freed from its mesentery with clamps and ties, a vessel sealer or ultrasonic shears. The ends are joined end to end, side to side or end to side, stapled or sewn in two layers, and the gap in the mesentery is closed. Bowel technique applies, and the wound is irrigated and closed in layers.
Wound class and after surgery: as for a colon resection: II with controlled spillage, III with gross spillage, IV with a perforation or infection already present. Bleeding, infection, a leaking anastomosis and obstruction from adhesions are the main risks.
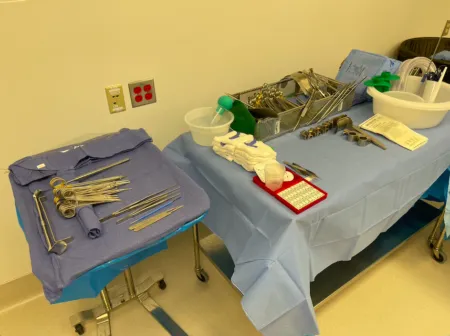
Low anterior resection
What and why: colon resections are named for the part removed: a right hemicolectomy, a transverse colectomykoh-LEK-tuh-meeSurgery to remove all or part of the colon.col/o colon-ectomy surgical removalFull entry , a left hemicolectomy, a low anterior resection, or an abdominoperineal resection, which takes the rectum and anus and leaves a permanent colostomykuh-LOS-tuh-meeA surgical opening that brings part of the colon through the belly wall, so stool leaves the body into a pouch.col/o colon-stomy surgical openingFull entry . The supplies are the same for all of them.
A low anterior resection removes the lower sigmoidSIG-moydShaped like the letter S; most often short for the sigmoid colon, the S-shaped last part of the colon before the rectum.Full entry colon and the upper rectum, for cancer there or for inflammatory bowel diseasein-FLAM-uh-tor-ee BOW-ul dih-ZEEZA group of long-term diseases, mainly Crohn disease and ulcerative colitis, in which the lining of the digestive tract becomes inflamed.Full entry ; the colon is joined to the rectum if the lower margin is free of cancer and enough length remains. The anal sphincterSFINGK-terA ring of muscle that tightens to close an opening or passage in the body and relaxes to open it.Full entry stays. It may be done open, laparoscopically or with the robot: the anatomy and the disease are the same, and what differs is mostly the equipment and instruments.
Diagnosis and preparation: colonoscopy finds the lesionLEE-zhunAn area of tissue that has been damaged or has changed from normal, such as a sore, wound, lump or spot.Full entry and often tattoos it, with the workup described for the hemicolectomy. An elective colon resection or low anterior resection also needs a bowel prep the day before: enemas and cathartics to empty the colon, then oral antibiotics that the gut does not absorptionub-ZORP-shunThe taking in of a substance, such as a drug or a nutrient, into the bloodstream.Full entry , to cut down the live germs. A urologist may first place ureteral stentstentA small tube, often of metal mesh, placed inside a vessel or duct to hold it open.Full entry , which help the surgeon find the ureters.
Position, prep and drape (robotic): modified lithotomy on a vacuum mattress, so the table can tilt to the side in Trendelenburg positiontren-DEL-en-burg puh-ZISH-unA position in which the client lies on the back with the bed tilted so the head is lower than the feet.Full entry safely; both arms tucked; a prep from the nipple line to the pubisPYOO-bisThe front part of each hip bone, low in the pelvis; the two meet in the middle at the pubic symphysis.pub/o pubisFull entry ; laparotomy drapes with pockets.
Setup: for the robot, 30-degree and 0-degree scopes, a robotic stapler, an ultrasonic vessel sealer, a monopolar hook and scissors, bipolarby-POH-lerHaving two poles or two opposite ends; most often used as a short form of bipolar disorder.bi- twopolar having polesFull entry forceps, a 12 mm stapler cannulaKAN-yoo-luhA thin tube placed into the body or a body opening to deliver or remove fluid or air.Full entry and a suction-irrigator. For an open case, laparotomy and GI sets, linear and circular (EEA) staplers with EEA sizers, long pelvic instruments and a rigid sigmoidoscope. A separate small table holds the rectalREK-tulRelating to the rectum, the last part of the large intestine; also, given or measured through the rectum.rect/o rectum, straight-al relating toFull entry instruments, the sigmoidoscope and the circular stapler for the part done through the anus, and another may hold the closing instruments.

Medications: the anesthesia provideran-us-THEE-zhuh pruh-VY-derThe licensed professional who gives anesthesia and watches over the client's breathing and vital functions during a procedure.Full entry injects indocyanine green (ICG), a fluorescent dye, into a vein, so a near-infrared scope can show whether the bowel ends have good blood flow before they are joined.
Key steps (robotic):
- Pneumoperitoneum, an optical camera port and the other ports; the robot is docked, and the surgeon moves to the console.
- Adhesions are released and the left colon is freed.
- The inferior mesenteric artery and vein are sealed and divided with the robotic stapler.
- The bowel is divided with the stapler, which needs several loads.
- ICG confirms the blood flow, and the anastomosis is made.
- The specimen leaves through a small wound protector in the stapler port.
The open operation: through a midline incision, the surgeon frees the sigmoid colon while protecting both ureters, frees the rectum in the space in front of the sacrumSAY-krumThe large, triangle-shaped bone at the base of the spine, between the two hip bones.sacr/o sacrumFull entry , and divides it with a curved stapler. The anvil of a circular stapler is tied into the colon with a purse-string stitch, and an assistant between the legs passes the stapler through the anus to join colon and rectum. The two donuts must be complete rings and go with the specimen, and every stapler part is counted. With saline in the pelvis, air pushed gently into the rectum shows any leak as bubbles. The assistant who worked below then changes gown and gloves, and fresh drapes cover the legs.
after a circular stapler fires, both donuts must be complete rings. They go with the specimen, and every part of the stapler is accounted for in the count.
Wound class: II.
After surgery: as for any colon resection: a leak, bleeding, DVT, loss of blood supply to the bowel and infection.
Colostomy and ileostomy
What and why: an ostomyOS-tuh-meeA surgically made opening from an inside organ, such as the bowel or urinary tract, through the belly wall to the outside.-ostomy surgical openingFull entry brings an opening of bowel to the skin, where it is called a stoma. A colostomy uses colon; an ileostomyil-ee-OS-tuh-meeA surgical opening that brings the end of the ileum through the belly wall, so stool leaves the body there.ile/o ileum-stomy surgical openingFull entry uses ileum. An end stoma uses one cut end; a loop stoma brings up a loop, held up by a rod or bridge, and opens it. An ileostomy is built as a raised spout because its liquid drainage burns skin, while a colostomy is sewn flat to the skin. A stoma may be temporary or permanent, and its appliance goes on in the room. A temporary colostomy lets an abdominal infection settle or a lower anastomosis heal; a permanent one is needed when too little colon remains to rejoin safely.
Before surgery: the surgeon and an ostomy nurse choose the site with the patient's lifestyle, age and belt line in mind and mark it on the skin. Take care not to scrub the mark off during the prep. A stoma changes body imageBOD-ee IM-ijHow a person sees, thinks and feels about their own body and its appearance and function.Full entry , and patients adjust better with support and with teaching from an ostomy specialist.
Setup: laparotomy and GI sets with a linear stapler, 3-0 absorbable sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry to sew the bowel to the skin, a temporary pouch, and for a loop stoma a rod, a length of red rubber tubing or a loop ostomy bridge. Butterfly anchors are among the ostomy supplies too.
End stoma: an Allis or Kocher clamp lifts the skin at the marked site and a disk of skin is cut away; the opening is carried down to the fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry , which gets a cross-shaped cut. A Babcock pulls the bowel through without twisting it or stretching its blood supply, and it is tacked to the peritoneum so it cannot slip back or form a hernia. The main incision is closed and covered first. Then the stapled end is cut off with the ESU (have suction ready), the edges are turned out and sewn to the skin, and a pouch cut to fit goes on clean, dry skin.

Loop stoma: a Penrose drain around the bowel helps pull a loop up through the opening. A rod or bridge keeps the loop from slipping back; its two wings are sewn to the skin with nonabsorbable suture on a cutting needle. The loop is opened lengthwise and its edges sewn to the skin with absorbable suture on a taper needle, either at once or later: an ileostomy loop left closed is opened (matured) within 24 hours, and a loop colostomy after about 48 hours. The rod comes out after about 5 to 7 days. When the bowel is divided, its far (distal) stump may also be brought out through the skin as a mucous fistulaFIS-choo-luhAn abnormal passage between two organs or vessels, or between an organ and the skin.Full entry , which is matured at the same operation or, when the bowel is inflamed and swollen, later, once that settles.
Wound class: II when a stoma is made, since the bowel is opened.
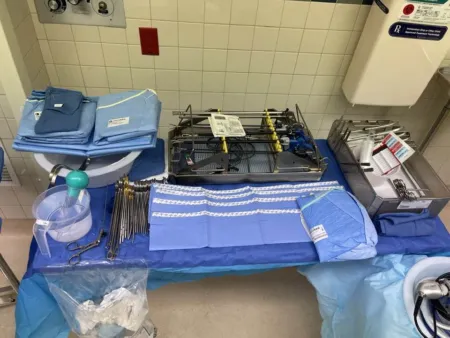
Closing a stoma: closing a colostomy restores the bowel's continuitykon-tih-NOO-ih-teeBeing unbroken over time; in health care, care that stays connected as a client moves between people and places.Full entry . A gauze sponge in the stoma opening limits spillage while the surgeon cuts around the stoma, frees it from the abdominal wall with laps around it and trims its edges. It is closed in two layers, or the end is cut off with a stapler and the bowel rejoined, using a circular stapler through the anus, in low lithotomy, when the sigmoid colon or rectum is involved. The fascia is closed with heavy absorbable suture; the fat and skin may be left open to heal from the base or closed, by surgeon preference, and the stoma site is considered contaminated. A temporary ileostomy is traditionally closed about 3 months later, and a contrast study may first check the connection beyond it. A loop ileostomy can be closed through an incision around the stoma, while an end ileostomy needs a laparotomy; the bowel is closed by hand or rejoined side to side with staplers.
13Liver, pancreas and spleen
The liver and spleenspleenAn organ in the upper left abdomen that filters the blood and helps fight infection.splen/o spleenFull entry are full of blood vessels, and a tear can bleed hard and be difficult to stop, so control of bleeding is a major technical concern. Disease shows up as pain, jaundiceJAWN-disYellow color of the skin, the whites of the eyes and other tissues from too much bilirubin in the blood.Full entry , diabetes or weakness, and is worked up with blood tests such as liver function testsLIV-er FUNK-shun TESTSA group of blood tests that check how well the liver is working and whether its cells are damaged.Full entry and with computed tomographykum-PYOO-tid toh-MOG-ruh-feeAn imaging test that uses x-rays and a computer to make cross-section pictures of the inside of the body.tom/o cut, slice-graphy process of recordingFull entry , magnetic resonance imagingmag-NET-ik REZ-uh-nunts IM-uh-jingAn imaging test that uses a strong magnet and radio waves to make detailed pictures of the inside of the body.Full entry , ultrasound and contrastKON-trastA dye or other substance given before an imaging test so body parts show up more clearly.Full entry studies, plus endoscopic retrograde cholangiopancreatographyen-doh-SKOP-ik RET-roh-grade koh-lan-jee-oh-pan-kree-uh-TOG-ruh-feeA procedure that uses a scope passed through the mouth, with dye and X-rays, to see and treat the bile and pancreatic ducts.endo- within-scopic viewingretrograde moving backwardcholangi/o bile ductpancreat/o pancreas-graphy making a pictureFull entry to look at the ducts directly. Basic general surgery instruments are used, with vascular instruments for open resectionrih-SEK-shunSurgery to remove part of an organ or tissue.re- back, againsect to cut-ion processFull entry and right-angle clamps for every case. hemostatichee-moh-STAT-ikStopping bleeding; also, a product or agent used to stop bleeding.hem/o blood-stasis stopping, standing still-ic relating toFull entry on hand include microfibrillar collagenKOL-uh-jenThe main structural protein of the body, which gives strength to skin, bones, tendons, ligaments and scar tissue.coll/a glue-gen producingFull entry , oxidized cellulose, topical thrombinTHROM-binAn enzyme in the blood that turns fibrinogen into fibrin, the threads that hold a blood clot together.thromb/o clot-in substanceFull entry , absorbable gelatin and fibrin sealant. The anatomy is above, and chapter 7 has more.
Liver resection
What and why: a liver resection removes one or more segments (a segmental resection) or a lobe (a lobectomy). The most common reason is a malignant tumor, usually one that has spread from elsewhere, often from organs that drain into the portal vein; cancer that starts in the liver is rare. Infection, parasitic disease and trauma are other reasons. The best case for resection is a small tumor in a liver without cirrhosissih-ROH-sisLong-term scarring of the liver, in which scar tissue replaces healthy tissue and keeps the liver from working normally.cirrh/o orange-yellow-osis abnormal conditionFull entry .
Diagnosis: a needle biopsy through the skin, guided by MRI or ultrasound. Ultrasound in the OR maps each segment and its vessels.
Position, prep and drape: supine, sometimes in mild Trendelenburg positiontren-DEL-en-burg puh-ZISH-unA position in which the client lies on the back with the bed tilted so the head is lower than the feet.Full entry , with an nasogastric tubenay-zoh-GAS-trik toobA thin, flexible tube passed through the nose and down the esophagus into the stomach.nas/o nosegastr/o stomach-ic having to do withFull entry and a urinary catheter. The prep runs from the nipple line to mid-thigh. A right subcostalsub-KOS-tulBelow the ribs.sub- belowcost/o rib-al relating toFull entry incision, which can be extended across to the left, is common; a midlineMID-lineAn imaginary line down the center of the body; also, a type of IV catheter placed in a vein of the upper arm.Full entry or paramedian incision also works, and a few cases need a sternotomy or thoracotomythor-uh-KOT-uh-meeA surgical cut through the chest wall to reach the lungs, heart or other organs in the chest.thorac/o chest-tomy cutting intoFull entry with chest instruments.
Setup: a major laparotomylap-uh-ROT-uh-meeSurgery that opens the abdomen through a large cut to reach the organs inside.lapar/o abdomen-tomy cutting intoFull entry set with bilebileA yellow-green fluid made by the liver and stored in the gallbladder that helps digest fats.chol/e bileFull entry and vascular instruments, noncrushing liver clamps, a self-retaining retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry such as a Bookwalter, a stapler, vessel loops, umbilical tapes and clips, and liver sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry on blunt needles. Equipment includes intraoperativein-truh-OP-er-uh-tivHappening during surgery, from when the client is brought into the operating room until they are moved to recovery.intra- within, duringoperative of surgeryFull entry ultrasound, an argon beam coagulator and an ultrasonic aspirator (CUSA), with supplies for warming the patient and replacing blood loss and a smoke evacuator. Confirm blood is available, be ready to set up a cell saver, and keep more than one suction tip.

Medications: hemostatic agents (gelatin sponge, oxidized cellulose, microfibrillar collagen) and collagen sheets are ready when the resection begins. Methylene blue, with a 10 mL syringe and a needle, can be injected into a segment's vessels to stain its borders.
Key steps:
- The surgeon opens and explores the abdomen and places moist laps around the neighboring organs and between the liver and the diaphragmDY-uh-framThe dome-shaped sheet of muscle under the lungs that is the main muscle of breathing; also the flat side of a stethoscope.Full entry before setting the retractor. Sponges are easily left under the diaphragm, so note exactly how many go there.
- Ultrasound finds the tumor's segment. A Harrington or wide Deaver retractor may lift the liver.
- The surgeon may slow the liver's blood flow with the Pringle maneuver, a clamp across the vessels to the liver (the hepatichih-PAT-ikRelating to the liver.hepat/o liver-ic relating toFull entry artery and portal vein) that buys up to about an hour, or with vascular clamps on the segment's own vessels.
- The vessels and duct of the segment are clamped, tied and divided.
- The line is scored with the electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry , and the liver tissue is divided with the CUSA, the ESU, an ultrasonic scalpel or the surgeon's fingers (finger fracture).
- The raw surface is checked for bleeding and bile: a lap held on it and rolled off shows any leak. Bleeding points are sewn, sealed with the argon beam or ESU, or covered with a hemostatic agent.
- Drains along the liver bed leave through separate stab wounds, and the abdomen is closed.
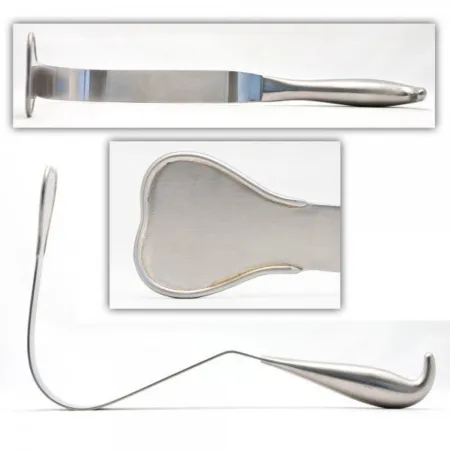
laps tucked between the liver and the diaphragm are easily left behind, so note exactly how many go there and count them all out.
Wound class: I; II if the gallbladder is removed too.
After surgery: the patient goes to PACU or the ICU. Because the liver is so vascular, bleeding can happen during or after surgery, and a fall in blood volume afterward may need the rapid response teamRAP-id rih-SPONS TEEMA team of critical care staff who come quickly to the bedside of a client whose condition is getting worse.Full entry . Bile leak, liver failure and return of the tumor are the main complications.
Pancreaticoduodenectomy (Whipple)
What and why: a Whipple procedure is a curative operation for pancreasPAN-kree-usA long, flat gland behind the stomach that makes digestive enzymes and the hormones insulin and glucagon.pan- allcreas fleshFull entry cancer. It removes the head of the pancreas, the duodenumdoo-uh-DEE-numThe first, short part of the small intestine, just after the stomach.Full entry , part of the jejunumjeh-JOO-numThe second of the three sections of the small intestine; it follows the duodenum and leads into the ileum.jejun/o jejunum (from the Latin for empty)Full entry , the lower third of the stomach, the lower part of the common bile ductKOM-un BILE DUKTThe tube that carries bile from the liver and gallbladder into the small intestine.Full entry and the gallbladder, then rebuilds the biliary, pancreatic and GI tracts. Pancreatic cancer spreads fast and is often found late; most tumors start in the head of the gland and block the bile ductbyle duktOne of the tubes that carry bile from the liver and gallbladder to the small intestine.Full entry . In a pylorus-preserving version the stomach is not removed. The operation takes 5 to 8 hours.
Diagnosis: a full lab workup, MRI, positron emission tomographyPOZ-ih-tron ih-MISH-un toh-MOG-ruh-feeAn imaging test that uses a small amount of a radioactive tracer to show how active the body's tissues are.tom/o cut, slice-graphy recordingFull entry and CT scans, and ERCP with biopsies.
Position, prep and drape: supine, with gel pads or a pressure-reducing mattress on the pressure points, compression devices and a forced-air warmer; an NG tube and a urinary catheter. The prep runs from the nipple line to mid-thigh. An upper midline or bilateral subcostal incision.
Setup: a major laparotomy set with gallbladder, GI and vascular instruments, vessel loops, clips and a linear cutting stapler; long instruments, wide Deaver and Harrington retractors, and a Bookwalter or similar ring retractor; extra suction and sometimes two ESU units; hemostatic agents and drains. Hand out sutures, staples and clips as needed and hold extras in reserve, and keep spare towels and half sheets to keep the field tidy. Ordered blood productBLUD PROD-uktAny part of donated blood prepared for transfusion, such as red cells, plasma or platelets.Full entry must be ready, because the case can need many units.
Key steps:
- A short midline incision lets the surgeon feel for spread. If the cancer has spread, the team may simply close; if not, the incision is lengthened.
- The duodenum is freed by cutting the peritoneumpair-ih-toh-NEE-umThe thin membrane that lines the belly cavity and covers most of the organs inside it.peri- aroundton stretched-eum a structureFull entry beside it (the Kocher maneuver).
- The structures under the liver are looped with vessel loops. A lymph nodelimf nohdA small, bean-shaped organ of the immune system that filters lymph fluid and holds white blood cells.Full entry removed here goes into its own small container and is labeled at once; the gallbladder is freed.
- The stomach, the bowel beyond the duodenum and the pancreas are divided, and the specimen goes to pathologypuh-THOL-uh-jeeThe study of disease and its causes and effects, or the disease changes found in a person or tissue.path/o disease-logy study ofFull entry for frozen section.
- The rebuild usually joins the pancreas to the jejunum first, over a small stentstentA small tube, often of metal mesh, placed inside a vessel or duct to hold it open.Full entry in the pancreatic duct, then the bile duct, then the stomach. Follow bowel technique per facility policy.
- The abdomen is irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry , two suction drains are placed and the wound is closed in layers.
Wound class: II; III if bowel or bile spills.
After surgery: the patient goes to PACU and often the ICU, with close checks of metabolismmuh-TAB-uh-liz-umAll the chemical processes in the body's cells that make energy, build tissue and break substances down.Full entry , kidney function, infection and fluids, and may stay up to 10 days; antineoplastican-tee-nee-oh-PLAS-tikA drug used to treat cancer by killing cancer cells or stopping them from growing and dividing.anti- againstneo- newplas growth, formation-tic relating toFull entry and radiationray-dee-AY-shunEnergy that travels as waves or particles, such as X-rays, used to make images or treat cancer; also pain that spreads from its starting point.radi/o rays, radiation-ation processFull entry usually follow. Some complication affects 20 to 40 percent of patients: abdominal infection, a pancreatic fistulaFIS-choo-luhAn abnormal passage between two organs or vessels, or between an organ and the skin.Full entry , diabetes, bleeding, return to the OR, ulcerUL-serAn open sore where the skin or the lining of an organ has broken down.Full entry , poor absorptionub-ZORP-shunThe taking in of a substance, such as a drug or a nutrient, into the bloodstream.Full entry of food and slow emptying of the stomach; in-hospital deaths are now under 5 percent.
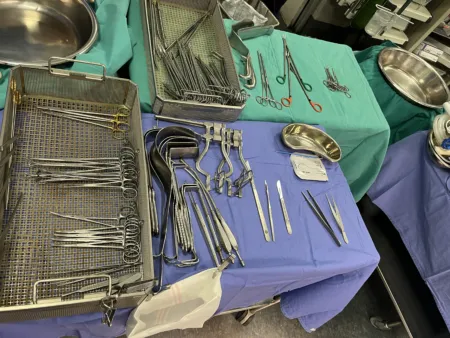
Splenectomy
What and why: the spleen is removed to stop bleeding after trauma or to treat disease. A stable patient with a low-grade injury, graded on CT or ultrasound, is often treated without surgery, and surgeons try to save the spleen because it helps fight infection. Immune thrombocytopenic purpuraPUR-pyuh-ruhPurple or red-brown patches on the skin caused by bleeding under the skin, which do not fade when pressed.Full entry (ITP), in which changes in the immune system cause a loss of plateletPLAYT-litA tiny cell fragment in the blood that sticks together at a wound to help form a clot.Full entry , is the most common disease reason; others are lymphomalim-FOH-muhA cancer of lymphocytes, the white blood cells of the lymph system.lymph/o lymph-oma tumorFull entry and some leukemialoo-KEE-mee-uhA cancer of the blood-forming cells in the bone marrow, in which abnormal white blood cells are made in large numbers.leuk/o white-emia blood conditionFull entry , hemolysishee-MOL-ih-sisThe breaking apart of red blood cells, which releases hemoglobin into the blood.hem/o blood-lysis breaking downFull entry jaundice, tumors, cysts and an enlarged spleen. Any accessory spleens are removed too, because they can keep the disease going.
Approach: laparoscopiclap-uh-roh-SKOP-ikDone through a few small cuts in the abdomen with a thin camera and long instruments, instead of one large opening.lapar/o abdomen-scopic viewingFull entry splenectomy is the standard for benign blood disorders, with less pain, less bleeding and a shorter stay. Open surgery is used for severe portal hypertension, a clottingKLOT-ingThe process by which blood thickens into a gel to plug a damaged vessel and stop bleeding; also called coagulation.Full entry problem that cannot be corrected, severe ascitesuh-SY-teezA buildup of fluid in the abdominal cavity, the space around the organs of the belly.Full entry , a very large spleen, heavy adhesionad-HEE-zhunA band of scar tissue that joins two surfaces inside the body that are normally separate.ad- towardhes stick-ion conditionFull entry and most injuries.
Position, prep and drape: open, supine in reverse Trendelenburg positionree-VERS tren-DEL-un-burg puh-ZISH-unA position lying on the back on a bed or table that is tilted so the head is higher than the feet, with the body kept straight.Full entry tilted slightly to the right, prepped from the nipple line to mid-thigh, through a midline incision. Laparoscopic, turned onto the right side about 45 degrees, or fully, with the table flexed, the kidney rest raised, a beanbag and safety straps; a flank prep.
Setup: open, a laparotomy set with vascular clamps and forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry , large right-angled pediclePED-ih-kulA narrow stem or stalk that attaches a structure, such as a tumor or a skin flap, to the body.Full entry clamps, clips, long instruments and hemostatic agents, plus extra suction, large basins for clots, an autotransfusion system and extra laps. Laparoscopic, a 30-degree scope, trocarTROH-karA sharp or bladed instrument inside a tube (cannula), used to pierce a body wall and leave the tube in place as a port.Full entry , ultrasonic shears, a clip applier, an endoscopicen-doh-SKOP-ikDone with an endoscope, a thin tube with a light and camera passed into the body.endo- within-scopic viewingFull entry linear stapler with vascular loads and a retrieval bag, with a morcellator on hold.
Medications: the patient is vaccinated against pneumococcus, meningococcus and Haemophilus influenzae type B, ideally before surgery. Blood must be ready, many units after trauma, and a cell saver may return the patient's own blood.
Key steps after trauma:
- A fast midline laparotomy. Have two suctions running as the abdomen opens, a large basin for the clots, and laps ready in quick succession; if the patient is bleeding hard, dry laps may go in first.
- All four quadrants are packed, then the laps come out one quadrant at a time as each is checked.
- The ligaments holding the spleen are divided, a pedicle clamp goes across the splenic artery and vein, and the vessels are tied twice.
- The rest of the abdomen is checked for other injuries, irrigated and closed, with a drain near the splenic pedicle.
During the bleeding, stay focused: watch the wound, listen for instructions and move quickly but carefully.
Laparoscopic steps: the spleen is freed from the colon and stomach, the splenic artery is tied, and a linear stapler seals the vessels at the hilum. The spleen goes into a retrieval bag and is broken up (morcellated) to fit through a port, or lifted out through a hand-assist port; receive it in a basin big enough for the whole organ and bag.
Wound class: an elective splenectomy opens no tract, so it meets Class I, and so can an operation after blunt trauma that meets the same criteria. Otherwise the class follows the injury: a fresh traumatic wound or gross spillage from the GI tract is Class III, and an old traumatic wound with dead tissue is Class IV; one reference lists splenectomy as Class II.
After surgery: trauma patients go to the ICU; after a laparoscopic splenectomy most go home in a day or two. Complications include bleeding, infection, a wound that separates and a weaker defense against infection. Over the long term the patient is at risk of overwhelming infection after splenectomy and of blood clots.
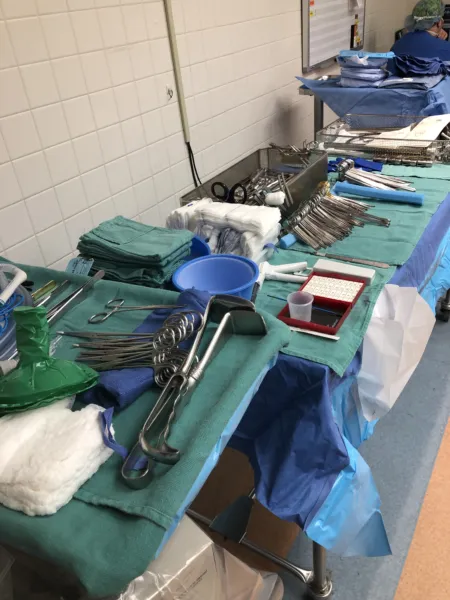
14Breast and thyroid procedures
Breast disease
Most breast surgery that is not cosmetic treats cancer. Invasive (infiltrating) ductal carcinomakar-sih-NOH-muhA cancer that starts in the cells that line the skin or the inside and outside surfaces of organs.carcin/o cancer-oma tumorFull entry is the most common type, about 80 percent of new cases. Ductal carcinoma in situ (DCIS) is cancer cells still confined to the milk ducts, not yet able to spread. The risk rises with female sex and with age, and with a family history, benign breast disease and hormonal patterns such as an early first period and a late menopauseMEN-uh-pawzThe time in a woman's life when menstrual periods stop for good, counted once there has been no period for 12 months in a row.men/o month, menstruation-pause stopFull entry ; men have under 1 percent of breast cancers.
Benign changes are often grouped as fibrocystic change: fibrousFY-brusMade of or containing tough threads (fibers), especially of connective tissue.fibr/o fiber-ous full of, relating toFull entry tissue, cysts and solid lumps, of which the fibroadenoma is the most common. Paget disease of the breast is a scaly, raw or bleeding change of the skin of the nipple and areola that signals a much higher chance of a cancer beneath it; treatment removes the nipple and areola, along with any cancer found.
A mass under about 1 cm usually cannot be felt, but mammography can find it. A fine needle can draw cells from a lump, and a stereotactic biopsy takes a core of tissue with the patient lying prone on the mammography table. How far the cancer has spread to the lymph nodelimf nohdA small, bean-shaped organ of the immune system that filters lymph fluid and holds white blood cells.Full entry predicts the outcome more than the size of the tumor.
The breast surgery patient
For many patients the breast is tied to body imageBOD-ee IM-ijHow a person sees, thinks and feels about their own body and its appearance and function.Full entry and identity, so breast surgery can bring anxiety and depression. A patient may fear cancer, losing part of the body, a partner's or family's reaction and a change in how they see themselves. What helps most is a calm presence: listen, give time for questions and worries, respect the patient's feelings, and offer comfort such as warm blankets. After a mastectomyma-STEK-tuh-meeSurgery to remove all or part of a breast.mast/o breast-ectomy surgical removalFull entry a patient may grieve deeply, and support at that time matters for a healthy self-image. Treatment has moved toward smaller operations, and breast-conserving surgery with a sentinel node biopsy is now the usual choice unless the cancer is advanced.
Breast biopsy
What and why: an excisional biopsy removes a lump or suspicious area whole, with a rim of normal tissue; a lumpectomy (breast-conserving surgery) removes a known cancer the same way. Many lesionLEE-zhunAn area of tissue that has been damaged or has changed from normal, such as a sore, wound, lump or spot.Full entry are first sampled with a core biopsy needle, often guided by mammography (stereotactic biopsy). A lesion too small to feel is marked first in radiology, with a hooked wire placed the day of surgery or a tiny radioactive seed placed up to 5 days before; wires are becoming less common.
Position: supine or in a modified beach chair, the arm out on an armboard at less than 90 degrees. Prep and drape: the breast and the skin around it, gently, so the wire stays put; towels and a fenestrated sheet. Setup: a minor set with small retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry such as Senn retractors and rakes, Allis clamps, fine hemostatHEE-moe-statA clamp with finger rings and a locking ratchet used in surgery to grasp and close off bleeding vessels.hem/o blood-stat stopping, standing stillFull entry , an electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry , and stitches or ink for marking; a gamma probe in a sterile cover for a seed.
Key steps: the surgeon removes the tissue around the wire, seed or lump in one piece, often with scissors rather than the ESU so the margins are not distorted. The edges are marked with stitches or ink so the pathologist can tell each side. A wire or seed specimen goes for an X-ray to prove the lesion and its markerMAR-kerSomething that can be measured, such as a substance in the blood, that shows a disease or body process is present.Full entry are inside. If a margin is not clear, more tissue is taken, so keep the field ready until the surgeon closes. Extra "shave" margins may be cut from each wall of the cavity, each labeled by side, and after a lumpectomy clips may mark the cavity walls to guide radiationray-dee-AY-shunEnergy that travels as waves or particles, such as X-rays, used to make images or treat cancer; also pain that spreads from its starting point.radi/o rays, radiation-ation processFull entry later.
Specimen: oriented and sent to pathologypuh-THOL-uh-jeeThe study of disease and its causes and effects, or the disease changes found in a person or tissue.path/o disease-logy study ofFull entry at once, or placed in formalinFOR-muh-linA solution of formaldehyde in water used to preserve tissue specimens for the pathology lab.Full entry right away by facility policy; a delay can change the hormone receptorrih-SEP-terA structure on or in a cell that a specific chemical, such as a hormone or drug, attaches to in order to act.Full entry tests that guide cancer treatment. Counts: sponges and sharps; the wire counts as a sharp. Dressing: strips or a buried stitch, gauze and often a surgical bra. Wound class: I, clean.
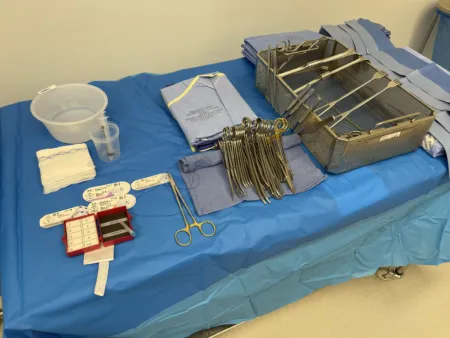
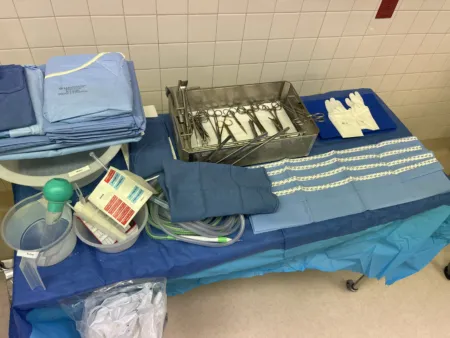
Sentinel node and mastectomy
A sentinel lymph node biopsy removes the first node or nodes that drain the tumor. If they are free of cancer, the rest of the axilla can usually be left alone. A radioactive tracer (technetium-99) is injected before surgery, often hours ahead, and blue dye may be injected before or during surgery. "Hot" nodes are found with a gamma probe in a sterile cover, "blue" nodes by sight. Blue dye can cause allergic reactions, even anaphylaxisan-uh-fuh-LAK-sisA sudden, severe allergic reaction that affects the whole body.ana- away, against-phylaxis protectionFull entry , so a crash cart is kept nearby, and it can make the pulse oximeter read falsely low.
Each sentinel node goes in its own container, labeled exactly as the surgeon names it. Never put two nodes in one container. A radioactive specimen's label and paperwork name the tracer. When a mastectomy follows, the node biopsy comes first; its instruments then leave the field, and a fresh setup is used for the breast.
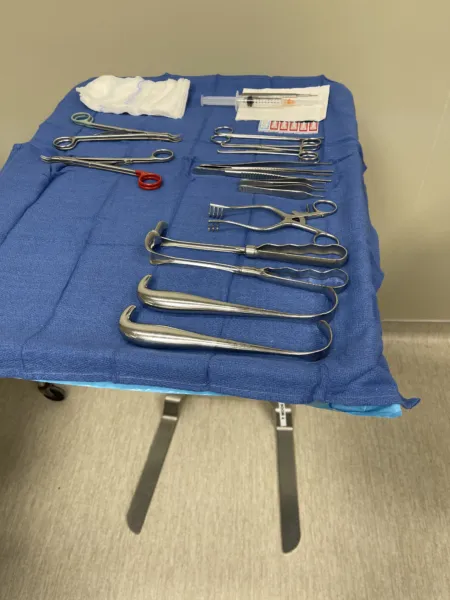
A simple mastectomy removes the whole breast with its nipple and areola and leaves the axillary nodes and chest muscles. A modified radical mastectomy removes the whole breast with a sentinel node biopsy or an axillary node dissectiondy-SEK-shunA tear in the inner layer of an artery wall that lets blood split the layers apart; also, the cutting apart of tissue in surgery.Full entry , which usually takes levels I and II, and leaves the chest muscles. A radical mastectomy, which also removes the chest wall muscles, is rare today.
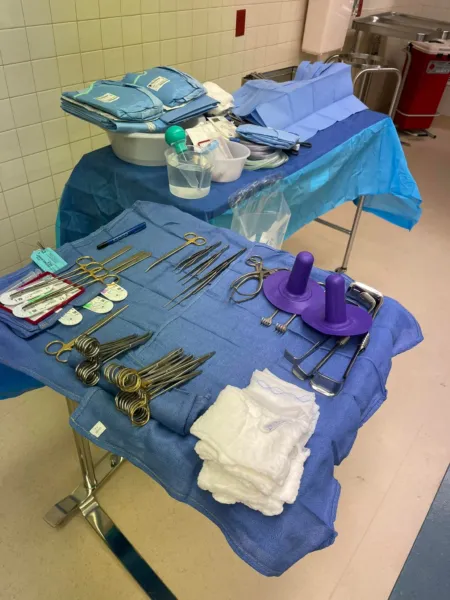
Modified radical mastectomy: supine, the arm out on a padded armboard at less than 90 degrees and often draped free. Setup: a basic set with skin hooks and rakes, small Deaver retractors, two ESU units so one can be cleaned while the other is used, clip appliers, vessel loops and one or two closed suction drains. Steps:
- An elliptical incision around the nipple and tumor, extended toward the axilla.
- Skin flaps are raised with the knife or ESU while hooks or rakes lift the edges. Knife blades dull quickly here, so change them often.
- The breast and its fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry are peeled off the pectoralis major.
- The axillary fat and nodes are removed below the axillary vein, sparing the long thoracicthuh-RAS-ikRelating to the chest, or to the middle part of the spine.thorac/o chest-ic relating toFull entry and thoracodorsal nerves.
- The wound is irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry , and the drains are placed through separate stab wounds and stitched to the skin. Reconstruction may follow on a separate setup; chapter 38 teaches it.
Specimen: oriented (often with a marking stitch) and sent to pathology promptly; the lab also tests it for hormone receptors and HER2. Counts: initial and closing. Dressing: a nonadherent layer, fluffs and a wrap or surgical bra, with the drains attached to their suction. After an axillary dissection, the patient is taught to avoid injections, IV lines, blood draws and blood pressure cuffs on that arm. Complications include bleeding, infection, fluid collections (seromas), death of part of a skin flap, numbness, a stiff shoulder and a swollen arm (lymphedemalimf-uh-DEE-muhSwelling of a body part from a buildup of lymph fluid in the tissues.lymph/o lymph, the clear fluid of the lymph systemedema swellingFull entry ). Wound class: I, clean.
Thyroidectomy
What and why: a thyroidectomythy-roy-DEK-tuh-meeSurgery to remove all or part of the thyroid gland in the neck.thyr/o thyroid-ectomy surgical removalFull entry removes the whole gland (total) or one lobe with the isthmus (hemithyroidectomy, or lobectomy) for cancer or a suspicious noduleNOD-yoolA small, firm, rounded lump of tissue that can be felt or seen, in or under the skin or in an organ.Full entry , a goiterGOY-terAn enlarged thyroid gland, seen or felt as a swelling at the front of the neck.Full entry that presses on the tracheaTRAY-kee-uhThe windpipe: the tube that carries air from the throat to the lungs.Full entry or esophagusih-SOF-uh-gusThe muscular tube that carries food and liquid from the throat to the stomach.esophag/o esophagusFull entry , or an overactivityoh-ver-ak-TIV-ih-teeMore activity than normal, in a person, an organ or a body system.Full entry gland. Graves diseaseGRAYVZ dih-ZEEZAn autoimmune disease in which antibodies make the thyroid gland overactive.Full entry , the most common cause of an overactive gland, goes to surgery when antithyroid drugs and radioactive iodineEYE-uh-dyneA mineral the thyroid gland uses to make thyroid hormone; it is also used to kill germs on the skin and in some contrast dyes.Full entry have failed or cannot be used. Hashimoto thyroiditishah-shee-MOH-toh thy-roy-DY-tisAn autoimmune disease in which the immune system attacks the thyroid gland, slowly reducing its hormone output.thyr/o thyroid-itis inflammationFull entry , an autoimmune diseaseaw-toh-ih-MYOON dih-ZEEZA disease in which the immune system attacks the body's own healthy tissue.auto- selfimmune protectedFull entry that enlarges the gland and is the most common cause of an underactive one (hypothyroidismhy-poh-THY-roy-diz-umA condition in which the thyroid gland makes too little thyroid hormone.hypo- below, underthyr/o thyroid gland-ism conditionFull entry ), goes to surgery to relieve pressure in the neck. For cancer, a total or near-total thyroidectomyTOE-tul thy-roy-DEK-tuh-meeSurgery to remove the whole thyroid gland.thyroid thyroid gland-ectomy surgical removalFull entry is the usual operation.
Approach: minimally invasive video-assisted thyroidectomy (MIVAT), done through a small neck incision with a scope's help, is now a standard operation. An entirely open thyroidectomy is seldom done, kept for selected cases such as a very large gland, and a MIVAT that must be converted becomes one. Robotic thyroidectomy reaches the gland from a site away from the front of the neck, such as the armpit, behind the ear or through the mouth, an approach patients seek for its cosmetic result; a large goiter reaching behind the breastbone or behind the throat, a tumor of 4 cm or more or one that looks to be invading nearby tissue, and medullamuh-DUL-uhThe inner part of an organ; most often the medulla oblongata, the lowest part of the brainstem.Full entry cancer rule it out. For the transaxillary and transoral routes the patient has an electromyographyih-lek-troh-my-OG-ruh-feeA test that records the electrical activity of muscles, usually through thin needles placed in the muscle.electr/o electricitymy/o muscle-graphy recordingFull entry breathing tube for nerve monitoring, and a transoral case is prepped and draped from the nose down to the areolae, so the surgeon can still convert to an open operation or take the specimen out through the armpit.
other references still teach the open thyroidectomy through a collar incision as the standard operation; its steps follow below.
Position: supine, a roll behind the shoulder blades to extend the neck, the head on a gel or foam ring, arms tucked, and the head of the table raised (reverse Trendelenburg positionree-VERS tren-DEL-un-burg puh-ZISH-unA position lying on the back on a bed or table that is tilted so the head is higher than the feet, with the body kept straight.Full entry ) to reduce venous congestion. Many teams use a breathing tube with sensors that warn when the recurrent larynxLAIR-inksThe voice box: the part of the airway in the neck, above the windpipe, that holds the vocal cords.laryng/o larynxFull entry nerve is near, and the surgeon may use a nerve stimulator on the field.
Prep and drape: from the chin to the nipples, including the neck and shoulders, the same for a MIVAT in case it is converted; towels and a thyroid sheet. Laps tucked at the sides of the neck go on the count sheet. Setup: a thyroid tray with fine clamps (12 to 15 for the vessels), right angles, neck retractors such as the Green and Lahey retractors, and a thyroid tenaculum such as the Lahey; bipolarby-POH-lerHaving two poles or two opposite ends; most often used as a short form of bipolar disorder.bi- twopolar having polesFull entry , ultrasonic shears or a small vessel sealer; clips; peanuts on clamps.

For a MIVAT, add a 5 mm 30-degree scope, spatula and suction dissectors, endoscopicen-doh-SKOP-ikDone with an endoscope, a thin tube with a light and camera passed into the body.endo- within-scopic viewingFull entry scissors and forcepsFOR-sepsA hand instrument with two blades or arms used to grasp, hold or pull tissue or objects.Full entry , small retractors (such as Farabeuf or Miccoli retractors) and a small clip applier, with the ultrasonic scalpel. Keep the open thyroid instruments ready, and follow fire precautionprih-KAW-shunA step taken ahead of time to prevent harm, such as the infection-control practices used with every client.Full entry with the light cord and scope.
Key steps (MIVAT):
- A horizontal incision of about 1.5 to 3 cm above the sternal notch, and the fascia between the strap muscles is opened.
- The lobe is freed from the strap muscles with small spatulas, and retractors hold the muscles aside.
- The scope goes in. The surgeon dissectdy-SEKT, or dih-SEKTTo cut apart or separate tissues carefully during surgery.Full entry with the spatula and suction dissector, clips and divides the vessels, and finds the laryngeal nerves, perhaps with a nerve stimulator, and the parathyroid glandpair-uh-THY-royd glandOne of four small glands behind the thyroid that control the amount of calcium in the blood.para- besidethyr/o thyroid gland-oid likeFull entry .
- The lobe is lifted out through the incision and freed from the trachea. Close to the nerve and the parathyroids, the surgeon stops using the ultrasonic scalpel and dissects without heat.
- The isthmus is divided, and for a total thyroidectomy the other lobe comes out the same way.
- The muscle is closed with 4-0 absorbable sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry and the skin with a buried absorbable stitch or tissue glue, under flat gauze.
The open operation: a low collar incision in a skin crease, about 2 cm above the joints where the collarbones meet the breastbone. Flaps are raised under the platysma, the strap muscles are separated in the midlineMID-lineAn imaginary line down the center of the body; also, a type of IV catheter placed in a vein of the upper arm.Full entry , and the lobe is rolled inward. Vessels are tied, clipped or sealed close to the gland while the surgeon protects the recurrent laryngeal nerve and each parathyroid gland; electrocautery is kept away from the nerves. The isthmus is divided. Closure: the strap muscles if they were cut, the platysma, then a buried skin stitch or glue.
If a parathyroid gland comes out with the specimen, the surgeon may reimplant it. Keep it on the field in chilled saline: it is cut into tiny pieces and placed in a pocket in a muscle, usually in the neck (such as the sternocleidomastoid or a strap muscle), marked with a permanent stitch.
Specimen: labeled right or left, sometimes for frozen section. Counts: initial and closing, including the neck laps. Dressing: strips or glue. A neck hematomahee-muh-TOH-muhA collection of blood, often clotted, that has leaked out of the blood vessels into the tissue.hem/o blood (here as hemat-)-oma swelling or massFull entry can squeeze the airway; it means an urgent return to the OR to open the wound. Keep the back table and Mayo sterile until the patient leaves the room, and send a tracheotomytray-kee-OT-uh-meeThe surgical cut made into the windpipe through the front of the neck.trache/o windpipe-tomy cutting, incisionFull entry tray with the patient to PACU, in case bleeding, swelling or nerve injury blocks the airway. Wound class: I, since no tract is entered.
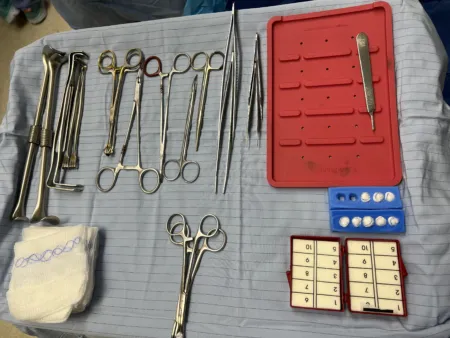
Parathyroidectomy
What and why: a parathyroidectomy removes overactive parathyroid tissue: an adenomaad-uh-NOH-muhA tumor of gland tissue that is not cancer.aden/o gland-oma tumorFull entry (a tumor that oversecretes the hormone), hyperplasiahy-per-PLAY-zhuhAn increase in the number of cells in a tissue or organ, making it larger.hyper- more than normal-plasia formation, growthFull entry or a cancer. Too much parathyroid hormonepar-uh-THY-royd HOR-mohnA hormone from the parathyroid glands in the neck that raises the calcium level in the blood.para- besidethyr/o thyroid-oid resemblingFull entry (hyperparathyroidismhy-per-pair-uh-THY-roy-diz-umOveractivity of the parathyroid glands, which make too much parathyroid hormone.hyper- excessivepara- besidethyroid -ism conditionFull entry ) raises blood calcium, which can cause kidney stoneKID-nee STOHNA hard, pebble-like lump of minerals that forms inside the kidney.Full entry , thin bones, high blood pressure and abnormal heart rhythms; a calcium level above 13.5 mg/dL can trigger life-threatening dysrhythmiadis-RITH-mee-uhA heart rhythm that is not normal: too fast, too slow or irregular.dys- abnormalrhythm/o rhythm-ia conditionFull entry . Thirst, heavy urination, constipation, joint pain and depression are other signs. The glands sit behind the thyroid, as described above; chapter 9 covers the hormones.
Diagnosis: a sestamibi scan or an ultrasound finds the overactive gland and shows where to make the incision. A patient whose sestamibi scan shows nothing is not a candidate for the minimally invasive approach.
Approach: the classic open operation explores both sides of the neck and looks at all four glands. Hyperplasia still needs it: three and a half glands come out, and part of one stays to prevent low calcium. A single adenoma is now usually removed through a small, focused incision, guided by hormone levels measured during surgery and by a gamma probe.
Position, prep and drape: as for a thyroidectomy.
Setup: thyroid instruments with mosquito hemostats and fine ligatures, clips, an energy device, a smoke evacuator and small gauze dissectors. Vascular forceps such as the DeBakey and bipolar and ultrasonic devices are used to free the gland. Have many specimen containers and the blood tubes for hormone levels, make sure the pathologist is ready, and keep instruments for opening the chest (a mediastinotomy) available.
Medications: for a radio-guided operation, technetium-99m sestamibi is given before surgery so a gamma probe can find the gland in the OR.
Key steps (hormone-guided):
- A baseline blood sample is drawn before surgery, and a 2 cm incision is made where the scan pointed.
- Another sample is drawn when the gland is exposed, and the gland is removed.
- Keep the gland in sterile saline on the back table until the result is back: a drop in the hormone level of 50 percent or more confirms the right gland came out. Samples may be drawn 5, 10 and 20 minutes after removal; if the level does not drop, the surgeon explores further.
- A normal gland removed by mistake is minced with a #15 blade and replanted in a small pocket in a strap muscle of the neck.
- Closure is as for a thyroidectomy: the platysma with fine absorbable suture, then a buried skin stitch or skin glue.
a removed parathyroid gland stays in sterile saline on the back table until the hormone result is back. A normal gland taken by mistake can still be replanted.
Specimens: there may be several. When each one is collected, the surgeon, the scrub and the circulator agree on its name, type, source and preservative; it is labeled with the order it was taken (A, B, C), pathology results are read back, and counts are not done while specimens are being handled.
Wound class: I, since no tract is entered.
After surgery: many patients go home the same day. Low calcium can follow when several glands come out, which is why part of one is left; a repeat neck exploration is avoided because it puts the recurrent laryngeal nerves at risk.
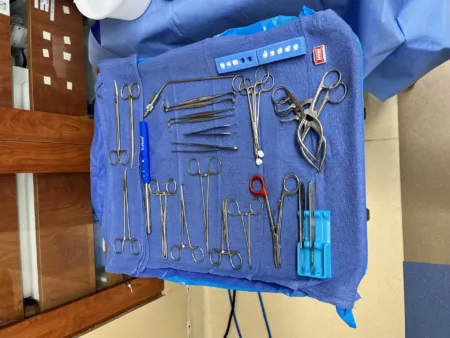
15Anorectal surgery
These cases share a rectalREK-tulRelating to the rectum, the last part of the large intestine; also, given or measured through the rectum.rect/o rectum, straight-al relating toFull entry set and the prone jackknife, lithotomylih-THOT-uh-meeA position lying on the back with the hips and knees bent and the legs raised and spread apart, often in stirrups.lith/o stone-tomy cutting intoFull entry or lateral position, with the buttocks taped apart in jackknife. The anal canal is the end of the GI tract: a hemorrhoidectomy is classed as Class II, clean-contaminated, and a wound with pus already in it, such as an abscessAB-sesA closed pocket of pus in tissue, walled off by the body.Full entry , is Class IV. An anal fissureFISH-erA narrow crack or split in the skin, a lining or an organ.Full entry , a tear in the skin lining the anal canal from the dentate line to the anal margin, comes from trauma, childbirth or hard stools, or with diseases such as Crohn diseasekrohn dih-ZEEZA long-term inflammatory bowel disease that can affect any part of the digestive tract, through the full thickness of its wall.Full entry ; it hurts during and after a bowel movement and often bleeds.
Hemorrhoidectomy
A hemorrhoidHEM-uh-roydA swollen vein in or around the anus or lower rectum.Full entry is a normal cushion of blood vessels in the anal canal that becomes a problem when it swells, bleeds or slips down (prolapsePROH-lapsThe slipping or falling of an organ or part from its normal position.Full entry ). Internal hemorrhoids, above the pectinate line, have little pain sense; external ones, below it, are covered with skin and can hurt badly when a clot forms in them. Surgery is for hemorrhoids that diet and office treatments such as banding did not fix.
Position: prone jackknife with the buttocks taped apart, or lithotomy. In jackknife, use chest rolls, padding under the knees and a pillow under the ankles. Prep and drape: the area around the anus first and the anus last; a fenestrated or lithotomy sheet. Setup: a rectal set with a Hill-Ferguson retractorrih-TRAK-terA surgical instrument that holds back tissue or organs so the surgeon can see and reach the operative site.Full entry or Pratt speculumSPEK-yoo-lumAn instrument used to open and hold open a body opening, such as the vagina, so the inside can be seen.Full entry , Allis or Babcock clamps, Metzenbaum scissors, an electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry or vessel sealer, local anestheticLOH-kul an-es-THET-ikA drug that blocks feeling in one part of the body without making the person unconscious.Full entry (sometimes with epinephrineep-ih-NEF-rinA hormone and drug, also called adrenaline, that raises heart rate and blood pressure and opens the airways.Full entry ) and absorbable sutureSOO-cherA stitch, or the thread used to stitch, that holds the edges of a wound or incision together.Full entry .

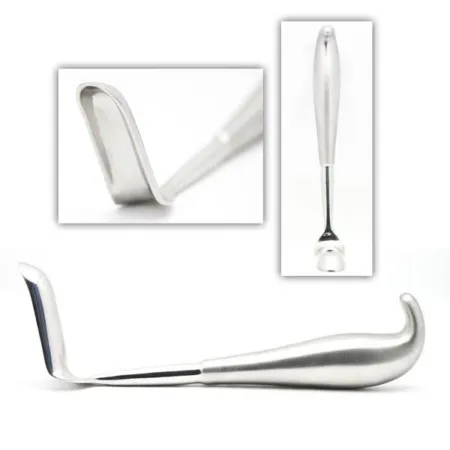
Key steps: each hemorrhoid is grasped, cut out in a narrow ellipse up to its apex, and tied off there. The wound is sewn closed or left open, by surgeon preference. Bridges of normal skin and lining stay between the cuts, so too much skin is not lost and the anus does not scar narrow.
Specimen: the hemorrhoids; if the surgeon marks one with a stitch, its position (such as 12 o'clock) goes on the label. Counts: sponges and sharps; packing left in the canal is never a counted sponge. Dressing: petrolatum gauze in the canal and gauze dressings. Trouble passing urine is the most common problem afterward.
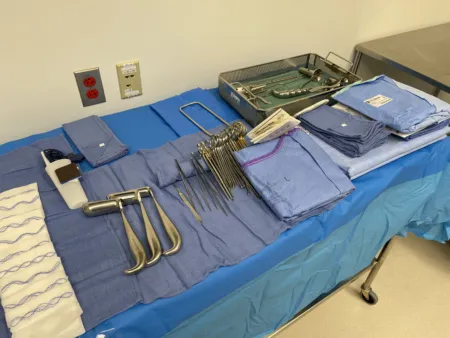
Anal fistula: fistulotomy, fistulectomy and seton
What and why: an anal fistulaFIS-choo-luhAn abnormal passage between two organs or vessels, or between an organ and the skin.Full entry (fistula-in-ano) is a tract from an opening inside the anal canal to an opening on the skin beside the anus. It is a long-lasting form of a perianal abscess that did not heal after draining, which can start in a blocked, infected anal gland, and it is linked with Crohn disease, tuberculosistoo-ber-kyoo-LOH-sisAn infection caused by the bacterium Mycobacterium tuberculosis, which most often attacks the lungs.tubercul/o small swelling-osis abnormal conditionFull entry , cancer and trauma. Fistulas are grouped by how they cross the sphincterSFINGK-terA ring of muscle that tightens to close an opening or passage in the body and relaxes to open it.Full entry muscles: intersphincteric, transsphincteric, suprasphincteric or extrasphincteric. A fistulotomy lays the tract open; a fistulectomy cuts it out and leaves the wound open to heal by granulation. A tract that crosses the sphincter needs a more careful operation, because cutting too much muscle causes incontinencein-KON-tih-nensLoss of control over the bladder or bowel, so urine or stool leaks out without the person meaning it to.in- notcontin/o to hold back-ence state ofFull entry .
The seton: a thread, suture or soft rubber loop tied through the tract, which keeps it draining while scar tissue slowly closes it. Tightened over several visits, a seton can divide the muscle so slowly that it heals behind the cut, which protects continence.
Diagnosis: anoscopy, examination under anesthesiaan-us-THEE-zhuhLoss of feeling or sensation, often brought on by drugs so that surgery or a procedure can be done without pain.an- withoutesthesi/o feeling, sensation-ia conditionFull entry , probing of the tract and a hydrogen peroxide injection study, with magnetic resonance imagingmag-NET-ik REZ-uh-nunts IM-uh-jingAn imaging test that uses a strong magnet and radio waves to make detailed pictures of the inside of the body.Full entry or ultrasound for a complex fistula.
Position, prep and drape: jackknife or lateral, the buttocks taped apart, and a fenestrated sheet; a simple excisionek-SIZH-unCutting out tissue, such as a growth or damaged area, during surgery.Full entry can be done under regional anesthesia with sedationsih-DAY-shunA calm, relaxed or sleepy state brought on by drugs, or the use of drugs to cause it.sed calm, settle-ation processFull entry .
Setup: a minor rectal set with fistula probes, a lighted retractor, a monopolar ESU, curettekyoo-RETA surgical instrument with a small spoon- or loop-shaped tip used to scrape tissue.Full entry , an ultrasonic scalpel for some cases, and a vessel loop for a seton. A probe with an eye at its tip can pull the seton through the tract.

Key steps: the surgeon passes a probe to find each end of the tract. The tract is laid open, or cored out with the ESU, and the wound is left open to heal. For a seton, the loop is threaded through the eye of the probe, drawn around the muscle and tied with several knots, the end stitched so it cannot come untied.
After surgery: the open wound heals by granulation, and a seton needs follow-up visits to tighten or replace it.
Pilonidal cystectomy
What and why: a pilonidal sinusSY-nusA hollow space in the body, most often one of the air-filled spaces in the skull bones around the nose.Full entry forms in the skin over the sacrumSAY-krumThe large, triangle-shaped bone at the base of the spine, between the two hip bones.sacr/o sacrumFull entry and coccyxKOK-siksThe small, triangle-shaped bone at the very bottom of the spine; the tailbone.Full entry , in the cleft of the buttocks; blocked, it becomes a pilonidal cyst, and infected, a pilonidal abscess. Ingrown hairs cause it, and it is more common in men, mostly in their 20s and 30s. A pit is often seen in the midlineMID-lineAn imaginary line down the center of the body; also, a type of IV catheter placed in a vein of the upper arm.Full entry about 5 cm above the anus. An abscess that does not heal can leave a chronic draining tract, which can be mistaken for an anal fistula. An acute abscess is drained; the cyst and its tracts are cut out once the infection has settled.
Position and setup: jackknife, with the buttocks taped apart and secured to the sides of the table. A minor set and rectal instruments, methylene blue, a 10 or 20 mL syringe and a blunt-tipped needle.
Medications: methylene blue injected into the tracts stains them so none is missed.
Key steps: the surgeon finds the tracts with a probe, opens over it and injects the dye. An elliptical incision goes down to the fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry , granulation tissuegran-yuh-LAY-shun TISH-ooNew, moist, red tissue that fills a healing wound from the bottom up.Full entry is scraped out with a curette, and the cyst and every tract are removed. The skin is closed, after freeing its edges to take off the tension, or the wound is left open to heal by granulation.
Wound class: the area is skin, not the GI tract, so the class follows what the surgeon finds; an abscess or an infected tract is an infection already present, Class IV.
After surgery: removing the whole cyst and every tract prevents it coming back.
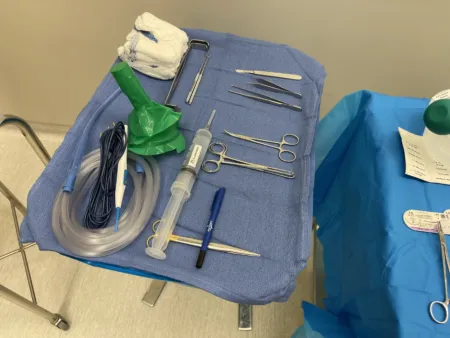
Sphincteroplasty
What and why: a sphincteroplasty is surgical repair of a sphincter. An anal sphincteroplasty repairs the anal sphincter for fecal incontinence, which can follow a birth defect, an injury during childbirth, an accident or an earlier operation, radiationray-dee-AY-shunEnergy that travels as waves or particles, such as X-rays, used to make images or treat cancer; also pain that spreads from its starting point.radi/o rays, radiation-ation processFull entry , infection, a tumor, years of straining or aging. Digital examination, defecography, anal manometry and ultrasound show which part of the continence mechanism is at fault. Direct repair of the muscle is the usual operation.
Position, prep and drape: jackknife prone, lithotomy or a modified lateral position. compression stockingkum-PRESH-un STOK-ingA tight elastic stocking that squeezes the leg, most firmly at the ankle, to help blood flow back toward the heart.Full entry and a urinary catheter may be used; every bony point is padded and a return electrode pad is applied. The prep and drape are as for a hemorrhoidectomy.
Setup: the hemorrhoidectomy setup plus two skin hooks and two sharp Senn retractors.
Key steps: a curved incision around half of the anus, over the torn part. The scarred ends of the muscle are freed, keeping the scar, which holds stitches better than muscle alone, and then sewn together, overlapped when there is enough length. The perinealper-ih-NEE-ulHaving to do with the perineum, the area between the genitals and the anus.Full entry body may be rebuilt, and the skin is closed loosely or left partly open to drain. A colostomykuh-LOS-tuh-meeA surgical opening that brings part of the colon through the belly wall, so stool leaves the body into a pouch.col/o colon-stomy surgical openingFull entry may divert the stool while a large repair heals.
After surgery: results tend to fade with time, and in one series full continence returned in only about half of patients.
16Pediatric general surgery
Chapter 13 covers a child's temperature, fluids and airway, and chapter 18 their care as people. Two operations on young infants are taught here: pyloromyotomy and omphalocele repair. You may also meet anal atresia (imperforate anus), in which the normal anal opening is missing or closed at birth; it ranges from low to high lesionLEE-zhunAn area of tissue that has been damaged or has changed from normal, such as a sore, wound, lump or spot.Full entry , and the repair closes any fistulaFIS-choo-luhAn abnormal passage between two organs or vessels, or between an organ and the skin.Full entry and brings the rectum through the external anal sphincterSFINGK-terA ring of muscle that tightens to close an opening or passage in the body and relaxes to open it.Full entry .
Pyloromyotomy
What and why: in infantile pyloric stenosispy-LOR-ik steh-NOH-sisA narrowing of the outlet of the stomach in a young infant, caused by thickening of the pylorus muscle.pylor/o pylorussten/o narrow-osis conditionFull entry , the muscle of the pylorus thickens and narrows the outlet of the stomach. It is the most common cause of a blocked stomach outlet in children and the most common condition needing surgery in the newborn. Signs start at 2 to 6 weeks of age: forceful (projectile) vomiting without bilebileA yellow-green fluid made by the liver and stored in the gallbladder that helps digest fats.chol/e bileFull entry after feeds, poor weight gain, and dehydration with a loss of chlorideKLOR-ideA negatively charged mineral (electrolyte) in the blood that works with sodium to keep fluid and acid-base balance.Full entry and potassium (hypochloremiahy-poh-klor-EE-mee-uhA blood chloride level below normal, under 98 mEq/L.hypo- belowchlor chloride-emia in the bloodFull entry , hypokalemiahy-poh-kuh-LEE-mee-uhA blood potassium level below normal, under 3.5 mEq/L.hypo- belowkal potassium (from its Latin name, kalium)-emia in the bloodFull entry metabolic alkalosismet-uh-BOL-ik al-kuh-LOH-sisAn acid-base imbalance in which the blood holds too much bicarbonate, so its pH rises above 7.45.alkal base (the opposite of acid)-osis conditionFull entry ). It is about four times more common in boys. A pyloromyotomy splits the thickened muscle and leaves the lining (mucosamyoo-KOH-suhThe moist lining of body passages that open to the outside, such as the mouth, nose, gut and bladder.Full entry ) intact; the laparoscopiclap-uh-roh-SKOP-ikDone through a few small cuts in the abdomen with a thin camera and long instruments, instead of one large opening.lapar/o abdomen-scopic viewingFull entry operation has replaced the open one as the standard.
the open pyloromyotomy is still taught as an option, and some facilities still do it.
Diagnosis and preparation: the physical exam or imaging confirms it, and fluid and electrolyte problems are corrected before surgery. The stomach is emptied just before inductionin-DUK-shunThe starting of a process on purpose, such as bringing on labor or putting a client under anesthesia.Full entry and the nasogastric tubenay-zoh-GAS-trik toobA thin, flexible tube passed through the nose and down the esophagus into the stomach.nas/o nosegastr/o stomach-ic having to do withFull entry removed.
Position, prep and drape: supine but turned across the table, so the surgeon works from the feet and the anesthesia provideran-us-THEE-zhuh pruh-VY-derThe licensed professional who gives anesthesia and watches over the client's breathing and vital functions during a procedure.Full entry keeps the airway; a small roll may lift the pylorus, and the monitor goes above the head. The chest and abdomen are prepped with povidone-iodinePOH-vih-done EYE-uh-dineA brown antiseptic solution of iodine used to kill germs on the skin before procedures and on wounds.Full entry and draped for a laparotomylap-uh-ROT-uh-meeSurgery that opens the abdomen through a large cut to reach the organs inside.lapar/o abdomen-tomy cutting intoFull entry .
Setup: a 3 or 5 mm trocarTROH-karA sharp or bladed instrument inside a tube (cannula), used to pierce a body wall and leave the tube in place as a port.Full entry , 3 mm laparoscopic instruments, a pyloric grasper, a pyloric spreader, a small knife and blunt graspers.
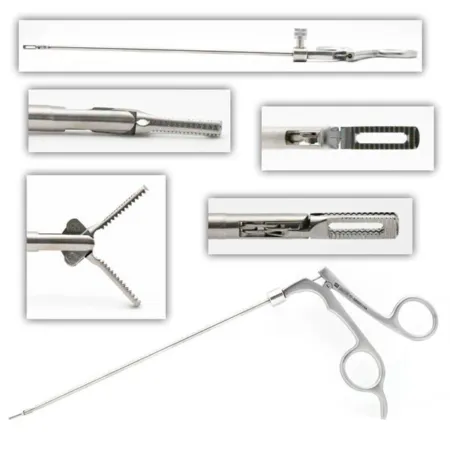
Medications: local anestheticLOH-kul an-es-THET-ikA drug that blocks feeling in one part of the body without making the person unconscious.Full entry is injected at the trocar sites.
Key steps:
- A trocar goes in at the umbilicus, and the abdomen is inflated to no more than 10 mm Hg.
- Two stab incisions take the instruments, and the grasper steadies the pylorus.
- The muscle is cut along the pylorus from the stomach end to the duodenumdoo-uh-DEE-numThe first, short part of the small intestine, just after the stomach.Full entry end, with the electrosurgeryee-LEK-troh-SUR-jer-eeUsing high-frequency electric current through a handheld tool to cut tissue or seal bleeding vessels during surgery.Full entry or a small blade.
- The spreader widens the cut until the mucosa shows.
- Air is pushed into the stomach through an orogastric tube; bubbles at the cut would mean the mucosa is torn.
- The fasciaFASH-ee-uhA sheet or band of tough connective tissue that covers and separates muscles and organs.fasci/o bandFull entry at the umbilicus is closed to prevent a herniaHER-nee-uhA bulge of an organ or tissue through a weak spot in the muscle or tissue wall that normally holds it in.Full entry , and the skin gets strips or glue.
Wound class: I while the mucosa stays intact, because the lumenLOO-menThe open space inside a tube, such as a blood vessel, the intestine or a catheter.Full entry is not entered.
Omphalocele repair
What and why: in an omphalocele, the abdominal organs develop outside the body, inside a sac of peritoneumpair-ih-toh-NEE-umThe thin membrane that lines the belly cavity and covers most of the organs inside it.peri- aroundton stretched-eum a structureFull entry and amnion at the base of the umbilical cord, with no skin over it. It ranges from a few loops of bowel to a giant sac holding the liver and spleenspleenAn organ in the upper left abdomen that filters the blood and helps fight infection.splen/o spleenFull entry , through a defect of 2 to 15 cm. About 30 percent of these babies have a chromosomeKROH-muh-sohmA thread-like structure in the nucleus of a cell that carries the genes, made of tightly packed DNA.chrom/o color-some body (they take up colored stains easily)Full entry disorder (trisomyTRY-soh-meeHaving three copies of a chromosome instead of the usual two.tri- three-some body (chromosome)Full entry 13, 18 or 21), and heart, bone and muscle, and urinary defects are also linked to it. Gastroschisis is different: the opening is to the right of the cord, and no sac covers the bowel.
Before surgery: IV fluids, antibiotics and an NG tube; surgery prevents rupture of the sac and infection. The sac is covered with moist sponges or plastic wrap until the operation, and a ruptured sac makes it an emergency. The exposed surface loses heat fast, so warming is a priority. Nitrous oxide is avoided, because gas in the bowel makes it harder to fit back inside, and the rectum may be irrigationeer-ih-GAY-shunWashing out a wound, body cavity, tube or eye with a steady flow of liquid.Full entry with warm saline to empty it.
Position, prep and drape: supine; the abdomen, cord and sac are prepped gently with povidone-iodine, a urinary catheter is placed, and great care is taken not to break the sac; a laparotomy set and drape.
Primary closure: for a small defect (under about 2 cm), soon after birth. The sac is removed from the skin edge and the umbilical vessels are tied. The skin is freed on both sides to make room, the organs are returned, and the fascia is closed, bridged with mesh or biologic material if needed; a purse-string stitch may close the skin.
Staged closure: for a large or ruptured omphalocele, a silo of Silastic sheeting is sewn to the edge of the defect and hung above the baby. Over days to weeks in the NICU, gravity and daily tightening ease the organs back inside, watching that the tighter abdomen does not hamper breathing. The abdominal wall is then closed in the OR; if everything cannot go back, only the skin is closed, and the hernia that results is repaired later in childhood.
Wound class: the class follows what the surgeon finds; an intact sac with no bowel opened, closed at the same operation, meets the definition of Class I.
What to take from this chapter
- General surgery has the largest case requirement of any specialty. Learn the open abdomen once, with the fascia holding the closure, and every case becomes a new middle; flexible endoscopy through a natural opening often confirms the disease first.
- Laparoscopy starts with a Veress needle, an open Hasson entry or an optical trocar. In a laparoscopic cholecystectomy, nothing is clipped or cut until the critical view of safety shows only the cystic duct and artery entering the gallbladder.
- Babcocks and noncrushing clamps protect bowel that stays. Bowel technique starts when the GI tract is opened and ends when it is closed: dirty stays dirty, then fresh gloves (often gowns), drapes, tips and instruments for a clean closure. Circular stapler donuts must be complete rings.
- Groin hernias: indirect lateral to the inferior epigastric vessels, direct medial to them through the Hesselbach triangle, and femoral below the inguinal ligament, the most likely to strangulate. A hiatal hernia is closed and wrapped over an esophageal dilator that the anesthesia provider passes from a nonsterile table.
- Morbid obesity is a BMI of 40 or more. Before a band, sleeve or bypass, check the bed's weight rating, have an anti-skid or vacuum positioner and padded straps, and open long instruments.
- The liver, spleen and pancreas bleed: have hemostatic agents, blood and a cell saver ready, count every lap placed under the diaphragm, and remember that splenectomy patients need vaccines.
- Breast and neck: breast tissue goes oriented and fast, and each sentinel node gets its own container. A thyroidectomy is now often video-assisted (MIVAT) through a small incision, with the open set ready; the surgeon guards the recurrent laryngeal nerves and the parathyroids, and a removed parathyroid stays in saline until the hormone drop confirms it.
- Anorectal cases are done in prone jackknife, lithotomy or lateral position, and a seton keeps a fistula draining. A pyloromyotomy splits the pyloric muscle and leaves the mucosa intact; a large omphalocele is closed in stages with a silo.
Check yourself5 quick questions
Free for everyone. Pick an answer for each, then check them all at once.
In the ORWhere you'll use this
The chapter's whole question pool in sets of 10, with the answer explained after each one.
Part of the educators programThe chapter's words on spaced cards: the ones you miss come back sooner.
Part of the educators programGiven by your class's teacher. Each class draws its own 25 from the chapter's pool.
Part of the educators program
Suggest a fix
Something wrong, unclear or out of date in this chapter? Tell us and we will fix it for everyone. Your email is only used to reply.